Procedures

Cystic Acne Scar Treatment Options for Deep Tethered Scars
 October 5, 2026 |
 Author
Cystic acne does its damage underneath the surface. The lesion forms deep in the skin, and when the inflammation finally calms, what remains is often not a flat mark but a structural dent held in place by fibrous tissue. That tethering is why a scar looks deeper when you smile or lift your brows. It is also why the treatment options for cystic acne scars are not the same as the options for simple post-acne redness.
Picking a plan is not about choosing the most aggressive procedure available. It is about matching the depth and number of scars you have to a technique that can actually reach them, then protecting the result while new collagen settles in.
What Makes a Cystic Acne Scar Tethered
Acne scars are the marks left behind after acne clears, and they can be treated with chemical peels, skin needling, laser, and other procedures. What changes from patient to patient is how deep the problem runs and how many scars are involved.
When a cyst heals, the skin can pull downward and attach to the tissue beneath it instead of sitting flat. The scar stays anchored, which is why it tends to look like a rolling or pitted depression rather than a spot. Because the problem is partly mechanical, a product that only exfoliates the surface will not release that tether. The scar needs a treatment that either rebuilds collagen in the deeper layers or interrupts the tension holding it down.
That distinction is the single most useful thing to understand before you compare clinics or devices. Two scars that look similar in a mirror can sit at completely different depths, and depth determines which tools are worth your time.
Why Scar Count and Depth Change the Plan
Severity drives everything. Mild scarring, meaning fewer than 10 visible scars with minimal depth, may respond well to less aggressive treatments such as superficial chemical peels. Deeper and more numerous scars generally need approaches that reach below the epidermis, where collagen remodeling actually happens.
| Scar pattern | Typical starting point |
|---|---|
| Mild scarring: fewer than 10 visible scars, minimal depth | Less aggressive options such as superficial chemical peels |
| Deeper or tethered scarring | Resurfacing approaches that reach deeper layers, including microneedling radiofrequency and laser skin resurfacing |
| Active cystic acne alongside existing scars | Medical control first, using topical treatments, oral medications for inflammation or hormone levels, and short-term anti-inflammatory care |
Notice that the third row is not really a scar treatment at all. It is acne treatment. If cysts are still forming, every new lesion is a chance for another tethered scar, so controlling the disease comes before chasing the damage it already caused.
Professional Treatment Options for Deep, Tethered Scars
In-office options overlap, and most real treatment plans combine more than one. The sections below cover the categories that come up most often in acne scar care.
Microneedling Radiofrequency
Microneedling radiofrequency, often shortened to MNRF, is one of the well-known acne scar treatment solutions. Fine needles create controlled channels in the skin while radiofrequency energy is delivered below the surface, where collagen remodeling takes place. Because the energy is deposited under the skin rather than dragged across the top, MNRF can work on scars that sit deeper than a peel is able to reach.
Morpheus8 is discussed alongside chemical peels and lasers in current acne scar treatment literature, and it falls into this same resurfacing family. If you have heard the name and wondered how it fits, the short answer is that it belongs to the energy-based group, not the topical group.
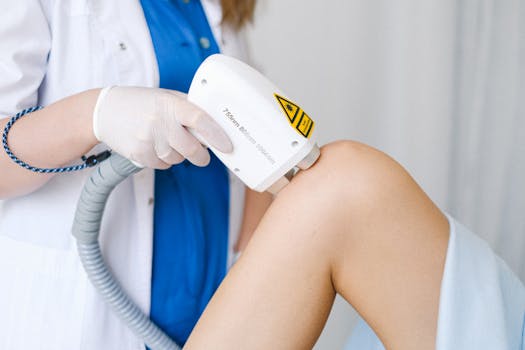
Laser Skin Resurfacing
Laser skin resurfacing removes damaged skin layers and boosts collagen in deeper layers, which reduces the visibility of scars. For tethered scarring, the collagen response matters as much as the surface removal. The goal is to rebuild support under the scar so it settles closer to the level of the surrounding skin rather than sitting in a fixed depression.
Laser treatment is also useful when texture and pigment are both part of the complaint, since a single resurfacing plan can often address both rather than sending you through two separate treatment tracks.
Chemical Peels
Chemical peels are tailored to the concern being treated. Superficial peels are a reasonable starting point for mild scarring with minimal depth. For deep, tethered scars, a peel is better understood as one component of a plan than a standalone fix, useful for tone, texture, and pigmentation while a deeper treatment addresses the structural component.
This is where a lot of disappointment happens. Someone buys a package of peels expecting the depressions to fill in, and the depressions do not change because nothing in the treatment reached them. Matching the tool to the depth is the whole job.
Combining Procedures
Because a tethered scar has more than one component, plans often stack. A series of microneedling radiofrequency sessions might be scheduled with peels in between, or laser resurfacing might be reserved for specific areas while a broader resurfacing approach handles overall texture. The sequencing matters as much as the menu, and it is usually spread over multiple visits rather than completed in one appointment.
Control Active Cystic Acne First
New cysts create new scars, so a scar plan that ignores ongoing acne tends to lose ground. A treatment plan may include a retinoid on its own; a retinoid combined with benzoyl peroxide, azelaic acid, or salicylic acid; or benzoyl peroxide paired with another topical active.
Topical treatments work to reduce oil production and bacteria. Oral medications help control inflammation or hormone levels, which matters for cystic acne because inflammation is what drives the deep damage in the first place. Short-term anti-inflammatory care can also be part of the picture during a flare. Your dermatologist will match the combination to your skin, your history, and how well you tolerate each active.

What You Can Do at Home Between Visits
Home care supports professional treatment, though it does not replace it for tethered scars. Vitamin C serums can be a good option for treating acne scars at home, and aloe vera is another commonly used ingredient. Sunscreen belongs in the routine as well, because unprotected exposure works against the skin you are trying to rebuild.
Think of these products as protecting your investment. They can improve tone, hydration, and overall appearance while procedures do the structural work. They will not release a tether, and no topical product will lift a scar floor that is anchored to deeper tissue.
How Colorado Dermatology Center Approaches Scar Revision
Colorado Dermatology Center is a South Denver dermatology practice led by board-certified dermatologist Dr. James M. Swinehart. The practice covers medical, surgical, and cosmetic dermatology, with acne scar repair among its focus areas alongside skin cancer treatment, hair restoration, tumescent liposuction, and clinical research trials.
That breadth is relevant for scar patients. Acne scarring is rarely a single problem, because active breakouts, pigment change, and deep structural scars often show up together. A practice that manages medical acne and procedural scar revision under one roof can sequence those pieces instead of sending you between providers who never compare notes. The practice is also known for offering procedures that many others do not, with an emphasis on personalized care and natural-looking results.

Questions to Bring to a Consultation
A scar consultation is more productive when you arrive with specifics. These are the questions that tend to shape a plan.
- Which of my scars are tethered, and which are surface-level texture or pigment?
- Which procedure actually reaches the depth of my deepest scars?
- How will my active acne be controlled while we work on scarring?
- What is the realistic sequence of treatments, and how many visits does it involve?
- What does recovery look like between sessions, and what should I do at home?
Ask for a realistic picture rather than a promise. Deep, tethered scars can improve meaningfully, but improvement is the honest word. A plan built around your actual scar pattern will always outperform a package sold without looking at your skin.
Frequently Asked Questions
Do deep cystic acne scars go away on their own?
Flat marks left after acne can fade over time, but tethered scars are structural and generally do not resolve without treatment. The tissue is anchored below the surface, so there is nothing for the skin to remodel on its own. Options such as microneedling radiofrequency, laser resurfacing, and chemical peels are used to improve them, and results build over a series rather than a single visit.
Can I treat tethered cystic acne scars at home?
At-home products can support tone and texture, and options like vitamin C serums and aloe vera are commonly used for acne scars at home. They cannot release a tether anchored in deeper tissue. Think of home care as maintenance around professional treatment, not a substitute, especially when scars are deep or numerous.
Should I treat active cystic acne and scarring at the same time?
Usually the acne gets controlled first, or at least concurrently, because new cysts create new scars. A plan may include a retinoid, a retinoid with benzoyl peroxide, azelaic acid, or salicylic acid, or oral medications that help with inflammation or hormone levels. Your dermatologist will decide what can safely run alongside scar procedures.
How many treatments will deep acne scars need?
It depends on scar depth, scar count, and which procedures are combined. Mild scarring with fewer than 10 visible scars and minimal depth may respond to less aggressive options like superficial chemical peels, while deeper tethered scarring typically needs a series of resurfacing sessions. Ask your dermatologist for a realistic sequence rather than a fixed number before your skin has been evaluated.
Which is better, laser resurfacing or microneedling radiofrequency?
Neither is universally better, and the choice depends on your scarring and skin. Laser skin resurfacing removes damaged surface layers and boosts collagen in deeper layers, while microneedling radiofrequency delivers energy below the surface through fine needles. Both are used for acne scarring, and many plans combine categories rather than choosing one exclusively.
If your scars are deep and tethered, the most valuable next step is an evaluation that identifies which scars are structural and which are not. That assessment is what turns a list of procedures into an actual plan, and it is the difference between spending money on treatments that suit your skin and spending it on treatments that suit someone else’s.
 Posted in

Squamous Cell Carcinoma on the Ear: Treatment Options
Skin cancer on the ear is common, and the reason comes down to anatomy and sunlight. The skin covering the outer ear spends more time in direct ultraviolet light than almost any other part of the body, and that exposure accumulates over decades. Squamous cell carcinoma is one of the skin cancers that develops in this location, and because the ear is small, cartilage-based, and sits next to a narrow canal, treatment decisions here carry more weight than they would on a shoulder or a back.
Most cases of ear skin cancer are easily treated, but the same cancer can spread to other parts of the body if it is left untreated. That combination, straightforward treatment when the tumor is small and real risk when it is not, is why the timing of care matters as much as the choice of procedure.
Why the Ear Is Considered a High-Risk Location
The skin on your outer ear is susceptible to cancer because it is often exposed to the sun’s damaging UV rays. That exposure is relentless, since the rims and the tops of the ears catch light from above at nearly every hour of the day, and many people never think to apply sunscreen there.
Ear cancer can develop in any part of the ear. It often starts on the outside of the ear as a skin cancer, and it can also form inside the ear canal. Cancers of the ear canal are rare and can be hard to diagnose because of their location, but they are generally curable if caught early enough.
Dermatologists and head and neck surgeons treat these tumors as a distinct group because the ear is an anatomically complex area. Skin there is thin, it sits directly over cartilage, and the canal is a tight space that is difficult to examine without the right equipment. Each of those features affects which treatment approach makes the most sense.
Signs and Symptoms That Deserve a Closer Look
Symptoms include changes to your skin, such as discoloration. Not every change on an ear turns out to be cancer, but a persistent one is worth having examined rather than watched at home. Points to raise with a clinician include:
- Any discoloration or other visible change in the skin of the outer ear
- A spot or lesion that persists instead of resolving on its own
- Any change involving the ear canal, which is hard to see on your own
Because tumors inside the canal can be difficult to diagnose from the outside, a symptom that seems minor may still need an in-office examination to be sorted out.
Treatment Options for Squamous Cell Carcinoma of the Ear
The main treatments for cancer of the outer ear are surgery and radiotherapy. Beyond surgery, other options for removal of skin cancer on the ear include chemotherapy, cryotherapy, immunotherapy, and photodynamic therapy. For more advanced-stage tumors, treatment often requires a combination of surgery, chemotherapy, and radiation therapy, and immunotherapy is now used as a first-line approach in some situations.
| Approach | Where it fits |
|---|---|
| Mohs micrographic surgery | Often preferred for high-risk sites such as the lips and ears; removes cancer cells layer by layer while preserving normal skin and cartilage |
| Surgery with or without post-operative radiotherapy | Forms the mainstay of treatment for squamous cell carcinoma of the external auditory canal and temporal bone |
| Sleeve resection | Usually recommended for growths located closer to the opening of the affected ear; removes the skin of the ear canal |
| Radiotherapy | One of the two main treatments for cancer of the outer ear, and used after surgery in some cases |
| Immunotherapy | Used in more advanced disease; pembrolizumab has been studied for recurrent or metastatic squamous cell carcinoma |
| Chemotherapy, cryotherapy, photodynamic therapy | Additional non-surgical options for skin cancer on the ear |
Mohs Micrographic Surgery for Ear Tumors
For high-risk areas such as the lips and the ears, Mohs surgery is often the preferred method. The technique removes cancer cells layer by layer, with each layer examined under the microscope before the surgeon decides whether more tissue needs to come out. That step-by-step confirmation is what separates it from a standard excision, where the margin is checked only after the tissue is closed.
Published research supports its role in this location. A case series described 170 cases of squamous cell carcinoma of the external ear treated with Mohs surgery, and the same literature has examined pembrolizumab for recurrent or metastatic squamous cell carcinoma of the ear.
Why Tissue Preservation Matters on the Ear
Mohs micrographic surgery is the preferred treatment in many cases because it removes the cancer while preserving as much normal skin and cartilage as possible. On an ear, that margin for error is narrow. Cartilage gives the ear its shape, and thin skin over that cartilage does not leave much room for a wide surgical defect. Preserving tissue can mean a simpler reconstruction and a result that looks closer to the original ear.
When the Tumor Involves the Ear Canal or Temporal Bone
Surgery with or without post-operative radiotherapy forms the mainstay of treatment for squamous cell carcinoma of the external auditory canal and temporal bone. These tumors behave differently from surface lesions on the rim or lobe, and the surgical plan reflects the anatomy around them.
For growths located closer to the opening of the affected ear, a sleeve resection, which removes the skin of the ear canal, is usually recommended. The goal is to clear the tumor while leaving as much function and structure intact as the location allows.
When Advanced Disease Changes the Plan
More advanced-stage tumors often require a combination of surgery, chemotherapy, and radiation therapy. Immunotherapy is now used as a first-line treatment in some advanced cases, and pembrolizumab has been studied specifically for recurrent or metastatic squamous cell carcinoma. These decisions are typically made by a team rather than a single specialist, and the sequence of treatments can change as the disease responds.
When to Act on a Suspicious Spot on the Ear
If you notice a change in the skin of your ear, an evaluation is the sensible next step rather than a wait-and-see approach. Most cases of ear skin cancer are easily treated, and cancers of the ear canal are generally curable if caught early enough. The same cancer can spread to other parts of the body if untreated, which is the practical argument against monitoring it at home for months.
There is no single answer to how long someone can safely wait before treatment. That timeline depends on the type, size, and depth of the tumor, whether nearby lymph nodes are involved, and other individual factors, so it is a question for your dermatologist rather than a general rule you can apply to yourself. The general principle that the research supports is simpler: earlier diagnosis widens the options and usually makes the treatment smaller.
Questions Worth Asking at Your Appointment
- Is this squamous cell carcinoma, and how was that determined?
- Is Mohs surgery appropriate for my tumor, or would another approach work better?
- Does the tumor involve the ear canal or the temporal bone?
- Would radiation, immunotherapy, or another treatment play a role in my case?
- What signs would mean the tumor is changing and needs faster attention?
Frequently Asked Questions
Is squamous cell carcinoma on the ear considered high risk?
Yes. The ears are treated as a high-risk area for skin cancer, alongside sites such as the lips, and that classification shapes treatment planning. For high-risk areas like these, Mohs surgery is often the preferred method because it removes cancer cells layer by layer while preserving as much normal skin and cartilage as possible. Your dermatologist can confirm whether your tumor fits that profile.
Can squamous cell carcinoma on the ear be treated without surgery?
Surgery is the mainstay for most tumors of the outer ear, where the two main treatments are surgery and radiotherapy. Beyond surgery, options include chemotherapy, cryotherapy, immunotherapy, and photodynamic therapy. Which approach fits a specific tumor depends on its size, depth, location, and whether it has spread, so the plan is made case by case rather than by a single standard.
How is a tumor inside the ear canal treated?
Cancers of the ear canal are rare and can be hard to diagnose because of their location, but they are generally curable if caught early enough. When a growth sits closer to the opening of the affected ear, a sleeve resection, which removes the skin of the ear canal, is usually recommended. For the external auditory canal and temporal bone, surgery with or without post-operative radiotherapy forms the mainstay of treatment.
What happens if squamous cell carcinoma on the ear is not treated?
Most cases of ear skin cancer are easily treated, but the same cancer can spread to other parts of the body if it is left untreated. That is the core reason a persistent change on the ear deserves examination rather than indefinite monitoring at home. Prompt evaluation keeps the treatment options broader and, in most cases, the procedure smaller.
Does Mohs surgery work for squamous cell carcinoma of the ear?
Mohs surgery is widely used for squamous cell carcinoma of the external ear, and one published case series described 170 cases treated with this technique. It is often preferred on the ear because it removes the cancer while preserving as much normal skin and cartilage as possible, which matters for both reconstruction and appearance. Your dermatologist can say whether your specific tumor is suited to it.
Annual Skin Cancer Screening: Who Needs One and When to Start
Skin cancer screening is unusual among cancer checks because it starts with your own eyes and ends with a short visit to a clinician. The harder question is scheduling. Some people are advised to book a full-body exam every year, some every six months, and some can reasonably stretch the interval to two or three years. Which group you fall into depends less on your calendar and more on your personal risk.
What Happens During a Full-Body Skin Exam
Most full-body skin screenings take as little as 10 to 15 minutes to complete. You will be asked to remove your clothes and change into a medical gown before the exam begins. A clinician then works across your skin in a systematic way, checking the scalp, back, arms, legs, and other areas that are difficult to see in a mirror.
Less visible areas deserve the same attention. The CDC advises checking parts of the skin that rarely see daylight, such as the soles of your feet, and telling your doctor about any unusual moles or changes you have noticed. Those changes are often the reason a particular spot gets a closer look in the first place.
Why Regular Screening Matters
Approximately 1 in 5 Americans will develop some form of skin cancer by age 70, yet only 8 percent of patients who recently saw a primary care provider received a skin examination during that visit. That gap is part of why dedicated skin checks exist. A primary care appointment covers a lot of ground, and a full-body skin exam is easy to skip when time is tight.
An annual skin exam performed by a board-certified dermatologist ensures that suspicious spots are detected and addressed before they progress. Timing is the variable that matters most in skin cancer care, and a scheduled exam puts a firm date on the calendar instead of waiting for a spot to become obvious on its own.
Who Needs an Annual Skin Cancer Screening
Harvard Health’s guidance is direct: most people are at low risk of melanoma and do not need annual skin cancer screenings. People should be screened annually if they have risk factors that raise their likelihood of developing the disease.
Other dermatology practices describe the same split from the opposite direction. In that framing, experts recommend annual skin cancer screening for most adults, and personal risk factors can substantially change the recommended schedule. People in higher-risk categories are often advised to come in every six months rather than once a year.
The short version looks like this. Annual screening is the default for people with meaningful risk factors, a six-month interval is common for higher-risk patients, and a longer gap can be reasonable for people with low risk. Because the sources do not agree on a single universal rule, your individual history is what settles the question.
When to Start Screening
The guidance reviewed here does not set one age at which everyone should begin annual skin cancer screening. It ties the start of screening to risk instead, which means the practical starting point is a conversation rather than a birthday.
If you have never had a professional skin exam, a reasonable next step is to ask a dermatologist what interval fits your history. Bring whatever you already know about your own skin, including spots that have changed, and let that information shape the plan. Anyone with a strong reason for concern should not wait for a specific age to arrive before asking.
Screening Frequency: How the Guidance Compares
Different organizations emphasize different parts of the same picture. The table below summarizes what each source recommends, so you can see where the advice overlaps and where it diverges.
| Source | Screening guidance |
|---|---|
| Skin Cancer Foundation | See a dermatologist once a year, or more often if you are at higher risk, for a full-body professional skin exam. |
| Harvard Health | Most people at low risk of melanoma do not need annual screenings. Annual screening is advised for people with risk factors. |
| Dermatology practice guidance | Annual screening for most adults, every six months for higher-risk categories, and two to three years may be sufficient for about 80 percent of people. |
| U.S. Preventive Services Task Force | Inadequate evidence that clinician visual skin examination reduces morbidity or mortality. |
| Memorial Sloan Kettering | Check your own skin regularly, every month, for spots or moles that are new or changing. |
What the Evidence Says About Screening Programs
Not every medical body agrees that routine visual screening changes outcomes across an entire population. The U.S. Preventive Services Task Force found inadequate evidence that screening for skin cancer through visual skin examination by a clinician reduces morbidity or mortality. That finding concerns evidence at the population level, not whether a single exam can turn up a suspicious spot.
Two things can be true at once. A clinician exam can identify a lesion worth evaluating, and the evidence base for mass screening programs can remain unsettled. If you want the current recommendation in full, including any updates since it was issued, read the task force statement directly rather than relying on a summary.
How to Prepare for Your Appointment
Preparation makes a short exam more productive. The Skin Cancer Foundation’s guidance for annual exams puts self-examination first, so come to the appointment ready to point out specific areas of concern.
- Perform a self-exam before your visit so you know what you want to ask about.
- Bring notes about any new, changing, or unusual spots you want your dermatologist to look at.
- Bring smartphone photos of a spot that has changed, since a photo can show a shift that is hard to describe.
It also helps to mention anything you have noticed but dismissed, including a spot on the soles of your feet or another area you rarely inspect. Those details guide where the clinician spends time.
Monthly Self-Exams Between Visits
Memorial Sloan Kettering recommends checking your own skin regularly, every month. This is called a skin self-exam, and the goal is to notice skin spots or moles that are new or changing.
A self-exam does not replace a professional full-body exam, and it is not a diagnosis. What it does is teach you what is normal for your own body, which makes it easier to report something different at your next appointment. Pair the monthly habit with the CDC reminder to check less visible areas like the soles of your feet.
Where to Get Screened in South Denver
Colorado Dermatology Center is a South Denver dermatology practice led by board-certified dermatologist Dr. James M. Swinehart, whose clinical experience spans more than three decades. The practice focuses on medical, surgical, and cosmetic dermatology, with particular emphasis on skin cancer treatment including MOHS micrographic surgery, a technique used to remove certain skin cancers while preserving as much healthy tissue as possible.
If you are unsure whether you need an annual exam, checks every six months, or a longer interval, that question is worth asking at a consultation. Bring your notes and photos, share any family history or past sun exposure concerns you have, and let the exam findings and your personal history guide the schedule you follow from there.
Frequently Asked Questions
How long does a full-body skin exam take?
Most full-body skin screenings take as little as 10 to 15 minutes to complete. You will be asked to remove your clothes and change into a medical gown before the exam begins. Because the visit is short, arriving with notes about the spots you want checked helps the clinician focus on what matters most to you.
Do most people need an annual skin cancer screening?
It depends on risk. Harvard Health notes that most people are at low risk of melanoma and do not need annual screenings, while people with risk factors should be screened annually. Other dermatology guidance recommends annual exams for most adults, with higher-risk patients often checked every six months. Ask your dermatologist which interval fits your history.
Should I check my own skin between professional exams?
Yes. Memorial Sloan Kettering recommends checking your own skin regularly, every month. A skin self-exam means looking for spots or moles that are new or changing. It does not replace a professional full-body exam, but it helps you learn what is normal for your skin so you can report anything different at your next visit.
What should I bring to a skin cancer screening?
Come with notes about any new, changing, or unusual spots you want your dermatologist to examine. If you have taken smartphone photos of a spot that has changed over time, bring those as well. Preparation guidance recommends this self-exam-first approach so the appointment centers on the areas that concern you most.
How often should higher-risk patients be screened?
Dermatologists often recommend screening every six months for people in higher-risk categories. For lower-risk patients, one source suggests two to three years may be sufficient for about 80 percent of people. Because the right interval depends on your personal risk factors, confirm your schedule with your dermatologist rather than relying on a general rule.
Psoriasis Treatment in Denver: From Topicals to Biologics
Psoriasis is a chronic, inflammatory autoimmune disease. The immune system becomes overactive and speeds up the production of new skin cells, so those cells build up on the surface instead of shedding at a normal rate. The result is the redness, scaling, and raised patches that define the condition for millions of Americans.
Because psoriasis behaves differently from person to person, treatment in Denver is rarely a single prescription. It is usually a layered plan that starts with what you apply to your skin, adds light-based therapy when more surface area is involved, and moves toward systemic or biologic medication when the disease is moderate to severe. Understanding how those layers fit together makes it easier to have a productive conversation with a dermatologist.
What Psoriasis Actually Is
In healthy skin, new cells are formed at approximately the same rate that old cells are shed. In psoriasis, that balance breaks down. New cells develop far more rapidly, accumulate at the surface, and create the lesions people recognize as psoriasis.
Several types of psoriasis exist, and each one shows up differently. Lesions may appear as red, scaly, thickened plaques, or as pustules. Common locations include the elbows, knees, and scalp, but the condition can also affect the fingernails and toenails, the soft tissues of the genitals, and the inside of the mouth.
The precise triggers for psoriasis are not fully understood, which is one reason treatment focuses on controlling symptoms and slowing the underlying cell turnover rather than on eliminating a single known cause. That framing matters: psoriasis is managed, not cured, and the goal of care is fewer flares, less discomfort, and clearer skin over the long term.
The Treatment Ladder, Explained
Denver dermatologists generally work from the least invasive option upward, matching the intensity of treatment to how much skin is involved and how much the condition interferes with daily life. The three broad categories below cover most of what patients encounter.
Topical Therapy: Where Most Plans Begin
Topicals are medications applied directly to the affected skin. They are the standard first step for mild to moderate psoriasis, and corticosteroids are the most frequently prescribed medications in this category. They reduce inflammation and help calm the redness and scaling that come with an active flare.
Vitamin D analogues make up a second common topical group. These are often used to help slow the excessive cell growth that drives plaque formation, and they may be prescribed alongside a corticosteroid or used in rotation depending on how the skin responds.
Topical treatment works best with consistency. Applied as directed, these medications can keep limited psoriasis under good control, but they are not designed to manage widespread disease on their own. If plaques cover large areas or keep returning after each course, that is a signal to discuss stronger options rather than simply using more of the same product.
Phototherapy and UVB Light
UVB light therapy involves exposing the skin to controlled ultraviolet B light in a clinical setting. The purpose is to decelerate the excessive cell growth that produces psoriatic plaques, and it is listed among the psoriasis treatments offered by Denver-area practices.
Phototherapy is typically delivered in a series of sessions rather than as a one-time treatment, which means it asks for a real time commitment. It also requires medical supervision, because the dose of ultraviolet light has to be calibrated and adjusted as the skin responds. Session schedules, insurance coverage, and the number of treatments needed vary by practice and by patient, so those details are worth confirming directly with the clinic before starting.
Systemic and Biologic Therapy for Moderate to Severe Psoriasis
When psoriasis is moderate to severe, or when topicals and phototherapy have not produced adequate control, treatment shifts to medication that works throughout the body rather than only on the surface. Biologic therapies fall into this category. They target specific parts of the immune response that drive psoriatic inflammation.
Some biologic therapies are delivered as infusions in a clinical setting, which is why certain Denver rheumatology practices list advanced biologic infusion therapy specifically for moderate to severe plaque psoriasis. That detail is a useful reminder that psoriasis care is not confined to dermatology offices alone.
Biologic treatment is not a casual step. It usually requires a confirmed diagnosis, a review of your health history, and ongoing monitoring while you are on the medication. The tradeoff is that for people with extensive or stubborn disease, biologics can achieve a level of control that topicals and light therapy cannot reach.
Comparing the Main Treatment Categories
The table below summarizes how the three main approaches differ in what they involve and who they typically serve. It is a general framework, not a substitute for an individual assessment.
| Approach | What it involves | Typically considered for |
|---|---|---|
| Topical therapy | Corticosteroids and vitamin D analogues applied directly to affected skin | Mild to moderate psoriasis |
| Phototherapy (UVB) | Controlled exposure to ultraviolet B light, delivered in repeated clinical sessions | Slowing excessive skin cell growth when a broader area needs treatment |
| Biologic therapy | Immune-targeting medication, in some cases delivered as a clinical infusion | Moderate to severe plaque psoriasis |
Why Your Care Team May Include More Than One Specialist
Psoriasis is an immune-driven condition, and Denver rheumatology clinics treat moderate to severe plaque psoriasis with biologic infusion therapy. That overlap means a patient’s care may involve both a dermatologist and a rheumatology team, particularly when biologic treatment is part of the plan.
If two providers are involved, the most important thing is communication. Each one should know what the other has prescribed, how the skin is responding, and whether any new symptoms have appeared. Coordinated care prevents duplicated efforts and makes it easier to judge whether a treatment is actually working.
Questions Worth Asking at a Denver Psoriasis Consultation
A first appointment moves faster and produces more useful answers when you arrive with specific questions. Consider bringing this list:
- Which type of psoriasis do I have, and how much of my body is affected?
- Is topical therapy a reasonable starting point for my case?
- Would UVB phototherapy help, and how many sessions would that require?
- At what point would systemic or biologic treatment make sense for me?
- What side effects should I watch for, and which ones warrant a call?
- How long should I continue a treatment before deciding whether it is working?
- Do I need to see another specialist as well?
Write down the answers. Psoriasis treatment unfolds over months and years, and having a record of the original plan makes it much easier to tell whether the approach is holding up.
Choosing a Psoriasis Provider in Denver
Denver has no shortage of options. A national physician directory lists 508 doctors in the Denver area who treat psoriasis, which sounds reassuring until you realize how hard it becomes to compare them. Volume alone does not indicate who is the right fit for a chronic skin condition that requires long-term management.
A few filters narrow the field quickly. Look for a board-certified dermatologist, since psoriasis is a medical skin condition and diagnosis drives everything that follows. Ask whether the practice offers phototherapy on site, because a treatment that requires repeated visits is much easier to sustain when it is not spread across multiple locations. Ask how the practice handles biologic therapy and whether coordination with other specialists is part of the process.
Colorado Dermatology Center, led by board-certified dermatologist Dr. James M. Swinehart, combines more than three decades of clinical expertise with medical, surgical, and cosmetic dermatology, along with clinical research. For patients with psoriasis, that combination matters: an accurate diagnosis, a realistic treatment plan, and access to newer options as they become available. Appointments can be scheduled through the practice website at coloderm.com.
What Realistic Management Looks Like
Psoriasis is chronic. That single fact reshapes what success means. The target is not a permanent cure but sustained control, with fewer flares, less itching and scaling, and skin that stays manageable between appointments.
Getting there depends heavily on consistency. Topicals only work when they are actually applied. Phototherapy only works when sessions are kept. Biologics only work when the schedule is followed. It also depends on honest reporting. If a treatment is irritating your skin, or if you have stopped using it because of cost or convenience, say so at your next visit. There is almost always another option, and a plan you can live with beats a perfect plan you abandon.
Frequently Asked Questions
Is psoriasis curable?
No. Psoriasis is a chronic, inflammatory autoimmune disease, and the precise triggers behind it are not fully known. Because there is no single cause to remove, treatment focuses on controlling symptoms and slowing the rapid skin cell production that creates plaques. With the right combination of topicals, phototherapy, or systemic therapy, most people can achieve meaningful and lasting improvement.
What is the most common topical treatment for psoriasis?
Corticosteroids are the most frequently prescribed medications for treating mild to moderate psoriasis. They reduce inflammation and help calm redness, scaling, and itching. Vitamin D analogues are another common topical option and are often used to help slow excessive cell growth. Topical therapy tends to work best for limited disease and requires consistent application to keep results steady.
Why would a rheumatology clinic treat psoriasis?
Psoriasis is driven by an overactive immune system, and Denver rheumatology practices list advanced biologic infusion therapy for moderate to severe plaque psoriasis. Biologics target specific parts of the immune response rather than just the skin surface. Because of that, care for moderate to severe disease can involve both a dermatologist and a rheumatology team working from the same treatment plan.
Can psoriasis affect the nails, scalp, or other areas?
Yes. Psoriasis can appear on the fingernails and toenails, the scalp, and the soft tissues of the genitals and inside the mouth, in addition to the elbows and knees. Lesions may look like red, scaly, thickened plaques or as pustules, depending on the type. Treatment for these areas can differ from what works on the body.
How do I choose a psoriasis doctor in Denver?
Start with board certification in dermatology, since accurate diagnosis drives every treatment decision that follows. Ask whether the practice offers phototherapy on site and how it handles biologic therapy, because repeated visits are easier when care is coordinated. A national directory lists 508 Denver-area doctors who treat psoriasis, so narrowing by credentials and services is more useful than choosing by volume alone.
Deep Wrinkle Treatment vs. Fine Line Care: What Works
Fine lines and deep wrinkles are not the same problem, and they rarely respond to the same fix. A serum that softens the small creases around your eyes can do almost nothing for a fold that stays visible when your face is completely relaxed. The in-office procedures that smooth a deep groove are usually far more than a fine line needs. Knowing which category a line falls into is the first step toward choosing a treatment that actually helps.
What Separates a Fine Line From a Deep Wrinkle
Dermatologists begin by looking at the skin to assess the lines and creases and what may have caused them, according to Mayo Clinic. That evaluation also includes a conversation about your medical history and what matters most to you, because results, side effects, and recovery time all shape the recommendation.
In practical terms, fine lines are shallow creases. They show up most clearly when the skin moves, such as when you smile, squint, or raise your eyebrows, and they tend to respond to approaches that improve surface texture and tone.
Deep wrinkles are deeper creases that remain visible even when the face is at rest. They often sit in areas where the skin has folded the same way for years, and they can be linked to sun exposure, repeated expression patterns, and the natural loss of support beneath the skin. Because the crease goes deeper, treatments aimed only at the surface rarely produce a satisfying change.
Why the Same Wrinkle Treatments Do Not Work Equally
Depth is what determines how much a treatment can accomplish. Products applied to the surface work on texture, tone, and very fine lines. Procedures that create controlled injury below the surface, or that add volume under a crease, can change the shape of a deeper wrinkle in ways a cream cannot.
That difference shows up clearly in expert commentary. Dermatologist Bittar told CNN Underscored that the best and fastest way to get rid of deep wrinkles is through laser or microcoring treatments, pointing specifically to ablative fractional lasers such as CO2. That statement is about deep wrinkles, and it comes with recovery considerations that a superficial treatment does not carry.
A drugstore night cream and a fractionated CO2 laser should not be compared as if they are competing for the same job. They are not. The useful question is whether the line you want to improve is a surface crease or a structural fold.
Treatments That Help Fine Lines
Fine lines are the category where consistent home care and lighter procedures can make a visible difference. Options that dermatologists commonly discuss include:
- Over-the-counter retinol products, which appear throughout dermatologist-recommended skin care lists for softening the look of lines
- Prescription creams and serums, since Mayo Clinic notes a doctor may prescribe an anti-wrinkle product with prescription-strength retinoids
- Chemical peels, which are included in published lists of wrinkle treatments that work and are used at lighter depths to refresh surface texture
- Microdermabrasion, a surface exfoliation option that appears on wrinkle treatment lists
- Red light therapy, also included among wrinkle treatments in dermatology coverage
- Microneedling at lighter depths, since the same treatment can be adjusted for deeper concerns
The thread connecting these options is consistency. Fine lines build slowly, and the treatments that address them generally work gradually rather than overnight.
Deep Wrinkle Treatment Options That Go Below the Surface
When a line stays visible at rest, treatment usually needs to reach deeper or restore support under the skin. Options dermatologists discuss include:
- Injectables. Botox injections are listed by Mayo Clinic among wrinkle treatments and appear in dermatologist treatment roundups. They are typically used for lines created by muscle movement.
- Fillers. Dermal fillers are included in lists of wrinkle treatments that work and are used where a crease or fold needs volume restored beneath it.
- Microneedling. The same treatment that helps fine lines can be performed at greater depth for more established concerns.
- Chemical peels. A medium or deeper peel is a different procedure from a light refresh peel, even though both carry the same name.
- Ablative fractional lasers. CO2 and similar ablative fractional lasers are the option dermatologists cite as the fastest route for deep wrinkles.
- Microcoring. Named alongside lasers as a leading option for deep wrinkles.
- Dermabrasion and laser skin resurfacing. Both appear on published lists of wrinkle treatment options.
Because these treatments change skin at a deeper level, the conversation about recovery time matters as much as the conversation about results. Ask what the days after treatment look like before you commit.
Fine Lines vs. Deep Wrinkles: Treatment Comparison
The table below organizes common options by where they are performed and what they are typically used for. Depth, settings, and your individual skin determine the final plan, so treat this as a starting point rather than a prescription.
| Treatment | Where it is done | Typically used for |
|---|---|---|
| Retinol and prescription retinoids | Home, or by prescription | Fine lines, texture, and early creases |
| Chemical peels | In office, depth varies | Light peels for fine lines, deeper peels for more established wrinkles |
| Microdermabrasion | In office | Surface texture and fine lines |
| Red light therapy | Varies by provider | Fine lines |
| Microneedling | In office | Fine lines at lighter depths, deeper concerns at greater depths |
| Botox injections | In office | Lines created by muscle movement |
| Dermal fillers | In office | Creases and folds that need volume support |
| Ablative fractional laser such as CO2 | In office | Deep wrinkles |
| Microcoring | In office | Deep wrinkles |
| Dermabrasion and laser skin resurfacing | In office | More established lines and wrinkles |
Creams and Serums: What They Can and Cannot Do
Skin care aisles are full of products marketed with phrases like Botox in a bottle. Those products are pain-free and comparatively inexpensive, and dermatologists note they can deliver results when used consistently and as directed. What they cannot do is match a professional treatment. No topical formula creates the same result as an in-office procedure.
That does not make topicals pointless. Retinol and prescription-strength retinoids are legitimate, dermatologist-recognized options for softening the look of lines and supporting skin over time. They simply work on a different level than a laser, a filler, or an injectable. If a topical is part of your plan, expect results to build gradually, and do not expect it to erase a fold that stays put when your face is still.
How a Dermatologist Chooses Between Treatments
The decision is not based on a product category name. Mayo Clinic describes the process as assessing the lines and creases along with what may have caused them, reviewing medical history, and discussing what is important to you. Results, side effects, and recovery time are all part of that conversation.
It also helps to remember that treatment is a choice, not an obligation. As GoodRx notes, some people choose to treat wrinkles while others embrace them as part of aging, and both choices are valid. If you do decide to treat, the goal is a plan that fits your skin, your budget of time, and how much downtime you are willing to accept.
At Colorado Dermatology Center, board-certified dermatologist Dr. James M. Swinehart brings more than three decades of clinical experience to evaluations like these, and the practice emphasizes personalized care and natural-looking results. An in-person assessment is the only reliable way to know whether a given line is best addressed with a topical, an injectable, a filler, or a resurfacing procedure.
Preventing Fine Lines From Becoming Deep Wrinkles
Sun protection is the strongest lever you have. According to GoodRx, daily sun protection is the best way to prevent photoaging and slow new wrinkles from forming, and it is never too late to start using sunscreen. That single habit does more for long-term skin appearance than any individual product purchase.
Beyond sunscreen, the habits that support any treatment plan are consistent use of whatever your dermatologist recommends, realistic expectations about timing, and regular skin checks. Fine lines are easier to influence early than late, but starting today still counts.
Frequently Asked Questions
Do over-the-counter creams really work on deep wrinkles?
They can soften the look of lines and improve texture, especially when they contain retinol or a prescription-strength retinoid. What they cannot do is match a professional procedure. Dermatologists are clear that no topical formula produces the same result as an in-office treatment, so a cream is best viewed as support rather than a fix for a deep fold.
Is Botox or a filler the better choice for deep wrinkles?
They address different problems. Botox injections are used for lines created by muscle movement, while fillers are used where a crease or fold needs volume restored beneath the skin. Many treatment plans combine both, because a deep line often has a movement component and a volume component. A dermatologist can tell you which one fits the line you want to improve.
What is the fastest way to get rid of deep wrinkles?
Dermatologists point to procedures rather than products. One dermatologist told CNN Underscored that the best and fastest route for deep wrinkles is laser or microcoring treatment, specifically ablative fractional lasers such as CO2. These are in-office procedures with real recovery considerations, so the tradeoff for speed is downtime. Discuss timing with your dermatologist before scheduling around work or an event.
How do I know which wrinkle treatment is right for me?
It starts with an evaluation. Mayo Clinic describes the process as assessing the lines and creases and what may have caused them, then reviewing your medical history and what matters to you. Results, side effects, and recovery time all factor into the recommendation. The depth of the line, your skin, and your schedule usually narrow the list quickly.
Can fine lines be prevented from turning into deep wrinkles?
Sun protection is the strongest lever. Daily sunscreen use is the best way to prevent photoaging and slow new wrinkles from forming, according to GoodRx, and it is never too late to begin. Retinoids and consistent skin care help over time as well. None of these habits erase existing deep lines, but they can slow how quickly new ones develop.
Laser Acne Scar Treatment Price: What Denver Patients Pay
Acne scarring has a way of outlasting the breakouts that caused it, and the treatments that smooth it out are rarely inexpensive. Published cost data for laser acne scar removal generally lands between $200 and $3,000 per treatment, and the wider market stretches from $100 to $5,000 or more once scar size, scar count, and the number of laser sessions are factored in. Denver quotes sit inside those national bands rather than outside them, so the useful question is not what the price is in the abstract. It is what a specific number covers, and how many times you will be asked to pay it.
What follows is the published pricing picture, the arithmetic that turns a per-session quote into a real total, and the questions that separate a clear written estimate from a vague one.
Why Laser Acne Scar Prices Cover Such a Wide Range
Four variables do most of the work. The first is surface area. Published figures note that laser scar removal costs vary based on the size and number of scars being treated, which is why a small area treated with a single pass and a full-face resurfacing do not belong in the same price conversation. The second is technology, since the quoted range of $200 to $3,000 or more depends partly on the device being used and the size of the session. The third is the provider, because laser removal of acne scars can cost thousands of dollars, particularly when a large area of skin is treated by specialist physicians. The fourth is repetition, and it is the one patients underestimate most often.
- Area treated, from a single cheek to the full face and neck
- Laser technology and whether it is ablative or non-ablative
- Provider type and clinical setting
- Number of sessions required to reach the goal
- Whether combination treatments such as fillers or peels are added
What Published Laser Acne Scar Prices Actually Look Like
Published figures are not quotes, and none of the numbers below are Denver-specific. They are useful as a reference frame, because they show where a fair quote should fall once you know what is being treated.
| Source context | Treatment | Reported price |
|---|---|---|
| National range (GoodRx) | Laser acne scar removal | $200 to $3,000 |
| National range (CareCredit) | Laser scar removal | $100 to $5,000 or more |
| National average out of pocket, October 2019 (Healthline) | Ablative laser skin resurfacing | Around $2,000 |
| National average out of pocket, October 2019 (Healthline) | Non-ablative laser skin resurfacing | Around $1,100 |
| New York City | Single laser acne scar session | $1,500 to $3,500 |
| Encino | Laser acne scar treatment, per session | $800 to $3,000 |
| Los Angeles | Pixel laser, medium area | $349 |
| Knoxville | Fractional laser skin resurfacing | Starting around $300 to $350 |
| Patient-reported (Reddit) | Aggressive CO2 laser | $1,200 |
| Patient-reported (Reddit) | Bellafill | $1,200 |
The spread is enormous, and the gap between the low end and the high end is explained by area and technology rather than by any single market being uniquely expensive. A $300 fractional resurfacing starting price and a $3,500 single session in a major metro describe very different amounts of treated skin.
Session Count Is the Number That Decides Your Total
Published guidance indicates that treatment generally requires two to five laser sessions. That single sentence changes how you should read every quote you receive. A figure of $900 becomes $1,800 to $4,500 once you multiply it across the likely treatment plan, before any maintenance sessions or add-on treatments enter the picture.
Here is the arithmetic using published ranges, offered as an illustration and not as a Denver quote. If a session is priced at the lower end of a typical published band, three sessions stay modest. If a session is priced near the top of the published band for a large area treated by a specialist physician, the same three sessions reach the thousands of dollars that the national data describes. Ask any practice for the projected number of sessions in writing before you commit, because the per-session number alone tells you very little.
Ablative Versus Non-Ablative: The Price Split
The clearest structural divide in published cost data is between ablative and non-ablative laser skin resurfacing. As of an October 2019 industry figure, the average out-of-pocket cost sat around $2,000 for ablative treatments and around $1,100 for non-ablative treatments. That roughly twofold gap reflects the intensity of the procedure and the recovery it involves.
That published average is dated, so treat it as a historical benchmark rather than a current rate. It is still useful for one purpose: if a quote you receive sits far outside that relationship between ablative and non-ablative pricing, it is worth asking exactly which device is being used and why the number falls where it does. Verify current pricing directly with the practice before you plan a budget around any published average.
Non-Laser Options and What They Add to the Bill
Laser treatment is frequently only part of a plan. Published pricing for related procedures includes radiofrequency microneedling at roughly $600 to $1,200 per session and chemical peels at roughly $150 to $400 per peel. One patient reported spending $1,200 on an aggressive CO2 laser treatment and another $1,200 on Bellafill within the same treatment period, which shows how quickly a combination approach doubles the total.
Some clinics publish narrower, device-specific pricing. One Los Angeles provider lists a free consultation alongside Pixel laser treatment at $349 for a medium area, $399 for a medium area plus the neck, $499 for a large area, and higher for an extra-large area. Another clinic publishes smaller line items, including a deep pore treatment at $290, an acne chemical peel at $150, a pigmentation laser at $250, and a pigmentation chemical peel at $150. These figures show what a fully itemized price list looks like, which is the standard you should hold a Denver quote to.
Insurance Rarely Pays for Acne Scar Laser Treatment
Acne scar removal is treated as a cosmetic procedure, and cosmetic procedures are not covered by medical insurance. That means the published ranges above describe money that comes out of your pocket, not a negotiated rate an insurer absorbs.
If you plan to use a health savings account or flexible spending account, confirm eligibility with your plan administrator before scheduling. The rules are set by the plan and by tax guidance, not by the dermatology practice, so a clinic cannot tell you whether your specific account will reimburse the expense. Get that answer in writing from the account administrator first.
Why Denver Quotes Differ From One Practice to the Next
Market pricing varies. In New York City, patients can expect to pay between $1,500 and $3,500 for a single session of laser acne scar removal, which reflects that market rather than a universal standard. Denver is not New York, and it is not a small rural market either, so quotes tend to fall in the middle of the published national bands.
Within a single metro area, differences come down to which devices a practice owns, whether the treating clinician is a specialist physician, how the practice bundles consultations and follow-up visits, and how much of the face or body the quote actually covers. Two quotes for the same dollar figure can describe completely different amounts of treatment. That is why comparing practices means comparing scope, not just numbers.
Questions to Ask Before You Pay a Deposit
A short, direct list of questions will surface almost every hidden cost in a laser acne scar treatment plan.
- Which specific laser or device will be used, and is it ablative or non-ablative?
- Exactly what area does the quoted price cover, and is the neck or jawline included?
- How many sessions are recommended, and is that number guaranteed in writing?
- Is the consultation fee separate, and is it credited toward treatment?
- What is included in follow-up care, and what is billed separately?
- What is the total estimated cost if the full recommended plan is completed?
- Are there payment plan options, and what are the terms?
How to Build a Realistic Acne Scar Budget
Start with a consultation rather than a price list, because published ranges cannot tell you which category of treatment your scarring falls into. Once you have a recommended plan, multiply the per-session price by the recommended session count, then add any separate consultation, topical, or filler costs. Compare that total against the published bands in this article. If the total lands within the $200 to $3,000 per-session range across two to five sessions, the quote is consistent with the national data. If it falls far outside, ask what is driving the difference before you commit.
It also helps to decide in advance how much improvement you are paying for. Published sources list questions such as whether acne scars can be removed completely, whether laser treatment is worth it, and whether laser gets rid of acne scarring entirely as open questions rather than settled ones. A realistic budget is built around measurable improvement in texture and depth, not a promise of flawless skin, and any practice that frames it that way is being straight with you.
Frequently Asked Questions
Does insurance cover laser acne scar treatment?
No. Acne scar removal is classified as a cosmetic procedure, and cosmetic procedures are not covered by medical insurance. Published pricing therefore reflects out-of-pocket cost. Some national averages put ablative laser skin resurfacing around $2,000 and non-ablative around $1,100 as of an October 2019 commercial figure, so plan for the full amount to come from you.
How many laser sessions will I actually need?
Published guidance indicates that treatment generally requires two to five laser sessions, though the exact number depends on scar depth, scar type, the area being treated, and the device used. Because session count multiplies directly into your total cost, ask any practice to put the recommended number of sessions in writing before you schedule the first one.
Why are quotes from different practices so far apart?
The variance usually comes from scope and technology rather than arbitrary pricing. A single session in New York City can run $1,500 to $3,500, while other published listings start around $300 to $350 for fractional resurfacing. Different devices, different treated areas, and different clinician types all move the number, so compare what each quote actually includes.
Can laser treatment remove acne scars completely?
Whether acne scars can be removed completely remains an open question in published consumer sources rather than a settled outcome. Lasers are used to improve the appearance and texture of scarring, and results vary by scar type and skin. Treat significant improvement as the realistic goal, and ask your dermatologist what degree of change is reasonable for your specific scarring.
What should a written acne scar quote include?
A useful quote names the device, states whether treatment is ablative or non-ablative, defines the treated area, lists the recommended number of sessions, and separates consultation fees from procedure fees. Itemized clinic price lists show how this looks in practice, with individual treatments priced separately. Ask for the total estimated cost of the complete plan, not just one session.
Basal Cell Carcinoma on the Nose: Why MOHS Surgery Works
A basal cell carcinoma on the nose creates two problems at once. The first is the cancer itself. The second is that the nose sits in the middle of the face, covered in thin skin stretched tightly over cartilage, where any removed tissue shows. Treatment has to clear the tumor completely while leaving the nose as close to its original shape and appearance as possible. MOHS surgery is often recommended for basal cell carcinomas on the nose, along with the eyelids, lips, ears, scalp, hands, and other areas where preserving healthy tissue matters.
Why the Nose Is a Challenging Place for Skin Cancer
The nose is a high-traffic area for sun exposure, which is part of why basal cell carcinoma so often appears there. A dermatologist can spot a lesion near the tip of the nose that carries a pearly, slightly raised border and would likely bleed easily. That description matches the classic appearance of nasal basal cell carcinoma.
The anatomy makes treatment harder than the diagnosis. Nasal skin is thin and moves with every facial expression. Beneath it lies cartilage that gives the nose its shape. Remove too much tissue, or remove it in the wrong place, and the result can be a dent, a flattened edge, or a pulled nostril. Because of that, the goal in treating a nasal basal cell carcinoma is tumor-free margins with the smallest possible defect.
What Basal Cell Carcinoma on the Nose Looks Like
Basal cell carcinoma is easy to overlook because it rarely announces itself. Early signs on the face include:
- A pearly or shiny bump
- A sore that bleeds or crusts
- A flat, scaly patch
- A scar-like area
On the nose specifically, the lesion may appear as a small raised bump with a translucent or pearly rim. It may bleed when you wash your face or towel off, then seem to heal, then bleed again. Some basal cell carcinomas look like a dry patch of skin or a pimple that never quite goes away. Others look like a small scar that appeared without any injury to explain it.
This variety is why a visual inspection alone is not enough. A dermatologist may examine the spot with a dermatoscope and, if it looks suspicious, take a biopsy. The biopsy is what confirms basal cell carcinoma and rules out other conditions that can look similar on the nose.
Why Treatment Choice Matters More on the Nose
On the back or the shoulder, a slightly larger excision scar is easy to accept. On the nose, every millimeter counts. The tissue there is unforgiving of guesswork, and a repair that distorts the nasal tip or narrows a nostril is a permanent cosmetic and sometimes functional problem.
That is the core reason treatment selection matters so much for this location. Some treatment methods destroy tissue without mapping exactly where the cancer ends. Others leave the surgeon uncertain whether the margins were truly clear, which can mean a second procedure later. For a tumor sitting on the nose, that uncertainty is worth avoiding.
Why MOHS Is Often Recommended
MOHS micrographic surgery is designed for exactly this situation. Instead of removing the visible tumor with a wide margin of normal-looking skin, the MOHS surgeon removes the tumor and then examines the complete outer edge of that tissue under a microscope before deciding whether more needs to come out.
The practical benefit is precision. If cancer cells are found at one spot on the margin, the surgeon goes back for another thin layer at that spot only, not across the whole wound. If the margin is clear, the surgery stops. Nothing healthy is sacrificed beyond what is necessary to get a clean result.
For a basal cell carcinoma on the nose, that tissue-sparing quality is the main argument in favor of MOHS. It also gives the surgeon a mapped, documented answer about whether the tumor was fully removed, which reduces the chance of a surprise recurrence down the road.
What Happens During MOHS Surgery
- The area around the tumor is numbed with a local anesthetic, so you stay awake during the procedure.
- The surgeon removes the visible tumor along with a thin layer of surrounding tissue.
- The tissue is mapped, marked, and processed so the entire outer margin can be examined under a microscope.
- The surgeon reviews the slides. If cancer is still present at any point on the margin, another thin layer is removed from that exact spot.
- Steps three and four repeat until the margin is clear of cancer cells.
- Once the tumor is fully removed, a defect is left behind, and the surgeon repairs it. On the nose, that repair may be a simple closure, a flap, or a graft, depending on the size and depth of the defect.
Because each round of margin checking takes time, MOHS is a longer appointment than many other skin cancer removals. The trade-off is that the surgeon knows the margins are clear before closing the wound, rather than waiting for a pathology report days later.
Other Treatment Options That May Be Considered
MOHS is not the only option for basal cell carcinoma on the nose, and it is not right for every tumor. Cryosurgery, which destroys tissue with cold, has been used for multiple basal cell carcinomas on the nose, and case reports on that approach exist in the medical literature. Radiotherapy has also been recommended for basal cell carcinoma of the nose in certain settings, though published reviews note wide variation in the techniques used and the doses prescribed.
Other factors shape the decision, including the size and depth of the tumor, how it looks under the microscope, and the condition of the surrounding skin. Ask your dermatologist which options apply to your specific lesion and why one is preferred over another in your case.
Recovery and Scarring After Nasal Surgery
Any treatment that removes skin cancer from the nose leaves a scar. The question is what kind of scar and how noticeable it will be. A small, superficial tumor closed in a straight line looks very different from a larger tumor repaired with a flap or graft that borrows tissue from nearby.
Healing timelines vary from person to person, and the final appearance of a scar can take months to settle. Your surgeon is the best source for a realistic picture of what your repair will look like at three weeks, three months, and beyond. Follow the aftercare instructions you are given, keep the area protected from sun, and attend your follow-up visits so healing can be monitored.
Choosing Care for a Nasal Basal Cell Carcinoma
Before committing to a treatment plan, it helps to ask a few direct questions:
- What type of basal cell carcinoma is this, based on the biopsy?
- Why is this treatment recommended over the alternatives for my nose?
- How will the wound be repaired, and who performs the repair?
- What should I expect during healing, and what signs would mean I should call?
- How often should I be checked afterward for new skin cancers?
Colorado Dermatology Center is a South Denver dermatology practice led by board-certified dermatologist Dr. James M. Swinehart, whose clinical experience spans more than three decades. The practice focuses on medical, surgical, and cosmetic dermatology, with particular emphasis on skin cancer treatment including MOHS surgery. Patients looking for evaluation of a suspicious spot on the nose can schedule a consultation to have it examined and, if needed, biopsied.
Frequently Asked Questions
What does basal cell carcinoma on the nose look like?
It often appears as a pearly or shiny bump, a sore that bleeds or crusts and then seems to heal, a flat scaly patch, or a scar-like area. On the nose, a lesion may have a pearly, slightly raised border and bleed easily. Any spot that persists, changes, or bleeds repeatedly should be examined by a dermatologist.
Why is MOHS often recommended for basal cell carcinoma on the nose?
The nose has thin skin over cartilage, so removing too much tissue can change its shape. MOHS surgery examines the entire outer margin of the removed tissue under a microscope, and additional layers are taken only where cancer remains. That gives the surgeon margin control while sparing as much healthy nasal tissue as possible.
Are there alternatives to MOHS for nasal basal cell carcinoma?
Yes. Cryosurgery has been used for multiple basal cell carcinomas on the nose, and radiotherapy has been recommended for nasal basal cell carcinoma in certain situations, with wide variation in techniques and doses across published reports. Which option fits depends on the tumor and the surrounding skin, so discuss the trade-offs with your dermatologist.
How is the wound repaired after the tumor is removed?
Once the margins are clear, a defect remains where the tumor was. The surgeon repairs it based on size, depth, and location on the nose. Options include closing the skin directly, using a flap of nearby tissue, or placing a graft. Your surgeon can explain which approach is planned for your case.
Free Skin Cancer Screenings Near Denver: How to Find One
If you live in the Denver area and want a skin check without paying out of pocket, free skin cancer screenings do exist. The catch is that they rarely happen at the same place on a predictable schedule. Most free screenings come from national programs that travel from city to city, hospital outreach events, and dermatology practices that open a limited number of no-cost appointments.
Finding one takes some legwork, but the search follows a repeatable pattern. The tools and phone calls below are the ones that reliably lead people to a free skin check, along with what to expect at the appointment and what to do if the exam turns up something that needs a closer look.
Why a Professional Skin Check Is Worth Pursuing
One in five people of all skin colors in the United States will develop skin cancer, according to the American Academy of Dermatology. The AAD recommends an annual total-body skin cancer exam performed by a dermatology professional, because skin cancer caught early is generally easier to treat.
A free screening is not the same thing as that annual exam, and it is not a diagnosis. It is a first look by a trained professional, meant to flag spots that deserve closer attention. For anyone who has put off a check because of cost, an insurance gap, or simply not knowing where to go, a free event removes most of those barriers.
Use the AAD Screening Map to Find Events by State
The American Academy of Dermatology maintains a free skin cancer check locator built around a national map. Clicking on your state shows the scheduled free skin cancer checks currently listed there, which makes it the fastest starting point for anyone typing a search like free skin cancer screening near me.
Because these are scheduled events rather than permanent clinics, listings change throughout the year. Check the map before assuming nothing is happening in Colorado, and check it again if the calendar looks empty the first time. Events are often added closer to their date.
How to work the screening map efficiently
- Open the AAD find-a-screening page and select Colorado.
- Write down the dates, locations, and any eligibility notes attached to each listing.
- Contact the sponsoring organization directly to confirm the event is still on before you travel.
- Recheck the map every few weeks, since new screenings get posted through the year.
Destination Healthy Skin, the Skin Cancer Foundation’s Mobile Program
Destination Healthy Skin is a mobile screening and education program run by The Skin Cancer Foundation. A 38-foot RV travels the country with two private exam rooms inside, staffed by volunteer dermatology providers who perform free full-body skin exams. The program offers free exams performed by licensed dermatology professionals, and no appointment is necessary at the mobile unit.
The program’s numbers show how much a mobile clinic can handle. Since its launch, the team has provided 35,000 free skin cancer screenings, identified more than 14,200 potential skin cancers and precancers, including 699 suspected melanomas, and distributed free educational materials and sun protection products to more than 119,000 people.
The tour schedule shifts by city and season, so the practical step is to visit the Destination Healthy Skin page and see whether a Colorado stop is planned during the current tour.
Ask Denver Hospitals and Health Systems About Outreach Screenings
The Prevent Cancer Foundation points people without insurance toward community resources for free and low-cost screening. Its guidance is straightforward: contact your local hospital or health care facility and ask whether routine cancer screening, testing, and vaccinations are offered through their foundations or outreach programs, including mobile testing.
That phone call is worth making in the Denver area. Hospital foundations, cancer resource centers, and community health events frequently host screenings that never surface in a general web search. When you call, ask specifically about skin cancer screening events, whether registration is required, and whether there is an age or eligibility requirement.
Dermatology Practices That Offer Free Screenings to New Patients
Some dermatology practices set aside free skin cancer screenings for new patients as a way of introducing themselves to the community. These offers usually come with conditions. The screening is often valid for new patients only, at participating locations, and you typically need to book rather than walk in.
If you call a practice near you, ask three questions before scheduling:
- Is the screening free for new patients, and at which locations?
- What does the exam include?
- Is there any cost if something needs a closer look afterward?
Getting those answers up front prevents surprises. A free screening offer is not the same as free follow-up care, and a biopsy or treatment is normally billed separately from the screening itself.
What Happens During a Free Skin Cancer Screening
Free screenings are shorter and more limited than a full dermatology visit, and expectations vary by event. The general pattern looks like this:
- The exam is a full-body skin check focused on moles, spots, and lesions that look unusual.
- At the larger national programs, licensed dermatology professionals perform the exams.
- Some community clinics report screenings that last about 10 minutes.
- Some events are walk-in only, while others ask you to sign up online in advance.
- Some clinics set eligibility rules, such as being 18 or older or not having had a professional skin exam within a certain period.
The table below compares the main routes to a free screening so you can decide where to start.
| Where to look | What it offers | What to verify first |
|---|---|---|
| AAD find-a-screening map | State-by-state list of scheduled free skin cancer checks | Current dates and eligibility notes, since listings change through the year |
| Destination Healthy Skin | Free full-body exams in a 38-foot mobile unit with two private exam rooms; no appointment necessary | Whether the tour is stopping near Denver during the current season |
| Hospital and health system outreach | Screenings offered through foundations or community programs, sometimes through mobile testing | Whether skin cancer screening is included and whether registration is required |
| Dermatology practice offers | Free screenings for new patients at participating locations | Whether the free exam covers only the initial check or includes follow-up |
Questions to Ask When You Call About an Event
A short phone call can save a wasted trip. Ask whether the screening is still scheduled, whether you need an appointment, what age or insurance rules apply, and who performs the exams. If you have specific spots that worry you, say so when you call and ask whether the screening format can address them or whether you should book a full dermatology visit instead. It also helps to bring a list of the spots that concern you, along with your personal and family history of skin cancer, so the examiner has context.
If the Screening Finds Something Suspicious
Screening programs are built to flag problems, not to treat them. The Skin Cancer Foundation’s mobile program, for instance, reports identifying thousands of potential skin cancers and precancers over its history, along with hundreds of suspected melanomas. All of those findings needed follow-up with a dermatologist.
That follow-up is where a diagnosis gets made. If a screening professional recommends further evaluation, the next step is usually a dermatology appointment for a closer exam and, if warranted, a biopsy. In the Denver area, Colorado Dermatology Center in South Denver provides that kind of follow-up care. The practice is led by board-certified dermatologist Dr. James M. Swinehart and specializes in skin cancer treatment, including MOHS micrographic surgery for certain skin cancers. A free screening gives you a first look; a dermatology practice handles everything that comes after it.
Insurance, Cost, and Coverage Questions
If you have health insurance, most private insurance companies as well as Medicare and Medicaid cover the cost of certain routine cancer screenings, according to the Prevent Cancer Foundation. Coverage rules differ from plan to plan, so confirm your specific benefits with your insurer before scheduling a diagnostic visit.
If you do not have insurance, the same organization recommends starting with community resources, your local hospital, or a health care facility’s outreach program. Free screening events are the other route, and they exist precisely for people who would otherwise skip a check.
Frequently Asked Questions
Do I need an appointment for a free skin cancer screening?
It depends on the event. The Skin Cancer Foundation’s Destination Healthy Skin mobile unit states that no appointment is necessary, and walk-in screenings are common at health fairs and community events. Other programs, including some hospital events and new-patient offers at dermatology practices, ask you to register or book a time in advance. Always confirm with the sponsoring organization before you go.
Who is eligible for a free skin cancer screening?
Eligibility rules are set by each sponsoring organization, so they vary. Some free clinics are open to adults 18 years or older, and some ask that participants not have had a professional skin exam within a certain period. Others are open to anyone who shows up. Check the event listing or call ahead to confirm the requirements for the specific screening you plan to attend.
What happens if the screening finds something suspicious?
A screening is a first look, not a diagnosis. If the professional examining you sees a spot that needs closer attention, they will recommend a follow-up visit with a dermatologist. At that appointment, the dermatologist may examine the area in more detail and, if needed, perform a biopsy to determine whether it is skin cancer.
Where should I start looking for free screenings near Denver?
Start with the American Academy of Dermatology’s find-a-screening map, which lists scheduled free skin cancer checks by state. Next, check The Skin Cancer Foundation’s Destination Healthy Skin tour schedule and call local hospital foundations to ask about outreach events. Dermatology practices that offer free new-patient screenings are another option worth calling directly.
Is a free skin screening as thorough as a dermatologist visit?
No. Free screenings are shorter by design and focus on spotting anything that looks concerning, with some community clinics reporting exams of about 10 minutes. A full dermatology visit includes a complete history, a total-body exam, and the ability to biopsy or treat on the spot when needed. The American Academy of Dermatology still recommends an annual total-body exam by a dermatology professional.
Wrinkle Treatment in Denver: Injectables, Fillers, and What Works
Denver has no shortage of places offering to smooth a line or two. Search for wrinkle treatment in Denver and you will find medspas, plastic surgery offices, and dermatology practices, each with a slightly different philosophy and a different menu. The harder question is not where to go. It is which treatment matches the wrinkles you actually have. A forehead line created by years of muscle movement behaves nothing like a fold caused by lost volume, and a plan built for one will disappoint you if your skin needs the other. What follows is a practical way to sort the options, from injectable wrinkle relaxers and dermal fillers to peels, dermabrasion, and laser resurfacing.
Start With the Type of Wrinkle You Have
Wrinkles are not one condition. Dynamic lines appear when muscles pull the skin into a crease, which is why they show up first in the forehead, between the brows, and at the outer corners of the eyes. Static lines stay visible even when your face is at rest, and they usually reflect volume loss, thinning collagen, and cumulative sun exposure. Many people have both at once, which is why a single product rarely solves everything.
Sun exposure in Colorado shows up as more than lines. Uneven pigmentation, sun damage, and melasma tend to appear alongside fine wrinkling, and several Denver treatment menus group these concerns together for that reason. One local package marketed as a dual-action rejuvenation treatment is specifically described as formulated for people dealing with melasma and sun damage. That grouping is not marketing noise. Pigment and texture often respond to the same resurfacing tools.
Before choosing a treatment, figure out whether your lines are mostly movement-driven, mostly volume-driven, mostly texture and pigment, or a mix. That answer narrows your list to two or three realistic options.
Injectable Wrinkle Relaxers: Botox and Dysport
Injectable neuromodulators are the most familiar wrinkle treatment, and in Denver they are widely available under brand names including Botox and Dysport. Providers who specialize in advanced wrinkle relaxers describe their goal as softening lines, refreshing the skin, and restoring confidence rather than freezing expression. The mechanism is straightforward: the injectable relaxes the specific muscles that fold the skin, which reduces how deeply those creases set over time.
What relaxers handle well
Movement-based lines in the upper face are the classic target: horizontal forehead lines, the vertical lines between the brows, and crow’s feet. Because the treatment works on muscle activity rather than on the skin surface, it can soften lines that no topical product reaches. Results are temporary, which is both the appeal and the ongoing cost.
What relaxers do not fix
Relaxers do nothing for volume loss. A fold that remains visible when your face is completely relaxed, such as a deep nasolabial fold or a line running from the corner of the mouth downward, is usually a filler or resurfacing question rather than a relaxer question. That distinction is the most common source of disappointment for first-time patients.
Dermal Fillers: Restylane and Juvederm
Dermal fillers work from a different direction. Instead of reducing muscle pull, they replace some of the volume that has shifted or diminished, which lifts and softens static folds. Denver clinics offering dermal fillers commonly stock Restylane and Juvederm, and those brand families include multiple formulations designed for different areas and depths.
Fillers suit lines that persist at rest, hollowing under the eyes or along the cheeks, and folds around the mouth. They are also frequently combined with a relaxer in the same visit, because the two address separate mechanisms. If your goal is a natural result, that layered approach usually looks more convincing than pushing a high volume of filler into a single area.
Resurfacing: Peels, Dermabrasion, and Laser
A third category improves the skin surface itself. According to treatment information from Denver-area providers, a medium depth peel, light dermabrasion, or gentle laser treatment can produce mild to moderate improvement in wrinkles and in abnormal pigmentation. That word mild matters. Resurfacing is a gradual strategy, often delivered across a series of sessions, and it suits fine lines, texture, tone, and sun-related damage better than deep creases.
Laser treatments are marketed in Denver as a way to reduce wrinkles and fine lines with personalized plans and natural-looking results. Candidacy depends on skin tone, sensitivity, downtime tolerance, and how recently you have had sun exposure, which is a real consideration in a state with strong year-round sun. A board-certified dermatologist can tell you whether your skin type is a good candidate for a given laser or whether a lighter peel is the safer route.
How Denver Practices Put These Together
Most comprehensive anti-aging programs in Denver are built as layers rather than single treatments. One Denver provider describes its program as addressing the skin and body from the surface down to the deepest tissue layer, which is a reasonable description of how injectables, fillers, and resurfacing fit together. The surface layer covers texture and pigment. The middle layer covers volume. The deepest layer covers muscle movement.
Geography shapes the market too. Clinics in the south metro, including those serving Greenwood Village, the Denver Tech Center, and Cherry Hills Village, tend to attract patients who work nearby and want appointments that fit around a lunch break. That detail influences what a practice offers: shorter injectable visits, longer resurfacing sessions, and package pricing that bundles related treatments. When a Denver provider lists a session length and a price together, treat it as a starting point rather than a final quote, since the number of areas and the amount of product change the total.
Board-Certified Dermatology, Medspas, or Both
Denver’s wrinkle treatment market spans a wide range. Directory listings for wrinkle treatments in the area include medical spas such as Cunningham Clinic, Smoothe Denver, Sesen Skin Body Wellness, Happy Clinic Denver, and Novuskin Denver, along with individual physicians listed for the 80246 area, including Dr. Robert G Fante and Dr. Michael Edward Contreras. Names appearing in search results are not an endorsement, and they are not a substitute for checking credentials, licensing, and experience with the specific treatment you want.
There is a practical reason to keep a dermatology practice in the mix. Colorado Dermatology Center, led by board-certified dermatologist Dr. James M. Swinehart, combines more than three decades of clinical expertise with medical, surgical, and cosmetic dermatology, including facial rejuvenation, acne scar revision, hair restoration, and skin cancer treatment such as MOHS surgery. A practice that treats skin disease and skin aging in the same building can evaluate whether a changing spot, a new line, or a rough patch is cosmetic or medical. For anyone with a history of sun damage or skin cancer, that evaluation belongs before the injectable, not after.
Questions Worth Asking at a Consultation
- Which of my lines are movement-based and which are volume-based?
- What result is realistic in one visit, and what would need a series?
- Who performs the injection or the laser, and what is their training?
- What are the risks for my skin tone and my history of sun damage?
- How much downtime should I plan for, and what aftercare is required?
- What is the full cost, including any follow-up sessions?
Timing, Maintenance, and Expectations
No wrinkle treatment in Denver produces a permanent result, and plans that promise otherwise should raise questions. Relaxers are maintained on an ongoing schedule, fillers are gradually metabolized, and resurfacing results build across sessions. The reason to start early is not vanity. Softening a line while it is still dynamic is generally easier than rebuilding a fold that has become static. That said, starting later is not pointless. Patients in their forties, fifties, and beyond are treated regularly, and a well-designed combination plan often produces visible improvement regardless of the starting line.
Realistic expectations matter more than the product name. Providers across Denver describe their goals in similar terms: personalized plans, natural-looking results, and improvement that fits your face rather than changing it.
Frequently Asked Questions
What is the most effective treatment for wrinkles?
There is no single winner, because effectiveness depends on the type of line. Movement-based lines in the forehead and around the eyes respond best to injectable relaxers such as Botox or Dysport. Static folds and volume loss respond to dermal fillers. Fine lines, texture, and sun-related pigmentation respond to peels, dermabrasion, or gentle laser treatments. Most patients get their best result from a combination chosen for their specific pattern.
Is 40 too late to start Botox?
No. Wrinkle relaxers work on muscle movement at any age, so they can still soften dynamic lines that have already formed. What changes with time is how much of the line has become static, which may call for adding a filler or a resurfacing treatment to the plan. A consultation is the best way to learn which category your lines fall into.
How much does wrinkle treatment in Denver cost?
Pricing varies by treatment type, the number of areas treated, and how much product or how many sessions are needed. Some Denver providers publish package prices and session times, but those figures are starting points rather than final quotes. Ask for a written estimate covering the initial visit and any recommended follow-up, since maintenance visits add up over a year.
How long do results last?
Duration depends on the treatment. Injectable relaxers are temporary and require scheduled maintenance, while fillers are gradually broken down by the body over time. Resurfacing results build across a series of sessions rather than appearing all at once. Your provider should give you a realistic timeline for your specific plan, and individual results vary with skin, lifestyle, and sun exposure.
Should I see a dermatologist or a medspa?
Both can be appropriate, and many patients use each for different needs. A board-certified dermatologist can evaluate your skin for medical concerns alongside cosmetic ones, which matters if you have a history of sun damage or skin cancer. Medspas often focus on injectables and package pricing. Check credentials, licensing, and experience with your specific treatment before booking either option.

Acne and Acne Scar Treatment in Denver: Matching Procedures to Scars
Two people can walk into a dermatology office with a similar history of breakouts and leave with completely different treatment plans. That is not inconsistency. It is the nature of scar revision. Acne scars come in distinct shapes, depths, and textures, and no single treatment is best for everyone. What improves one person’s skin may do very little for another’s. Matching the procedure to the scar is the first real decision in any acne and scar treatment plan.
Why Acne Leaves Scars Behind
Acne scarring can develop as a complication of acne itself. Any type of acne spot can lead to scarring, but it is more common when the most serious types of spots, nodules and cysts, burst and damage nearby skin. The damage happens below the surface, which is why a scar can appear after the visible bump has already faded.
Picking and squeezing matter too. Scarring can also occur if you pick or squeeze your spots, so it is important not to do this. That advice is not about willpower. Manipulating a healing lesion adds trauma to skin that is already repairing itself, and that extra injury can make a scar more noticeable.
The Main Scar Types, and Why the Difference Matters
The NHS groups acne scars into three main types. Two of them are easy to picture:
- Ice pick scars: small, deep holes in the surface of the skin that look like the skin has been punctured with a sharp object.
- Rolling scars: caused by bands of scar tissue that form under the skin, which pull the surface into gentle, wave-like depressions.
Ice pick scars are narrow and deep. Rolling scars are wider and shallower but tethered underneath. A third main type also exists, and the practical point is the same for all of them: depth and tethering change how a treatment needs to work. A surface treatment reaches the top layers of skin. A procedure designed to release or fill tissue underneath addresses a different part of the problem. Choosing without classifying the scar first is how people end up disappointed after a treatment that was never aimed at their actual scar.
Procedure Options That Dermatology Uses for Scarring
Multiple treatments exist, including chemical peels, dermabrasion and microdermabrasion, laser treatment, punch techniques, dermal grafting, needling, and combined approaches. Most scars can be improved by modern interventions, which may include surgical revision and excision, laser therapy, intralesional injections, and topical creams.
Those categories can sound like a menu, and in some ways they are, but they work at different depths and in different ways. Dermabrasion, for instance, involves removing the top layer of skin, either using lasers or a specially made wire brush. Soft tissue fillers work differently: injecting collagen, fat, or other substances under the skin can plump the skin over indented scars. Surgical techniques such as punch techniques and dermal grafting address scars that need a structural change rather than surface refinement.
Home care belongs in the plan as well, although it is not a substitute for procedures. Using sunscreen can help limit the contrast between unscarred skin and a scar. Some medicated creams, such as those containing azelaic acid or hydroxyl acids, might help too.
Matching the Procedure to the Scar
| Approach | What the research describes | Where it fits |
|---|---|---|
| Dermabrasion and microdermabrasion | Removing the top layer of skin, either using lasers or a specially made wire brush | Surface texture and shallow irregularity |
| Laser treatment | Listed among treatments for acne scarring and among modern interventions | Resurfacing and scar revision planning |
| Chemical peels | Named among the numerous treatments for acne scars | Surface-level improvement |
| Needling | Named among treatments and can be combined with retinol creams and filler | Surface and deeper marks within a combined plan |
| Soft tissue fillers | Injecting collagen, fat, or other substances under the skin to plump skin over indented scars | Depressed or indented scars |
| Punch techniques and dermal grafting | Named among surgical treatments for scarring | Scars that need structural change |
| Surgical revision and excision | Listed among modern interventions that can improve most scars | Selected scars after evaluation |
| Intralesional injections | Listed among modern interventions for scarring | Specific scar types as determined by a physician |
| Topical creams | Azelaic acid or hydroxyl acids might help; retinoids can visibly lighten dark spots; salicylic acid helps lighten dark areas and even out skin tone | Home care alongside procedures |
Read that table as a starting point for a conversation, not a prescription. Acne scars are stubborn, and no single treatment is best for everyone. One or a combination of approaches might improve the appearance of your skin depending on your scar type, your skin type, and the severity of the scarring.

Combination Plans Target Surface and Depth Together
Combining two or more treatments, such as retinol creams, microneedling, and filler for acne scars, can target both surface and deep skin marks. That layered logic is why combination planning shows up so often in scar revision. A filler addresses volume under an indented scar while a resurfacing method works on the texture above it, and a topical routine supports the skin between procedures.
Combination also means sequencing. Procedures that remove or remodel surface skin and procedures that add volume underneath place different demands on healing tissue. The order, the spacing, and the number of sessions are clinical decisions, and they depend on how your skin responds.
Marks, Active Acne, and Scars Are Different Problems
Not everything left behind by a breakout is a scar. Post-acne marks are color changes, and topical retinoids are one way to improve their appearance; retinol can help visibly lighten dark spots. Salicylic acid is sometimes used for the treatment of acne as well, and studies show it helps lighten dark areas and even out skin tone. Marks and scars can coexist, which is why a plan may include both a topical routine and a procedure.
Active acne deserves its own attention. Treating scarring while breakouts are still forming means new lesions can keep creating new damage. A dermatologist can address active acne and scar revision as parts of one plan rather than treating them as separate errands.

What to Ask During a Consultation in Denver
Colorado Dermatology Center is a South Denver dermatology practice led by board-certified dermatologist Dr. James M. Swinehart, whose clinical experience spans more than three decades. The practice covers medical, surgical, and cosmetic dermatology, and acne scar revision is one of its areas of emphasis alongside skin cancer treatment, hair restoration, and clinical research trials.
Bring specific questions to that visit:
- Which of the main scar types do I have, and where are they located?
- Is what I am seeing a scar, a post-acne mark, or both?
- Do I still have active acne that needs treatment first or alongside revision?
- Which procedures are being recommended, and what does each one target at the surface versus underneath?
- How many treatments are planned, and in what order?
- What home care, including sunscreen and any topical creams, supports the result?
A useful consultation ends with you understanding why a particular procedure fits your particular scars. If the explanation is vague, or if the plan is a single treatment applied the same way to everyone, ask for the reasoning. Scar revision rewards precision, and precision starts with classification.
Frequently Asked Questions
What is the best treatment for acne scars?
There is no single best treatment. Acne scars are stubborn, and no one approach is right for everyone. One or a combination of options might improve the appearance of your skin depending on your scar type, your skin type, and the severity of the scarring. A dermatologist matches the procedure to what your skin actually shows.
Can acne scars actually be improved?
Most scars can be improved by modern interventions. Depending on the evaluation, that may include surgical revision and excision, laser therapy, intralesional injections, and topical creams, along with chemical peels, dermabrasion or microdermabrasion, punch techniques, dermal grafting, and needling. Improvement is the realistic goal rather than erasing a scar completely.
Do I need to clear active acne before treating scars?
Active breakouts can keep creating new damage, including when nodules and cysts burst and damage nearby skin, so it makes sense to address both. A dermatologist can build a plan that manages active acne while planning scar revision, rather than treating the two as unrelated problems. Ask how your own plan sequences them.
Does sunscreen or skincare really matter for scars?
Yes, as support rather than a cure. Using sunscreen can help limit the contrast between unscarred skin and a scar. Some medicated creams containing azelaic acid or hydroxyl acids might help too, and topical retinoids can visibly lighten dark spots. Salicylic acid is also used for acne treatment and helps lighten dark areas and even out skin tone.
Why do dermatologists combine treatments?
Because scars vary in depth and texture. Combining two or more treatments, such as retinol creams, microneedling, and filler for acne scars, can target both surface and deep skin marks. Soft tissue fillers plump skin over indented scars using collagen, fat, or other substances, while resurfacing approaches work on the surface. The mix depends on your scars.

MOHS Surgery Denver: How Micrographic Removal Works
Mohs micrographic surgery is a highly specialized treatment for the removal of skin cancer, and it works differently from almost any other cancer operation. The same physician serves as surgeon, pathologist, and reconstructive surgeon during a single visit, which is why the procedure has earned a reputation as the most precise way to clear certain tumors. The technique is named in honor of Dr. Frederic Mohs, and it is performed in the office using local anesthesia rather than in a hospital operating room.
For patients in Denver searching for a Mohs surgeon, the appeal is easy to understand. The procedure yields the highest cure rate of all skin cancer treatments, with cure rates approaching 99% for tumors that have not previously been treated. Just as important, it spares healthy tissue in a way that standard excision cannot, which matters a great deal when the cancer sits on the nose, eyelid, ear, lip, or another visible part of the face.
What Makes Mohs Surgery Different From Standard Excision
A traditional excision removes the visible tumor along with a margin of normal skin, and the tissue is sent to a pathology lab for review. Results often come back days later. If the margins are not clear, the patient returns for a second procedure.
Mohs surgery compresses that cycle into one appointment. The surgeon removes the cancer, examines 100% of the tissue edges under a microscope while the patient waits, and knows immediately whether any cancer remains. If it does, another thin layer is taken from only the precise area where tumor cells were found. Nothing is guessed, and nothing is removed simply for safety margin.
- The physician acts as surgeon, pathologist, and reconstructive surgeon in one sitting.
- The procedure is performed in the office using local anesthesia.
- The removal of healthy skin is minimized compared with other skin cancer treatments.
- Cure rates approach 99% for tumors that have not previously been treated.
How Micrographic Skin Cancer Removal Works, Step by Step
The procedure relies on the precision and accuracy of examining tissue under a microscope to trace and ensure removal of the skin cancer, which may have roots that extend beyond what is visible to the naked eye. Here is how that plays out during a typical Mohs visit.
- Consultation and biopsy review. Your surgeon confirms the diagnosis and reviews the pathology report, the tumor’s location, and its size before scheduling the procedure itself.
- Mapping the tumor. On the day of surgery, the visible cancer and a small surrounding area are marked and mapped so the tissue can be oriented accurately once it leaves the body.
- First stage removal. The area is numbed with local anesthesia, and the visible tumor plus a thin layer of surrounding tissue is removed.
- Tissue processing. The specimen is flattened, frozen, sectioned, and stained so the entire outer edge can be viewed at once rather than sampled in random slices.
- Microscopic review. The surgeon reads the slides personally and marks on the map exactly where cancer cells remain, if any do.
- Additional stages if needed. When cancer is still present, another thin layer is removed only from the mapped area, and the review repeats until the margins are clear.
- Reconstruction. Once the cancer is fully removed, the surgeon closes the wound, which may involve a simple closure, a flap, or a graft depending on the size and location.
Why the Microscope Step Carries So Much Weight
Skin cancers can send out microscopic extensions that are invisible to the naked eye. Those extensions are the reason some tumors recur after an apparently complete removal. By examining the entire perimeter of each removed layer, Mohs surgery finds those roots while the patient is still in the chair, which is what allows the surgeon to be confident the cancer is gone before the wound is closed.
Reconstruction Is Part of the Procedure, Not an Afterthought
Because the surgeon who removed the cancer also understands exactly how deep and wide the defect is, reconstruction can be planned around both function and appearance. Denver Mohs practices commonly perform reconstructive surgery on the chin, forehead, and nose, areas where a poorly planned closure would be noticeable and where tissue movement and skin tension need careful handling.
Cure Rates and Why Mohs Is Not Used for Every Tumor
Mohs surgery exists in a category of its own when it comes to cure rates. For tumors that have not previously been treated, cure rates approach 99%. That figure is the reason the technique is often reserved for cancers in high-risk locations, cancers that have returned after earlier treatment, tumors with aggressive growth patterns, and cancers where the amount of healthy tissue removed matters a great deal.
Not every skin cancer requires Mohs surgery, though. A small, superficial cancer on the back or shoulder may be managed perfectly well with another approach. The right choice depends on the tumor type, its size and depth, its location, whether it has been treated before, and your own health history. A board-certified dermatologist is the right person to make that call, and a referral to a Mohs surgeon does not automatically mean you need the most complex option.
Who Performs Mohs Surgery in Denver
Mohs micrographic surgery requires training beyond a dermatology residency. Mohs surgeons complete a dedicated fellowship program, which typically runs about a year, focused on the technique itself plus the pathology reading and reconstructive skills that go with it. When you look for a provider in the Denver area, that fellowship training and board certification are the credentials worth checking first.
Denver has a substantial pool of Mohs providers across the metro, from Cherry Creek and central Denver to Aurora, where hospital-based dermatology departments also offer the procedure. Colorado Dermatology Center has served the region for more than three decades under board-certified dermatologist Dr. James M. Swinehart, with Mohs surgery offered as part of its skin cancer services. The Denver and Longmont office can be reached at (303) 761-0906.

What Recovery Looks Like After Mohs Surgery
Most patients leave the office the same day with the wound closed and written instructions in hand. Because the procedure uses local anesthesia only, there is no general anesthetic to recover from. The first days are usually about keeping the site clean, protecting the repair, and managing soreness, and your surgeon’s team will tell you exactly how to care for your specific closure.
Scarring is a normal part of any procedure that removes skin, and Mohs surgery does not change that. What it does change is how much tissue is taken and how carefully the closure can be designed. Patients are typically advised to avoid strenuous activity and sun exposure on the healing site for a period determined by the surgeon, and follow-up visits are used to confirm healing and check for new skin cancers elsewhere.

Questions to Ask Before Booking a Mohs Appointment in Denver
A short list of questions will tell you a great deal about how a practice operates and whether it fits your situation.
- Is the surgeon board certified, and did they complete a Mohs fellowship?
- Who reads the pathology slides, and is the tissue processed on site?
- Who performs reconstruction if my wound needs a flap or graft?
- How long should I expect to be at the office on the day of surgery?
- What does my insurance cover, and what will I be responsible for?
Coverage details vary by plan, so confirm them directly with the practice and your insurer rather than relying on a directory listing or an online summary. For patients comparing providers, it also helps to ask how many stages a typical case requires at that office and whether the surgeon handles the reconstruction personally.
Frequently Asked Questions
Is Mohs surgery painful?
The area is numbed with local anesthesia before any tissue is removed, so most patients feel pressure or movement rather than sharp pain during the stages. Once the numbing wears off, soreness at the site is normal and manageable with standard post-procedure care. Your surgeon will give you specific instructions for pain control, dressing changes, and activity limits based on the size and location of your repair.
How do I choose a Mohs surgeon in Denver?
Start with credentials. Look for a board-certified dermatologist who completed a dedicated Mohs fellowship, since that training covers both the surgery and the microscope work. Then ask practical questions about on-site tissue processing, who performs reconstruction, and how your insurance applies. Denver has providers across Cherry Creek, central Denver, and Aurora, so you have options and can compare before you book.
Will I have a scar after Mohs surgery?
Any procedure that removes skin leaves a scar, and Mohs surgery is no exception. The advantage is that the removal of healthy skin is minimized and the surgeon who clears the cancer also plans the closure, which supports the best possible cosmetic result. Reconstruction on visible areas such as the nose, forehead, and chin is planned around how the scar will mature over the following months.
Can Mohs surgery treat any type of skin cancer?
Mohs surgery is a highly specialized treatment for the removal of skin cancer, and it delivers the highest cure rate of all skin cancer treatments, approaching 99% for tumors that have not previously been treated. Even so, not every skin cancer needs it. Small, low-risk tumors may be handled with another method after your dermatologist weighs the tumor type, location, size, and history.
If you have been told you need Mohs surgery in Denver, the most useful next step is a direct conversation about your specific tumor. Ask who will read your slides, ask who will close the wound, and ask what your recovery will realistically involve. Those three answers will tell you more about your care than any ranking or directory list, and they put you in a much better position to move forward with confidence.
Skin Cancer Screening Cost in Denver: Pricing and Coverage
A skin cancer screening is one of the few medical visits where the price can swing widely depending on where you go, what kind of clinician you see, and whether your insurance treats the visit as preventive care. Published cost figures for a full-body skin check generally land between $100 and $300 without insurance, with dermatologist-performed exams clustering in the $120 to $300 range.
Denver patients face the same broad pricing band as the rest of the country, but the exact number depends on the practice, the type of visit, and your specific plan. This guide breaks down what the published data shows, how coverage usually works, and what to confirm before you book so there are no surprises on the bill.
What You Are Paying For During a Skin Check
A skin cancer screening is a visual examination. A clinician looks over your skin, often from head to toe, checking for spots, moles, or lesions that look new, changing, or otherwise unusual. The visit also includes the clinical judgment behind it: deciding whether something needs to be watched, photographed, or biopsied.
The fee you pay reflects the time and expertise involved, plus the administrative side of the visit. Because there is no single national price list, two offices in the same city can charge different amounts for what sounds like the same appointment. That is why asking for the self-pay rate upfront is worth the phone call.
Typical Skin Cancer Screening Costs Without Insurance
The published ranges below come from cost surveys and consumer health resources. They represent typical national figures rather than a guaranteed rate at any one office, and your actual cost may be higher or lower depending on the complexity of the exam and whether a board-certified dermatologist performs it.
| Type of visit | Typical cost without insurance |
|---|---|
| Full-body check by a dermatologist | $120 to $300 |
| General skin cancer screening | $100 to $200 |
| Dermatologist visit paid out of pocket | $150 to $300 |
| Teledermatology case | $40 to $80 |
| Insurance copay for a dermatologist visit | $30 to $75 |
The lower end of the range usually reflects a straightforward visual exam. The higher end can reflect a more detailed evaluation or a specialist practice. For comparison, published figures for a metro area like Phoenix run $100 to $250, which sits inside the same national band. There is no separately published Denver rate in the sources reviewed here, so treat the national ranges as your starting point and confirm the real number with the office or your insurer.
How Insurance Coverage Usually Works
Most private insurance companies, along with Medicare and Medicaid, cover the cost of certain routine cancer screenings. That sounds straightforward, but skin checks sit in a gray area because a screening visit and a problem-focused visit can be billed differently.
A skin screen performed as part of an annual physical through a primary care physician is usually covered, since it folds into the preventive visit. When you see a dermatologist specifically for a skin check, some plans cover it as preventive care and others treat it as a specialist visit. In the second case, the charge may apply to your deductible or require a copay, which published figures place at roughly $30 to $75.
The practical step is to call the number on the back of your insurance card and ask two questions: how a skin cancer screening is classified under your plan, and what your responsibility would be for a preventive visit versus a diagnostic one. Getting the answer in writing or noting the reference number of the call can help if the claim is processed unexpectedly.
Denver Pricing: What to Confirm Before You Book
Colorado Dermatology Center is a South Denver practice led by board-certified dermatologist Dr. James M. Swinehart, whose clinical experience spans more than three decades. The practice handles medical, surgical, and cosmetic dermatology, with a strong focus on skin cancer treatment, including MOHS micrographic surgery.
Because self-pay rates change and vary by the type of visit, the most reliable approach is to contact the office directly and ask for the current fee for a skin cancer screening, along with what the visit includes. It also helps to confirm whether the practice will bill your insurance and, if so, which billing codes the visit would use. Those codes determine whether your plan processes the visit as preventive or diagnostic care, which in turn determines what you owe.
If you have a specific spot that worries you, say so when you schedule. A focused evaluation of a concern is a different appointment than a full-body screening, and the cost structure can differ.
If a Suspicious Spot Is Found: Biopsy and Follow-Up Costs
A screening itself does not remove or test anything. If the clinician sees something that needs a closer look, the next step may be a biopsy, where a sample of tissue is taken and sent to a lab for examination. That step typically carries its own charges, and how much you pay depends on your plan, whether you have met your deductible, and how the claim is categorized.
The sources reviewed here do not include specific biopsy or pathology pricing, so anyone who needs one should ask their insurer directly about coverage for a skin biopsy and laboratory analysis before the procedure. Requesting a cost estimate from both the practice and the insurance company is a reasonable step, especially early in a plan year when a deductible may not yet be met.
Free and Low-Cost Screening Options
Cost should not be the reason a suspicious spot goes unchecked, and there are established programs built around that idea.
- The American Academy of Dermatology runs its free skin cancer check program, the organization’s longest-standing public health effort. Dermatologists have conducted more than 2.9 million free checks through it.
- Destination Healthy Skin travels to roughly 40 cities around the United States each spring and autumn, offering free skin cancer screenings and educational materials.
- The Prevent Cancer Foundation points people without insurance toward free and low-cost medical care in their community, and suggests contacting a local hospital or health care facility to ask whether it offers routine cancer screening or testing through foundation or outreach programs, including mobile testing.
These options fill up quickly and availability varies by season, so checking program websites for current schedules is the best way to plan.
Ways to Lower Your Out-of-Pocket Cost
Several practical moves can shift the number you pay.
- Ask whether the visit can be handled during an annual physical with your primary care physician, which is usually covered as preventive care.
- Confirm with your insurer how a dermatology skin check is classified before you book, so you know if it falls under preventive benefits or a deductible.
- Consider teledermatology for a specific concern. Published pricing runs about $40 to $80 per case, and these visits are often insured.
- Request the self-pay rate if you are paying cash, since offices sometimes have a different price for uninsured patients.
- Watch for free screening events in your area, particularly in spring and autumn.
Questions to Ask When You Schedule
A short list of questions before the appointment can prevent billing confusion later.
- What is the current cost of a full-body skin cancer screening if I pay out of pocket?
- Do you bill my insurance, and how is a screening visit coded?
- Is this visit treated as preventive care or as a specialist visit under my plan?
- What would a biopsy cost if one is needed, and is pathology included?
- Are there any fees for follow-up visits related to the same concern?
Screening recommendations matter as much as price. The AAD recommends annual exams for adults with risk factors, so the right cadence for you is a conversation worth having with your dermatologist rather than something to decide based on cost alone.
Frequently Asked Questions
How much does a skin cancer screening cost without insurance?
Published figures put a full-body skin check by a dermatologist at roughly $120 to $300, while general screening ranges run about $100 to $200. Dermatologist visits paid entirely out of pocket are often quoted at $150 to $300. The final number depends on the practice, the complexity of the exam, and whether a board-certified dermatologist performs it, so confirm the rate when you schedule.
Does insurance cover skin cancer screenings?
Most private insurance companies, Medicare, and Medicaid cover the cost of certain routine cancer screenings. A skin screen done as part of a primary care annual physical is usually covered. When a dermatologist performs the screening, some plans cover it as preventive care while others treat it as a specialist visit, which may mean a copay of about $30 to $75 or a charge toward your deductible.
Can I get a free skin cancer screening?
Yes, free options exist. The American Academy of Dermatology’s free skin cancer check program has provided more than 2.9 million free checks. Destination Healthy Skin visits roughly 40 cities each spring and autumn with free screenings and educational materials. The Prevent Cancer Foundation also directs people without insurance to free and low-cost care in their community, including hospital outreach and mobile testing programs.
Is teledermatology a cheaper way to get a skin check?
Teledermatology is generally the lowest-cost option in the published data, running about $40 to $80 per case, and these visits are often covered by insurance. It works best for evaluating a specific spot or concern rather than a comprehensive head-to-toe screening. If you have multiple spots or a history of skin cancer, an in-person exam with a dermatologist is usually the better fit.
What happens if the dermatologist finds something suspicious?
A screening does not involve removing or testing tissue. If something needs closer evaluation, the clinician may recommend a biopsy, in which a sample is taken and sent to a lab. Biopsies typically carry separate charges, and the sources reviewed here do not include specific pricing. Ask your insurer about coverage for a skin biopsy and pathology before the procedure.
Mohs Surgery Recovery: What to Expect and How Scars Heal
Mohs surgery is a precise, outpatient procedure used to remove high-risk skin cancer while preserving healthy tissue. The surgeon removes the cancer in thin layers and examines each layer under a microscope, which allows for complete tumor removal and high cure rates. For most patients with basal cell carcinoma or squamous cell carcinoma, Mohs surgery offers a highly effective treatment option. Once the procedure is finished, attention shifts to recovery. Knowing what to expect during healing, how to care for the wound, and how the scar will change over time can make the days and weeks after surgery much easier to manage. The recovery process has clear phases, and each phase has its own set of care instructions.
Understanding Mohs Surgery and the Healing Process
Mohs surgery is considered a precise method for treating certain skin cancers because it allows the surgeon to see exactly where the cancer ends. The layer-by-layer excision means healthy tissue is preserved whenever possible, and the microscopic examination of each layer helps confirm that the tumor has been completely removed. This approach is most effective for treating basal cell carcinoma and squamous cell carcinoma, two of the most common forms of skin cancer.
Recovery from Mohs surgery is not a single event but a process with distinct phases. The first 48 hours focus on protecting the fresh wound. The first two weeks involve dressing changes and basic wound care. After that, the body continues to repair the deeper layers of skin, and the scar gradually matures over many months. Understanding these phases can help you set realistic expectations and follow the right care steps at the right time.
The First 48 Hours: Protecting the Surgical Site
The first 24 to 48 hours after Mohs surgery are the most delicate part of the recovery process. Your surgeon will place a dressing over the surgical site, and that dressing should be left undisturbed during this initial window. Touching, changing, or removing the dressing too early can disrupt the healing wound and increase the risk of complications.
Minor bleeding or oozing may occur within the first 48 hours, and this is normal. If it happens, apply firm, constant pressure with a clean, dry piece of gauze directly on the dressing. Hold the pressure until the bleeding stops. This simple step usually resolves the issue, but contact your surgeon if bleeding continues or seems heavy.
During these first two days, minimize physical activity as much as possible. Avoid anything that may raise your blood pressure or put tension on your incision. Heavy lifting should be avoided entirely during this early period. Keeping your body calm and your heart rate steady gives the wound the best chance to begin healing properly.
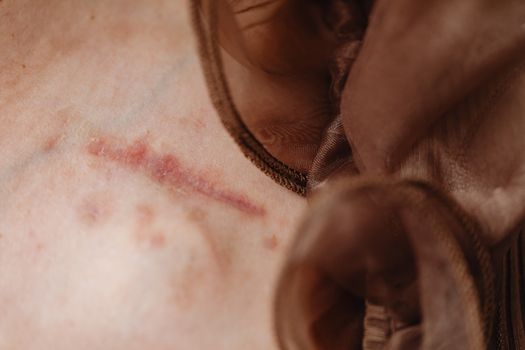
Wound Care During the First Two Weeks
Bandages are typically worn for 10 to 14 days after Mohs surgery. During this time, the wound needs consistent but gentle care. Cleanse the area once or twice daily with mild soap and lukewarm water. Keep the wound clean and moisturized, and follow your surgeon’s instructions for changing the dressing and applying any prescribed ointments.
Avoid picking or scratching the surgical site, even when it begins to itch or feel uncomfortable. Picking at the wound can disrupt healing, increase the risk of infection, and lead to a more noticeable scar. If the area feels irritated, resist the urge to touch it and let your surgeon know at your follow-up appointment.
Simple daily habits make a big difference during this period. Pat the area dry rather than rubbing it, and wash your hands before and after any dressing change. If you have questions about how the wound looks or how often to change the dressing, reach out to your surgeon’s office for guidance. It is always better to ask than to guess about a healing wound.
Activity Restrictions and Returning to Normal Life
Most patients will need to avoid strenuous physical activities for a minimum of one to two weeks after Mohs surgery. This restriction is essential to avoid putting tension on the incision while it is still healing. Intense exercise raises your heart rate and blood pressure, which can increase blood flow to the surgical site and lead to bleeding or swelling.
During the first 48 hours, minimize all physical activity. In the weeks that follow, most patients recover within several weeks, though the exact timeline varies based on the size and location of the surgical site and the type of wound closure used. Light activities may be comfortable sooner, but anything that pulls, stretches, or strains the area should wait.
Listen to your body during recovery. If an activity causes discomfort or a pulling sensation around the wound, stop and rest. Your surgeon will let you know when it is safe to resume exercise, heavy lifting, and other demanding activities.

How Mohs Surgery Scars Heal Over Time
Scarring is one of the most common concerns for patients preparing for Mohs surgery, especially when the procedure is performed on the face, neck, or another visible area. The reassuring news is that Mohs scars improve significantly over time, but the process requires patience.
Scars from Mohs surgery continue to heal for 12 to 18 months after the procedure. In some cases, it can take up to a year for the surgical site to fully heal. During this period, the scar will flatten significantly and fade in color. The bright, raised scar you see in the early weeks is not the final result.
Most Mohs surgery scars take 3 to 12 months to fully heal. The way the wound is closed has a direct impact on the healing process. Some wounds are stitched closed, which typically produces a thin, linear scar. Other wounds heal by second intention, meaning the area is left open to heal gradually from the inside out. Each approach has a different healing timeline and produces a different scar pattern. Your surgeon can explain which method was used and what you can expect.
After the dressing comes off, the scar will likely look red and may feel raised or firm. This is a normal part of the healing process. Over the following months, the body gradually remodels the scar tissue, which is why the scar flattens and fades in color. The final appearance of the scar depends on many factors, including its location, your skin type, and how well you followed the post-operative care instructions.
Mohs Surgery Recovery Timeline at a Glance
The table below summarizes the key recovery milestones after Mohs surgery.
| Timeframe | What to Expect |
|---|---|
| First 24 to 48 hours | Keep the dressing undisturbed; minimize physical activity; avoid heavy lifting; minor bleeding or oozing may occur |
| First 10 to 14 days | Bandages are worn; cleanse gently once or twice daily with mild soap and lukewarm water; avoid picking or scratching |
| 1 to 2 weeks | Strenuous physical activities should be avoided |
| Several weeks | Most patients recover within several weeks |
| 3 to 12 months | The scar continues to mature and typically takes this long to fully heal |
| 12 to 18 months | Scars continue to heal, flattening significantly and fading in color |
Tips for Supporting Your Scar’s Healing
Good wound care is the most reliable way to support scar healing after Mohs surgery. Keep the area clean and moisturized, and cleanse it gently once or twice daily with mild soap and lukewarm water. Follow your surgeon’s instructions for dressings and any ointments or creams they recommend.
Avoid picking or scratching the site, and be patient with the appearance of the scar. Early in the healing process, scars often look red, raised, or uneven. Over the following months, they flatten and fade. Ask your surgeon about protecting the scar from sun exposure and whether any scar care products are appropriate for your specific wound.
Consistency matters more than perfection. A simple daily routine of gentle cleansing and dressing changes, followed faithfully, gives your scar the best chance to heal well. If you have concerns about how the scar is developing, bring them up at your follow-up visits.
Frequently Asked Questions
How long does Mohs surgery recovery take?
Most patients recover within several weeks, though the full healing process takes longer. The surgical site may take up to a year to fully heal, and the scar continues to mature for 12 to 18 months. Bandages are typically worn for the first 10 to 14 days, and strenuous activities should be avoided for at least one to two weeks.
Will my Mohs surgery scar go away?
A scar will not disappear completely, but it will improve significantly over time. Scars from Mohs surgery continue to heal for 12 to 18 months, flattening and fading in color as they mature. Most scars take 3 to 12 months to fully heal, and the final result is typically much less noticeable than the fresh wound.
When can I exercise after Mohs surgery?
Most patients need to avoid strenuous physical activities for a minimum of one to two weeks after Mohs surgery. During the first 48 hours, minimize all physical activity and avoid heavy lifting. This is essential to avoid tension on the incision and to prevent bleeding. Ask your surgeon when it is safe to resume your normal exercise routine.
What should I do if bleeding occurs after surgery?
Minor bleeding or oozing may occur within the first 48 hours after Mohs surgery. If this happens, apply firm, constant pressure with a clean, dry piece of gauze directly on the dressing. Hold the pressure until the bleeding stops. If bleeding is heavy or does not stop, contact your surgeon’s office for guidance.
Cellulite Release Technique
To find out more about how to treat cellulite “dimples” on the
thighs or backside, call us at (303) 744-1202 for a consultation!
Neck and Jowl Lift
Dr. Swinehart has perfected a Neck and Jowl Lift, combined with tumescent liposuction through 3 tiny incisions, performed in the office on an outpatient basis! To schedule a consultation, please call (303) 744-1202.