Deep Wrinkle Treatment vs. Fine Line Care: What Works for Each
 November 13, 2026 |
 Author
A fine line and a deep fold can sit an inch apart on the same face and still need completely different care. That is why a deep wrinkle treatment plan built around fillers or collagen stimulation can disappoint when it is applied to surface texture, and why a good night cream rarely softens a fold that has been forming for years. The dividing line is depth and what is causing the crease. Once you know which problem you are looking at, the options narrow quickly. This guide separates the two concerns, explains what each type of treatment actually does, and shows where the categories overlap.
Why Depth Decides the Plan
Wrinkles are not one condition. Fine lines sit in the upper layers of the skin and usually show up as texture: thin creases, uneven tone, roughness that makeup catches on. Deep wrinkles involve something more structural. Volume loss beneath the skin and repeated muscle movement both play a part, which is why a deep fold stays visible even when the face is at rest.
Surface products are formulated for the first problem. Injectable and energy-based treatments are designed for the second. Matching the treatment to the depth keeps expectations realistic and avoids spending on a product or procedure that was never aimed at your concern in the first place.
How to Tell a Fine Line From a Deep Wrinkle
Before comparing treatments, work out what you are actually looking at. A few simple checks in front of a mirror will separate most fine lines from structural folds:
- Relax your face completely. A line that disappears when the muscles are relaxed is usually a movement line. A crease that remains is deeper.
- Change the lighting. Fine lines show up best in raking side light. Deep folds cast a visible shadow even in flat, front-facing light.
- Look at texture versus shadow. Roughness and thin surface creases point toward fine line care. A groove or hollow points toward volume loss.
- Note the location. Forehead lines and crow’s feet are commonly described as dynamic wrinkles, while nasolabial folds and marionette lines are commonly described as areas of volume loss.
These checks are a starting point, not a diagnosis. A dermatologist can assess skin thickness, sun damage, and volume loss in a short examination and confirm which category your concern falls into.
Deep Wrinkle Treatment Options
Deep wrinkles are addressed with treatments that work below the surface or that change how the muscle behaves. Several categories exist, and the right choice depends on whether the crease is driven by movement, volume loss, or both.
Botulinum Toxin for Movement Lines
Treatment options include botulinum toxin and fillers, and the two are chosen for different jobs. Botulinum toxin therapy is used to diminish dynamic wrinkles, the lines created by repeated muscle contraction. Crow’s feet and forehead lines are the classic examples, and many patients choose botulinum toxin therapy for exactly those areas. It relaxes the muscle rather than filling a hollow, so it does little for a fold caused by volume loss on its own.
Dermal Fillers for Volume Loss
Dermal fillers such as hyaluronic acid restore volume to areas with deep wrinkles, including the nasolabial folds and marionette lines. The logic is straightforward: if a fold is created by a loss of support beneath the skin, adding volume back into that area softens the crease. This makes fillers a structural treatment rather than a surface one, and it is why they are grouped with deep wrinkle care rather than with creams and serums.
Sculptra and Collagen Stimulation
Sculptra is FDA-approved to help treat mild to deep facial wrinkles and folds. It is composed of poly-L-lactic acid, and it is injected deep rather than placed just under the surface. That deep placement is the key difference from a standard filler. Because it works through the skin’s own remodeling response rather than by directly filling a space, the approach and the timeline differ from hyaluronic acid fillers, and a consultation should cover those differences before treatment.
Skin Tightening and Light-Based Treatments
Energy-based options round out the deep and mid-depth category. Skin tightening treatments such as EndyMed are listed among proven wrinkle options, and Forever Young BBL is described as targeting fine lines, sun damage, and uneven skin tone. Notice that the second one is a fine line and sun damage tool as much as a wrinkle tool. Light-based treatments are often chosen when tone and texture are part of the complaint, not just depth.
Fine Line Care: Topicals and Daily Habits
Fine lines respond to consistent surface care and to reducing the exposures that create them. Results build slowly, and no cream reverses a structural fold, but the right routine can improve texture and tone over time.
Retinol and Night Creams
Dermatologists recommend wrinkle creams that include retinol-based night products, and published recommendations have named options such as RoC Retinol Correxion Deep Wrinkle Anti-Aging Night Cream and M-61 Hydraboost. Deep wrinkle skin care ranges also include anti wrinkle creams, serums, and face moisturizers designed to reduce the appearance of wrinkles. Look for a formula you can use consistently, since irregular use is the most common reason a topical routine fails to show results.
Daily Habits That Support Fine Line Care
Prevention habits appear on nearly every dermatology list for a reason. Commonly recommended steps include wearing sunscreen, limiting sugar intake, quitting smoking, changing sleep position, and washing your face. Other natural suggestions that circulate include coconut oil, beta carotene, and lemon balm leaf tea. Those last items have far less support than sun protection and smoking cessation, so treat them as optional additions rather than substitutes for proven habits, and ask your dermatologist before adding supplements or new products to your routine.
Side-by-Side Comparison
| Feature | Fine lines | Deep wrinkles |
|---|---|---|
| Where the change sits | Surface texture, tone, and thin creases | Structural folds and hollows, visible at rest |
| Common drivers | Sun damage, surface texture, uneven tone | Volume loss and repeated muscle movement |
| Typical approaches | Retinol night creams, serums, moisturizers, light-based treatments such as Forever Young BBL | Botulinum toxin for dynamic lines, hyaluronic acid fillers for volume loss, Sculptra, skin tightening |
| Example treatment areas | Overall facial texture and sun damage | Nasolabial folds, marionette lines, crow’s feet, forehead lines |
| Pace of change | Gradual, built through consistent routine | Determined by the procedure and confirmed at consultation |
When the Two Categories Overlap
Most faces do not fall neatly into one column. A patient with deep nasolabial folds often has fine lines around the eyes as well, and the best facial wrinkle treatment or combination of treatments is determined during a consultation rather than chosen from a menu. Published treatment lists reflect that reality by grouping Botox, skin tightening, and facial treatments such as DiamondGlow facials together, since different tools address different layers of the same face.
A sensible plan usually starts with the structural issue. Correcting volume loss and movement first often makes surface texture easier to assess, and it prevents a patient from investing months in creams that were never going to change a fold. From there, a topical routine supports the result and protects against further sun damage. Your dermatologist can sequence the steps and explain what each treatment can and cannot do.
Frequently Asked Questions
Can a wrinkle cream fix a deep wrinkle?
Deep wrinkles involve volume loss and muscle movement beneath the surface, while creams are formulated for surface texture. Dermatologists do recommend retinol-based night creams for fine lines and overall skin appearance, but a topical product is not designed to restore lost volume or relax a muscle. Deep folds usually need a structural option such as fillers, botulinum toxin, or a collagen-stimulating injectable.
What is the difference between dynamic and static wrinkles?
Dynamic wrinkles are created by repeated muscle contraction and include crow’s feet and forehead lines. Botulinum toxin therapy is used to diminish these lines by relaxing the muscle. Static wrinkles remain visible when the face is at rest and are more often linked to volume loss, which is why dermal fillers and other structural treatments are used for folds such as nasolabial and marionette lines.
Is Sculptra the same as a hyaluronic acid filler?
No. Sculptra is composed of poly-L-lactic acid and is FDA-approved to help treat mild to deep facial wrinkles and folds, and it is injected deep. Hyaluronic acid fillers are used to restore volume directly to areas with deep wrinkles such as nasolabial folds and marionette lines. Because the materials and placement differ, the appropriate choice should be made at a consultation.
How do I know which treatment I need?
Start by checking whether the line remains visible when your face is completely relaxed, then have a dermatologist confirm. The best treatment or combination of treatments for facial wrinkles is determined during a consultation, where skin thickness, sun damage, volume loss, and muscle movement can all be assessed together. Guessing from a photograph or a product label rarely gives an accurate answer.
 Posted in

Cyst Acne Scar Treatment: When Deep Scars Need Surgery
Cystic acne leaves a particular kind of mark behind. Some of those marks soften with time. Others stay in the skin as dips, pits, or firm ridges that no serum seems to touch. If you have spent months layering products onto a scar that has not changed at all, the problem may not be the product. It may be the depth of the scar. This article explains how dermatologists separate deep scars from shallow ones, which treatments actually reach below the surface, and when a surgical approach makes more sense than another bottle of cream.
Why cystic acne scars are so stubborn
Acne scars can be one of the most stubborn skin issues to treat, and the research is consistent on one point: while scars can fade, they rarely go away completely on their own. Cysts do leave scars. That is why the conversation about scarring often starts while the acne is still active, rather than months later when the marks have already settled in.
A topical product sits on the outermost layer of skin. A scar that formed beneath that layer is structurally different from a surface blemish. A cream that helps with redness or discoloration may do very little for a depression or a firm band of tissue, because it never reaches the level where the change exists. This explains a common frustration: the color fades, but the texture does not. The scar looks less angry and just as deep.
What a cream can realistically do
Topical care has a real place in any scar plan. Gentle, non-comedogenic cleansers used twice a day are standard advice, and avoiding heavy oils and pore-clogging products helps reduce new lesions that would otherwise create new scars. Mild cases may respond to gentle cleansing along with supportive tools such as red light therapy. Good daily care keeps the skin calm and lowers the odds of adding to the problem.
What topicals generally cannot do is rebuild tissue. If a scar involves a loss of volume or a change in how the skin sits against what lies beneath it, no cream applied to the surface will restructure it. Expecting that outcome leads to years of buying products and no visible difference. The realistic goal for any scar treatment, topical or otherwise, is measurable improvement rather than erasure.
In-office options that reach deeper than a cream
For scars that do not respond to topicals, dermatologists have a broad set of non-surgical tools. Non-surgical options include laser resurfacing, chemical peels, microneedling, RF microneedling, PRP, BBL, and dermal fillers. Fractional lasers in particular can help remove surface imperfections and significantly reduce the appearance of scarring, and there are different types of fractional laser platforms used for this purpose.
- Laser resurfacing, including fractional lasers
- Chemical peels
- Microneedling and radiofrequency microneedling
- Platelet-rich plasma (PRP)
- Broadband light (BBL)
- Dermal fillers
- Microdermabrasion, which a dermatologist may suggest in some cases
Which of these fits depends on how severe the scars are. A shallow, mostly discolored scar and a deep, pitted scar are not the same problem, so they do not call for the same treatment. In some cases a doctor or dermatologist may suggest a chemical peel or microdermabrasion to improve the appearance of the skin. In other cases those lighter approaches are simply not enough, and choosing them anyway wastes time and money.
When a deep scar needs surgery instead of cream
Some scars do not respond well to surface-level treatment because the problem is not on the surface. When a scar creates a true change in the contour of the skin, a dermatologist may recommend surgical scar revision rather than another round of topicals or light-based treatment. The goal is not to erase the scar. It is to change its structure so it sits more evenly with the skin around it.
Surgery is not automatically the first step for every scar, and it is not only a last resort after everything else fails. For the right scar, a surgical approach can be more direct and more efficient than a long series of treatments that never reach the depth of the issue. The reverse is also true: a surgical plan applied to a scar that would have responded to a peel or a laser is unnecessary. The distinction matters, and it is why an in-person evaluation carries more weight than any online description of a scar.
The specifics of a surgical plan depend on the scar itself, where it sits, how many there are, and how your skin behaves. Those details are settled during a consultation with a board-certified dermatologist, not guessed at beforehand.
How a dermatologist decides which treatment fits
Treatments depend on how severe the scars are, so the evaluation starts with the scars themselves. A dermatologist looks at the type of scar, how deep it sits, how many are present, and how much of the surface is affected. Active acne is part of the picture too, since creating new scars while treating old ones accomplishes very little.
Partnering with a board-certified dermatologist can help you diminish scarring in a way that matches your skin rather than a general routine. At Colorado Dermatology Center in South Denver, Dr. James M. Swinehart brings more than three decades of clinical experience to acne scar revision, and the practice offers procedures that many other practices do not. That range matters, because a clinician who only offers one type of treatment will tend to recommend that treatment for every scar.
Daily care while you treat a deep scar
Whatever procedure you choose, the basics still apply between visits. These habits support the plan rather than replace it.
- Cleanse twice daily with a gentle, non-comedogenic cleanser
- Avoid heavy oils and pore-clogging products
- Keep active acne under control so new scars do not form
- Use supportive tools like red light therapy for mild cases, understanding they are not a substitute for structural treatment
- Take consistent photos so progress is measured rather than remembered
Setting realistic expectations
Scars can fade, and they can be improved substantially, but they rarely disappear completely. Anyone promising a total erasure is overselling. What good treatment offers is a visible reduction in depth, texture, and color, often built over a series of sessions rather than a single visit. That is a modest-sounding goal that makes a large difference in how skin looks in daylight and in photographs.
If a scar has not budged after a reasonable course of topical care, that is useful information rather than a failure. It suggests the scar needs a different category of treatment, and it is a good reason to have a dermatologist look at it directly instead of starting another cream.
Frequently Asked Questions
Can a cream remove a deep cystic acne scar?
Generally no. Creams work on the surface layers of the skin, while a deep scar involves structure beneath that level. Topicals can help with discoloration and can support overall skin health, and mild cases may respond to gentle cleansing and supportive tools. A scar that creates a real change in contour usually needs a procedure rather than a product.
Do cystic acne scars go away on their own?
They can fade, but they rarely go away completely without treatment. Cysts are known to leave scars, and the marks that remain often improve somewhat over time while still staying visible. Partnering with a board-certified dermatologist is the more reliable path to diminishing a scar that has already formed and stayed put.
Which non-surgical treatments can improve acne scars?
Non-surgical options include laser resurfacing, chemical peels, microneedling, RF microneedling, PRP, BBL, and dermal fillers. Fractional lasers can help remove surface imperfections and significantly reduce the appearance of scarring. A dermatologist may also suggest a chemical peel or microdermabrasion in some cases. The right choice depends on how severe the scars are.
How does a dermatologist decide between a procedure and surgery?
The decision comes down to scar depth, scar type, how many scars are present, and how the skin responds. Scars that sit near the surface often respond to lasers, peels, or microneedling. Scars that create a genuine contour defect may call for surgical revision instead. That judgment is made during an in-person evaluation, not from a photo or a description.
A deep cystic scar is not a personal failing and it is not proof that you have not tried hard enough. It is a structural problem, and structural problems respond to treatments designed for structure. If a cream has had its chance and the scar looks the same, the next step is a conversation with a board-certified dermatologist who can look at the scar, explain what is happening beneath it, and lay out the options that actually reach that depth.
Dermatology Clinical Trials in Denver: What Joining a Study Is Really Like
Denver readers who search for dermatology clinical trials usually want a straight answer about the experience, not just a list of studies. They want to know what a visit involves, how much time it takes, what questions to ask, and whether a research site feels like a good fit. Colorado Dermatology Center, a South Denver practice led by board-certified dermatologist Dr. James M. Swinehart, is one local option. The practice offers clinical trials in psoriasis, eczema, acne, seborrheic dermatitis, warts, and precancerous spots.
Why Dermatology Clinical Trials in Denver Attract Volunteers
Denver has a broad clinical research presence. Public trial directories list paid clinical trials in Denver, along with studies across many health conditions. Colorado has actively recruiting trials organized by city, including Denver. For someone with a persistent skin condition, that means dermatology studies sit inside a larger research ecosystem. The appeal is practical: a study can offer another way to learn about your condition, receive structured follow-up, and contribute to information that may help future patients. A study is not a standard office visit, so it helps to separate general curiosity from a real willingness to follow a research plan.
Dermatology trial listings cover a wide range of skin concerns. Some directories include dermatological condition studies enrolling across the United States and Canada. Denver residents may see options tied to local sites or to broader multicenter research. Focus on studies that match your skin condition and your comfort with the time involved. A long list of listings does not mean every study is a fit.
What Colorado Dermatology Center Studies
Colorado Dermatology Center offers clinical trials in psoriasis, eczema, acne, seborrheic dermatitis, warts, and precancerous spots. These are common reasons people see a dermatologist, and each can involve ongoing management. A study in one of these areas may be relevant if your condition has already been discussed with a clinician and you want to know whether research is a reasonable next conversation. The practice combines more than three decades of clinical expertise with medical, surgical, and cosmetic dermatology, which matters if your skin history includes more than one concern.
For direct questions about current studies, the practice lists 303-744-7000 as its contact number. Use that call to ask which trials are enrolling, what the study involves, and whether your condition matches the current criteria. A phone call is a low-pressure way to gather facts before deciding whether to pursue an in-person conversation. Current availability can change, so confirm the details with the practice rather than relying on an old listing.
The First Conversation: What to Ask Before You Join
Joining a study should feel like a decision, not a sales pitch. A useful first conversation with any Denver research site should cover the purpose of the study, what participants are asked to do, how long the study lasts, and what visits are required. Ask who covers study-related costs, whether compensation is available for time and travel, and what happens if you want to stop. Those details can vary by study, so get them in writing or ask where they are described in the consent materials.
- Ask what skin condition or treatment the study is evaluating.
- Ask how many visits are expected and whether any are longer than a typical office visit.
- Ask whether travel, parking, or time compensation is available, and confirm the details with the site.
- Ask what is known about risks and what follow-up looks like.
- Ask who to call with questions after you leave the office.
Denver listings sometimes mention paid clinical trials or compensation for time and travel, but payment is not a reason by itself to join. Treat any payment information as one detail among many. The more important question is whether the study fits your health situation, your schedule, and your willingness to follow the study plan. If a site cannot explain the basics in plain language, ask again or consider another option.
What a Study Visit Can Feel Like
A dermatology study visit can look different from a routine appointment because research follows a plan. You may be asked about your skin history, current products, medications, and symptoms. You may also be asked to complete questionnaires or have your skin examined in a consistent way. The routine can feel more structured than a standard visit, and that structure is part of how researchers compare information over time. The exact steps depend on the study, so ask the site to walk you through a typical visit before you enroll.
For people with psoriasis, eczema, acne, seborrheic dermatitis, warts, or precancerous spots, consistency matters. A study may ask you to track changes, avoid certain products, or return at set intervals. The site should explain those expectations in plain language. If you leave the first conversation unsure about what a visit involves, ask for a walkthrough. A good research conversation should leave you with fewer unknowns, not more.
Denver Logistics and the Practical Side of Participation
Denver is a car-oriented city for many patients, and a study can add appointments to an already busy schedule. Before you commit, map the trip from home or work, think about parking, and consider whether the visit times work with your obligations. The research pack for this topic does not list specific addresses or hours, so confirm those details directly with Colorado Dermatology Center at 303-744-7000. If you are comparing more than one site, use the same questions for each so the answers are easier to compare.
Travel and time compensation may be available for some studies, according to local trial listings, but availability can differ by study. Ask whether compensation applies, how it is handled, and whether it affects anything else. Keep the practical questions separate from the medical ones. You want to know both whether the study is a good clinical fit and whether it fits your real life.
How to Decide Whether a Study Is Right for You
There is no single profile for a good research volunteer. Some people are drawn by close follow-up. Some want to learn more about a condition that has been hard to manage. Others are interested in contributing to dermatology research and are comfortable with the structure. What matters is that you understand the commitment and feel able to ask questions without pressure.
Start with your own priorities. Are you able to attend the required visits? Do you have a way to get to appointments? Are you comfortable with the study design once it is explained? The research team should answer those questions, but you should also know your own limits. If a study feels rushed or unclear, wait. A legitimate research conversation can survive a second call or a follow-up question.
How to Inquire About Dermatology Clinical Trials in Denver
To begin, contact Colorado Dermatology Center at 303-744-7000 and ask about current dermatology clinical trials. Mention the condition you are interested in, such as psoriasis, eczema, acne, seborrheic dermatitis, warts, or precancerous spots, so the staff can point you toward relevant information. Ask whether a prescreening conversation is available and what records or details you should bring. If you are also browsing Denver trial listings, use them as a starting point, not a final answer. Confirm every detail with the site running the study.
Denver has many clinical research options, and that is a good reason to be specific. The right study for you should match your skin condition, your schedule, and your comfort with the research process. A careful conversation at the start can make the rest of the experience feel much more manageable.
Frequently Asked Questions
These answers cover common questions about dermatology clinical trials in Denver.
Are dermatology clinical trials in Denver paid?
Some Denver trial listings mention payment or compensation for time and travel, but payment is not universal. Colorado Dermatology Center can explain whether a specific study offers compensation and how it is handled. Ask about any payment before you enroll, and do not treat compensation as the main reason to join. The study must still be a good fit for your skin condition and schedule.
What skin conditions are studied at Colorado Dermatology Center?
The practice offers clinical trials in psoriasis, eczema, acne, seborrheic dermatitis, warts, and precancerous spots. Current availability can change, so call 303-744-7000 to ask which studies are enrolling. If your condition is not on that list, ask whether other studies or referrals are available. The practice is led by board-certified dermatologist Dr. James M. Swinehart.
Do I need a referral to join a study?
The research pack does not specify referral requirements for Colorado Dermatology Center studies. Ask the site directly when you call. A referral may depend on the study and your insurance, so get the answer for the specific trial you are considering. Bring any relevant records the staff requests. Do not assume a referral is required or that one is not needed.
Can I stop participating after I enroll?
Ask the research team to explain withdrawal before you enroll. Study rules and follow-up expectations can differ, and the consent materials should describe what stopping involves. If you are uncomfortable with the answer, do not join. A clear explanation at the start is part of choosing a research site that respects your questions and your time.
How do I compare Denver research sites?
Use the same questions for each site: what the study involves, how many visits are required, what compensation is available, and who to call with concerns. Confirm the details directly with the site running the study. Colorado Dermatology Center can be reached at 303-744-7000. Denver has multiple research options, so compare carefully rather than choosing the first listing you see.
Actinic Keratosis Treatment: Clearing Sun Damage Early
Decades of Colorado sun can leave their mark in ways that are easy to overlook. A rough patch on the scalp that feels like sandpaper. A scaly spot on the cheek that never quite smooths out with moisturizer. These are common descriptions of actinic keratosis, a precancerous lesion caused by long-term, excessive exposure to ultraviolet rays.
Actinic keratoses are not cancer. They are, however, a warning written directly on the skin, and dermatologists treat them for a straightforward reason: when left untreated, an actinic keratosis could turn into squamous cell carcinoma, one of the most common types of skin cancer. The good news is that the condition is very common and several effective treatment approaches exist, from freezing a single spot to treating an entire area of sun-damaged skin.
What Actinic Keratosis Is and Why Treatment Matters
An actinic keratosis, sometimes called a solar keratosis, is a precancerous skin lesion that forms on skin that has received years of sun exposure. The underlying cause is cumulative ultraviolet damage, which is why these lesions tend to appear on areas that see the most daylight over a lifetime, such as the face and scalp.
Two points matter for anyone deciding what to do about a rough, scaly patch:
- An actinic keratosis is not cancer in itself, but it has the potential to progress to squamous cell carcinoma if it is not treated.
- Because sun damage is usually spread across a region of skin rather than confined to one tiny point, a single visible lesion often sits within a broader area of damaged skin.
That second point shapes how dermatologists approach treatment. Some options target one lesion at a time, while others treat a whole field of sun-damaged skin. Choosing between them depends on how many lesions are present, where they are, how much surrounding damage exists, and the patient’s own health and preferences.
Recognizing Sun Damage Before It Becomes a Spot
Actinic keratoses typically appear as rough, scaly patches on sun-exposed skin. They can be small and easy to dismiss, and they may be more noticeable to the fingertips than to the eye. Because the same ultraviolet exposure that produces these lesions also raises skin cancer risk, an examination for actinic keratosis is also an opportunity to check the skin for other problems.
Anyone who has spent years outdoors, whether through work, sport, or simply living at altitude, has a reason to have suspicious patches looked at rather than monitored indefinitely at home. A dermatologist can distinguish actinic keratosis from other scaly conditions and decide whether a spot needs treatment or closer evaluation.
Lesion-Directed Treatment Options
Lesion-directed therapies focus on individual actinic keratoses. They are often a good fit when the number of spots is limited and each one can be identified clearly.
Cryosurgery
Cryosurgery is the most commonly used therapy for actinic keratosis. The procedure freezes the lesion, and the scaly skin patch falls off after a few days. Dermatologists apply the cold either by spraying it with a cryogun or by placing it directly on the lesion with a cotton swab.
Some actinic keratoses need more than one freeze to clear completely. Follow-up matters here, because a lesion that does not resolve as expected deserves another look rather than repeated attempts without reassessment.
When a Single Spot Deserves a Second Look
Not every rough patch is a straightforward actinic keratosis. A dermatologist may decide that a particular spot should be examined more carefully before or instead of routine destruction, especially if it behaves differently from the surrounding sun damage or does not respond to treatment. That clinical judgment is one of the reasons a dermatology visit is more than a quick freeze.
Field-Directed Treatment for Widespread Sun Damage
When sun damage covers a broad area, treating one visible spot at a time may leave a great deal of damaged skin behind. Field-directed therapies treat the region itself. Options include topical medications and photodynamic therapy.
Topical Medications
Several prescription creams are used for actinic keratosis. Treatment options cited in primary care guidance include Efudix, Actikerall, imiquimod, and Solaraze. One commonly described regimen is 5-fluorouracil cream, either 5% 5-FU cream or 4% 5-FU cream (Tolak), applied once a day for four weeks, with hands washed thoroughly after application.
Topical treatment courses can produce inflammation in the treated area. Guidance notes that if inflammation is significant, treatment can be reduced. That is a decision to make with the prescribing clinician rather than by adjusting the schedule alone, since the response is part of how the therapy works.
Photodynamic Therapy
Photodynamic therapy, often shortened to PDT, is quite effective for widespread lesions on the scalp and face. The dermatologist applies a light-sensitizing topical agent to the lesion, then activates it with light. Because it can cover a broad treatment area in a single session, PDT is frequently considered when sun damage is spread across the face or scalp rather than concentrated in one or two spots.
Comparing the Main Treatment Approaches
| Approach | Type | What the treatment involves |
|---|---|---|
| Cryosurgery | Lesion-directed | Freezing the actinic keratosis with a cryogun spray or a cotton swab; the scaly patch falls off after a few days, and some lesions require more than one treatment |
| Topical medications | Field-directed | Prescription creams applied at home over a course of weeks; for example, 5-FU cream applied once a day for four weeks |
| Photodynamic therapy | Field-directed | A light-sensitizing topical agent applied to the lesion, followed by light activation; quite effective for widespread lesions on the scalp and face |
There is no single best option for every patient. A dermatologist weighs the number and location of lesions, how much surrounding sun damage is present, how the skin has responded to past treatments, and how a given course of therapy fits into the patient’s routine.
What Recovery and Aftercare Look Like
Recovery depends on the treatment chosen. After cryosurgery, the treated scaly patch falls off within a few days. Topical therapy unfolds over weeks, and the skin’s visible response during that course is expected. Photodynamic therapy is delivered in the office, with the light-sensitizing agent applied beforehand.
Skin maintenance after actinic keratosis removal deserves real attention. The lesions that were treated are gone, but the ultraviolet damage that produced them is not reversed, and the same skin remains vulnerable. Daily sun protection and regular skin checks are the practical foundation for keeping new lesions from going unnoticed. A dermatologist can recommend a maintenance plan suited to how much sun damage is present and where it sits.
Why Follow-Up Matters More Than a Single Treatment
Actinic keratosis is a chronic condition of sun-damaged skin rather than a one-time event. New lesions can develop in the same areas that were treated, and additional areas of damage may become apparent over time. Follow-up visits allow a dermatologist to catch those changes early, when treatment is typically simpler.
This is also why patients should mention new rough patches between scheduled visits rather than waiting. An actinic keratosis that has been treated successfully does not mean the surrounding skin is now safe from further damage.
Getting Sun-Damaged Skin Evaluated in Denver
Colorado Dermatology Center is the South Denver practice of board-certified dermatologist Dr. James M. Swinehart, whose clinical experience spans more than three decades. The practice covers medical, surgical, and cosmetic dermatology, with particular emphasis on skin cancer treatment, including MOHS micrographic surgery.
For patients with rough, scaly patches on sun-exposed skin, that combination matters. An evaluation can confirm what a lesion is, sort out which spots need treatment, and build a plan that addresses the broader field of sun damage rather than only the spot that prompted the appointment. Patients who have had actinic keratoses treated before can also use a visit to review maintenance and decide whether another round of field therapy is appropriate.
Sun damage accumulates quietly over decades, and actinic keratosis is the visible signal that it has reached a point worth acting on. Clearing those lesions is not cosmetic housekeeping. It is precancerous skin being managed before it has a chance to become something more serious.
Frequently Asked Questions
Can actinic keratosis go away without treatment?
There is no reliable way to predict which lesions will stay quiet and which will progress, and an actinic keratosis has the potential to develop into squamous cell carcinoma if it is left untreated. Because that risk cannot be judged by looking in the mirror, a dermatologist should evaluate any new rough or scaly patch rather than waiting to see what happens.
Is cryosurgery better than a topical cream?
They solve different problems. Cryosurgery targets individual lesions and is the most commonly used therapy for actinic keratosis, while topical medications and photodynamic therapy treat a broader field of sun-damaged skin. A dermatologist chooses based on how many lesions are present, where they sit, and how much surrounding damage exists.
How long does actinic keratosis treatment take?
It varies by approach. After cryosurgery, the treated scaly patch typically falls off within a few days, though some lesions need more than one freeze. Topical courses run over weeks, such as 5-FU cream applied once daily for four weeks. Photodynamic therapy is performed in the office using a light-sensitizing agent followed by light.
Will new actinic keratoses appear after treatment?
They can. Treatment clears existing lesions, but the ultraviolet damage that caused them remains in the skin, so new spots may develop in the same sun-exposed areas. That is why dermatologists recommend ongoing skin checks and consistent sun protection after treatment rather than treating once and considering the matter closed.
When should a rough patch on the scalp or face be checked?
Any new, persistent, rough or scaly patch on sun-exposed skin is worth an evaluation, particularly if it does not heal, feels different from the skin around it, or changes over time. A dermatologist can confirm whether it is an actinic keratosis and discuss lesion-directed or field-directed treatment options.
Crow’s Feet Treatment for Softer Lines Without a Frozen Look
Crow’s feet are the fine lines that fan out from the outer corners of the eyes. They usually appear first when you smile, laugh, or squint, and over time some of them stay visible even when your face is at rest. The good news is that the same anatomy that creates these lines also gives a dermatologist several precise ways to soften them, and a skilled injector can do it without wiping the expression from your face.
Why Crow’s Feet Form in the First Place
The lines at the outer eye are tied to the orbicularis oculi, the ring of muscle that closes around the eye. Every smile, squint, and laugh contracts that muscle, and the skin over it folds in the same place again and again. Crow’s feet develop partly because the muscles around the eye keep pulling the skin into those folds.
Two things happen as a result. First, the folding becomes a habit, so the creases show up more easily and stay longer. Second, the skin itself changes, losing some of the support that once let it snap back flat. That is why a line that starts as a smile-only crease can eventually become a groove that is visible in a completely neutral face. Understanding which stage your lines are in is the single most useful step in choosing a treatment.
Dynamic Versus Static Lines: Matching the Treatment to the Line
Dermatologists generally sort crow’s feet into two groups, and the distinction explains why one person gets excellent results from injections while another needs a different approach.
| Line type | How it behaves | Treatments that target it |
|---|---|---|
| Dynamic | Appears when you smile, laugh, or squint and fades at rest | Botulinum toxin injections that temporarily relax the orbicularis oculi |
| Static | Visible even when the face is still, often a deeper crease | Hyaluronic acid dermal fillers, which are best suited to static, deeper creases |
| Surface texture | Fine crinkling, uneven texture, and dullness around the eye | Chemical peels, microdermabrasion, laser skin rejuvenation, topical retinoid and glycolic acid preparations |
Most people have a mix of all three, which is why a single product rarely delivers the whole result. A treatment plan is built around what your lines actually do.
Botulinum Toxin: Relaxing the Muscle That Folds the Skin
Botulinum toxin injections are often the most effective option for crow’s feet because they temporarily relax the orbicularis oculi, the muscle responsible for the folding. BOTOX Cosmetic is commonly used to soften the lines that appear when you smile, laugh, or squint. By quieting part of that muscle, the skin over it is no longer creased with every expression, and the lines soften.
The word temporary matters. Muscle relaxation wears off, so the creasing pattern returns unless treatment is repeated. Many patients treat it as maintenance rather than a one-time fix, and the schedule is set with the treating physician based on how your muscle responds.

Dermal Fillers for the Creases That Stay at Rest
When a line is etched in even with a still face, relaxing the muscle alone may not be enough. Hyaluronic acid dermal fillers are best for static, deeper creases, because they address the groove rather than the pull that created it. The eye area is delicate, so placement and product choice deserve extra care, and this is a region where an experienced injector matters more than usual.
Resurfacing Options That Improve the Skin Itself
Beyond muscle and volume, the quality of the skin around the eye shapes how visible crow’s feet appear. A range of options can be used for this, and they are often combined with injectables rather than used instead of them.
- Chemical peels to refresh surface texture
- Microdermabrasion for mild superficial improvement
- Laser skin rejuvenation to address skin quality around the eye
- Topical retinoid and glycolic acid preparations, which help improve skin texture over time
- The OBAGI Skin Care line, a topical skincare option used in some treatment plans
- Eyelid surgery, which addresses the eyelid area itself rather than the crow’s feet lines alone
Each of these works on a different layer or a different problem. Peels and microdermabrasion focus on the surface. Retinoids and glycolic acid support texture gradually at home. Lasers reach deeper into skin quality. A consultation is the point where those differences get sorted into a plan that suits your skin type and your tolerance for downtime.

How to Get Softer Lines Without a Frozen Look
The frozen look is not an unavoidable side effect of crow’s feet treatment. It is usually the result of treating too much, too widely, or treating the wrong thing. The outer eye is surrounded by muscle that also creates your smile, and a conservative approach leaves enough movement for expression to read naturally.
- Start conservatively and assess, rather than treating the maximum area at the first visit.
- Treat dynamic lines with muscle relaxation and reserve fillers for static creases that remain.
- Keep the treatment focused on the crow’s feet rather than spreading it across the mid-face.
- Review the result together and adjust at a follow-up rather than adding more immediately.
An honest assessment also helps. Some of what reads as crow’s feet is actually a combination of lines, skin texture, and volume change, and a plan that only addresses one of those will look incomplete no matter how carefully it is injected. A board-certified dermatologist can identify which component is dominant in your face before any product is chosen.
Short-Term Smoothing and Long-Term Skin Improvement
It helps to separate two timelines. Short-term smoothing is achieved through muscle relaxation and immediate hydration, which is why some change is visible early. Long-term skin improvement develops gradually as the skin responds over time to retinoids, acids, peels, or laser treatments.
Patients who expect both results from a single appointment often feel disappointed, while patients who understand the two timelines tend to be far happier with the outcome. Muscle relaxation handles the folding. Skincare and resurfacing handle the canvas.
What Home Remedies Can and Cannot Do
Home remedy articles circulate widely, and one common suggestion is to rub fresh lemon juice onto the crow’s feet, leave it for about ten minutes, and rinse with cold water, repeating a couple of times. Citrus juice on the thin skin around the eye can sting and irritate, so it is worth asking a dermatologist before trying it.
More importantly, no topical home remedy relaxes the orbicularis oculi muscle or fills a static crease. Moisturizing and sun protection are reasonable habits, but they act on the skin surface, not on the muscle contraction that folds it.

Choosing a Provider in South Denver
Colorado Dermatology Center is the practice of board-certified dermatologist Dr. James M. Swinehart, whose clinical experience spans more than three decades. The South Denver practice covers medical, surgical, and cosmetic dermatology, which means the person assessing your crow’s feet is also trained to recognize what else may be happening around the eye. The practice emphasizes personalized care, proven techniques, and natural-looking results, all of which line up with the goal of softer lines rather than a still, expressionless face.
Bring your questions to the consultation. Useful ones include: which of my lines are dynamic and which are static, what would a conservative first step look like, what are the risks for my skin type, how much downtime should I plan for, and how will we decide whether to add a second treatment.
Frequently Asked Questions
What is the most effective treatment for crow’s feet?
For lines that appear when you smile, laugh, or squint, botulinum toxin injections are often the most effective option because they temporarily relax the orbicularis oculi muscle that creates the fold. For creases that remain visible at rest, hyaluronic acid dermal fillers are generally better suited because they address the deeper groove rather than the muscle pull.
Can crow’s feet be treated without injections?
Yes, though the results work differently. Topical retinoid and glycolic acid preparations help improve skin texture over time, and chemical peels, microdermabrasion, and laser skin rejuvenation can address surface quality around the eye. These approaches support the skin itself but do not relax the muscle contraction, so lines that appear only with expression may remain.
Will treatment make my whole face look frozen?
It should not. A frozen look typically comes from treating too much or too widely. When treatment stays focused on the crow’s feet and starts conservatively, enough muscle movement usually remains for a natural smile. Reviewing the result at a follow-up and adjusting gradually is a more reliable route than treating aggressively at the first visit.
How soon will I notice a difference?
Short-term smoothing comes from muscle relaxation and immediate hydration, so some change appears early. Longer-term skin improvement develops gradually as the skin responds to retinoids, acids, resurfacing, or laser treatment. Because the two timelines differ, it helps to discuss expected sequencing with your dermatologist rather than judging the full result from the first week.
Do fillers work on crow’s feet?
Hyaluronic acid fillers are best suited to static, deeper creases, meaning lines that stay visible when your face is at rest. They address the groove itself. If your lines mostly appear when you smile, muscle relaxation is usually the more appropriate first step, and the two approaches are often combined after an assessment.
Crow’s feet respond best to a plan built around what your lines actually do: relax the muscle that folds the skin, support the skin’s texture over time, and add volume only where a crease genuinely stays at rest. Handled conservatively, that combination softens the outer eye while leaving your expressions intact.
Subcision for Acne Scars in Denver: What to Know
Acne can clear and still leave a map of depressions, rolling contours, and uneven texture behind. Those marks are not just a surface issue. Some depressed acne scars are tethered underneath the skin by fibrous bands, which pull the scar downward and keep it from sitting level with the surrounding skin. Subcision is a minimally invasive, in-office procedure designed to release those bands so the scar can elevate.
Not every Denver-area clinic offers subcision, even when it provides other acne treatments. That can make the search frustrating if you have already tried creams, washes, or superficial treatments and still see depressed scars. At Colorado Dermatology Center in Denver, acne scar revision is part of the practice’s focus. The office is led by board-certified dermatologist Dr. James M. Swinehart, whose clinical experience spans more than three decades. This guide explains what subcision does, which scars it may help, what recovery and risks look like, and what to ask before scheduling.
What subcision is
Subcision is a simple, in-office procedure designed to treat depressed acne scars. A dermatologist uses a small needle or blunt cannula to break up fibrous bands of tissue that tether the scar. The goal is not to remove skin or resurface the top layer. The goal is to release the downward pull so the depressed area can lift and the skin surface can look smoother.
Another way to describe subcision is that it treats valley scars, or scars that are depressed. It is specifically used for depressed scars such as those caused by acne. The procedure is considered minimally invasive, and it targets the structural tethering that gives some scars their sunken appearance. That makes it different from a general acne treatment aimed only at active breakouts.
How subcision releases depressed scars
Depressed acne scars can be bound down by fibrous bands. Those bands act like small anchors under the skin. When a dermatologist performs subcision, the needle or blunt cannula is used to break those fibrous bands. Once the tethering is released, the scar is no longer held down in the same way, and the treated area may elevate.
The procedure is minimally invasive, but it still requires an understanding of scar depth, surrounding tissue, and the pattern of tethering. One clinical discussion focuses on subcision for acne scars of the cheeks and temples, areas where rolling and depressed scars commonly appear. A dermatologist’s evaluation matters because not every indentation has the same cause or the same tethering pattern.
Which acne scars may respond to subcision
Subcision is designed for depressed scars, including atrophic acne scars such as rolling scars and valley scars. These are the scars that sit below the surrounding skin surface and may look shadowed depending on lighting. A scar that is primarily a color change, or a scar that is raised rather than depressed, is not the main target of subcision.
- Rolling scars, which can create a wavy or undulating surface
- Valley scars, which are depressed below the surrounding skin
- Atrophic acne scars, which result from lost or tethered tissue
- Depressed scars on areas such as the cheeks and temples
Effectiveness depends on several factors, including the nature of the injury or scar, the body’s healing mechanism, the size and depth of the wound, and the thickness and color of the skin. That is why a consultation should include a close look at the scars rather than a general promise that subcision will work on every mark.
Why subcision is not offered at every clinic
Availability varies by practice. Some clinics concentrate on general dermatology, while others may offer a narrower set of cosmetic services. Subcision is a procedural scar treatment, so not every office may build it into its service list. If you are searching in Denver and a clinic does not offer subcision, ask whether the provider can refer you to a dermatologist who performs scar revision.
Colorado Dermatology Center describes itself as offering procedures that many practices do not, and acne scar revision is one of its stated focus areas. For patients with depressed acne scars, that matters because the first step is often finding a provider who can distinguish scar types and discuss procedural options, not just skin care products.
What a consultation should cover
A consultation for acne scar subcision should be specific to your skin and your scars. The dermatologist should examine the scar pattern, ask about your acne history, and discuss whether the scars are depressed and tethered. The conversation should also cover realistic expectations, because subcision is intended to improve the appearance of depressed scars rather than guarantee flawless skin.
- Which scars are depressed, rolling, or valley-type scars
- Whether fibrous tethering appears to be contributing to the depression
- How scar depth, skin thickness, and skin color may affect planning
- What complications have been reported with subcision
- What aftercare instructions will be provided
- What improvement is realistic for your scar pattern
Bring your questions to the appointment. A good consultation should leave you understanding what subcision can address, what it cannot address, and whether another approach or a combination of approaches may be more appropriate for your scars.
Recovery and aftercare after subcision
After subcision, patients may have bruising, tenderness, or other temporary changes. A 2025 review of complications reported pain or tenderness, bruising, infection, formation of subcutaneous lumps, and dyspigmentation as possible issues. Because aftercare can vary by provider and by the details of the procedure, ask for written instructions before you leave the office.
Those instructions should tell you what to do about cleansing, sun protection, makeup, exercise, and skin care products, along with warning signs that need attention. If you are unsure about anything during recovery, contact the office rather than guessing. The quality of aftercare and follow-up is part of the treatment experience, especially when the procedure is performed for scar revision.
Risks and complications to discuss
Subcision is minimally invasive, but it is still a procedure. The main complications reported in a 2025 review were pain or tenderness, bruising, infection, formation of subcutaneous lumps, and dyspigmentation. Your dermatologist should discuss these risks with you and explain what can be done if a complication occurs.
Ask about infection precautions, how lumps under the skin are managed, and what pigment changes may mean for your skin type. If you have a history of poor scarring, pigment problems, or unusual reactions after skin procedures, share that information during the consultation. The goal is an informed decision, not pressure to schedule on the first visit.
Questions to ask before scheduling subcision in Denver
If you find a Denver clinic that offers subcision, use the consultation to confirm that the procedure is a good fit for your scars. The questions below can help you compare providers and avoid assumptions about what the procedure will do.
- Are my acne scars depressed and tethered, or are they primarily color changes?
- Is subcision appropriate for the location and depth of my scars?
- Who will perform the procedure, and how often does that provider perform it?
- What side effects and complications should I expect?
- What aftercare instructions will I receive, and who do I contact with concerns?
- What improvement is realistic, and will I need additional treatments for other scar types?
Why a dermatologist’s assessment matters
Acne scar treatment starts with diagnosis. A depressed scar, a rolling scar, a raised scar, and a flat mark with discoloration may all look like “acne scars” to a patient, but they do not respond to the same approach. Subcision specifically targets depressed scars by breaking fibrous bands, so identifying the right scar type is essential.
Colorado Dermatology Center combines medical, surgical, and cosmetic dermatology with a focus on acne scar revision and other procedures that may not be available at every practice. Dr. James M. Swinehart’s board certification and more than three decades of clinical experience support an approach built around careful evaluation, procedural skill, and natural-looking improvement. For Denver patients who have been told that nothing more can be done for depressed acne scars, a consultation can clarify whether subcision or another scar revision option deserves consideration.
Frequently Asked Questions
What is subcision for acne scars?
Subcision is a minimally invasive, in-office procedure for depressed acne scars. A dermatologist uses a small needle or blunt cannula to break fibrous bands that tether the scar downward. Releasing those bands can allow the depressed area to elevate and the skin surface to look smoother. It is designed for valley scars and depressed scars rather than all acne marks.
Does subcision work on all acne scars?
No. Subcision is designed for depressed scars, including rolling scars and atrophic acne scars. Scars that are primarily color changes or raised scars are not the main target. Effectiveness also depends on the nature of the scar, its size and depth, your body’s healing response, and the thickness and color of your skin. A dermatologist can assess whether your scars fit the procedure.
What are the side effects of subcision?
A 2025 review reported pain or tenderness, bruising, infection, formation of subcutaneous lumps, and dyspigmentation as complications of subcision for acne scarring. Some side effects are temporary, but infection and pigment changes deserve prompt discussion with your provider. Ask for aftercare instructions and warning signs before the procedure so you know what to monitor during recovery.
How do I find a Denver clinic that offers subcision?
Ask directly whether the practice offers subcision for depressed acne scars and who performs it. Availability varies, so a clinic that treats acne may not provide this specific procedure. Look for a dermatology practice with acne scar revision experience, and request a consultation to confirm that the provider evaluates scar type, discusses risks, and explains realistic outcomes.
Can subcision get rid of acne scars completely?
Subcision is not described as a way to erase every acne scar. It targets depressed scars by breaking fibrous bands so the scar can elevate. Improvement depends on scar depth, tethering, skin characteristics, and healing. A dermatologist should explain what change is realistic for your scars and whether other treatments may be needed for texture or color.
Free Skin Cancer Screenings in Colorado: Where to Look
Free skin cancer checks are available across Colorado, but they do not come from a single statewide office. They show up through national screening directories, community health events, awareness campaigns, and free or low-cost clinics. Each channel works a little differently, and each has its own rules about who qualifies and how many people can be seen. Knowing where to look, and what to confirm before you go, saves you a string of phone calls and a wasted trip.
This guide walks through the realistic options in Colorado, explains what a free screening typically includes and leaves out, and covers what to do if the screening turns up something that needs a closer look.
Start With the National Screening Directories
The fastest starting point is a national directory that collects free screening events in one searchable place. The SPOT me free skin cancer screening program is one example, and its listings have included free skin cancer checks available across Colorado, with Denver-area locations appearing in the past. Directories like this are built for exactly the question you are asking, and they let you search by state or by city rather than guessing which clinic might be hosting an event.
The catch is that these listings change constantly. Events are added weeks before they happen and removed once slots fill. A listing you saw last spring may no longer be active, and a new event may have appeared since. Treat any directory entry as a lead rather than a confirmed appointment, and verify the date, location, and eligibility rules with the organization hosting the screening before you plan your day around it.
Community Health Events and Awareness Campaigns
Free skin cancer screenings are often available through community health events, nonprofit organizations, and special awareness campaigns. In Colorado and elsewhere, many of these events cluster around Skin Cancer Awareness Month, when dermatology practices, hospitals, and community groups host one-day screening clinics. Some practices open free screenings to new patients during that window, which makes it a good time to check with offices you have not visited before.
Community events come with practical limits worth knowing in advance. Some run for only a few midday hours, and appointments are often capped, so walk-ins may be turned away once the schedule fills. Others are held at health services sites rather than in a dermatology office. Eligibility rules vary too. A common pattern is to offer free screenings to adults 18 and older who have not had a professional skin exam within a set period, though the exact rule is set by each host. Ask about age limits and recent-exam restrictions when you call.
Free and Low-Cost Clinics
If you do not have health insurance, free and low-cost clinics are a practical route, and these clinics exist throughout the United States. Many are general primary care sites rather than dermatology practices, so the visit may not be a dedicated skin cancer screening event. That does not make them useless. It means you should ask two specific questions when you call: whether the visit can include a skin exam, and what happens if the clinician finds something that needs a biopsy or a specialist.
That second question matters more than most people expect. A free screening is a look, not a diagnosis, and any follow-up testing or treatment is a separate step with its own arrangements and costs. Ask about it before you are sitting in the exam room.
How the Main Options Compare
| Screening channel | Good fit for | Confirm before you go |
|---|---|---|
| National screening directory | Finding events across Colorado without calling around | That the listing is current, plus date, location, and eligibility |
| Community health event or awareness campaign | A no-cost visual check during a set window | Appointment limits, hours, age rules, and who performs the exam |
| Free or low-cost clinic | People without insurance who need a starting point | Whether a skin exam is included and how follow-up is handled |
| Dermatology practice visit | A spot that is new, changing, or not healing | Scheduling, what the visit covers, and coverage if you have insurance |
What a Free Screening Usually Covers
A free skin cancer screening is a brief visual exam. A clinician looks at your skin, often focusing on sun-exposed areas and any spots you point out, and flags anything that looks suspicious. The visit is short by design, because the goal is to move as many people through as possible and catch obvious concerns early.
Because of that pace, a free screening is not the same as a full dermatology appointment. It may not include a head-to-toe exam of every square inch, and it rarely includes magnification tools, photography, or documentation beyond a note. If you have a specific spot you are worried about, say so at the start so it gets looked at rather than skipped.
What a Free Screening Does Not Cover
Free means the screening itself, not everything that follows. A screening event typically does not include a biopsy, lab work, treatment, or a written clearance that your skin is healthy. If the clinician sees something that needs testing, you will be referred for follow-up care, and that referral is a separate appointment with its own scheduling and cost questions.
It also does not replace regular skin checks if you are at higher risk. A single normal screening is a snapshot of one day, not a guarantee about the future. People with a personal or family history of skin cancer, a lot of sun exposure, or many moles generally need ongoing follow-up with a dermatologist rather than a once-a-year community event.
How to Prepare for a Screening
A little preparation makes a short appointment more useful. Try to arrive with these items settled:
- Make a short list of spots that are new, have changed in size or color, itch, bleed, or have not healed.
- Note any personal or family history of skin cancer, since it affects how closely you should be followed.
- Bring a list of medications you take, particularly anything that affects your immune system or makes your skin sensitive to light.
- Wear clothing that is easy to remove or move aside so the clinician can see your arms, legs, and back.
- Skip heavy makeup, and remove nail polish if you want your nails checked.
- Arrive early for any paperwork the host requires, since event slots are often tightly scheduled.
Questions Worth Asking Before You Book
A two-minute phone call can separate a useful screening from a frustrating one. Ask whether the event is open to your age group and whether it excludes people who have had a professional skin exam recently. Ask who performs the exam, since some events use dermatologists and others use other clinicians. Ask whether the exam covers the whole body or only exposed areas. Ask what the host recommends if something suspicious is found, and whether they can help you get a follow-up appointment. If no one can answer these questions, look for a different event or call a dermatology office directly.
When a Free Screening Is Not Enough
Some situations should not wait for the next screening event. A spot that is new, changing, bleeding, or failing to heal deserves an appointment with a dermatologist rather than a place in a queue. The same goes for a history of skin cancer, a large number of atypical moles, or a family member who has had melanoma.
In South Denver, Colorado Dermatology Center is led by board-certified dermatologist Dr. James M. Swinehart, whose clinical experience spans more than three decades. The practice covers medical, surgical, and cosmetic dermatology, with particular depth in skin cancer treatment including MOHS micrographic surgery, and it also runs clinical research. If you cannot find a free screening that fits your schedule, or if you want a full exam rather than a brief check, that kind of practice is the next step. Call ahead to ask what a visit involves and what your insurance covers, since coverage rules vary by plan and are not something a screening event can answer for you.
Frequently Asked Questions
Are free skin cancer screenings really free?
The screening event itself is offered at no charge, which is the point of the program. What is not included is anything beyond the visual exam, such as a biopsy, lab work, treatment, or a follow-up visit. Ask the host what happens after the screening and how follow-up is arranged, so you are not surprised by a bill later.
Who qualifies for a free screening?
Eligibility is set by each host, and rules differ from event to event. A common pattern is to offer free screenings to adults 18 and older who have not had a professional skin exam within a set period of time. Some events also limit the number of appointments available. Confirm the rules with the organization before you go.
Do I need insurance to attend a screening?
No. Free screening events are designed to be accessible without insurance, and free or low-cost clinics exist throughout the country as a starting point for people without coverage. Keep in mind that insurance questions come up later, at the follow-up appointment, not at the screening itself. Ask about follow-up options while you are there.
What should I do if I cannot find a free screening near me?
Check a national screening directory first, since listings change often and new Colorado events appear throughout the year. If nothing fits, call free and low-cost clinics in your area and ask whether a skin exam can be included in a visit. Scheduling a skin exam with a dermatology practice is the most reliable option when you have a specific concern.
Free screenings are a genuine starting point, not a replacement for care you already know you need. Use the directories and community events to get a baseline look at your skin, ask the questions above before you go, and move to a dermatologist without delay if a spot is changing or a screening turns up something that needs testing.

Does Medicare Cover Skin Cancer Screening? Colorado Coverage Facts
The answer depends on why the exam is happening. Medicare generally pays for skin cancer related care when it is medically necessary, meaning there is a symptom, a suspicious spot, a changing mole, or another reason your doctor needs to evaluate you. What Medicare does not typically do is pay for a routine, preventive full body skin check for someone with no symptoms and no concerning lesions. That distinction drives almost every coverage question patients ask at a dermatology office.
For people in Colorado, the practical takeaway is simple. If you have a spot that worries you, a sore that will not heal, or a mole that has changed, that visit is usually treated as medical care rather than screening. If you are simply due for a yearly skin check with nothing specific to point to, expect to ask about cost before the appointment.
The Short Answer on Medicare and Skin Cancer Screening
Original Medicare, which includes Part A and Part B, typically covers medically necessary dermatological treatment. Coverage for skin cancer screening sits inside that larger idea. Medicare covers medically necessary services for skin cancer detection and treatment, including doctor visits when there is a suspected case, biopsies, and related care.
At the same time, Original Medicare does not cover routine, preventive skin cancer screenings for asymptomatic individuals. The United States Preventive Services Task Force, whose recommendations shape which preventive services Medicare covers, does not list skin cancer screening as a covered preventive service. That is why a symptom free skin check and a check for a suspicious lesion can end up in two different coverage categories.
Note that published guidance is not perfectly consistent on this point. Some coverage summaries describe regular skin cancer screenings, including visual exams and biopsies, as typically covered by Medicare. The safest approach is to treat coverage as conditional on medical necessity and to confirm your own situation with Medicare or your plan before the visit.
Routine Screening vs. a Medically Necessary Skin Exam
The table below shows how the same appointment can be handled two different ways depending on what is documented in your chart.
| Service | Typical Medicare treatment | What to know |
|---|---|---|
| Full body skin check with no symptoms and no suspicious spots | Generally not covered as preventive screening under Original Medicare | Skin cancer screening is not listed as a covered preventive service by the USPSTF |
| Skin exam because of a suspicious lesion, changing mole, or symptom | Typically covered as a medically necessary service | Part B covers skin exams and doctor visits when cancer is suspected |
| Skin biopsy to check a lesion for cancer | May be covered by Part B | Medicare Part B may cover a skin biopsy to check for skin cancer |
| Cancer treatment after a diagnosis | Medicare may cover the treatment | If cancer is found, Medicare may cover cancer treatment such as chemotherapy |
What Part B Covers When There Is a Concern
Part B is the part of Original Medicare that handles outpatient care, including dermatology visits and procedures. When a patient points to a specific lesion, reports a symptom, or has a history that raises the risk of skin cancer, the visit becomes a medical evaluation rather than a screening. In that situation, Part B coverage is far more likely.
Services that commonly fall into this medically necessary category include:
- An office visit where you show your dermatologist a specific spot or describe a symptom
- A skin exam performed because cancer is suspected
- A skin biopsy to check tissue for cancer
- Follow up visits related to a diagnosed skin cancer
- Cancer treatment when a diagnosis has been confirmed
Documentation matters. The reason for the visit goes on the claim, and that reason is what supports coverage. When you schedule, describe the concern plainly. “I have a spot on my shoulder that has been bleeding” tells the office something very different from “I would like a general skin check.”
What Part A Covers
Part A covers inpatient hospital care. Most skin cancer screening and dermatology office visits do not involve a hospital stay, so Part A rarely enters the conversation for a skin check or a biopsy. Part A becomes relevant if treatment requires inpatient care. For everyday dermatology, Part B is the part that matters.
Medicare Advantage and Other Plan Types
Medicare Advantage plans are required to provide at least the same coverage as Original Medicare, but many plans add extra benefits. A Medicare Advantage plan may cover routine skin checks that Original Medicare would not. Whether yours does is a plan specific detail that you need to confirm directly, ideally before you book.
Some coverage summaries also note that most private insurance companies, along with Medicare and Medicaid, cover the cost of certain routine cancer screenings. Medicare provides coverage for many cancer screenings and treatments, and the details vary by service. If you have secondary insurance or a supplemental plan, ask how it coordinates with Medicare for a dermatology visit.

Why the Screening Question Is Treated Differently
Preventive coverage under Medicare is tied to recommendations from the USPSTF. Services on that list, such as certain colon or breast cancer screenings, are covered as preventive care. Skin cancer screening is not on that list, so a symptom free skin exam does not automatically qualify as a covered preventive service.
That does not mean skin exams have no value. It means the payment rules separate a screening visit from a diagnostic one. A dermatologist examining a specific lesion is diagnosing. A dermatologist examining the whole body with no particular target is screening. Same skin, different billing category.
Colorado Patients: What to Bring and What to Say
If you live along the Front Range and spend time outdoors at elevation or on the slopes, you already know sun exposure adds up. Colorado Dermatology Center in South Denver, led by board-certified dermatologist Dr. James M. Swinehart, sees patients with a wide range of skin concerns, from a single suspicious spot to a personal history of skin cancer. Being specific about your concern helps the practice bill the visit correctly.
Before your appointment, gather these items:
- Your Medicare card and any supplemental or Advantage plan card
- A list of the specific spots or symptoms you want evaluated, with how long they have been present
- Any history of previous skin cancers, biopsies, or treatments
- Notes on family history of skin cancer, if it applies to your situation
- A question list, starting with what your plan will cover for this visit

How to Verify Your Own Coverage
Coverage questions are best answered by the payer, not by a general article. A few steps will give you a clear answer before you arrive.
- Call Medicare or log into your Medicare account and ask specifically about a diagnostic skin exam versus a screening skin exam
- If you are in a Medicare Advantage plan, call the member services number on your card and ask about dermatology and skin cancer screening benefits
- Ask the dermatology office how they will code the visit based on the concern you describe
- Ask whether your supplemental plan covers any remaining patient responsibility
- Request the cost estimate in writing if you are booking a visit that may not be covered
A short phone call before scheduling removes most of the uncertainty. It also helps you decide whether to book a focused concern visit, which is more likely to be covered, rather than a general screening visit.
Frequently Asked Questions
Does Medicare pay for a yearly skin check?
Not usually as preventive screening. Original Medicare does not cover routine skin cancer screenings for people without symptoms, and the USPSTF does not list skin cancer screening as a covered preventive service. If you have a specific spot or symptom, the visit is generally treated as medically necessary and coverage is more likely. Medicare Advantage plans may add benefits, so check your plan.
Is a skin biopsy covered by Medicare?
Medicare Part B may cover a skin biopsy to check for skin cancer when it is medically necessary. If cancer is found, Medicare may also cover cancer treatment such as chemotherapy. Your dermatologist’s office can explain how the biopsy will be coded. Confirm the details with Medicare or your plan before the procedure if cost is a concern.
What if my dermatologist finds something during a routine visit?
This happens often. If your doctor identifies a suspicious lesion and evaluates or biopsies it, that portion of the visit is typically handled as medically necessary care rather than screening. Ask the office to document the finding clearly and to explain how the claim will be submitted. You can also call your plan afterward to confirm what was processed.
Do Medicare Advantage plans cover skin exams differently?
They can. Medicare Advantage plans must provide at least what Original Medicare covers, and many add extra benefits that may include routine skin checks. The specifics vary widely by plan and by year. Read your plan’s evidence of coverage or call member services and ask directly about dermatology and skin cancer screening benefits before booking.
How do I check coverage before booking a Colorado appointment?
Call Medicare or your Medicare Advantage plan and describe the visit you are planning. Ask whether a diagnostic skin exam and a screening skin exam are handled differently. Then ask the dermatology office how they will code your visit based on the concern you describe. Comparing both answers before the appointment gives you the clearest picture of your expected cost.

Screening for Skin Cancer: What the Exam Covers and Who Should Book One
Screening for skin cancer is one of the few cancer checks that happens mostly with the eyes. No needles, no blood draw, no imaging machine. A clinician looks carefully at your skin, notes anything that seems off, and decides what, if anything, should happen next.
That simplicity can make the exam sound less important than it is. A regular skin exam by a health professional can help find skin cancer early, and a 2023 evidence report published in JAMA noted that a substantial body of nonrandomized evidence suggests a clear association between earlier stage at detection and lower mortality. Early detection is the whole point of the visit. What follows is a plain description of what the exam involves, how it differs from the checks you do at home, and how to think about booking one.
What a Skin Cancer Screening Actually Is
A skin cancer screening is a visual inspection of the skin for suspicious lesions. That is the core of it. One widely shared description of these exams states plainly that screening does not involve blood tests, which surprises some people who assume a cancer check must include lab work.
During a skin exam, a doctor or nurse checks the skin for moles, birthmarks, or other pigmented areas that look abnormal in color, size, shape, or other features. The clinician is not looking for one specific spot. The goal is a survey of the skin as a whole, because a lesion that looks unremarkable in isolation can still stand out when compared with the skin around it or with other marks on the body.
The visual inspection
The exam relies on trained eyes and comparison. A clinician notes the color of a spot, its size, its shape, and any other features that set it apart from nearby skin. Moles and birthmarks that have changed, or that simply look different from the rest, tend to draw attention. Because the entire assessment is visual, the quality of the exam depends on the clinician being able to see your skin clearly and on your being able to point out anything that has been on your mind.
What the exam does not include
The screening visit itself is not a blood test and does not produce a lab result. The sources reviewed for this article do not describe routine use of dermoscopy, biopsy, or other follow-up procedures during screening, so it is reasonable to ask your clinician what tools they use and what happens if something looks suspicious. If a spot needs closer evaluation, that is a separate conversation from the initial look.
Screening Exam vs Monthly Self-Exam
Professional screening and self-examination are complementary rather than competing. A professional exam is described as a way to help find skin cancer early. Self-exams are described as a simple, powerful way to detect skin cancer early, and the Skin Cancer Foundation advises examining your skin head to toe every month.
During a self-check, look for new moles, growths, blemishes, freckles, and similar changes. The value of the habit is familiarity. Once you know how your skin normally looks, a new or shifting spot is easier to notice, and you have something concrete to describe when you do see a clinician. The sources reviewed do not compare which method is more effective, so treat them as two parts of one routine rather than a choice between options.
| Feature | Professional skin exam | Monthly self-exam |
|---|---|---|
| Who performs it | A doctor or nurse | You |
| What it involves | Visual check for moles, birthmarks, or pigmented areas that look abnormal in color, size, shape, or other features | Head-to-toe check for new moles, growths, blemishes, freckles, and changes |
| Blood tests | Not part of screening | Not applicable |
| Stated purpose | Can help find skin cancer early | Can help detect skin cancer early |

Who Should Consider Booking One
This is the part where readers most often want a cutoff: a starting age, a number of years between visits, a list of conditions that automatically qualify. The sources reviewed for this article do not include guideline details on the recommended age to start screening, screening frequency, or eligibility criteria for average-risk and higher-risk groups. Anyone presenting a single universal rule is going beyond what that evidence base supports.
What the sources do support is more practical. If you have noticed a new mole, growth, blemish, or freckle, or a change in one you already had, that is a reasonable reason to raise it with a clinician. If you would simply like a professional to look over your skin, a regular skin exam can help find skin cancer early, and asking about it is a normal request. People with a personal or family history of skin cancer, or other concerns about their own risk, should ask their own clinician how screening applies to them rather than relying on a general article.
Self-exams help here too. A monthly head-to-toe check gives you a record of what is normal for your skin, so that a conversation with a clinician starts with specifics instead of a vague sense that something changed.
What the Research Does and Does Not Show
The 2023 JAMA evidence report by Henrikson and colleagues concluded that a substantial nonrandomized evidence base suggests a clear association between earlier stage at skin cancer detection and decreased mortality. In plain terms, skin cancers found at an earlier stage are linked to better outcomes, and that link is consistent across a large body of observational evidence.
That is not the same as proof that screening programs themselves reduce deaths. The association described is not randomized, and the sources reviewed do not establish that routine screening lowers mortality in average-risk adults. Both ideas can be true at once: catching skin cancer earlier matters, and the case for universal screening of everyone is less settled than the case for early detection. If you want the current position that applies to your situation, ask your clinician directly.
Free and Low-Cost Screening Options
Cost is a real barrier, and one program is explicitly described as free. Destination Healthy Skin is a mobile skin cancer screening and education program that travels around the country, offering free screenings along its route. The sources reviewed do not list specific locations, dates, or a schedule for the program, so check the program’s own current information before planning around it.
Health systems also run their own screening events. UChicago Medicine, for example, lists a phone number for scheduling skin cancer screening appointments, with 1-888-824-0200 associated with that institution. That number is specific to UChicago Medicine and is not a national screening line, so use it only if that health system is relevant to you. For anything local, start with the scheduling line of the dermatology practice or health system you would actually visit.
Insurance coverage and out-of-pocket cost for skin cancer screening are not addressed in the sources reviewed here. Only Destination Healthy Skin is described as free. Confirm coverage with your insurer and the practice before you book, since the answer depends on your plan and on how the visit is coded.
Getting the Most From the Appointment
A visual exam only works as well as the information that goes into it. Arrive with a short list of the spots that concern you, including how long you have noticed them and what has changed. If you have had skin cancer before, or a family member has, say so. If you do self-exams, mention what you have been tracking.
Ask what the clinician is seeing as they go, and ask what to watch for afterward. If something needs a closer look, find out what the next step is and when you will hear about it. A screening exam is a snapshot, and knowing what to do between visits is as useful as the visit itself.
Screening Within a Dermatology Practice
Colorado Dermatology Center is a South Denver practice led by board-certified dermatologist Dr. James M. Swinehart, with more than three decades of clinical experience across medical, surgical, and cosmetic dermatology. Skin cancer care is a central part of the practice, including MOHS micrographic surgery for skin cancer. For patients who want a professional skin exam and a clear path forward if something needs treatment, that combination of screening and surgical expertise in one setting is the practical advantage. Call the practice to ask how a screening visit is scheduled and what to expect.
Frequently Asked Questions
Does a skin cancer screening involve blood work?
No. A skin cancer screening is a visual inspection of the skin for suspicious lesions, and one widely shared description of these exams explicitly states that screening does not involve blood tests. The clinician looks over your skin, checking moles, birthmarks, and other pigmented areas for anything abnormal in color, size, shape, or other features. Any lab work would relate to a separate concern, not to the screening itself.
How often should I check my own skin?
The Skin Cancer Foundation advises examining your skin head to toe every month, describing self-exams as a simple, powerful way to detect skin cancer early. During a check, look for new moles, growths, blemishes, freckles, and similar changes. Monthly is a habit-building rhythm rather than a strict medical rule, so ask your clinician if a different schedule suits your situation better.
Are skin cancer screenings free?
Not universally. Destination Healthy Skin is described as a free mobile skin cancer screening and education program that travels around the country. Beyond that, the sources reviewed here do not detail insurance coverage or out-of-pocket costs for screening. Check with your insurer and the practice you plan to visit before booking so there are no surprises about what the visit will cost.
Can a screening tell me for sure whether a spot is cancer?
A screening identifies lesions that look suspicious and warrant a closer look. The sources reviewed do not specify whether screening visits routinely use dermoscopy, biopsy, or other follow-up procedures, so the answer depends on the clinician and on what they see. Ask directly what the next step would be if a spot needs further evaluation, and when you would get results.
Who should book a screening appointment?
The sources reviewed do not define a starting age, a screening interval, or eligibility criteria for average-risk and higher-risk groups, so there is no universal rule to quote here. If you have noticed a new or changing mole, growth, blemish, or freckle, or if you want a professional to examine your skin, raise it with your own clinician and decide together.

Botox for Forehead Lines and Crow’s Feet in Denver
Forehead lines and crow’s feet tend to show up in photographs before they show up in the mirror. They are the creases that deepen when you raise your brows or squint into bright Colorado sun, and they often linger as faint grooves even after the expression fades. Botox is one of the most discussed options for softening those lines, and it is also one of the most misunderstood. This guide walks through what Botox actually does to the muscles that create forehead lines and crow’s feet, what the early results tend to look like, how it differs from filler, and the questions worth asking before you book a treatment in Denver.
What Botox Does to Forehead Lines and Crow’s Feet
BOTOX Cosmetic is a prescription medicine that is injected into muscles and used to temporarily improve the look of moderate to severe forehead lines. That sentence matters because it describes both the mechanism and the limit. Botox does not resurface the skin, fade pigment, or plump a hollow. It works on the muscle beneath the skin, and the change is temporary.
The muscle action is the key. Botox paralyzes your muscles, which is why the creases created by repeated movement begin to relax. When the muscles that pull the brow up or draw the corners of the eyes tight stop contracting as forcefully, the skin above them is no longer folded into the same pattern dozens of times a day.
There is a preventive side to this as well. Botox injections can prevent wrinkles from forming, which is why some patients start treatment when lines are still faint rather than waiting for them to settle into place. Botulinum toxin is commonly used to treat lines in the upper one-third of the face, including horizontal forehead lines, and that upper-face focus is exactly where crow’s feet sit as well.
Why the Upper Face Is Such a Common Treatment Area
The upper face moves constantly. Raising your eyebrows in conversation, squinting at a screen, narrowing your eyes against glare on I-25 at sunset: each of those expressions recruits the same small group of muscles, and each one folds the skin in the same places. Over time the fold becomes a line that stays visible at rest.
Botox and similar neuromodulators such as Dysport are used to inject the muscles that cause you to create these lines. Crow’s feet and forehead furrows are two of the most familiar targets because the muscles involved are accessible and the patterns are predictable. A provider maps those muscles, decides where to place the injections, and adjusts dosing based on how strongly your face moves.
Patients often assume the goal is a completely still forehead. A skilled injector is usually aiming for something quieter than that: movement that still looks like you, with the lines softened rather than erased. If your brows are expressive and you want to keep that, say so at the consultation. The plan can be built around it.
What to Expect After Treatment
Botox brings immediate benefits in the sense that you can return to your day, but the visible change is not instant. Within a few days, you can expect a noticeably smoother forehead with fewer lines. That window is the reason follow-up photographs taken the same afternoon rarely tell the whole story.
Because the effect is temporary, treatment becomes a schedule rather than a single event. Many patients treat it the way they treat a haircut or a dental cleaning, building it into the calendar so the muscle movement does not fully return before the next appointment. Your provider can tell you what interval makes sense for your response, since that varies from person to person.
Aftercare instructions are specific to the product and the practice, and they are worth following exactly. Ask your injector directly about activity, skincare, and anything else you should avoid in the hours after treatment rather than relying on what a friend was told at a different clinic.
Botox and Fillers Solve Different Problems
Botox and fillers like JUVÉDERM and Restylane are both popular treatments for moderate lines around the lips, forehead, and eyes, but they are not interchangeable. One relaxes the muscle that folds the skin. The other adds volume beneath the skin. Knowing which one addresses your concern is the difference between a satisfying result and a frustrating one.
| Treatment type | What it acts on | Typical target |
|---|---|---|
| Botox and similar neuromodulators | Muscle movement that folds the skin | Forehead lines, crow’s feet, frown lines |
| Fillers such as JUVÉDERM and Restylane | Volume beneath the skin surface | Moderate lines around the lips, forehead, and eyes |
Some patients are best served by one category, some by the other, and some by a combination. A line that is visible at rest because of lost volume behaves differently from a line that appears only when you make an expression. A consultation is where that distinction gets sorted out, and it is a good reason not to choose a treatment from a menu without an assessment.

Is Botox Safe and Effective?
Botox is safe and effective, and it will definitely help minimize your forehead lines when it is used appropriately. The qualifier is doing the work with a qualified provider who understands facial anatomy, screens for contraindications, and sets realistic expectations.
Botox is a prescription medicine, which means the decision to use it belongs in a medical conversation. Bring your full medication list, mention any neuromuscular conditions, and be honest about prior cosmetic treatments, including ones done elsewhere. If you are pregnant, planning pregnancy, or breastfeeding, raise it before treatment rather than after.
Also ask what to watch for afterward and who to call if something concerns you. Any provider offering injectables should be able to answer that clearly and give you a way to reach the practice.
Choosing a Provider in Denver
Injectable treatment looks simple in short videos and takes years to do well. The provider’s training, the assessment before the needle comes out, and the willingness to say no to an unrealistic request all shape the outcome more than the brand name on the vial.
Colorado Dermatology Center is a South Denver dermatology practice led by board-certified dermatologist Dr. James M. Swinehart, whose clinical experience spans more than three decades. The practice covers medical, surgical, and cosmetic dermatology, which means your cosmetic consultation happens in a setting where skin health is the foundation rather than an afterthought. That matters for forehead lines in particular, since the same skin can show sun damage, precancerous changes, or other findings that deserve attention on their own.
Patients considering Botox for forehead lines should expect a real conversation about goals, not just a price and a syringe. If the answer to “what are you hoping to change” is vague, the treatment plan will be vague too.

Questions Worth Asking at Your Consultation
A short list of questions makes the appointment more useful and surfaces any mismatch between your expectations and what the treatment can deliver.
- Which muscles are driving my forehead lines and crow’s feet, and where would you inject?
- How much movement should I expect to keep, and how do you decide the dose?
- Is Botox the right choice for this line, or is a filler or another approach a better fit?
- How soon should I expect to see a change, and when should I plan the next visit?
- What aftercare instructions do you recommend, and how do I reach you if I have a question?
- Are there findings on my skin today that I should have looked at separately?
The answers tell you as much about the provider as about the product. A clear, specific explanation is a good sign that the treatment plan is being built for your face rather than pulled from a template.
Frequently Asked Questions
How soon will I see results from Botox for forehead lines?
Visible change is not immediate. Within a few days, you can expect a noticeably smoother forehead with fewer lines as the treated muscles relax. Because the timeline varies from one patient to the next, ask your provider when to judge the result and when a follow-up makes sense for you.
Does Botox actually prevent new wrinkles?
Botox injections can prevent wrinkles from forming by reducing the repeated muscle contractions that fold the skin into the same creases. That is why some patients begin treatment while lines are still faint. Prevention is not the same as permanence, since the effect is temporary and movement returns if treatment stops.
Is Botox the same as filler for forehead lines?
No. Botox is a prescription medicine injected into muscles to temporarily improve the look of moderate to severe forehead lines, while fillers such as JUVÉDERM and Restylane add volume beneath the skin. Both are used for moderate lines around the forehead and eyes, but they address different causes and are often considered separately.
Can Botox treat crow’s feet as well as forehead lines?
Yes. Botulinum toxin is commonly used to treat lines in the upper one-third of the face, and crow’s feet sit within that zone alongside horizontal forehead lines. A provider will assess how the muscles around your eyes and brow work together and plan injections around your expressions rather than treating each area in isolation.
What should I do before booking a consultation in Denver?
Gather your medication list, note any prior cosmetic treatments, and write down what specifically bothers you in the mirror or in photos. Then choose a practice with a qualified injector who will assess your skin and explain the reasoning behind the plan. Colorado Dermatology Center schedules cosmetic consultations with that kind of evaluation built in.
Forehead lines and crow’s feet are a normal record of years of expression, and softening them is a personal choice rather than a requirement. What makes the choice a good one is accurate information: knowing which muscle creates the line, what Botox can and cannot change, how quickly the change appears, and who is holding the syringe. Start with a consultation, ask the questions on the list above, and let the plan come from an assessment of your own face.

Acne Scar Treatment on the Face: Texture and Depth Options
Facial acne scars are rarely a single problem. One cheek may have a soft, shallow dip that only shows in certain light, while the other has a narrow pit that holds shadow no matter what angles you try in the mirror. A raised, firm bump may sit near the jaw. These differences matter, because the treatment that smooths a shallow texture change is not the same one that lifts a tethered depression.
There is no single option that is best for everyone, and any practice that offers only one device will tend to see every scar through that lens. A more useful approach is to sort scars by what is actually happening under the skin, then match the tool to that structure. Sometimes the answer is a combination rather than one standout procedure.
Texture and Depth Are Two Separate Problems
Texture refers to the surface itself. It is the fine, uneven quality of skin that makeup catches on, the slight coarseness that makes light scatter instead of reflecting cleanly. Depth refers to what happens beneath that surface: indentations where collagen did not rebuild evenly after inflammation, bands of fibrous tissue that pull the skin downward, or excess tissue that pushes upward.
Most people have both. Resurfacing treatments address texture by encouraging the skin to rebuild its surface. Structural treatments address depth by physically changing the tissue underneath. A plan that only resurfaces a tethered scar will often produce a smoother surface over the same visible dent. A plan that only releases a tethered scar without refreshing the surface may leave the surrounding texture unchanged.
This is why an in-person assessment comes before any product recommendation or device setting. Scar type, skin tone, how recently the acne settled, and how the skin has responded to past treatments all shape what is realistic.
Matching the Treatment to the Scar Structure
The structural options below target specific scar behavior. They are frequently used alongside resurfacing rather than instead of it.
Subcision for Rolling Scars
Rolling scars are the ones that look like shallow valleys with sloped edges, often tethered to tissue below. Subcision uses a small needle to break up the scar tissue underneath a rolling acne scar, releasing the downward pull so the skin can rise.
Downtime is usually minimal, though bruising lasting one to two weeks may be seen. That bruising is the practical scheduling consideration: it is cosmetic and temporary, but it is visible, so timing around work or events is worth planning in advance.
Filler for Broad, Depressed Scars
Broad-based, depressed acne scars may be treated with Silikon-1000, an off-label filler used for permanent results. The phrase off-label matters. It means the product is being used in a way that differs from its formal labeling, which is a conversation to have directly with a treating physician rather than something to assume.
Filler approaches suit scars with a wide, soft depression more than narrow, sharply defined pits. The word permanent in the clinical description also deserves a careful reading. It describes the intended result of the product, not a guarantee for every individual scar.
Silicone for Raised Scars
Not every acne scar is a depression. Some heal as raised, firm tissue, and those need a different strategy. Silicone gel, applied as a sheet or an ointment, has been used since 1982 to treat a raised scar by reducing its size, hardness, redness, swelling, itch, or stiffness.
Silicone is non-invasive and can be used at home, which makes it a reasonable first layer for raised scarring. It works gradually and is not a resurfacing tool, so it will not change pitting or shallow indentations.
Resurfacing Options for Facial Texture
Resurfacing is the other half of most facial scar plans. It targets the surface quality of skin rather than the structural pull beneath it.
Fractional Laser and eCO2 Laser Resurfacing
Laser options for acne scars include fractional laser platforms such as ResurFX and eCO2 Laser. These approaches treat the skin in a pattern rather than all at once, which is the reasoning behind the fractional name: controlled injury prompts the skin to rebuild, and leaving untreated tissue between treated zones supports healing.
Laser resurfacing is generally aimed at texture, pore appearance, and surface irregularity. It carries a recovery period that varies with the aggressiveness of the settings, so the honest question is not whether a laser works but how much downtime fits your life right now.
Microneedling and RF Microneedling
Microneedling for acne scars creates controlled micro-channels in the skin to stimulate a remodeling response. RF microneedling adds radiofrequency energy delivered at depth, pairing the mechanical effect of the needles with a thermal one.
These are commonly listed among the corrective options for scarring because they address texture with a different recovery profile than ablative laser. Many practices treat them as a series rather than a single event, and results build over time.
Chemical Peels
Chemical peels for acne scars work on the surface layer, encouraging exfoliation and renewal. They are often described as helpful for discoloration and superficial texture, and less suited to changing structural depth on their own.
Peels are a practical option when post-acne marks are the main complaint rather than true indentations. Patients sometimes use the terms interchangeably, but marks and scars behave differently and respond to different tools.
A Device Option Without Topical Medication
TheraClear Acne System treats acne scars without any oral or topical medication, ointments, or creams. It is an FDA-approved vacuum and light device treatment. For patients who have struggled with topical routines or who want to avoid adding another product to their day, a device-based route is worth asking about.
It is one option among several, not a universal substitute for structural work. Suitability depends on scar type and skin history, and the device is best discussed as part of a broader plan.

Combining Treatments Often Produces the Best Result
Scarring is frequently multi-layered, so treatment is too. Combining acne scar treatments is a recognized strategy for maximizing results, pairing a structural procedure with a resurfacing one so that both depth and texture are addressed in the same overall plan.
A typical reasoning pattern looks like this:
- Release tethered, rolling scars with subcision, planning around one to two weeks of possible bruising.
- Refresh surface texture with a laser, microneedling, or RF microneedling option chosen for your recovery tolerance.
- Add chemical peels where discoloration is contributing to the uneven look.
- Use silicone gel on raised scars, since a raised scar needs reduction rather than resurfacing.
- Consider a filler for broad, depressed scars when structure rather than surface is the dominant issue.
The sequencing and spacing belong to your physician. Combining treatments does not mean stacking everything at once, and the right interval between procedures is a clinical judgment, not a menu choice.

Setting Realistic Expectations for Facial Scarring
Various products and procedures can improve the look of acne scars, but improvement is the operative word. Scar revision softens, refines, and blends. It rarely erases. Skin that has been through significant inflammation has a history, and the goal is usually a texture that reads as normal in ordinary light rather than a surface that has never been marked.
Two practical points help. First, active acne deserves attention before or alongside scar treatment, because treating scars over new inflammation works against the plan. Second, results accumulate. Scars that took years to form are usually not resolved in one session, and most resurfacing approaches are structured as a series with assessment in between.
At a practice focused on acne scar repair, the evaluation should include your scar types, your skin tone and healing history, and how much recovery time you can realistically protect. Board-certified dermatologist Dr. James M. Swinehart leads Colorado Dermatology Center in South Denver, where acne scar revision is part of a broader medical, surgical, and cosmetic dermatology practice. A consultation is the point at which general information like this becomes a specific plan.
Frequently Asked Questions
Can microneedling help boxcar scars?
Microneedling appears among the corrective options for acne scarring, and RF microneedling adds energy at depth. Whether it suits a boxcar scar depends on the scar’s walls, depth, and how much structural tethering is present. That is an in-person judgment, and it is common for boxcar scarring to be treated with more than one modality rather than microneedling alone.
How long does bruising last after subcision?
Subcision usually involves no downtime, but bruising lasting one to two weeks may be seen. The procedure uses a small needle to break up scar tissue underneath rolling acne scars, and the bruising is a normal part of the recovery rather than a complication. Plan social and work commitments with that window in mind.
Is there a permanent filler for depressed acne scars?
Broad-based, depressed acne scars may be treated with Silikon-1000, an off-label filler used for permanent results. Off-label means the use differs from formal labeling, so it should be discussed directly with a treating physician. Permanent describes the intended result, not a promise for every individual scar.
Do I have to choose just one treatment?
No. Combining acne scar treatments is a recognized approach for maximizing results, and it is often the practical choice for facial scarring with both texture and depth components. A structural procedure such as subcision may be paired with a resurfacing option like laser or microneedling, with spacing determined by your physician.
Is there an acne scar treatment without creams or medication?
TheraClear Acne System treats acne scars without any oral or topical medication, ointments, or creams, and it is an FDA-approved vacuum and light device treatment. It is one option among several rather than a replacement for structural work, so suitability should be confirmed during an evaluation of your specific scar types.

Skin Cancer Screening Cost: Denver Prices and Coverage
A skin check that feels like one simple visit can generate more than one bill, and the total often depends on things patients never think to ask about before they book. Skin cancer is the most common cancer in the United States, and early detection plays a critical role in treatment outcomes, which is why so many people want a straightforward answer about price before they make an appointment.
The honest answer is that a skin cancer screening cost is not a single fixed number. It shifts with where you live, who performs the exam, how the visit is coded for insurance, and whether anything suspicious turns up during the check. Here is how those pieces fit together, what published price ranges look like in other metro areas, and how Denver patients can get a real number instead of a guess.
What the Price of a Skin Cancer Screening Covers
A screening visit is usually a visual examination of your skin along with a review of your history and risk factors. The fee attached to that visit is not standardized across practices. Research on screening pricing points to several variables that move the number up or down:
- The complexity of the exam and how much of the body is checked
- Whether a board-certified dermatologist performs the screening
- Whether the screening is a standalone visit or part of a larger appointment
- Your location and the individual practice’s fee schedule
- Whether a biopsy or other procedure is added during the same visit
That last point matters more than most patients expect. A screening that stays a screening is one thing. A screening where the dermatologist removes a small sample for testing becomes a different visit with different charges attached to it.
Published Price Ranges for Skin Cancer Screening
Publicly posted ranges from dermatology practices in other metro areas give a useful reference point, even though Denver practices set their own fees. Published screening prices in Phoenix, Arizona and in Detroit and Dearborn, Michigan both fall in the same general band.
| Market | Typical published screening price | What the range reflects |
|---|---|---|
| Phoenix, AZ | $100 to $250 | Complexity of the exam and whether a board-certified dermatologist performs it |
| Detroit and Dearborn, MI | $100 to $250 | Complexity of the exam and any additional services during the visit |
| Denver, CO | Confirm directly with the practice | Local fee schedules are not published in the sources reviewed here |
Treat that $100 to $250 band as a benchmark rather than a Denver quote. A South Denver practice may sit above or below it depending on the clinician, the length of the visit, and whether the appointment is billed as a preventive screening or a problem-focused evaluation. The only reliable number is the one a specific office gives you in writing.

Why a Full-Body Screening Is Not Automatically Free Under Insurance
Many patients assume a routine full-body skin cancer screening is covered at no cost the way some other preventive services are. That assumption causes unpleasant surprises. Routine full-body skin cancer screening is not automatically free, even under insurance, because coverage depends on how the visit gets coded and on whether anything suspicious turns up.
Coding is the hinge. If you book a general skin check with no specific complaint, the visit may be submitted as preventive care. If you arrive with a spot that has been changing, or you point one out during the exam, the visit can be coded as diagnostic instead. Diagnostic visits are commonly subject to deductibles and coinsurance, which is how a “free” screening ends up with a patient balance.
This is not a reason to hide a concern. It is a reason to ask how the visit will be submitted before you are seen, so you can plan for the difference.
The Three-Bill Problem
One appointment can produce three separate bills, and understanding the split helps you read your statement later. The pieces usually break down like this:
- The office visit itself, coded as preventive or diagnostic
- Any procedure performed during the visit, such as a biopsy
- Laboratory or pathology charges for examining the tissue
These can come from different entities, arrive on different dates, and apply to your deductible in different ways. Before your appointment, ask the office which of these are included in the quoted price and which are billed separately. Requesting a written estimate is a reasonable ask and one that practices handle routinely.
Free and Low-Cost Screening Options
Cost should not be the reason someone skips a skin check. Free options exist, though they are limited and often tied to specific programs and eligibility rules.
The American Academy of Dermatology publishes a screening locator that lets you click your state to see scheduled free skin cancer checks in your area. Some programs provide screening services at no cost to participants, and some specifically offer free skin cancer screenings for low-income, uninsured residents ages 18 and up. Availability varies by location and by calendar, so it is worth checking the locator more than once if nothing is listed near you today.
If you have insurance but a high deductible, a free event or a clear self-pay quote may still be the more predictable path. Ask about both.

What Happens to Cost If Something Is Found
Screening and treatment are separate financial events. Once skin cancer or a precancerous lesion has been diagnosed, the cost of treatment depends on the size and location of the suspected lesion. A small lesion in an accessible spot and a larger lesion in a cosmetically or functionally sensitive area do not carry the same treatment plan or the same price.
That is why a screening quote should never be treated as a total estimate for the year. If your dermatologist recommends a biopsy, ask what the biopsy, pathology, and any follow-up treatment would involve so you are not comparing a screening fee to a treatment bill.
Questions to Ask Before You Book in Denver
A five-minute phone call can prevent most billing confusion. Ask these questions when you schedule:
- Is this appointment being scheduled as a preventive screening or as a problem-focused visit?
- How will the visit be coded for my insurance, and what will I owe if it is coded as diagnostic?
- What is the self-pay price if I choose not to use insurance?
- Is a biopsy included in that quote, or is it billed separately?
- Who processes the pathology, and will I receive a separate bill from them?
- Can you send me a written estimate before my appointment?
Bring your insurance card and be ready to describe any spots that concern you. Being specific at scheduling time helps the office code the visit accurately instead of guessing.

Getting a Straight Answer From a Denver Practice
Colorado Dermatology Center is a South Denver practice led by board-certified dermatologist Dr. James M. Swinehart, with more than three decades of clinical experience. The practice covers medical, surgical, and cosmetic dermatology, with particular depth in skin cancer treatment, including MOHS micrographic surgery.
If you are comparing screening prices in the Denver area, call the office and ask for the information above directly: how the visit will be coded, what the self-pay rate is, and what would be billed separately if a biopsy is needed. A practice that handles skin cancer treatment regularly will have clear answers, because these are the same questions their patients ask every week.
Price matters, but so does what the exam actually catches. A screening that costs a little more and identifies a lesion early is a better value than a cheaper visit that skips the full check. Use published ranges as your starting point, confirm the Denver number with the office, and get the estimate in writing before you go.
Frequently Asked Questions
Does insurance cover skin cancer screenings?
Not automatically. Routine full-body skin cancer screening is not always free even under insurance, because coverage depends on how the visit is coded and whether anything suspicious is found. A preventive screening may be handled differently than a diagnostic visit for a specific spot. Ask your insurer and the practice how the appointment will be submitted before you are seen.
How much does a screening cost without insurance?
The cost without insurance varies by location, provider, and whether the screening is a standalone visit or part of a larger appointment. Published ranges from practices in Phoenix and in Detroit and Dearborn fall between $100 and $250. Denver fees are set locally, so request a written self-pay quote from the office you plan to visit.
Where can I find a free skin cancer screening?
The American Academy of Dermatology maintains a screening locator where clicking your state shows scheduled free skin cancer checks. Some programs offer screening services at no cost to participants, including free screenings for low-income, uninsured residents ages 18 and up. Availability changes, so check the locator periodically if nothing appears in your area.
Why did one appointment produce multiple bills?
A single skin check can generate separate charges for the office visit, any procedure such as a biopsy, and the pathology review of the tissue. These may come from different billing entities and apply to your deductible differently. Asking which charges are bundled into the quoted price, and which are billed separately, keeps the final total predictable.
What if my dermatologist finds something suspicious?
Once skin cancer or a precancerous lesion has been diagnosed, treatment cost depends on the size and location of the suspected lesion. Screening fees do not include that care. Ask what a biopsy, pathology review, and any recommended follow-up would involve so you can plan for the full picture rather than only the initial visit.

Does a Dermatologist Do Skin Cancer Screening? What to Ask
Yes. Skin cancer screening is a standard part of dermatology practice, not a specialty add-on that requires a separate referral. Board-certified dermatologists perform full-body skin exams, evaluate individual moles and growths, and decide whether a spot needs to be watched, photographed, or sampled with a biopsy. Many practices describe comprehensive screening as a way to detect melanoma and other skin cancers as early as possible, which is exactly what a screening visit is designed to do.
What varies from practice to practice is how the visit is structured, how long it takes, what it costs, and how results are communicated. Those are the details worth asking about before you book, and they shape the questions below.
Why Dermatologists Handle Skin Cancer Screening
Skin cancer is the most common cancer and is increasing at a rapid rate. The three most common types are basal cell carcinoma, squamous cell carcinoma, and malignant melanoma. Dermatologists see these conditions daily, which means they develop a trained eye for the difference between a harmless mole and something that deserves a closer look.
Training matters here. Dermatologists are trained to use a dermatoscope, a handheld magnifying instrument with a light that is considered an essential tool in identifying skin cancers. A screening appointment is not just a visual once-over. It is an examination performed by someone who examines skin all day, using equipment designed to see structures beneath the skin surface that are not visible to the naked eye.
What Happens During a Full-Body Skin Exam
A full-body screening follows a fairly predictable sequence. The exact routine depends on the practice and on your reasons for being there, but most visits include the same core steps.
- You discuss your history and any spots that concern you, including how long you have noticed them and whether they have changed.
- You remove your clothes and change into a medical gown so that skin normally covered by clothing can be examined.
- The dermatologist examines you from head to toe, including areas people often overlook, such as the scalp, the backs of the ears, the nails, the soles of the feet, and the skin between the toes.
- Individual moles and growths are inspected, often with a dermatoscope, and compared with one another for the odd-one-out patterns that dermatologists look for.
- The dermatologist explains what was found and whether anything needs monitoring, a biopsy, or treatment, and recommends when to return.
Many practices offer these visits as annual full-body skin exams with mole checks built in. Others provide targeted mole checks when a patient has one specific spot in mind. Both are legitimate reasons to be seen, but they are not the same appointment, and it helps to know which one you have scheduled.
How Long a Screening Takes
Screening visits are shorter than most people expect. Many full-body skin screenings take as little as 10 to 15 minutes to complete, with the rest of the appointment time spent on intake, conversation, and any follow-up planning. If a biopsy is needed, that adds time.
| Element of the Visit | What to Expect |
|---|---|
| Typical length | As little as 10 to 15 minutes for a full-body screening |
| Clothing | Clothes removed, medical gown provided |
| Who examines you | A dermatologist, often board certified |
| Key tool | Dermatoscope, used to identify skin cancers |
| Possible next step | Mole biopsy to catch melanoma and skin cancer early |
If your appointment is a single-spot check rather than a full-body exam, the visit may be even briefer. Ask which type you are booking so your expectations match the schedule.
Who Should Consider a Screening
Screening is not limited to people who already suspect a problem. Practices commonly offer skin cancer screenings to men, women, and teens who have specific skin concerns or abnormalities, and annual full-body exams are a routine recommendation for many patients. A dermatologist can advise on how often you personally should be seen based on what the exam shows.
Anyone who has noticed something new should feel comfortable booking. That includes a mole that looks different from the others, a growth that has appeared recently, a bump that will not heal, or a patch of skin that has changed. These are the kinds of observations a screening is meant to evaluate.
Monthly Self-Checks Between Appointments
Screening does not replace what you can do at home. Checking your skin monthly for any unusual moles, growths, bumps, or patches of skin is a simple habit that helps you notice change early, and it gives you something concrete to report at your next visit. Screening is important for helping prevent and detect melanoma, and self-checks support that effort between professional exams.
A practical approach is to check in a consistent order, use a mirror for the back and scalp, and ask a partner to look at areas you cannot see. If something looks new, changing, or simply wrong to you, do not wait for your next scheduled appointment to mention it.
Questions to Ask Before You Book
The quality of a screening conversation depends on what you ask ahead of time. These questions will help you compare options and arrive prepared.
- Is this appointment a full-body skin exam or a check of one specific spot?
- Who will perform the exam, and is that clinician board certified in dermatology?
- Will a dermatoscope be used during the exam?
- How should I prepare, and what should I wear?
- How long should I plan to be there, including paperwork?
- Can a biopsy be performed the same day if something needs sampling?
- How will I be told about results, and how long does that usually take?
- What does the visit cost, and is it billed as preventive screening or as a diagnostic problem visit?
- Should I bring a list of spots I want checked, or photos of changes I have noticed?
The billing question is worth asking directly. Insurance and cost details vary by practice and plan, and no clinic can quote your coverage accurately without checking your information. Ask the front desk staff to verify before the appointment so there are no surprises.
Questions to Ask During and After the Exam
- Did anything look suspicious, and are we watching it or acting on it now?
- Which specific spots should I keep an eye on, and what change would warrant a call?
- How often should I come back for a full-body exam?
- Would photographs or measurements help track these spots over time?
- What should I do if something changes before my next appointment?
- How should I protect my skin going forward, given what you saw today?
- If a biopsy was taken, when and how will I hear the result?
Write the answers down or ask for them in a patient portal message. A year is a long time, and the specifics of which mole was being watched are easy to forget.
If the Dermatologist Finds Something Suspicious
A screening is not a biopsy, and most spots examined during a screening turn out to need only monitoring. When something does need sampling, dermatologists perform mole biopsies and skin checks specifically to catch melanoma and skin cancer early. Some practices, including Colorado Dermatology Center in South Denver, also offer MOHS micrographic surgery for skin cancer treatment. That practice is led by board-certified dermatologist Dr. James M. Swinehart and combines more than three decades of clinical expertise with medical, surgical, and cosmetic dermatology.
Free and Lower-Cost Screening Options
Cost is a real barrier for some patients, and free skin cancer checks do exist. The American Academy of Dermatology publishes a map where you can find a free skin cancer check near you. The listing notes whether an appointment is required or walk-ins are welcome, since that differs from event to event. Schedules and requirements change, so confirm the details with the sponsoring organization before you go.
Frequently Asked Questions
Does a dermatologist do skin cancer screening checks?
Yes. Dermatologists perform skin cancer screenings as part of routine medical dermatology. A full-body exam involves changing into a gown and having your skin examined from head to toe, often with a dermatoscope, which is an essential tool for identifying skin cancers. Many full-body screenings take as little as 10 to 15 minutes, with extra time if a biopsy is needed.
How often should I have a skin cancer screening?
There is no single schedule that fits everyone. Many practices frame full-body skin exams and mole checks as annual visits, but the right interval depends on what your dermatologist finds and on any spots being monitored. Ask at the end of your exam how often you should return, and ask what specific change would justify calling sooner.
Can I book a skin check if nothing looks wrong?
Yes. Screenings exist to detect melanoma and other skin cancers as early as possible, which means they are useful before you notice a problem. Practices commonly offer screenings to men, women, and teens who have particular skin concerns or abnormalities. Monthly self-checks are still worthwhile between visits, since you are the person most likely to notice a new or changing spot first.
What should I wear and how should I prepare?
Wear something easy to remove, because you will undress and change into a medical gown for a full-body exam. Skip nail polish so your nails can be checked, and bring a list of any spots that concern you along with notes on when you first noticed them. Arrive early enough to complete paperwork without eating into exam time.
Will I find out the results at the appointment?
For most spots, yes. Your dermatologist can tell you during the visit whether something looks benign, needs monitoring, or should be sampled. If a biopsy is performed, the tissue must be examined before a result is available, so ask when and how you will be contacted. Confirm the follow-up method before you leave the office.
Booking a screening is a short appointment with a clear purpose, and the conversation around it matters as much as the exam itself. Ask who is performing the check, whether it covers your whole body, and how findings will be communicated, then keep up with monthly self-checks in between visits. If a spot worries you, call and describe it rather than waiting for the calendar to come around.
Skin Cancer Screening Near Me: Choosing a Denver Clinic
A search for skin cancer screening near me returns a map full of pins, and from the outside most of them look the same. A photo of a waiting room, a star rating, a phone number, a booking button. What that results page rarely tells you is who will actually examine your skin, whether that person focuses on skin cancer all day, or what happens if something suspicious turns up. Denver patients have real choices, and the best clinic is the one that can walk with you from a first look through diagnosis and, if needed, treatment. This is a practical way to sort through the list.
Start With What a Screening Actually Is
A skin cancer screening is a thorough examination of your skin by a healthcare professional, looking for early signs of skin cancer or precancerous lesions. That definition matters because it sets expectations. A screening is a visual and hands-on assessment, not a diagnosis carved in stone, and not a substitute for a biopsy when one is needed.
Many practices describe their screenings as full-body exams that use dermoscopy to detect suspicious lesions early. Dermoscopy is a handheld magnified light tool that lets a clinician see structures beneath the skin surface that are invisible to the naked eye. If a clinic’s service page mentions dermoscopy by name, that is a useful signal that the visit is built around skin cancer detection rather than a quick glance.
Time is another practical detail. One dermatology practice’s screening page notes that appointments typically last between 15 and 30 minutes, and that range is a reasonable expectation for a focused skin check. Ask when you book so you can plan your day and arrive without rushing.
Read the Skin Cancer Page, Not Just the Homepage
Almost every clinic homepage looks polished. The skin cancer section is where the substance usually lives, and it is worth two or three minutes of reading before you call anyone.
- Does the page describe full-body exams, dermoscopy, or both, or does it only promise “skin checks” in one vague sentence?
- Does the clinic explain what happens after a suspicious spot is found, including biopsy and pathology?
- Is there information about treatment, or does the site stop at screening?
- Are the clinicians named, with credentials and specialties listed?
- Can you tell from the page who performs the screening itself?
A clinic that treats skin cancer seriously tends to write about it in detail. Thin content on the topic is not proof of poor care, but detailed content gives you better questions to ask.
Check Who Performs the Exam
Some screening listings are staffed by board-certified dermatologists, and others by physician assistants, nurse practitioners, or primary care clinicians with dermatology experience. None of those is automatically the wrong answer, but you deserve to know before you arrive.
For patients with a personal history of skin cancer, many atypical moles, a family history of melanoma, or a spot that has been changing, a board-certified dermatologist is a sensible starting point. A board-certified dermatologist has completed specialized training in skin disease and skin surgery. Colorado Dermatology Center is led by board-certified dermatologist Dr. James M. Swinehart, whose clinical work spans medical, surgical, and cosmetic dermatology.
Look for a Full Care Pathway, Including MOHS Surgery
A screening is only useful if the next step is clear. Ask what happens if the clinician finds something that needs a biopsy, and where that biopsy is read. Ask who performs the procedure if skin cancer is confirmed.
MOHS micrographic surgery is a specialized technique for removing certain skin cancers while sparing as much healthy tissue as possible, and not every practice offers it. When a clinic provides screening, biopsy, and MOHS surgery under one roof, you avoid restarting the search at the most stressful moment. Colorado Dermatology Center emphasizes skin cancer treatment including MOHS surgery, alongside medical, surgical, and cosmetic dermatology.
Apply the Practical Filters: Location, Scheduling, and Coverage
Once you have two or three clinics that pass the clinical test, practical details decide the rest. Drive time matters more than people expect, because a screening is a recurring appointment rather than a one-time errand. A clinic that is easy to reach on a workday is a clinic you will actually return to.
Ask about scheduling lead time when you call. Ask whether the appointment is a focused skin check or a general dermatology visit that also includes a skin exam. And ask about coverage directly, since plan networks and benefits vary. The research behind this article did not include pricing, so confirm costs and insurance details with the clinic and your insurer before the visit rather than relying on any number you see online.

Questions Worth Asking Before You Book
- Who will perform my screening, and what are that person’s credentials?
- Will the exam be full body, and will dermoscopy be used?
- How long is the appointment, and should I arrive with a clean face and no nail polish?
- If something needs a biopsy, is it done in this office and how are results communicated?
- Does this practice offer MOHS surgery or other skin cancer treatment if it is needed?
- Is this clinic in network for my insurance plan, and what will I owe?
- How often should I come back for another screening given my history?
Those seven questions take about five minutes on the phone and can save you a wasted appointment. A well-run front desk will answer them without hesitation.
Sorting Through Directory Listings and Reviews
Directory sites and review platforms are useful for surfacing names, phone numbers, and rough geography, and they are common starting points for a skin cancer screening near me search. Treat them as a first filter, not the final word. Listings can lag behind reality, and a review written about a cosmetic treatment says little about how a practice handles a suspicious mole.
Use the listing to get a clinic name, then go to the practice’s own website and read its skin cancer pages. Confirm the address and phone number there before you drive anywhere. If a listing and the practice site disagree, trust the practice site and call to verify.
What to Bring and How to Prepare
Preparation is simple and makes the visit more productive. Come with clean skin, meaning no makeup, no self-tanner, and no nail polish on hands or feet, since pigment changes under nails can matter. Bring a list of your medications, your insurance card, and a note of any spot that has been itching, bleeding, or changing.
It also helps to bring a short family history of skin cancer if you know it, and to mention past sunburns or tanning bed use. Point out anything that concerns you, even if it seems minor. You know your skin better than anyone who is meeting it for the first time.

How Colorado Dermatology Center Fits a Denver Search
Colorado Dermatology Center is a South Denver dermatology practice built around medical, surgical, and cosmetic skin care, with a strong focus on skin cancer treatment. Patients searching for screening in the Denver area can request an appointment and ask directly about the scope of a skin exam, biopsy availability, and surgical options.
The practice combines more than three decades of clinical expertise with procedures that many offices do not offer, including MOHS surgery, hair restoration, tumescent liposuction, acne scar revision, and clinical research trials. That breadth matters for skin cancer patients, because it means a screening can lead to coordinated care rather than a referral letter and a new waiting list.
Frequently Asked Questions
How long does a skin cancer screening take?
One dermatology practice’s screening page notes that appointments typically last between 15 and 30 minutes. Actual time depends on how many spots need closer inspection, whether dermoscopy is used, and whether a biopsy is performed during the same visit. Ask when you schedule so you can allow enough time, and plan a little extra for paperwork if you are a new patient.
Do I need a referral to book a screening?
That depends on your insurance plan and the clinic’s scheduling rules. Some plans allow you to book a dermatology appointment directly, while others require a referral from a primary care clinician first. Call the clinic and your insurer before booking, and confirm both the referral requirement and your coverage so the visit does not turn into a billing surprise.
What should I bring to my first screening appointment?
Bring your insurance card, a photo ID, a list of medications and supplements, and notes on any family history of skin cancer. Come with clean skin, no makeup or nail polish, and a written list of spots that concern you. Mention past sunburns or tanning bed use, since that history shapes how closely a clinician will look.
How do I know if a clinic treats skin cancer or only screens for it?
Read the clinic’s service pages and look for biopsy, pathology, and surgical treatment such as MOHS micrographic surgery. Screening-only practices typically refer confirmed cancers elsewhere. Neither model is wrong, but knowing which one you are choosing helps you decide whether you want a single practice to handle the entire pathway from exam to treatment.
How often should I be screened?
There is no single schedule that fits everyone, and the research behind this article did not establish one. Your clinician can recommend an interval based on your personal and family history, skin type, sun exposure, and previous biopsies. Ask that question directly at your visit, and write the answer down so you can act on it.
Finding the right clinic comes down to a handful of unglamorous steps: read the skin cancer pages, ask who performs the exam, confirm what happens after a suspicious finding, and check coverage before you arrive. A practice that answers those questions clearly is usually a practice that runs a careful screening. If a spot has been on your mind, let that be the reason you make the call this week rather than next season.
Wrinkle Treatment in Denver: Injectables, Fillers, and Your Options
Denver has no shortage of places to get a wrinkle treatment. A quick search turns up dermatology practices, med spas, and hospital-affiliated clinics, all offering different combinations of injectables, fillers, lasers, and radiofrequency devices. The harder question is which of those options actually matches what is happening on your face.
Two people with the same line across the forehead can need very different approaches. One may have a muscle-driven crease, another may have lost volume beneath it, and a third may be seeing texture changes from years of sun exposure. The sections below break down the main categories of wrinkle treatment available in Denver, explain what each one is designed to do, and outline the questions worth asking before you book.
Why a Single Wrinkle Can Have Several Causes
Wrinkles form for more than one reason, and the treatments built to address them work in different ways. Expression lines come from repeated muscle movement. Folds that stay put when your face is relaxed often involve volume loss or changes in the skin’s support structure. Crepe-like texture and fine surface lines usually reflect collagen and elastin changes, often accelerated by sun exposure and pigment damage.
That distinction matters because a treatment aimed at muscle movement will not rebuild lost volume, and a device aimed at tightening skin will not soften a crease created by the muscles underneath. Many practices combine categories for exactly that reason. One Colorado skin clinic describes pairing two treatments as a way to maximize tightening while also reducing wrinkles, removing dark spots, and smoothing crepe-like skin texture. The combination is the point, not any single device.
Injectables: Neuromodulators for Movement Lines
Neurotoxins are the injectables most people mean when they say Botox. Denver practices list options such as Botox and Daxxify, and the category is used to treat signs of aging, including wrinkles and sagging skin around the face and jawline. These products work on the muscle activity that folds the skin, which is why they are typically chosen for lines that appear or deepen when you make an expression.
What a neuromodulator will not do is fill a hollow or lift tissue that has dropped. If your main concern is a fold that stays visible when your face is completely still, a muscle-relaxing injection on its own may leave you underwhelmed. Knowing that in advance protects you from paying for a treatment that was never designed to solve your particular problem.
Fillers: Restoring Volume and Softening Static Folds
Fillers add volume. Denver-area clinics list products such as Juvederm and Sculptra, which fall into different families: hyaluronic acid fillers that provide structural support, and collagen-stimulating options that work through the skin over time. Both are used for the folds and hollows that remain visible at rest, including lines around the mouth and the loss of fullness that can make a face look tired.
Filler results depend heavily on placement and restraint. The goal is not to erase every line, it is to restore enough structure that the face still moves and still looks like you. A thoughtful injector will talk about proportions and balance rather than a single crease. Because products differ in how they behave and how long they last, the choice belongs in a conversation with a clinician who can see your face in three dimensions, not on a price list.
Energy-Based Treatments for Texture, Laxity, and Pigment
Not every wrinkle is a fold. Some are surface changes that respond better to devices than to needles. Denver practices offer several categories worth understanding:
- Radiofrequency skin tightening, including Pellevé, a non-invasive option that uses radio waves to heat deeper layers of skin and reduce the appearance of fine lines and wrinkles without needles or surgery.
- Radiofrequency microneedling, listed by Denver clinics as Morpheus and Genius, which is used to improve skin texture, wrinkles, scars, and laxity.
- IPL and laser rejuvenation, which target tone, texture, and pigmentation while reducing the look of wrinkles.
- Combination protocols that pair tightening with resurfacing so several concerns are addressed in one plan.
These treatments are cumulative by nature. They ask for a series and for patience while collagen responds, which is a different rhythm from a single injection. They also tend to be the better fit for someone whose primary complaint is crepey texture, sun-related discoloration, or general laxity rather than one deep crease.
Matching the Treatment to What You See in the Mirror
Start with what you actually notice, then work backward to the category that addresses it. The table below maps common concerns to the treatment families described above. It is a conversation starter, not a prescription.
| What you notice | Category that usually addresses it | What to ask about |
|---|---|---|
| Lines that appear only with expression | Neuromodulators such as Botox or Daxxify | Which muscles create the line, and whether treating them alone will change your look |
| Folds visible at rest, or hollowing | Fillers including Juvederm and Sculptra | Which product family fits, and how placement will be balanced |
| Crepey texture and fine surface lines | Radiofrequency tightening such as Pellevé, or RF microneedling | How many sessions are needed and what improvement is realistic |
| Sun damage, uneven tone, pigment | IPL and laser rejuvenation | Whether pigmentation should be treated alongside or before wrinkles |
| Several concerns at once | Combination protocols | How treatments will be sequenced and spaced |
What a Good Consultation Looks Like in Denver
Colorado Dermatology Center, the South Denver practice led by board-certified dermatologist Dr. James M. Swinehart, is one example of the medical side of this market. The practice combines more than three decades of clinical expertise with medical, surgical, and cosmetic dermatology, and its facial rejuvenation work emphasizes personalized care and natural-looking results rather than a single signature procedure.
That orientation is worth looking for anywhere you go. A consultation should include an honest assessment of your skin, a discussion of what you want to change and what you want to keep, and a clear explanation of what each option can and cannot do. Ask who will perform the treatment and what happens if you are not happy with the result. Specific devices and product lines vary by practice, so confirm availability when you schedule.
Questions Worth Asking Before You Book
- What is causing this particular line, and which category of treatment addresses that cause?
- Is this one appointment or a series, and how will we judge whether it worked?
- What will my face look like in two weeks, and what will it look like in six months?
- How do you handle a result I do not like?
- If we combine treatments, how far apart will they be spaced?
Bring those questions in writing. The answers tell you as much about the practice as the treatment menu does, and a clinician who welcomes them is usually a clinician who will be honest about limits.
Frequently Asked Questions
Which wrinkle treatment is best for my face?
There is no single best option. A clinician will look at whether your lines come from muscle movement, volume loss, surface texture, or sun damage, then match the treatment to that cause. A crease that appears only when you smile points to a different approach than a fold that stays visible at rest.
Do injectables and fillers do the same thing?
They work in different ways. Neuromodulators such as Botox and Daxxify reduce the muscle activity that folds the skin, which softens expression lines. Fillers such as Juvederm and Sculptra add volume and support, which helps folds and hollows that remain visible when your face is relaxed. Many plans use both because those problems often appear together.
Can wrinkle treatments be combined?
Yes, and Denver practices frequently build plans that way. Pairing treatments is often described as a way to maximize tightening while also reducing wrinkles, dark spots, and crepe-like texture. Sequencing matters, so ask how the appointments will be spaced and what result you should expect from each stage before you commit.
Are these treatments surgical?
No. The options discussed here are non-invasive or minimally invasive. Pellevé, for example, is a radiofrequency treatment that reduces the appearance of fine lines without needles or surgery, and injectables are delivered in a clinic visit. Surgical options exist for more significant laxity, but that is a separate conversation with your physician.
How do I choose a provider in Denver?
Look for a practice that explains the reasoning behind a recommendation, not just the price. Credentials matter, and so does a willingness to tell you when a treatment will not help. Colorado Dermatology Center in South Denver, led by board-certified dermatologist Dr. James M. Swinehart, is one practice to consider, and comparing consultations is a reasonable step.
Acne and Scar Treatment in Denver: Match Procedure to Scar
Acne and scar treatment works best when the plan matches what is on the skin. A dark mark left after a pimple does not behave the same way as a boxcar or rolling scar. At Colorado Dermatology Center, a South Denver practice led by board-certified dermatologist Dr. James M. Swinehart, a customized plan begins with the skin.
Scars can form after acne clears, and dermatologist insight may help with prevention. Once scars are present, treatment options include dermabrasion, chemical peels, microneedling, dermal filler injections, laser resurfacing, light therapies, punch grafts, and autologous fat transfer. The useful question is not which option sounds strongest. It is which option fits the scar pattern, the skin’s healing needs, and the patient’s goals.
Post-acne marks and scars need different starting points
Dermatology sources describe post-acne marks as a separate concern from acne scars. Topical retinoids are one option for improving the look of post-acne marks, and retinol can help visibly lighten dark spots. A patient may see color and assume a scar must be cut, lasered, or filled. A dermatologist can assess whether the concern is primarily pigment, texture, or a true scar before recommending a procedure.
True scars can form after acne clears. The American Academy of Dermatology notes that patients may be able to prevent acne scars with a dermatologist’s insight. Waiting to see whether every mark resolves is understandable, but a consultation can clarify what may respond to topical care and what may need a procedure.
Why scar pattern matters in a Denver treatment plan
Not every acne scar responds the same way to the same device or peel. A dermatology source focused on effectiveness states that lasers are considered the most effective option for improving the appearance of acne scars, particularly boxcar and rolling scars. Ablative, fractional lasers are usually the type discussed. That does not mean every patient needs a laser. It means scar pattern belongs at the center of the decision.
Boxcar and rolling scars are named patterns in the source material. Other scars do not fit a simple description. A customized plan allows the dermatologist to combine options when needed and sequence care around healing. The plan should follow the skin, not a menu designed for a different scar.
A procedure-by-procedure view
The table below summarizes options named in the source material and the role each may play. It is a starting point for a consultation, not a prescription. A dermatologist decides which option or combination fits a specific scar and patient.
| Option | What the source material says | Where it may fit |
|---|---|---|
| Topical retinoids | Can improve the look of post-acne marks; retinol can visibly lighten dark spots. | Post-acne marks and dark spots, after assessment. |
| Laser resurfacing and light therapies | Lasers considered most effective for acne scars, particularly boxcar and rolling scars; ablative fractional lasers usually discussed. | Scar patterns that fit the evaluated laser approach. |
| Chemical peels | Listed as acne scar treatment. | Part of a customized scar plan. |
| Microneedling | Listed as skin needling among acne scar treatments. | Part of a customized scar plan. |
| Dermabrasion | Listed as acne scar treatment. | Part of a customized scar plan. |
| Dermal filler injections | Listed among acne scar treatments; collagen injections also appear in scar removal information. | Selected cases after dermatologist evaluation. |
| Punch grafts and autologous fat transfer | Listed in acne scar removal information. | Selected cases after dermatologist evaluation. |
Laser resurfacing and light therapies
Laser resurfacing receives the strongest mention in the source material for boxcar and rolling scars. Lasers are considered the most effective for improving the appearance of acne scars, particularly those patterns, and ablative fractional lasers are usually discussed. A consultation should confirm whether a laser is appropriate for the scar type and recovery plan.
Light therapies also appear in the treatment list. They are not interchangeable, and the source material does not rank every device against every scar. That gap is why a dermatologist’s assessment matters. The goal is not the most aggressive option. It is a treatment that matches the scar and can be carried out with a clear aftercare plan.
Chemical peels, microneedling, and dermabrasion
Chemical peels, microneedling, and dermabrasion are all named as acne scar treatments in the source material. They appear alongside laser resurfacing, filler injections, and surgical options. A patient may hear about one of these from a friend or an online review, but the better question is how it fits the evaluated scar.
Microneedling is also called skin needling. Dermabrasion and chemical peels are described as methods for acne scar removal. The sources do not provide a single rule that says every boxcar scar needs one option and every rolling scar needs another. They do support a structured consultation in which the dermatologist examines the scars, reviews the options, and explains the recommendation.

Fillers, punch grafts, and fat transfer
Dermal filler injections appear in the acne scar treatment list. Collagen injections, punch grafts, and autologous fat transfer appear in acne scar removal information. They are specialized options that a dermatologist may consider for selected scars after an in-person evaluation.
Several advanced options are useful for patients who have been told that nothing can be done. A filler, a punch graft, and a laser do different things, and the source material does not support using them interchangeably. A board-certified dermatologist can explain the tradeoffs and whether a referral or another approach is more appropriate.
What a customized plan at Colorado Dermatology Center can include
Colorado Dermatology Center describes acne scar revision as part of its dermatology services. The practice’s approach emphasizes personalized care and procedures that many practices do not offer. A consultation should start with the scar, not with a device.
A customized plan may include topical care for post-acne marks, a procedural option for scars, or a combination. The source material supports topical retinoids for the look of post-acne marks and lists dermabrasion, chemical peels, microneedling, dermal fillers, laser resurfacing, light therapies, punch grafts, and fat transfer as scar-related options. The dermatologist matches those tools to the finding on the skin.
After treatment, protect the healing skin
Aftercare is part of the treatment match. The American Academy of Dermatology advises avoiding tanning and spending time in the sun after acne scar treatment because the skin needs time to heal. In general, patients should avoid too much time in the sun during that healing period. A plan that ignores aftercare is incomplete.
Sun protection and healing time should be discussed before the procedure. The source material does not provide a single recovery timeline for every option, so patients should ask what their specific plan requires. That conversation should cover what to avoid and when to return for follow-up.
What to ask at an acne and scar treatment consultation
A good consultation should leave a patient able to explain why a specific option was chosen. These questions can help:
- Which concerns are post-acne marks and which are true scars?
- Does my scar pattern fit the boxcar or rolling patterns described in laser research, or is another approach more appropriate?
- Is a topical retinoid part of the plan for dark spots?
- Which options from the treatment list are relevant to my skin?
- What aftercare is required, including sun avoidance and healing time?
- Is the recommended plan customized to my scars?
These questions are not a substitute for an examination. They are a way to make the conversation specific. A dermatologist can answer them with reference to the actual scars and the available treatments.
Frequently Asked Questions
Do post-acne marks always fade on their own?
The source material does not promise that every mark will fade on its own. It separates post-acne marks from scars and notes that topical retinoids can improve the look of post-acne marks, with retinol helping to visibly lighten dark spots. A dermatologist can assess whether a mark will respond to topical care or needs another approach.
Does microneedling help acne scars?
Microneedling, also called skin needling, is listed among treatments for acne scars. The sources do not say it is the best option for every scar type or every patient. A dermatologist can determine whether microneedling fits the scar pattern and whether it should be used as part of a customized plan.
Are lasers the most effective treatment for acne scars?
One dermatology source states that lasers are considered the most effective for improving the appearance of acne scars, particularly boxcar and rolling scars, with ablative fractional lasers usually discussed. That is a strong statement for those scar patterns, not a universal ranking for every scar. An in-person evaluation should confirm whether laser resurfacing is appropriate.
Can acne scars be prevented?
The American Academy of Dermatology notes that scars can form after acne clears and that patients may be able to prevent acne scars with a dermatologist’s insight. The source material does not provide a guaranteed prevention method for every person. Early evaluation is reasonable when acne is leaving marks or textural changes, because a dermatologist can advise on care before more scarring develops.
What should I avoid after acne scar treatment?
The American Academy of Dermatology advises avoiding tanning and spending time in the sun after treatment because the skin needs time to heal. In general, patients should avoid too much time in the sun during recovery. Ask the treating dermatologist for instructions specific to the procedure, since the source material does not give one recovery schedule for every option.
Skin Assessment in Denver: What a Full-Body Exam Reveals
A skin assessment is a structured physical examination of the body’s largest organ, and it covers far more ground than most people expect. It is not a quick look at a single mole or a spot that has been bothering you. A proper assessment involves observing the entire body surface, feeling the skin and the tissue beneath it, and documenting what is found so that changes can be tracked over time. At Colorado Dermatology Center in South Denver, this kind of systematic review is part of how board-certified dermatologist Dr. James M. Swinehart and the clinical team build a complete picture of your skin health.
What a Skin Assessment Actually Covers
Clinical guidance on skin assessment is consistent on one point: the examination should include actual observation of the entire body surface. That means the skin on the back, the scalp, the soles of the feet, and the areas that are easy to overlook all belong in the review. The scope is broader than skin alone.
A comprehensive assessment typically includes:
- Observation of the entire body surface, including any existing wounds
- Inspection of the hair and scalp
- Inspection of the nails on hands and feet
- Inspection of skin folds, such as those under the breasts or in the groin
- Inspection of the web spaces between the fingers and toes
- Palpation of the skin and underlying tissue
That head-to-toe sequence is deliberate. Working in a fixed order reduces the chance that a lesion, a rash, or a subtle change in texture gets skipped because attention was pulled toward something more obvious.
The Visual Pass: Head to Toe
The inspection phase is about pattern recognition. A clinician is not only scanning for something suspicious in isolation. They are comparing one side of the body to the other, noting where skin looks different from the surrounding area, and checking whether a finding is solitary or part of a wider distribution.
Hair and nails are included because they can reflect what is happening in the skin beneath them. Nail composition and texture changes are part of the standard assessment picture, alongside skin findings. Skin folds and the web spaces between digits are examined because these are warm, often moist environments where irritation and breakdown can develop quietly and go unnoticed by the person living in that body.
Wounds, if present, receive specific attention. Their location, size, and appearance are documented rather than simply noted in passing, because a wound that is not measured and described cannot be compared meaningfully at the next visit.
Palpation: What Hands Find That Eyes Miss
Looking is only half of the examination. The other half involves the clinician feeling the area with their hands to determine the texture of the skin and the tissue underneath it. This step adds information that visual inspection cannot supply.
During palpation, a clinician checks for lumps, bumps, pimples, and changes in texture. They also note areas that feel unusually soft, unusually firm, or what is often described as boggy. A boggy sensation suggests tissue that is not behaving the way the surrounding skin does, and it is the kind of finding that is essentially invisible until someone presses on it.
Depth matters as well. Feeling the tissue below the surface helps distinguish a change that sits within the skin from one that involves deeper structures. That distinction shapes what happens next.
The Core Elements Clinicians Document
Documentation turns an examination into a record. A skin assessment commonly captures skin temperature, dryness, itching, bruising, and changes in the texture of the skin and nail composition. Each element is simple on its own, and together they form a baseline.
| Element | What is being checked |
|---|---|
| Temperature | Whether skin feels warmer or cooler than expected |
| Dryness | Areas of scaling, flaking, or rough texture |
| Itching | Reported itch and the areas involved |
| Bruising | Marks that may not be explained by known injury |
| Texture | Changes in skin feel and in nail composition |
None of these elements is dramatic in isolation. Their value comes from the pattern they form and from how that pattern compares with the previous assessment. Dryness that is new in one area tells a different story than dryness that has been stable for years.
Why Skin Breakdown Gets Its Own Attention
Pressure injuries and other forms of skin breakdown are a major reason structured skin assessment exists as a formal clinical process. Prevention and treatment both start with an in-depth assessment, because damage that is caught early is far easier to manage than damage discovered after it has progressed.
This is particularly relevant for people with limited mobility, those who spend long periods in bed or in a chair, and anyone using compression bandaging or similar devices. In those situations, assessment is not a one-time event. Clinical protocols call for reassessment on a regular schedule, whenever a person’s condition changes, and at points of transfer or discharge. The principle is straightforward: skin changes, so the record has to change with it.
What to Expect at a South Denver Dermatology Visit
An office assessment follows the same logic as the clinical protocols described above, adapted to a dermatology setting. You can expect to be asked about what you have noticed, including itching, dryness, tenderness, or marks you cannot explain. You can expect to be looked at thoroughly rather than selectively, which may mean removing clothing or wearing a gown so that areas normally covered can be seen.
You can also expect the clinician to touch your skin, not just look at it. Palpation of a lesion or a patch of skin is a normal and necessary part of the examination, and describing what it feels like is part of the clinical record. If something is found, the next step is usually a conversation about what it could represent and what, if anything, should be done about it.
Preparation is minimal. Arriving with clean skin and without heavy makeup or nail polish on at least some nails helps, since cosmetics can obscure both skin and nail findings. Bring a list of any products you use and any symptoms you have noticed, along with roughly when they started. If you have had a previous skin assessment elsewhere, those records are useful for comparison.
Frequently Asked Questions
How is a full-body skin assessment different from checking one spot?
A spot check focuses on a single concern. A full-body assessment involves observation of the entire body surface, including the scalp, nails, skin folds, and the web spaces between fingers and toes, plus palpation of the skin and underlying tissue. The broader view is what allows a clinician to notice patterns and compare findings across areas.
Does a skin assessment hurt?
No. The examination is noninvasive. It involves looking at your skin and feeling it with the clinician’s hands to judge texture and the tissue beneath. You may feel light pressure during palpation, and you should speak up if any area is tender, because that information is itself a useful finding.
How often should skin be reassessed?
That depends on your situation. Formal clinical protocols call for reassessment at regular intervals, whenever a person’s condition changes, and at transfer or discharge. In a dermatology setting, the right interval depends on your history and what was found. Ask your clinician what schedule makes sense for you rather than assuming a fixed timeline.
What does a boggy area of skin feel like?
Boggy describes tissue that feels unusually soft and slightly spongy rather than firm or normally resilient when pressed. It stands out from the surrounding skin. Clinicians check for this during palpation, along with lumps, bumps, and areas that feel unusually firm, because these texture differences can point to something worth evaluating further.
Skin assessment works best as an ongoing relationship rather than a single appointment. A baseline recorded today becomes the reference point that makes a subtle change visible next year, and that continuity is where the real value sits. If you have noticed dryness, itching, bruising you cannot account for, a change in texture, or a spot that simply looks different from the rest of your skin, that observation is worth bringing to a clinician who can examine it properly and document what they find.
Skin Cancer Treatment in Denver: Screening, Diagnosis and Removal
Colorado’s sunshine is one of the state’s best features, and it is also a big part of why skin cancer is so common here. Denver dermatologists see the consequences of that exposure regularly: a basal cell carcinoma on a nose, a squamous cell carcinoma on an ear, a melanoma discovered during a routine full-body check. The reassuring part is that the path from a suspicious spot to a confirmed diagnosis and a definitive removal is well established, and Denver has a deep bench of specialists who handle each step.
This guide walks through what screening, diagnosis, and removal look like going into 2026, how Mohs micrographic surgery fits into the picture, and which questions are worth asking before you commit to a provider. Colorado Dermatology Center, the south Denver practice led by board-certified dermatologist Dr. James M. Swinehart, brings more than three decades of clinical experience to exactly this kind of care, from the first skin check to surgical removal and follow-up.
Why Skin Cancer Screening Matters in Sunny Colorado
Skin cancer is all too common in sunny Colorado, which is why health systems across the state, including UCHealth, maintain dedicated skin cancer specialists for diagnosis and treatment. National figures cited by Denver-area dermatology practices put the lifetime risk at roughly one in five Americans. Those numbers are not meant to frighten anyone. They are meant to explain why routine skin checks belong on the calendar the same way dental cleanings do.
Screening is not only for people who have already spotted something odd. Many skin cancers begin as changes that are easy to overlook in a mirror, particularly on the scalp, back, ears, and the backs of the legs. A trained eye comparing one visit to the next catches those changes earlier, and earlier detection generally means simpler treatment and less tissue removed.
Certain factors make a screening plan more urgent. A personal history of skin cancer, a family history of melanoma, fair skin that burns easily, a large number of moles, years of outdoor work or tanning bed use, and a history of blistering sunburns all belong in the conversation with your dermatologist. So does any spot that bleeds, crusts, itches, or refuses to heal.
What Happens During a Skin Cancer Screening
A screening appointment is straightforward and usually quick. Your dermatologist reviews your medical history, including previous biopsies, sun exposure patterns, and any medications that affect sun sensitivity, then performs a visual examination of your skin from scalp to feet. Suspicious lesions get closer inspection, sometimes with a magnifying instrument, and a photo record may be kept so future visits have a comparison point.
Good screenings are also educational. Expect to leave with a clearer sense of your personal risk level, a recommended interval before your next visit, and practical guidance on sun protection that fits your routine rather than a generic handout. Free screening events do exist in the Denver area from time to time, and some clinics advertise them for new patients, but a screening event is no substitute for an established relationship with a dermatologist who knows your history.
Diagnosis: From Suspicious Spot to Confirmed Answer
Skin Cancer Types Evaluated in Denver
Denver practices evaluate and treat the three main categories of skin cancer. Basal cell carcinoma is the most frequently discussed and is closely tied to cumulative sun exposure. Squamous cell carcinoma also arises from sun-damaged skin and can behave more aggressively if ignored. Melanoma is less common but more serious, which is why mole changes deserve prompt attention. Some Denver clinics also support patients dealing with rarer diagnoses, including uveal melanoma, through specialized oncology and research programs.
What a Biopsy Involves and Why It Matters
No responsible clinician removes a lesion for cancer without confirming what it is first. A biopsy takes a small sample of tissue that a pathology lab examines under a microscope, and the resulting report identifies the type of lesion, confirms whether it is cancer, and gives the surgeon the information needed to plan removal. Ask how and when you will receive the pathology results, and request a copy for your own records. Those reports follow you through future visits and make second opinions far easier to obtain.
Removal Options, Including Mohs Surgery
Mohs micrographic surgery is widely described as an advanced treatment procedure for skin cancer and the gold standard for several types, including basal cell carcinoma and squamous cell carcinoma. The technique removes cancer layer by layer while the surgeon examines the tissue margins, which allows precise clearance of the tumor while preserving as much healthy skin as possible. For cancers on the face, ears, and other cosmetically sensitive areas, that precision matters a great deal.
Denver has an established community of Mohs-trained surgeons. Karen J. Sundby, M.D., for example, is described as a board-certified Mohs surgeon practicing in the city, and Colorado Skin Surgery and Dermatology positions itself as a leader in Mohs skin cancer surgery. Colorado Dermatology Center also offers Mohs surgery as part of its medical and surgical dermatology services. Not every skin cancer requires Mohs, however. Tumor type, size, location, and whether the cancer has recurred all factor into which removal approach your surgeon recommends.
| Stage of care | What typically happens | Questions worth asking |
|---|---|---|
| Screening | Full-body visual exam plus review of history, sun exposure, and prior biopsies | How often should I be checked with my risk profile? |
| Diagnosis | Biopsy of the suspicious lesion, followed by pathology analysis | When will results arrive, and can I get a written copy? |
| Removal | Mohs micrographic surgery or another surgical approach chosen for the tumor | Is Mohs appropriate for this type and location? |
| Follow-up | Periodic rechecks and a sun protection plan matched to your skin | Which changes should prompt an immediate call? |
Choosing a Skin Cancer Provider in Denver
The Denver metro area has no shortage of dermatology options, and the differences between them matter. Start with board certification. A dermatologist certified by the American Board of Dermatology has completed residency training and passed rigorous examinations, and clinicians such as Dr. Paola Aldana in Cherry Creek build their practices around prevention, detection, and treatment of skin cancer specifically.
Next, look at surgical depth. If Mohs is a possibility for your diagnosis, confirm that the surgeon who will actually perform your procedure has dedicated Mohs training and performs the technique regularly. Practices ranging from AboutSkin Dermatology, which reports caring for hundreds of skin cancer patients a year across its Denver Tech Center and Lone Tree locations, to single-surgeon Mohs centers each have different strengths. Match the practice to your diagnosis rather than to a billboard.
Also consider the full arc of care. A practice that handles screening, biopsy, surgery, and long-term follow-up in one place saves you from repeating your history at every step, and it keeps your records together. Colorado Dermatology Center, for instance, combines medical, surgical, and cosmetic dermatology with clinical research trials, which means patients sometimes have access to options that a purely cosmetic practice cannot offer.
Bring a short list of questions to your consultation. Ask who performs the procedure, where it is done, what anesthesia is used, how long you should plan to be there, what scarring is expected, and how follow-up is scheduled. Ask about pathology. Ask what happens if the margins are not clear. A practice that answers these questions plainly is a practice worth trusting.
Sun Protection After Treatment
Treatment closes one chapter, but the skin around the treated area and everywhere else remains vulnerable. Denver’s sunny climate means daily sunscreen, protective clothing, hats, and shade during peak hours are ongoing habits rather than seasonal ones. Monthly self-checks at home help you notice new changes between professional visits, and photographs of moles make those comparisons more reliable.
Any new spot that grows, bleeds, crusts, or changes color deserves a call rather than a wait-and-see approach. The same is true of a treated site that does not heal as expected. Colorado Dermatology Center and other Denver practices schedule follow-up visits based on your individual risk, and keeping those appointments is one of the simplest things you can do for your long-term health.
Frequently Asked Questions
How often should I get a skin cancer screening in Denver?
There is no single schedule that fits everyone. Your dermatologist will weigh your personal and family history of skin cancer, skin type, number of moles, sun exposure, and previous biopsies when recommending an interval. People at higher risk are often checked more frequently than the general population. Ask at your first visit and revisit the plan whenever your history changes.
Is Mohs surgery the right choice for every skin cancer?
No. Mohs micrographic surgery is described as the gold standard for several types of skin cancer, including basal cell carcinoma and squamous cell carcinoma, and it is especially valuable on the face and other sensitive areas. Even so, tumor type, size, location, and whether the cancer has returned all influence the recommendation. Your surgeon should explain why a particular approach fits your case.
Will insurance cover skin cancer treatment in Denver?
Coverage depends on your specific plan, the medical necessity documentation, and whether the provider is in network. Colorado practices vary in which insurers they contract with, so confirm benefits directly with your insurer and with the billing office before scheduling. Ask specifically about pathology fees and surgical fees, since those are sometimes billed separately by different entities.
How do I verify that a Denver dermatologist is qualified?
Ask whether the physician is board certified in dermatology, and if Mohs surgery is recommended, ask about dedicated Mohs training and how often the surgeon performs the procedure. Practice websites, professional society directories, and a direct question at the front desk all provide useful confirmation. It is entirely reasonable to request this information before booking a surgical consultation.
Dermatology in Denver: Medical, Surgical, and Cosmetic Care
Skin problems do not sort themselves neatly into categories. A stubborn rash, a changing mole, a scar left behind by teenage acne, and thinning hair can all lead someone to search for a dermatologist in Denver who can sort out what is happening and what to do about it. Dermatology covers a wide range, and many clinics handle all three of its main areas under one roof. Medical visits treat disease and inflammation. Surgical visits remove skin cancers and other growths. Cosmetic visits address appearance, texture, and hair. Knowing which type of appointment matches your concern makes it easier to pick a practice and prepares you for the conversation at the visit.
The Three Branches of Dermatology
Board-certified dermatologists are trained in medical, surgical, and cosmetic care, and most practices in the Denver metro area advertise some mix of all three. The overlap matters because the same skin can have more than one problem at once. Someone booking a cosmetic consultation for sun damage may leave with a recommendation to have a suspicious spot biopsied first. Someone seeing a dermatologist for eczema may also ask about fillers or laser resurfacing during the same visit. A practice that treats the full range can move between those concerns without sending you somewhere else.
The categories are still useful for setting expectations. Each one uses different tools, follows a different schedule, and is usually billed in a different way.
Medical Dermatology: Treating Skin Disease
Medical dermatology is the diagnosis and treatment of conditions affecting the skin, hair, and nails. It is the most common reason people book a dermatology appointment, and much of the work is chronic rather than one-time. Practices across Colorado routinely treat acne, rosacea, eczema, and psoriasis, along with skin cancer screening and detection. Those four conditions alone account for a large share of daily visits.
Treatment for chronic skin disease usually follows a stepwise pattern. A first visit typically involves a history, a visual exam, and sometimes a biopsy or patch test. From there, a plan might start with topical therapy, move to oral medication, and add light-based treatment if the condition does not respond. Follow-up visits track progress and adjust the plan. Because these conditions tend to flare and settle rather than disappear, the relationship with a dermatologist often lasts years rather than weeks.
Medical dermatology also handles the less visible work: hair loss evaluation, nail disorders, skin infections, pigment problems, and reactions to medications. Many of these require a careful look at the whole picture, including medications, family history, and other health conditions.
Surgical Dermatology and Skin Cancer Care
Denver sits in a state with plenty of sunshine and outdoor activity, and skin cancer detection and treatment form a major part of dermatology practice in the region. Surgical dermatology covers biopsies, removal of benign growths and cysts, and excision of skin cancers, including basal cell carcinoma, squamous cell carcinoma, and melanoma.
What MOHS Surgery Involves
MOHS micrographic surgery is a specialized technique for removing certain skin cancers, particularly on the face and other areas where preserving healthy tissue matters. The surgeon removes a thin layer of tissue, examines it under a microscope during the same visit, and maps exactly where cancer cells remain. If any are present, another layer is taken from that specific spot only. The process repeats until the margins are clear. Because the surgeon checks each layer before removing more, MOHS can spare tissue that a standard excision might take, and it is often completed in a single day.
Not every skin cancer needs MOHS. Smaller, low-risk lesions are frequently handled with simpler excision or other techniques. The choice depends on the tumor type, its size and location, and whether it has come back after earlier treatment. A dermatologist can explain which approach fits a specific diagnosis.
Cosmetic Dermatology: Appearance, Texture, and Confidence
Cosmetic dermatology addresses how skin looks rather than how it functions, though the two are often linked. Denver-area practices offer a broad menu that commonly includes injectables such as Botox and dermal fillers, laser and light treatments, chemical peels, and body contouring. Facial rejuvenation is one of the most requested categories, and much of it focuses on sun damage, uneven tone, fine lines, and lost volume.
The results people tend to value most are the ones that look natural. That usually means a conservative starting point, a plan built over several visits, and honest expectations about what a treatment can and cannot change. Set against that, cosmetic care is elective. It is reasonable to ask about downtime, how many sessions a result requires, and what happens if you stop.
Acne Scar Revision and Hair Restoration
Two areas sit between medical and cosmetic care and are worth calling out separately. Acne scar revision treats the textural changes left after acne has cleared, using techniques aimed at the depressed or uneven scars themselves rather than active breakouts. Hair restoration addresses thinning and hair loss, and can involve medical therapy, surgical approaches, or a combination. Both are areas where some practices specialize and others do not, so it helps to ask directly about experience and the specific techniques a clinic offers.
Body contouring is another procedure type that varies widely by practice. Tumescent liposuction, for example, is not offered at every dermatology clinic, so patients seeking it should confirm availability and credentials before booking a consultation.
Comparing the Three Types of Care
| Type of care | Typical focus | Usual reason for the visit |
|---|---|---|
| Medical dermatology | Diagnosing and treating skin, hair, and nail conditions | Acne, rosacea, eczema, psoriasis, rashes, hair loss |
| Surgical dermatology | Removing tissue, from biopsies to skin cancer surgery | Suspicious spots, skin cancer, cysts, benign growths |
| Cosmetic dermatology | Improving appearance, texture, tone, and volume | Sun damage, scarring, fine lines, body contouring |
The lines blur in practice. A skin cancer surgeon may also perform cosmetic reconstruction. A cosmetic visit may uncover a lesion that needs medical attention. That flexibility is one reason to look at a practice’s full scope rather than a single service page.
Clinical Research and Access to Newer Options
Some dermatology practices in Denver take part in clinical research trials, which study new treatments for skin conditions before they become widely available. For patients, participation can mean access to an investigational therapy, often at no cost, along with closer monitoring than a standard visit provides. Trials have eligibility rules, and participation is voluntary. Anyone considering one should ask what phase the study is in, what the visits involve, and how side effects are tracked.
Choosing a Dermatologist in Denver
The Denver metro area has a large supply of dermatology practices, spread from the central city out through Lakewood, Englewood, Lone Tree, Aurora, and the northern suburbs. That gives patients real choice, and a few practical filters narrow it quickly.
- Confirm board certification and check whether the dermatologist’s focus matches your concern. Skin cancer surgery, hair restoration, and acne scar revision are not identical skill sets.
- Ask whether the practice handles your specific procedure in house or refers it out.
- Check insurance participation before booking. Coverage rules vary by practice, and some clinics operate outside insurance networks entirely.
- Look at wait times. A practice that books months out may not suit an urgent spot that needs a prompt look.
- Local directories, including the doctor listings published by 5280 Magazine, can help you build a shortlist of names to research further.
Colorado Dermatology Center, the South Denver practice led by board-certified dermatologist Dr. James M. Swinehart, is one example of a clinic that combines medical, surgical, and cosmetic care with more than three decades of clinical experience and an active research program. Patients can reach the office at (303) 744-1202 to discuss scheduling. Verify current hours, insurance participation, and service availability directly with any office before making plans, since those details change.
Getting Ready for a Dermatology Visit
A little preparation makes an appointment more productive. Bring a list of medications and supplements, note when a symptom started and what makes it better or worse, and bring any products you use on your skin. Photographs of a rash that comes and goes can be more useful than a description. If you are concerned about a specific spot, avoid covering it with makeup on the day of the visit, and mention any personal or family history of skin cancer.
For cosmetic appointments, arrive without heavy makeup if a treatment is planned, and be ready to talk about budget, downtime, and what you hope to change. A good consultation includes as much listening as advising, and it should include a plain answer about what the treatment will not do.
Frequently Asked Questions
What is the difference between medical and cosmetic dermatology?
Medical dermatology treats disease and symptoms such as acne, eczema, psoriasis, and skin cancer. Cosmetic dermatology focuses on appearance, texture, tone, and volume. Both use overlapping tools and expertise, and many board-certified dermatologists practice both. Insurance generally covers medical care when it is medically necessary, while cosmetic treatments are usually paid out of pocket. Ask the office how a specific service will be billed.
Do I need a referral to see a dermatologist in Denver?
Requirements depend on your insurance plan and the individual practice. Some plans allow direct scheduling with a specialist, while others require a primary care referral before the visit is covered. Call both your insurer and the dermatology office before booking to confirm. Front desk staff can usually tell you quickly what documentation they need and whether your plan is accepted.
How do I know if a mole should be checked?
Any mole that is new, changing in size, shape, or color, itching, or bleeding deserves a professional look. So does a sore that will not heal. Most spots turn out to be harmless, but early evaluation of skin cancer makes treatment simpler. Photographing a spot periodically can help you notice gradual change between visits.
What is MOHS surgery used for?
MOHS micrographic surgery removes certain skin cancers one thin layer at a time, with each layer checked under a microscope during the visit. It is often chosen for cancers on the face or other areas where conserving healthy tissue matters, and for tumors that have returned after earlier treatment. Your dermatologist can explain whether MOHS or another approach fits your diagnosis.
Does insurance cover cosmetic dermatology?
Cosmetic procedures are typically not covered because they are elective rather than medically necessary. That includes most injectables, laser resurfacing for appearance, and body contouring. Medical visits for a diagnosed condition are handled differently. Because plans and practices vary, confirm coverage and payment options with the office and your insurer before scheduling a cosmetic consultation.
Dermatology in Denver spans a wide range of care, and the right starting point depends on what your skin is doing right now. A medical concern, a spot that needs checking, and a cosmetic goal can each lead to different conversations, and sometimes to the same clinic. What matters most is choosing a board-certified dermatologist whose focus matches your concern, confirming insurance and scheduling details in advance, and asking direct questions about what a treatment can realistically achieve.

Does Insurance Cover a Dermatologist Visit? What Colorado Patients Should Know
Plenty of people put off a dermatology appointment because they are not sure their health insurance will pay for it. That hesitation is understandable, because coverage for dermatology services can be confusing, and the answer changes depending on why you are going and who you are seeing. The good news is that the basic rule is simpler than it looks, and a few minutes of checking ahead of time can spare you a surprise bill later.
The Short Answer on Dermatology Coverage
Health insurance typically covers a dermatologist visit for medically necessary reasons, such as diagnosing or treating a skin condition. Dermatologists are medical doctors who specialize in diagnosing and treating diseases and conditions of the skin, hair, or nails. Because that work is medical in nature, most plans treat a dermatology appointment much like a visit to any other specialist.
The key phrase is medically necessary. A visit that exists to evaluate a symptom, a change, or a diagnosed condition is the kind of care plans are built to cover. A visit that exists only to change how something looks usually falls outside that definition. Understanding which category your concern falls into is the first step toward knowing what you will owe.
What Counts as a Medically Necessary Visit
Medical dermatology covers conditions such as acne, psoriasis, and other diseases and conditions of the skin, hair, or nails. It also covers the process of figuring out what is going on when something changes or does not look right. Many skin concerns and changes are not simply aesthetic matters, and they may merit medical attention, which is exactly why they belong in a medical visit rather than a cosmetic one.
If you have been watching a spot, a patch, or a persistent breakout and wondering whether it is worth a copay, that question is usually a sign that a medical evaluation is reasonable. A board-certified dermatologist can tell you whether what you are seeing needs treatment, monitoring, or nothing at all.
Medical Versus Cosmetic: The Line That Decides Coverage
Most dermatology clinics offer elective cosmetic services that address issues related solely to the appearance of your skin. Those services sit on the other side of the coverage line. They are optional by design, they are not treating a disease, and plans generally do not pay for them.
| Type of visit | How plans generally treat it | What to confirm |
|---|---|---|
| Evaluation of a medical condition such as acne or psoriasis | Typically covered when the visit is medically necessary | Network status and your cost share |
| Diagnosis and treatment of skin cancer | Typically treated as medical care | That the provider and any facility are in your network |
| Cosmetic treatments that only change appearance | Typically not covered | Self-pay pricing before you schedule |
Some appointments include both. You might come in for a medical concern and ask about a cosmetic treatment in the same visit. When that happens, the two parts are usually handled differently on the billing side, with the medical portion processed through insurance and the cosmetic portion handled as a self-pay service. Asking how a combined visit will be billed is a fair question, and a well-run office will explain it before you are seen.
How to Check Whether Your Dermatologist Is in Your Network
Coverage is not only about the reason for the visit. To determine whether your evaluation will be covered by your carrier, you have to first find out if your dermatologist is in your carrier’s network. A medically necessary visit with an out-of-network provider can still leave you with a much larger bill than the same visit with an in-network provider.
Network status can also vary by plan type. Two people with coverage from the same insurance company may have different networks, different deductibles, and different rules about referrals. That is why the plan documents you received, or your member portal, matter more than what a friend or coworker experienced with their own policy.
Steps to Verify Coverage Before You Book
- Confirm that the dermatologist is in your carrier’s network for your specific plan, not just that the practice name appears somewhere on a list.
- Ask how the office will bill the visit, and describe your reason for coming in so the answer reflects your actual situation.
- Ask whether your plan requires a referral from a primary care provider before you can see a specialist.
- Ask whether the service requires prior authorization under your plan, and if so, who submits it.
- Ask what your financial responsibility will be, including any deductible, copay, or coinsurance that applies.
- If you are on Medicare or Medicaid, ask directly whether the practice accepts your specific plan before scheduling.
- Call your insurance carrier as well, since the plan has the final say on what is covered and what you owe.
Writing down the name of the person you spoke with, along with the date of the call, is a small habit that can help if a question comes up after your appointment. It also gives you something concrete to reference if a claim is processed in a way you did not expect.
Medicare, Medicare Advantage, and Medicaid
Government coverage adds another layer. Dermatology practices vary in which plans they participate with. Some practices accept Medicare Part B and select Medicare Advantage plans while not accepting Medicaid at all. Others may participate in a different mix of plans. Because this varies from office to office, the only reliable answer comes from the practice itself and from your plan.
If you are enrolled in Medicare or Medicaid, make the call before you schedule rather than after. Ask which plans the office is contracted with, and confirm that your specific plan is one of them. If the practice does not accept your coverage, ask what self-pay would involve so you can compare options with a clear picture in front of you.
What Cost Sharing Still Looks Like With Coverage
Covered does not mean free. Even when a dermatology visit is a covered benefit, most plans apply some form of cost sharing. Depending on your policy, that could be a copay at the time of service, coinsurance calculated as a percentage of the allowed amount, or a bill that goes toward a deductible you have not yet met.
This is why two patients with the same diagnosis can owe very different amounts. Specialty visits sometimes carry a higher copay than a primary care visit, and services performed during the visit, such as a biopsy or a procedure, may be billed separately from the office visit itself. If you want a realistic estimate, ask the office for the codes associated with your visit and share those with your carrier.
Questions Worth Asking About Skin Cancer and MOHS Care
Skin cancer care tends to involve more than one step, and each step can have its own coverage details. A consultation, a biopsy, a pathology review, and a surgical appointment may all be billed separately. That does not mean any of them are uncovered, but it does mean the total is rarely a single line item.
If you have been told you may need MOHS micrographic surgery or another surgical treatment, ask whether the surgeon and any facility involved are in your network, and whether the procedure requires prior authorization. Getting those answers before the day of surgery is far easier than sorting them out afterward, and it lets you focus on the part that actually matters, which is treatment.
Working With a Denver Dermatology Practice on Coverage
Colorado Dermatology Center is a South Denver practice led by board-certified dermatologist Dr. James M. Swinehart, with more than three decades of clinical experience. The practice covers medical, surgical, and cosmetic dermatology, including skin cancer treatment and MOHS surgery, hair restoration, and clinical research. That mix of services is exactly why a coverage conversation at the start is useful, since medical and cosmetic care are handled differently by every plan.
When you call to schedule, say what is bringing you in. A clear description of your concern helps the front office tell you whether the visit is likely to be treated as medical or cosmetic, what information your plan will need, and what to expect on the billing side. You can reach the practice through coloderm.com to start that conversation.
Frequently Asked Questions
Does insurance cover a dermatologist visit?
Health insurance typically covers a dermatologist visit when the reason for the visit is medically necessary, such as diagnosing or treating a disease or condition of the skin, hair, or nails. Cosmetic services that address appearance alone are usually not covered. Confirm your network status and cost share with both the practice and your carrier before your appointment.
Is acne treatment considered medical or cosmetic?
Acne is a condition of the skin, and dermatologists treat it as part of medical dermatology. That means an evaluation and treatment plan for acne is generally handled as medical care rather than cosmetic care. Coverage still depends on your specific plan, so ask your carrier how acne visits and any prescribed treatments are handled under your policy.
Will my plan pay for a cosmetic dermatology service?
Elective cosmetic services that address issues solely related to the appearance of your skin are typically not covered by health insurance. That is because they are optional and are not treating a disease. If you are considering a cosmetic treatment, ask the practice for self-pay pricing so you know the full cost before you schedule.
Do I need a referral to see a dermatologist?
Some plans require a referral from a primary care provider before you see a specialist, and others do not. The requirement depends on your plan type, not on the dermatology practice. Check your plan documents or call the member services number on your insurance card to find out before you book.
Does Medicare cover dermatology visits?
Some dermatology practices accept Medicare Part B and select Medicare Advantage plans, while others do not accept Medicaid. Participation varies from office to office, so there is no single answer that applies everywhere. Call the practice and your plan directly to confirm that your specific coverage is accepted before scheduling your visit.
Dermatology Clinical Trials in Denver: What Joining Is Like
Skin problems show up in the mirror, at work, and at two in the morning when itching keeps you awake. That visibility is part of why so many people in Colorado start searching for dermatology clinical trials in Denver after a cream or a steroid has stopped being enough. Joining a study is not the same as booking a regular appointment, and knowing what the process actually looks like makes the decision much easier.
What a Dermatology Clinical Trial Actually Is
A clinical trial is a research study. In dermatology, that can mean testing a medication, a vaccine, a medical device, or a procedure, which is how one Denver research site describes the work it conducts. Trials follow a written plan called a protocol that sets out who can join, what each visit involves, and what researchers measure along the way. Some studies compare a new option against an existing treatment or a placebo, while others follow participants over time to learn more about how a condition behaves.
Why Skin Research Looks Different Than It Did a Decade Ago
For decades, many skin diseases were treated mainly with creams and steroids. That has shifted. In the past ten years, targeted injections and pills have come into use for atopic dermatitis, psoriasis, and alopecia, according to a dermatology trial listing service. The pipeline now reaches into conditions people were once told they simply had to live with. Itching, flaking, hair loss, and recurring rashes affect sleep, work, and confidence as much as comfort, which is part of why researchers and participants both take this work seriously.
Who Runs Dermatology Studies in the Denver Area
Denver has more research infrastructure than most patients expect. Velocity Clinical Research conducts clinical trials in Denver, Colorado, reachable at (303) 293-3733, and describes its studies as covering medications, vaccines, medical devices, and procedures. Center For Dermatology Clinical Research, Inc. presents itself as an institution dedicated to exploring new therapies for various skin conditions and invites people to contact the center to join a study.
In the Denver Tech Center area, dermatology practices list active clinical trials right alongside medical and cosmetic care. That is also how Colorado Dermatology Center approaches research: studies sit next to skin cancer treatment, hair restoration, and acne scar revision rather than in a separate building. Academic dermatology adds another layer. The Department of Dermatology offers a Mentored Medical Student Research Award for up to three Colorado University medical students each year, which is a training program rather than patient enrollment.
| Research option | Focus | How to start |
|---|---|---|
| Velocity Clinical Research Denver | Studies of medications, vaccines, medical devices, and procedures | Call (303) 293-3733 |
| Center For Dermatology Clinical Research, Inc. | New therapies for various skin conditions | Contact the center to ask about joining a study |
| Colorado Dermatology Center | Medical, surgical, and cosmetic dermatology with active clinical trials | Ask the practice about studies currently enrolling |
| CU Department of Dermatology | Mentored Medical Student Research Award for up to three students annually | Student research program, not patient enrollment |
Phone numbers, addresses, and open studies change often, so confirm current details directly with the site before you make plans.
Which Conditions Are Being Studied
Dermatology trial directories group studies around eczema, psoriasis, acne, hair loss, vitiligo, and other skin conditions, and one listing service counts 73 dermatological conditions with trials enrolling across the United States and Canada. Narrow that to Colorado and atopic dermatitis alone has had roughly eight active trials seeking participants at a time, according to one trial tracker. Those figures move constantly as studies open and close, so treat any count as a snapshot rather than a fixed menu of what is available near you.
What Joining Actually Involves
Most studies begin with screening rather than treatment. You talk with the study team about your history, your medications, and what you have already tried. You review and sign an informed consent document that explains the risks and what is expected of you. Depending on the study, screening may include blood work, skin assessments, or photographs. If you qualify, you are usually assigned to a treatment group, sometimes by random selection, and in some studies that means a placebo.
Follow up visits happen on the schedule the protocol sets. Many studies also use diaries, questionnaires, or phone check ins between visits. Because every protocol is different, the details you receive from the study team should always take priority over any general description of how trials work.
How Much Time It Really Takes
Time commitment is the part people underestimate. A study might ask for a handful of visits over a few weeks, or it might run for years with regular check ins. Ask how many visits there are, how long each one lasts, how wide the scheduling windows are, and whether any visits can be handled remotely. Ask as well whether the study offers compensation for time and travel or reimburses parking, because that varies. Some research listings are described openly as paid studies and others are not, so the only reliable answer comes from the study team itself.
Questions Worth Asking Before You Enroll
- What is being studied, and what stage is the research at?
- Will I know whether I am receiving the active treatment or a placebo?
- How many visits are required, and how long does the whole study last?
- What tests or procedures happen at each visit?
- Are study visits and the study treatment provided at no cost?
- Is there compensation for time, travel, or parking?
- Can I keep seeing my own dermatologist during the study?
- What happens if my skin gets worse or I decide to stop?
You can leave a study at any time, and participation is voluntary from the first screening appointment to the last follow up. No one can require you to continue.
How a Trial Fits With Your Regular Dermatology Care
Joining a study usually does not replace the care you already receive. Tell your dermatologist that you are considering a trial, and ask the study team whether the protocol requires you to pause any current treatments before you start. Many studies have rules about what you can apply to your skin during the research period, including prescriptions, over the counter products, and sometimes cosmetics. Keeping both care teams informed prevents surprises and keeps your records consistent.
What a Trial Is Not
A trial is not a shortcut to a guaranteed result, and it is not the same as a routine appointment. If you are assigned to a placebo group, you may not receive the investigational treatment at all. You also may not qualify, since eligibility rules around age, diagnosis, prior treatments, and other health conditions are strict on purpose. The honest version of what to expect is careful monitoring, a structured schedule, and access to options that may not be available outside a study.
Why People in Denver Say Yes
People join for a mix of reasons. Some have tried everything their dermatologist can prescribe and want another path. Some appreciate the close monitoring that comes with a research schedule. Others want to contribute to knowledge that could help people with the same condition later. Whatever the motivation, the same advice applies: read the consent document carefully, ask your questions out loud, and make sure the time commitment fits your life before you sign anything.
Frequently Asked Questions
How do I find dermatology clinical trials in Denver?
Start with the research centers that run studies locally, then check condition specific listings. Velocity Clinical Research conducts trials in Denver and can be reached at (303) 293-3733, and Center For Dermatology Clinical Research, Inc. invites people to contact them about joining a study. Colorado Dermatology Center runs trials alongside its medical and surgical dermatology work. Directories that track dermatology studies by condition and state help too, but confirm details with the study team.
Do dermatology clinical trials pay participants?
Some do and some do not. Research listings often describe studies as paid, and many trials offer compensation for time and travel, but the amount and structure vary by study and are set by the sponsor. Ask the study coordinator directly what compensation is offered, whether it covers travel and parking, and when payments are made. Also ask whether study visits and the treatment are provided at no cost.
Do I need a referral to join a study?
Usually not. Most research sites accept direct inquiries from people who contact them about a study, and eligibility is decided by the protocol criteria rather than by a referral. Your own dermatologist may be able to point you toward studies, and some health systems have their own processes. The simplest path is to call the site running the trial and ask what they need to begin screening.
What happens if I want to stop participating?
You can stop at any time, and you do not need to give a reason. Participation in research is voluntary, and leaving a study does not affect your ability to receive care elsewhere. Study teams usually ask for a final visit so they can close out your records safely, and they may ask whether you are willing to be contacted about future research. Ask about the exit process early.
Is a clinical trial the same as regular dermatology treatment?
No. A trial is a research study with a written protocol, scheduled assessments, and eligibility rules, while routine treatment is chosen by you and your dermatologist. You may receive a placebo rather than an active treatment, and the study may require you to pause other treatments. Many people continue seeing their regular dermatologist during a trial, and keeping both teams informed keeps your plan consistent.
Botox for Forehead Lines and Crow’s Feet | Denver
Forehead lines and crow’s feet are two of the most common reasons people schedule a cosmetic dermatology appointment. Injections of botulinum toxin, most often known by the brand name Botox, remain a first-line option for softening those creases without surgery. Knowing what the treatment can realistically change, and what it cannot, makes it easier to decide whether it fits your goals this year.
How Botox Softens Forehead Lines
Botox injections soften horizontal forehead lines by temporarily relaxing the frontalis muscle, the muscle responsible for lifting the eyebrows and creating the creases that appear when you raise your brows. Once that muscle relaxes, the repeated folding that deepens the lines is reduced, and the skin across the forehead looks smoother while the brow stays in a natural position rather than dropping.
Why Horizontal Lines Form
Horizontal creases form when you raise your brows. Botox relaxes the frontalis muscle so the lines soften without dropping the brows. That distinction matters in Denver, where bright sun and dry air keep many people squinting and raising their brows all year. Every surprised expression, every squint, every lifted eyebrow folds the same skin in the same place. Over years, those folds can become visible even when your face is at rest.
What Results Actually Look Like
The American Academy of Ophthalmology notes that wrinkles in the forehead are significantly reduced after treatment, both on the forehead and between the eyebrows. The same source is direct about the ceiling on results: botulinum toxin does not erase wrinkles. Softening is the goal, not erasure. Patients who expect a completely smooth, motionless forehead are often disappointed, while patients who expect their lines to look less etched usually are not.
What Botox Does for Crow’s Feet
Crow’s feet are the lines that fan out from the outer corners of the eyes. They are frequently treated in the same appointment as forehead lines, and the two areas share a treatment schedule. The average duration for Botox for the glabella, the forehead, and lateral crow’s feet is approximately three to four months. Treating both zones together keeps the upper face balanced, since relaxing only the forehead while leaving the eye area untouched can change how your expressions read.
What Botox Does and Does Not Address
| Concern | What treatment typically does |
|---|---|
| Horizontal forehead lines | Relaxes the frontalis muscle so creases soften when you raise your brows |
| Lines between the brows (glabella) | Treated on the same roughly three to four month cycle as the forehead |
| Lateral crow’s feet | Softened when treated alongside the forehead and glabella |
| Deep, etched-in lines | Softened, not erased; botulinum toxin does not remove wrinkles entirely |
Reading that table honestly is the most useful preparation you can do. The treatment works on muscle movement, so it performs best on lines that appear when you make an expression. Lines that stay visible when your face is still have a structural component, and no injection protocol changes that.
How Long Results Last
The average duration for Botox in the glabella, forehead, and lateral crow’s feet is approximately three to four months. That is an average, not a promise, and individual results vary. Temporary effects sit on both sides of the ledger. A treatment that wears off is one whose results can be adjusted at the next visit, and it is also one you have to schedule and pay for several times a year. Planning for that rhythm in advance makes the experience easier to manage.
Pros of Treating Forehead Lines with Botox
- Reduction of forehead wrinkles, visible as softened creases across the forehead
- Non-surgical and minimally invasive, with no downtime tied to a surgical recovery
- Customizable results, since dosing can be adjusted to your muscle strength and goals
- Temporary effects, which allow a conservative first treatment and later refinement
Customization is the part patients tend to underestimate. The frontalis is a large, strong muscle, and the amount needed to soften lines without affecting how your brows sit varies from person to person. A conservative starting point gives you room to add at a follow-up rather than waiting months for an over-treated result to fade.
Possible Downsides and Realistic Expectations
Patients with deep, etched-in lines often ask whether Botox will remove them. The honest answer is qualified. Botox will get rid of them, but only if you freeze your forehead entirely, and it will not completely fix deep lines. It will help a lot. Lines that remain visible at rest have a component that muscle relaxation alone cannot address, and that is a limitation of the treatment rather than a failure of the injector.
When Results Are Not What You Expected
A 2011 case report described four cases of exaggeration of wrinkles after botulinum toxin injection for forehead horizontal lines. Four reported cases does not mean this is a common outcome, and it does not mean the treatment is unsafe for most patients. It does mean the frontalis is a muscle where technique matters, and any change that looks wrong to you is worth reporting to your injector rather than quietly waiting it out.
Choosing a Provider in Denver
Colorado Dermatology Center is a South Denver practice led by board-certified dermatologist Dr. James M. Swinehart, whose clinical experience spans more than three decades. Cosmetic injectables sit alongside medical and surgical dermatology there, which matters if you also have a skin cancer history, acne scarring, or hair loss concerns that should be part of the same conversation. A dermatologist who treats the whole face, and not only the cosmetic concern, can flag things a stand-alone injectable clinic may miss.
Questions Worth Asking Before Your First Treatment
- Who will perform the injection, and what is that person’s training?
- How many units are planned for the forehead and the crow’s feet?
- What result is realistic for lines I see at rest versus lines I see only when I move?
- What is the plan if I am not happy with how the result looks?
- What is the total cost, and can I get it in writing before treatment?
What to Confirm Before You Book
Pricing, injection protocols, and aftercare instructions are not standardized across practices, so confirm them directly with the office rather than relying on general information you find online. That applies equally to guidance about the hours right after an appointment. Ask the practice for its own written instructions and follow those, since what one office recommends may differ from what another does.
Frequently Asked Questions
Is 40 too late for Botox?
Age is not the deciding factor. What matters is whether your lines are caused mainly by muscle movement or by changes in the skin itself. Botox relaxes the frontalis muscle and softens movement-related creases at any adult age. Lines that are visible at rest may soften but will not disappear. A dermatologist can assess your forehead and tell you what to expect.
How much does forehead Botox usually cost?
Pricing is not standardized, and this article does not establish a reliable range, so treat any figure you see online with caution. Cost depends on how many units are used, which areas are treated, and the practice’s own fees. Ask the Denver office directly for a written estimate before you schedule, and confirm whether a consultation fee applies.
Which area is riskiest to treat with Botox?
Any area where the muscle drives an important expression carries more risk of an unwanted result. The frontalis is one example, because relaxing it too much or unevenly can change how the brows sit. Published case reports have described exaggerated wrinkles after forehead treatment. Experienced injectors plan around this. Raise your concerns during the consultation rather than after.
What is the 4-hour rule for Botox?
Many practices give patients instructions about the first few hours after an injection, and the so-called four-hour rule is one version of that guidance. This article does not establish a standard rule, and protocols differ from office to office. Follow the specific written instructions your own provider gives you, and ask questions if anything is unclear.
Will Botox completely remove deep forehead lines?
Usually not. Botulinum toxin does not erase wrinkles; it softens them by relaxing the muscle that folds the skin. Deep lines that remain visible when your face is at rest often have a structural component that muscle relaxation alone cannot resolve. Many patients still see meaningful improvement. A dermatologist can tell you how much softening is realistic in your case.
Subcision for Acne Scars: Procedures Many Denver Clinics Don’t Offer
A depressed acne scar is not only a surface problem. Underneath it, fibrous bands can tether the scar tissue to deeper facial structures, which is why a pitted mark can still look deep long after the breakout itself has healed. Subcision is one of the few in-office procedures built to address that deeper problem directly, and it is not available everywhere.
What Subcision Does That Topical Products Cannot
Subcision is a minimally invasive procedure that improves the appearance of depressed acne scars, sometimes described as valley scars, by breaking the fibrous bands that hold the scar down. Once those bands release, the scar is free to elevate toward the level of the surrounding skin, which can make the surface look smoother.
The technique is often described as a kind of keyhole surgery for deep acne scars, because it works through a very small entry point to release scar tissue that is attached to deeper facial structures. It is performed in an office setting using a small needle or a blunt cannula, and it is regarded as a safe and effective treatment when it is matched to the right kind of scar.
The goal is not erasure. The goal is to change how the scar sits in the skin so it catches light more evenly and reads as less prominent from a normal conversation distance.
Which Acne Scars Are Good Candidates for Subcision
Subcision targets depressed scars, the ones that sit below the level of the surrounding skin. If a scar is pitted, tethered, or shaped like a shallow valley, it belongs to the category this procedure was designed to treat. Scars that are mainly a difference in color, without a depression, are a separate problem and need a separate plan.
Because the procedure depends on how much fibrous tethering sits beneath the surface, the only dependable way to know whether it will help is an in-person evaluation. A dermatologist can feel the scar, judge its depth, and watch how the surrounding skin moves. Photos taken in consistent lighting can help you describe what bothers you most.
What Happens During an In-Office Subcision Session
Subcision is performed in the office and does not require a hospital stay or general anesthesia. The dermatologist places a fine instrument beneath the scar and works it to free the fibrous attachments holding the skin down. As those attachments release, the scar can rise.
Will you feel it?
Comfort is one of the most common questions about subcision, and there is no single answer that applies to every patient. What you feel depends on the numbing approach used, the depth and location of the scar, and your own sensitivity. Ask the practice directly how they manage discomfort, what numbing they use, and what patients typically report afterward.
Which instrument does the dermatologist use?
Published descriptions of subcision mention both a small needle and a blunt cannula. Which one is used is a technical decision that varies with the dermatologist and with the scar being treated. If you want to understand the plan for your face, ask what instrument is planned and why it was chosen.
Recovery After Subcision: What the First Week Looks Like
Most patients can return to work or normal activities within 1 to 2 days. Minor bruising or tenderness may linger for about a week. That timeline makes planning straightforward: schedule the appointment when a couple of low-key days will not cause a problem, and check your calendar for anything important in the week that follows.
Follow the aftercare instructions your dermatologist provides, because those instructions are written for your specific treatment rather than for the procedure in general. Ask about sun protection, skincare products, and anything you should pause while the skin settles. If something seems to be healing unusually slowly, call the office rather than waiting for a scheduled follow-up.
Where Dermal Grafting Fits Into Acne Scar Treatment
Subcision is a release. Dermal grafting is a different type of intervention that comes up in the same conversation, and the two are frequently discussed together when a dermatologist plans treatment for depressed acne scars. In broad terms, a graft places tissue beneath a scar to give it more support, rather than simply freeing the tether that pulls it down.
The specifics vary widely between practices, including the technique itself, the material involved, and the recovery that follows. Because of that variation, the useful move is to ask for an explanation of what a graft would involve in your case, who would perform it, how many visits it would take, and what downtime to expect. If the practice does not offer grafting, ask whether subcision alone would make sense for your scars or whether you should be referred elsewhere.
Why Not Every Denver Practice Offers Subcision
Not every dermatology office offers subcision, and there is no public directory that reliably lists which Denver practices do. Some offices concentrate on medical dermatology, others on injectables and laser devices, and the procedure menu at any given clinic reflects the training and interests of the clinicians who work there.
Practices that focus on acne scar revision tend to be the ones that keep surgical scar techniques in their toolkit. Colorado Dermatology Center in South Denver is led by board-certified dermatologist Dr. James M. Swinehart and offers procedures that many practices do not, including acne scar revision. More than three decades of clinical experience informs how those treatment plans get built.
Questions to Ask Before You Book
A short list of questions will tell you more about a practice than any marketing page. Bring these to your consultation and listen for specific answers rather than general reassurance.
- Do you perform subcision in the office, and how often do you do it?
- Which scars on my face would you treat with subcision, and which would you leave alone?
- Are you planning subcision by itself or alongside another technique?
- How do you manage comfort during the procedure, and what do patients usually report?
- What should my first week look like, and what symptoms would make you want to hear from me sooner?
- What improvement is realistic for my skin, and how long would it take to show?
Clear answers to those questions are a reasonable expectation. A dermatologist who performs these procedures regularly can explain the reasoning behind a plan in plain language and can tell you honestly when a different approach would serve you better.
Setting Expectations for Improvement, Not Erasure
Acne scarring is a structural change in the skin, and no procedure removes it completely. What subcision can do is change how a depressed scar sits, which can make it less noticeable in everyday lighting. Ask your dermatologist to describe the improvement they expect for your specific scars, and ask whether they would plan one session or more than one visit over time.
Keeping a set of photos taken in consistent lighting helps you judge change objectively over months rather than comparing today’s mirror to a memory. Bring those photos to follow-up visits so you and your dermatologist are looking at the same evidence.
Frequently Asked Questions
Is subcision painful?
Comfort varies, and there is no single answer that applies to everyone. What you feel depends on the numbing approach used, the depth and location of the scar, and your own sensitivity. Because protocols differ between practices, the most reliable answer comes from asking the dermatologist who would perform your treatment what they use and what patients typically report afterward.
Can subcision get rid of acne scars completely?
No procedure removes acne scars entirely. Subcision is designed to improve the appearance of depressed valley scars by breaking the fibrous bands that hold them down, allowing the scar to elevate and the skin to look smoother. Think in terms of meaningful improvement rather than erasure, and ask your dermatologist what change they expect for the scars you have.
Can you have subcision while taking Accutane?
This is a clinical judgment rather than a rule you can look up, and guidance varies between dermatologists. Tell your prescribing dermatologist about every medication you take, including isotretinoin, and ask whether they want you to pause treatment or wait before scheduling subcision. Follow the instructions you are given rather than advice from a forum.
Which needle is used for subcision?
Descriptions of the procedure mention a small needle or a blunt cannula, and the choice depends on the dermatologist’s technique and the scar being treated. There is no single instrument that applies to every case. If you are curious about the plan for your skin, ask what will be used and why during your consultation.
How soon can I go back to work after subcision?
Most patients can return to work or their normal activities within 1 to 2 days, though minor bruising or tenderness may linger for about a week. Planning your appointment around a quiet couple of days keeps the recovery comfortable, and your dermatologist can provide aftercare instructions specific to your treatment.
Actinic Keratosis Treatment: Stopping Pre-Cancerous Spots
Actinic keratosis is one of the most common findings a dermatologist sees during a routine skin exam, and it is also one of the most treatable. These rough, sandpaper-like growths are classified as pre-cancerous, which means they have the potential to develop into a more serious skin cancer over time if they are ignored. The encouraging part is that actinic keratoses are reversible and can be treated when they are caught at an early stage. Treatment is not one single procedure. It is a category of options that ranges from a quick in-office freeze to prescription creams used at home over several weeks.
What Actinic Keratosis Looks Like
Actinic keratoses are rough, sandpaper-like, slightly raised growths that range in color from pink to red to brown. They often feel more noticeable than they look, and many people describe the surface as fine grit, a patch of stubborn dry skin, or a spot that never quite smooths out no matter how much moisturizer goes on it. In everyday conversation these lesions are sometimes called age spots, although that casual label can blur the difference between a harmless mark and a growth that deserves a closer look.
They show up on skin that has received a great deal of sun over a lifetime. That location pattern is part of why a dermatologist can usually recognize them quickly during an exam, and why a full skin check matters more than staring closely at any single spot in the mirror.
Who Tends to Develop Actinic Keratosis
Actinic keratoses are very common, particularly among fair-skinned individuals who have accumulated a lot of sun exposure. The word cumulative is the important one here. Risk builds over decades of time outdoors rather than from any single sunburn, which explains why these growths tend to appear later in life on the areas of skin that see the most sun.
If you have had one actinic keratosis, you are the type of patient a dermatologist will want to examine on a regular schedule. New lesions can develop over time, including on skin that was previously treated, and monitoring is a normal part of long-term care rather than a sign that earlier treatment failed.
The Main Actinic Keratosis Treatment Options
Dermatologists draw from a small set of well-established approaches, and the choice among them depends on your specific pattern of sun damage. Here is what each one involves.
Cryotherapy
Cryosurgery, which means freezing the involved area with liquid nitrogen, is the usual treatment for many patients. It is performed in the office and is frequently chosen when the number of lesions is small and the spots are well defined. The treated area typically crusts or peels before new skin forms underneath. Because cryotherapy targets what the dermatologist can see, it is often paired with other treatments when a wider field of sun-damaged skin also needs attention.
Prescription Topical Medications
A prescription, FDA-approved topical medication is another core option. These products are applied directly to the affected areas at home and work over time to remove damaged cells. 5-fluorouracil cream, commonly called 5-FU, is a frequently used topical therapy and is a chemotherapy agent, which helps explain why treated skin reacts visibly during the course of treatment. Topical therapy can cover a broader area than a single freeze, which makes it useful for skin with widespread damage. Your dermatologist will explain how long to use it and what the reaction should look like.
Light Therapy
Light therapy is another approach your dermatologist may recommend. It is one of the standard options in the actinic keratosis toolkit, alongside cryotherapy, topical medication, and surgical removal. Suitability depends on the number, thickness, and location of the lesions, along with your skin type and history. Ask your dermatologist where light therapy fits for your particular pattern of damage and how it compares with the alternatives in your case.
Laser Resurfacing
Lasers can be used to resurface the skin, removing the damaged cells and keratoses. This approach treats the surface layer where sun damage accumulates, which can be helpful when the goal is to address a field of affected skin rather than one isolated spot. Nearly all actinic keratosis treatments cause some redness, swelling, or other reactions, and laser resurfacing is no exception, so plan for a recovery period and follow the aftercare instructions you are given.
Surgical Removal
Surgical removal is also among the treatment options. It is often used when a lesion needs to be taken off and examined under a microscope, or when a spot is thick enough that other methods are less reliable. Your dermatologist will discuss whether a straightforward removal or a more detailed pathologic review is appropriate, and what that means for healing.
How Your Dermatologist Chooses a Treatment
The decision usually comes down to a few practical questions. How many lesions are there? Are they scattered single spots, or is there a broad field of damaged skin around them? How thick are they? Where are they located? How much downtime can you reasonably accept?
Spot treatment versus field treatment is a useful way to think about it. Cryotherapy removes what the dermatologist can see, which suits a small number of discrete lesions. Topical medications and laser resurfacing can address a wider area of sun-damaged skin, which matters when the visible spots are only part of the picture. Many patients end up using more than one approach over the years, adjusted as their skin changes.
What Recovery Usually Looks Like
Nearly all of these treatments cause some redness, swelling, or other reactions. That is not a sign that something went wrong. With cryotherapy, the site crusts and then heals. With topical therapy, the skin reacts gradually as damaged cells are removed over time. With laser resurfacing, the surface needs time to rebuild. Ask your dermatologist for specific aftercare instructions, including what to apply to the treated area, how to protect it while it heals, and which symptoms warrant a call to the office.
Why Treating Early Matters
An actinic keratosis is not a skin cancer, but it is a pre-cancerous growth, which is why dermatologists treat it rather than watch it indefinitely. Actinic keratoses are reversible and can be treated when diagnosed at early stages. Leaving one alone means leaving a known area of abnormal skin in place, and the options available for an early lesion are generally simpler than what a more advanced problem requires. That is the practical reason so much emphasis goes on routine skin exams and on treating spots while they are still small and easy to reach.
Reducing the Risk of New Spots
Because cumulative sun exposure is the driving factor behind actinic keratosis, protecting your skin from ongoing ultraviolet exposure is the most sensible long-term strategy. Talk with your dermatologist about sun protection habits that fit your skin type, your medications, and the amount of time you spend outdoors. Regular skin examinations matter too, since new lesions can develop on skin that was previously treated. Many patients alternate between treatment visits and monitoring visits, which keeps a dermatologist familiar with how your skin changes over the years.
Getting Evaluated in Denver
Colorado Dermatology Center is a South Denver dermatology practice led by board-certified dermatologist Dr. James M. Swinehart. The practice combines more than three decades of clinical expertise with medical, surgical, and cosmetic dermatology, with special emphasis on skin cancer treatment that includes MOHS micrographic surgery. That background is relevant to actinic keratosis, because choosing between cryotherapy, topical therapy, light therapy, laser resurfacing, and surgical removal depends on an accurate diagnosis and a clear view of how much sun-damaged skin is involved. If you have rough, scaly spots that will not smooth out, an in-person evaluation is the right first step.
Frequently Asked Questions
What is the most effective treatment for actinic keratosis?
There is no single answer that fits every patient, and dermatology sources do not rank one method above all others. Cryotherapy, prescription topical medications, light therapy, laser resurfacing, and surgical removal are all established options. The best choice depends on the number, size, thickness, and location of the lesions, your skin type, your history of sun damage, and how much recovery time you can manage.
Can actinic keratosis go away on its own?
Actinic keratoses are described as reversible and treatable when they are diagnosed early, but dermatologists do not generally recommend waiting to see whether a spot clears by itself. A pre-cancerous growth can change over time, and a lesion that looks harmless on the surface may not be. If you notice a new rough, scaly, or growing spot, have it checked rather than watched.
Do actinic keratosis treatments hurt?
Nearly all of these treatments cause some redness, swelling, or other reactions, and the level of discomfort varies by method. Cryotherapy is a brief in-office freeze that many patients tolerate without difficulty. Prescription topical therapy causes visible skin reactions that build over the course of treatment. Laser resurfacing involves a recovery period. Your dermatologist can explain what to expect for the specific plan you choose.
How do I know if a spot is actinic keratosis or skin cancer?
You cannot tell reliably on your own, and that is the main reason an in-person examination matters. Actinic keratoses are rough, sandpaper-like, slightly raised growths that can be pink, red, or brown, but other skin cancers can look similar. A dermatologist evaluates the lesion directly and may recommend a biopsy when the diagnosis is uncertain. Any spot that bleeds, grows, or changes should be examined promptly.

Skin Cancer Screening CPT Codes and ICD-10 Codes Explained
A skin cancer check can be over in fifteen minutes, but the paperwork it generates often lists several five-digit CPT codes and a separate diagnosis code. Those numbers are not random. Each one tells an insurer what happened during the visit, from the exam itself to a biopsy to the lab work that follows.
Knowing what the common codes mean makes it easier to read an explanation of benefits, spot a duplicate charge, and ask informed questions before you owe anything. This guide walks through the codes that appear most often around skin cancer screening, biopsies, pathology, and Mohs surgery, using published coding references and payer policy documents as the source.
There Is No Single Skin Cancer Screening CPT Code
One of the most common assumptions patients make is that a skin cancer screening has its own dedicated code. Based on the coding references reviewed for this article, that is not the case. No standalone screening code for skin cancer appears in those sources.
Instead, a screening visit is generally reported with an evaluation and management (E/M) code, the same family of codes used for any office visit. A published review of skin cancer screening encounters between January 2011 and December 2015 lists 99203 among the codes tied to those visits, alongside 11100 and 88305. That mix tells a story: an office visit code for the examination, a biopsy code when a lesion is sampled, and a pathology code when the sample is analyzed in a lab.
Because the exam itself is what drives the billing, the final cost of a screening depends on what the dermatologist finds and what happens next. A visual check that ends with “everything looks fine, see you next year” produces a very different claim than a visit that includes a biopsy.
The CPT Codes Most Often Linked to Skin Cancer Care
The codes below come up repeatedly in dermatology coding references and payer policy documents. They cover the visit, the procedure, and the lab work.
Evaluation and Management Visits (99203 and Similar Codes)
The office visit code is the foundation of most skin cancer related claims. It reflects the history your dermatologist takes, the examination performed, and the medical decision making involved. In the published screening encounter review mentioned above, 99203 was the E/M code listed. The specific E/M code on your claim depends on the complexity of the visit, so two patients seen on the same day may not carry the same code.
Skin Biopsy Codes (11102 Through 11107)
When a lesion looks suspicious, the dermatologist may remove a sample for testing. Coding references group 11102 through 11107 as skin biopsy codes, covering techniques such as punch and shave biopsies. The code reported depends on the technique used and the number of lesions sampled. The screening encounter review also lists 11100, another biopsy code, which shows that more than one code from the biopsy family can appear on a skin cancer related claim.
Pathology Codes (88305)
Once tissue is removed, it travels to a lab for microscopic examination. That step is reported separately, and 88305 is the pathology code listed in the same screening encounter review. This is why patients sometimes receive two bills for one small procedure: one from the dermatology practice for removing the tissue, and one from the lab for reading it. The pathology report also produces the diagnosis that gets attached to the claim.
Mohs Micrographic Surgery (17305)
For certain skin cancers, particularly on the face where preserving healthy tissue matters, Mohs micrographic surgery may be recommended. CPT code 17305 describes a two-stage Mohs micrographic surgery procedure for removing skin cancer that involves up to five tissue specimens. Coding references for 17305 also address whether a modifier is needed, which matters because modifiers can change how a payer processes the claim. If you are scheduled for Mohs, ask the billing office how the stages and specimens will be reported.
Whole Body Photography (96904)
Some patients, especially those with many moles or a personal history of melanoma, have their skin documented with a set of baseline photographs. Coding guidance notes that CPT code 96904 may be submitted to describe whole body photography. These images give the dermatologist a reference point for spotting changes at the next visit, and they are usually reported in addition to the examination itself.
Optical and Digital Lesion Analysis
Dermatoscopy, also called dermoscopy or epiluminescence microscopy, lets a clinician examine diagnostic features in pigmented skin lesions directly. A second category, multispectral digital skin lesion analysis (MSDSLA), is a noninvasive approach to diagnosing skin lesions and is described in policy language as analysis of clinically atypical cutaneous pigmented lesions for detection of melanomas and high risk melanocytic atypia. Both approaches are covered inconsistently, which is why payer policy language matters so much for these services.
| Code | What it describes |
|---|---|
| 99203 | Office visit code listed in a published review of skin cancer screening encounters |
| 11102 to 11107 | Skin biopsy codes, including punch and shave techniques |
| 11100 | Biopsy code also listed in the same screening encounter review |
| 88305 | Pathology code reported when a specimen is examined in the lab |
| 17305 | Two-stage Mohs micrographic surgery involving up to five tissue specimens |
| 96904 | Whole body photography |
ICD-10 Codes Describe the Diagnosis, Not the Service
CPT codes answer “what was done.” ICD-10 codes answer “why.” A claim normally carries at least one diagnosis code that supports the service being billed, and for skin cancer that code describes the specific type and location of the lesion.
Published listings for non-melanoma skin cancer include C44.319 for basal cell carcinoma of skin of other parts of face, and C44.320 for squamous cell carcinoma of skin of unspecified parts of face. The squamous cell series continues with C44.321. The pattern is worth noticing: these codes carry both a cancer type and a body site, because payers want to know exactly which cancer is being treated and where.
If you have ever wondered why your dermatologist measures and describes a lesion so carefully, this is part of the reason. The documentation has to support the code that gets submitted.
Why One Visit Can Produce Several Codes
A single appointment can legitimately generate an office visit code, a biopsy code, and a pathology code, because three distinct services were provided. That is not double billing. What would be a problem is the same service reported twice without reason, or a procedure code reported without a supporting diagnosis.
This is also where modifiers come in. The reference material for CPT 17305 includes a section specifically on modifiers, which reflects how often payers need extra information to understand the relationship between two procedures performed on the same day. If your claim is denied or reduced, a missing modifier is one of the first things a billing office checks.
Coverage Policy Changes, So Verify Before You Assume
Payer policies do not stay still. The policy covering optical diagnostic devices used to evaluate skin lesions suspected of malignancy carries an effective date of June 1, 2009, with a last update of November 6, 2018. A separate policy on multispectral digital skin lesion analysis carries an effective date of January 1, 2021, and lists committee approval dates stretching back years.
The code set changes too. When CPT updates were introduced for 2021, they added code 71271 for low dose CT thorax for lung cancer screening and 76145 for medical physics dose evaluation for radiation exposure. New codes appear regularly, and coverage decisions follow.
The practical takeaway is simple. Ask your insurer whether the specific service is covered under your plan, in writing if possible, and ask your dermatology office which codes they expect to submit. Neither the code list nor the coverage rules in this article should be treated as your final answer, because your plan’s current policy is the document that decides what you owe.
Questions Worth Asking Before Your Appointment
- Which CPT codes will be submitted for this visit, and does that change if a biopsy is needed?
- Is the visit being billed as a screening or as a problem focused visit for a specific lesion?
- If a biopsy is taken, will the pathology charge come from a separate lab?
- If Mohs surgery is planned, how are the stages and specimens reported?
- Does my plan require prior authorization for any of these services?
Skin Cancer Care in South Denver
Colorado Dermatology Center is a South Denver dermatology practice led by board-certified dermatologist Dr. James M. Swinehart. The practice focuses on medical, surgical, and cosmetic dermatology, with particular emphasis on skin cancer treatment including Mohs micrographic surgery. If you have questions about how a screening, biopsy, or Mohs procedure will be coded and billed, the office can walk you through what to expect before the claim is ever submitted.
Frequently Asked Questions
Is there a CPT code just for skin cancer screening?
No dedicated skin cancer screening code appears in the coding references reviewed here. Screening visits are typically reported with an evaluation and management code, such as 99203, which is the office visit code that appeared in a published review of skin cancer screening encounters from 2011 through 2015. Your dermatology office can confirm which code applies to your visit.
What is CPT code 17305 used for?
CPT 17305 describes a two-stage Mohs micrographic surgery procedure for removing skin cancer that involves up to five tissue specimens. It is specific to Mohs surgery, which is often chosen for cancers on the face where conserving healthy tissue matters. Coding references for 17305 also discuss modifier use, since payers may need extra detail about same-day services.
What does CPT 96904 mean on my bill?
CPT 96904 may be submitted to describe whole body photography. This is a set of baseline images your dermatologist uses to track moles and other lesions over time, which is helpful for patients with many moles or a history of melanoma. It is usually reported in addition to the examination, so seeing it alongside a visit code is normal.
Which ICD-10 code covers basal cell carcinoma of the face?
Published listings show C44.319 for basal cell carcinoma of skin of other parts of face, and C44.320 for squamous cell carcinoma of skin of unspecified parts of face. These C44 codes describe the diagnosis rather than the service. CPT codes describe what was done, and ICD-10 codes explain why, so both appear on the same claim.
Do I need to verify coverage myself?
Yes, and it is worth the phone call. Payer policies carry different effective and update dates, and the code set gains new entries over time. No article can tell you what your specific plan covers today. Confirm the coverage rules and any prior authorization requirements with your insurer, and ask your dermatology office which codes they plan to submit.

Dermal Fillers in Denver: Natural Results, Not Frozen
Search for dermal fillers in Denver and you will find a long list of options: plastic surgery practices, med spas, dermatology offices, and a few providers whose marketing leans heavily on brand names. What that list will not tell you is which of those offices is best at keeping a result subtle. Volume is easy to add. Knowing when to stop is the harder skill, and it is the difference between looking refreshed and looking done.
This guide covers what makes a filler result read as natural, which filler families are commonly stocked in the Denver area, how to compare providers, and the questions that separate a careful consultation from a rushed one.
What Makes a Filler Result Look Natural
An injector’s job is not to add filler until a line disappears. It is to restore support where the face has lost it, in amounts small enough that the expression itself does not change. Several factors decide that outcome:
- Product selection. Different filler families and formulations are built for different jobs. A product suited to deep structural support is not the same product used for fine surface lines.
- Volume restraint. Small amounts placed over a staged schedule tend to settle more softly than one large correction done in a single visit.
- Placement. Where the product goes matters as much as how much goes in. Deep support and superficial smoothing require different technique.
- Proportion over symmetry. Most faces age unevenly. Equal volume on both sides rarely produces a natural result.
- Honesty about limits. Some concerns are better addressed with treatments other than filler, and a good provider will say so rather than sell another syringe.
All of those decisions happen before the needle is uncapped. That is why the consultation matters more than the brand on the box.
Fillers Are Not the Same as a Frozen Forehead
People often use the word “frozen” to describe any injectable result, but fillers and neuromodulators are different categories of treatment with different goals. Denver clinics that offer both typically list them separately, with neuromodulators grouped under wrinkle relaxers and fillers grouped under volume restoration.
Filler adds or restores volume. It does not paralyze muscle. A genuinely frozen expression is more often connected to wrinkle relaxers than to filler, though overfilling can absolutely create a stiff, puffy look that people describe the same way. The practical takeaway is simple: if your concern is lost volume, hollowing, or a fold that has deepened, filler is the category to discuss. If your concern is movement lines, that is a different conversation.
Filler Families Commonly Stocked in Denver
Denver clinics offering dermal fillers commonly stock Restylane and Juvederm, and those brand families include multiple formulations rather than a single product. RealSelf lists Sculptra, Radiesse, and Restylane Lyft among the related procedures patients search for in Denver, which suggests those options are available in the market as well. Bellafill is a long-lasting filler approved for correction of smile lines, which makes it a different kind of option from the more widely used hyaluronic acid products.
The table below summarizes what the available research supports. It does not rank products, because the best choice depends on the area being treated, your anatomy, and your provider’s assessment.
| Filler | What the research supports | What to ask your provider |
|---|---|---|
| Juvederm | Commonly stocked in Denver clinics; sold as a brand family with multiple formulations | Which formulation is being recommended, and why |
| Restylane | Commonly stocked in Denver clinics; sold as a brand family with multiple formulations | How the recommended formulation differs from others |
| Restylane Lyft | Listed among related procedures patients search for in Denver | Whether it suits the area you want treated |
| Sculptra | Listed among related procedures patients search for in Denver | How its approach differs from standard fillers |
| Radiesse | Listed among related procedures patients search for in Denver | Whether it fits your treatment goals |
| Bellafill | A long-lasting filler approved for correction of smile lines | Why a long-lasting option may or may not be right for you |
Notice how little the brand names tell you on their own. Two offices can carry the same products and produce very different results. Product availability is a starting point, not a differentiator.
Who Offers Dermal Fillers in Denver
The provider mix in the Denver area is broad. Dermatology practices, plastic surgery practices, and med spas all offer injectables, and at least one Denver dental practice advertises dermal fillers alongside family dentistry. Reviews, before and after photos, and board certifications are all published on third-party directories such as RealSelf, which exists specifically so patients can compare providers in one place.
That breadth is useful for research and risky for decision making. A med spa and a physician-led dermatology practice are not equivalent settings, even when they list the same filler brands. What matters is who is holding the syringe, what happens if a complication arises, and whether the person assessing your face has the clinical background to recognize when filler is the wrong answer.
Questions to Ask Before You Book
- Who will actually perform the injections, and what is that person’s training and board certification?
- Which specific products do you recommend for my concerns, and what is the reasoning behind each one?
- How much do you plan to use at the first visit, and can we stage the treatment over more than one appointment?
- What does the practice do if I am unhappy with the result, and what options exist for reversal or adjustment?
- What are the risks and expected downtime for the areas being treated?
- Can I see before and after photos of patients with features similar to mine?
Any provider who cannot answer these plainly is giving you information about how the office operates.
How to Read Reviews and Photos Without Getting Fooled
Patient reviews are useful, but they reward the wrong things. A dramatic transformation often photographs better than a subtle one, so the most skilled injector in a given market may have the least eye-catching gallery. When you look at photos, pay attention to expressions, not just resting faces. A result that holds up when someone smiles or frowns is doing something a straight-on photo cannot show.
Read reviews for language about listening, pacing, and follow-up. Comments about a provider talking someone out of a treatment, or recommending a smaller amount than requested, are more meaningful than a dozen posts about a great deal.
What the Research Does Not Tell You
Pricing, how long specific products last in a given area, and aftercare instructions vary by provider and by product, and the sources behind this article do not include reliable figures for any of them. Treat any number you see online, including on a clinic’s own page, as a starting point that needs to be confirmed directly with the office before you schedule. Cost in particular depends on the number of syringes used, which is a clinical decision rather than a package you can price in advance with confidence.
Where Colorado Dermatology Center Fits In
Colorado Dermatology Center is a South Denver dermatology practice led by board-certified dermatologist Dr. James M. Swinehart, whose clinical experience spans more than three decades. The practice covers medical, surgical, and cosmetic dermatology, with facial rejuvenation sitting alongside skin cancer treatment including MOHS micrographic surgery, hair restoration, tumescent liposuction, acne scar revision, and clinical research trials.
That combination matters for filler patients more than it might appear. A practice that treats skin disease, performs surgery, and manages cosmetic concerns has a wider frame of reference than an injectable-only office. It also means patients whose concerns turn out to be better addressed by a different treatment have somewhere to go within the same practice.
The consistent emphasis in the practice’s approach is personalized care and natural-looking results rather than dramatic change. For anyone trying to avoid the overfilled look, that is the right starting point for a conversation.
Frequently Asked Questions
Are dermal fillers the same thing as Botox?
No. Fillers add or restore volume, while Botox and similar products relax the muscles that create movement lines. Denver clinics that offer both usually list them as separate categories. A frozen expression is more commonly linked to muscle relaxers, though overfilling with filler can create a stiff appearance that patients describe the same way.
How do I avoid looking overfilled?
Start smaller than you think you need, and plan to build over more than one visit. Ask your provider how much they intend to use at the first appointment and whether the plan can be staged. Choose an injector who is willing to say no to a request rather than one who agrees to everything.
Which filler is best for natural results?
There is no single best product. Denver clinics commonly stock Restylane and Juvederm, and those families include multiple formulations, with Sculptra, Radiesse, and Restylane Lyft also appearing in local search results. The right choice depends on the area being treated, your anatomy, and the injector’s technique, not on the brand name alone.
How should I compare providers in Denver?
Look at board certification, who performs the injections, and before and after photos of patients with similar features. Directories such as RealSelf publish reviews, photos, and credentials in one place. Pricing matters, but the research behind this article does not include verified Denver rates, so confirm costs directly with each office before scheduling.
What should I ask during a consultation?
Ask who will inject, which products are recommended and why, how much will be used at the first visit, what happens if you dislike the result, and what the risks and downtime are. A provider who answers these questions clearly and recommends a conservative starting point is usually the better choice.

Cystic Acne Scar Treatment Options for Deep Tethered Scars
Cystic acne does its damage underneath the surface. The lesion forms deep in the skin, and when the inflammation finally calms, what remains is often not a flat mark but a structural dent held in place by fibrous tissue. That tethering is why a scar looks deeper when you smile or lift your brows. It is also why the treatment options for cystic acne scars are not the same as the options for simple post-acne redness.
Picking a plan is not about choosing the most aggressive procedure available. It is about matching the depth and number of scars you have to a technique that can actually reach them, then protecting the result while new collagen settles in.
What Makes a Cystic Acne Scar Tethered
Acne scars are the marks left behind after acne clears, and they can be treated with chemical peels, skin needling, laser, and other procedures. What changes from patient to patient is how deep the problem runs and how many scars are involved.
When a cyst heals, the skin can pull downward and attach to the tissue beneath it instead of sitting flat. The scar stays anchored, which is why it tends to look like a rolling or pitted depression rather than a spot. Because the problem is partly mechanical, a product that only exfoliates the surface will not release that tether. The scar needs a treatment that either rebuilds collagen in the deeper layers or interrupts the tension holding it down.
That distinction is the single most useful thing to understand before you compare clinics or devices. Two scars that look similar in a mirror can sit at completely different depths, and depth determines which tools are worth your time.
Why Scar Count and Depth Change the Plan
Severity drives everything. Mild scarring, meaning fewer than 10 visible scars with minimal depth, may respond well to less aggressive treatments such as superficial chemical peels. Deeper and more numerous scars generally need approaches that reach below the epidermis, where collagen remodeling actually happens.
| Scar pattern | Typical starting point |
|---|---|
| Mild scarring: fewer than 10 visible scars, minimal depth | Less aggressive options such as superficial chemical peels |
| Deeper or tethered scarring | Resurfacing approaches that reach deeper layers, including microneedling radiofrequency and laser skin resurfacing |
| Active cystic acne alongside existing scars | Medical control first, using topical treatments, oral medications for inflammation or hormone levels, and short-term anti-inflammatory care |
Notice that the third row is not really a scar treatment at all. It is acne treatment. If cysts are still forming, every new lesion is a chance for another tethered scar, so controlling the disease comes before chasing the damage it already caused.
Professional Treatment Options for Deep, Tethered Scars
In-office options overlap, and most real treatment plans combine more than one. The sections below cover the categories that come up most often in acne scar care.
Microneedling Radiofrequency
Microneedling radiofrequency, often shortened to MNRF, is one of the well-known acne scar treatment solutions. Fine needles create controlled channels in the skin while radiofrequency energy is delivered below the surface, where collagen remodeling takes place. Because the energy is deposited under the skin rather than dragged across the top, MNRF can work on scars that sit deeper than a peel is able to reach.
Morpheus8 is discussed alongside chemical peels and lasers in current acne scar treatment literature, and it falls into this same resurfacing family. If you have heard the name and wondered how it fits, the short answer is that it belongs to the energy-based group, not the topical group.
Laser Skin Resurfacing
Laser skin resurfacing removes damaged skin layers and boosts collagen in deeper layers, which reduces the visibility of scars. For tethered scarring, the collagen response matters as much as the surface removal. The goal is to rebuild support under the scar so it settles closer to the level of the surrounding skin rather than sitting in a fixed depression.
Laser treatment is also useful when texture and pigment are both part of the complaint, since a single resurfacing plan can often address both rather than sending you through two separate treatment tracks.
Chemical Peels
Chemical peels are tailored to the concern being treated. Superficial peels are a reasonable starting point for mild scarring with minimal depth. For deep, tethered scars, a peel is better understood as one component of a plan than a standalone fix, useful for tone, texture, and pigmentation while a deeper treatment addresses the structural component.
This is where a lot of disappointment happens. Someone buys a package of peels expecting the depressions to fill in, and the depressions do not change because nothing in the treatment reached them. Matching the tool to the depth is the whole job.
Combining Procedures
Because a tethered scar has more than one component, plans often stack. A series of microneedling radiofrequency sessions might be scheduled with peels in between, or laser resurfacing might be reserved for specific areas while a broader resurfacing approach handles overall texture. The sequencing matters as much as the menu, and it is usually spread over multiple visits rather than completed in one appointment.
Control Active Cystic Acne First
New cysts create new scars, so a scar plan that ignores ongoing acne tends to lose ground. A treatment plan may include a retinoid on its own; a retinoid combined with benzoyl peroxide, azelaic acid, or salicylic acid; or benzoyl peroxide paired with another topical active.
Topical treatments work to reduce oil production and bacteria. Oral medications help control inflammation or hormone levels, which matters for cystic acne because inflammation is what drives the deep damage in the first place. Short-term anti-inflammatory care can also be part of the picture during a flare. Your dermatologist will match the combination to your skin, your history, and how well you tolerate each active.

What You Can Do at Home Between Visits
Home care supports professional treatment, though it does not replace it for tethered scars. Vitamin C serums can be a good option for treating acne scars at home, and aloe vera is another commonly used ingredient. Sunscreen belongs in the routine as well, because unprotected exposure works against the skin you are trying to rebuild.
Think of these products as protecting your investment. They can improve tone, hydration, and overall appearance while procedures do the structural work. They will not release a tether, and no topical product will lift a scar floor that is anchored to deeper tissue.
How Colorado Dermatology Center Approaches Scar Revision
Colorado Dermatology Center is a South Denver dermatology practice led by board-certified dermatologist Dr. James M. Swinehart. The practice covers medical, surgical, and cosmetic dermatology, with acne scar repair among its focus areas alongside skin cancer treatment, hair restoration, tumescent liposuction, and clinical research trials.
That breadth is relevant for scar patients. Acne scarring is rarely a single problem, because active breakouts, pigment change, and deep structural scars often show up together. A practice that manages medical acne and procedural scar revision under one roof can sequence those pieces instead of sending you between providers who never compare notes. The practice is also known for offering procedures that many others do not, with an emphasis on personalized care and natural-looking results.
Questions to Bring to a Consultation
A scar consultation is more productive when you arrive with specifics. These are the questions that tend to shape a plan.
- Which of my scars are tethered, and which are surface-level texture or pigment?
- Which procedure actually reaches the depth of my deepest scars?
- How will my active acne be controlled while we work on scarring?
- What is the realistic sequence of treatments, and how many visits does it involve?
- What does recovery look like between sessions, and what should I do at home?
Ask for a realistic picture rather than a promise. Deep, tethered scars can improve meaningfully, but improvement is the honest word. A plan built around your actual scar pattern will always outperform a package sold without looking at your skin.
Frequently Asked Questions
Do deep cystic acne scars go away on their own?
Flat marks left after acne can fade over time, but tethered scars are structural and generally do not resolve without treatment. The tissue is anchored below the surface, so there is nothing for the skin to remodel on its own. Options such as microneedling radiofrequency, laser resurfacing, and chemical peels are used to improve them, and results build over a series rather than a single visit.
Can I treat tethered cystic acne scars at home?
At-home products can support tone and texture, and options like vitamin C serums and aloe vera are commonly used for acne scars at home. They cannot release a tether anchored in deeper tissue. Think of home care as maintenance around professional treatment, not a substitute, especially when scars are deep or numerous.
Should I treat active cystic acne and scarring at the same time?
Usually the acne gets controlled first, or at least concurrently, because new cysts create new scars. A plan may include a retinoid, a retinoid with benzoyl peroxide, azelaic acid, or salicylic acid, or oral medications that help with inflammation or hormone levels. Your dermatologist will decide what can safely run alongside scar procedures.
How many treatments will deep acne scars need?
It depends on scar depth, scar count, and which procedures are combined. Mild scarring with fewer than 10 visible scars and minimal depth may respond to less aggressive options like superficial chemical peels, while deeper tethered scarring typically needs a series of resurfacing sessions. Ask your dermatologist for a realistic sequence rather than a fixed number before your skin has been evaluated.
Which is better, laser resurfacing or microneedling radiofrequency?
Neither is universally better, and the choice depends on your scarring and skin. Laser skin resurfacing removes damaged surface layers and boosts collagen in deeper layers, while microneedling radiofrequency delivers energy below the surface through fine needles. Both are used for acne scarring, and many plans combine categories rather than choosing one exclusively.
If your scars are deep and tethered, the most valuable next step is an evaluation that identifies which scars are structural and which are not. That assessment is what turns a list of procedures into an actual plan, and it is the difference between spending money on treatments that suit your skin and spending it on treatments that suit someone else’s.
Squamous Cell Carcinoma on the Ear: Treatment Options
Skin cancer on the ear is common, and the reason comes down to anatomy and sunlight. The skin covering the outer ear spends more time in direct ultraviolet light than almost any other part of the body, and that exposure accumulates over decades. Squamous cell carcinoma is one of the skin cancers that develops in this location, and because the ear is small, cartilage-based, and sits next to a narrow canal, treatment decisions here carry more weight than they would on a shoulder or a back.
Most cases of ear skin cancer are easily treated, but the same cancer can spread to other parts of the body if it is left untreated. That combination, straightforward treatment when the tumor is small and real risk when it is not, is why the timing of care matters as much as the choice of procedure.
Why the Ear Is Considered a High-Risk Location
The skin on your outer ear is susceptible to cancer because it is often exposed to the sun’s damaging UV rays. That exposure is relentless, since the rims and the tops of the ears catch light from above at nearly every hour of the day, and many people never think to apply sunscreen there.
Ear cancer can develop in any part of the ear. It often starts on the outside of the ear as a skin cancer, and it can also form inside the ear canal. Cancers of the ear canal are rare and can be hard to diagnose because of their location, but they are generally curable if caught early enough.
Dermatologists and head and neck surgeons treat these tumors as a distinct group because the ear is an anatomically complex area. Skin there is thin, it sits directly over cartilage, and the canal is a tight space that is difficult to examine without the right equipment. Each of those features affects which treatment approach makes the most sense.
Signs and Symptoms That Deserve a Closer Look
Symptoms include changes to your skin, such as discoloration. Not every change on an ear turns out to be cancer, but a persistent one is worth having examined rather than watched at home. Points to raise with a clinician include:
- Any discoloration or other visible change in the skin of the outer ear
- A spot or lesion that persists instead of resolving on its own
- Any change involving the ear canal, which is hard to see on your own
Because tumors inside the canal can be difficult to diagnose from the outside, a symptom that seems minor may still need an in-office examination to be sorted out.
Treatment Options for Squamous Cell Carcinoma of the Ear
The main treatments for cancer of the outer ear are surgery and radiotherapy. Beyond surgery, other options for removal of skin cancer on the ear include chemotherapy, cryotherapy, immunotherapy, and photodynamic therapy. For more advanced-stage tumors, treatment often requires a combination of surgery, chemotherapy, and radiation therapy, and immunotherapy is now used as a first-line approach in some situations.
| Approach | Where it fits |
|---|---|
| Mohs micrographic surgery | Often preferred for high-risk sites such as the lips and ears; removes cancer cells layer by layer while preserving normal skin and cartilage |
| Surgery with or without post-operative radiotherapy | Forms the mainstay of treatment for squamous cell carcinoma of the external auditory canal and temporal bone |
| Sleeve resection | Usually recommended for growths located closer to the opening of the affected ear; removes the skin of the ear canal |
| Radiotherapy | One of the two main treatments for cancer of the outer ear, and used after surgery in some cases |
| Immunotherapy | Used in more advanced disease; pembrolizumab has been studied for recurrent or metastatic squamous cell carcinoma |
| Chemotherapy, cryotherapy, photodynamic therapy | Additional non-surgical options for skin cancer on the ear |
Mohs Micrographic Surgery for Ear Tumors
For high-risk areas such as the lips and the ears, Mohs surgery is often the preferred method. The technique removes cancer cells layer by layer, with each layer examined under the microscope before the surgeon decides whether more tissue needs to come out. That step-by-step confirmation is what separates it from a standard excision, where the margin is checked only after the tissue is closed.
Published research supports its role in this location. A case series described 170 cases of squamous cell carcinoma of the external ear treated with Mohs surgery, and the same literature has examined pembrolizumab for recurrent or metastatic squamous cell carcinoma of the ear.
Why Tissue Preservation Matters on the Ear
Mohs micrographic surgery is the preferred treatment in many cases because it removes the cancer while preserving as much normal skin and cartilage as possible. On an ear, that margin for error is narrow. Cartilage gives the ear its shape, and thin skin over that cartilage does not leave much room for a wide surgical defect. Preserving tissue can mean a simpler reconstruction and a result that looks closer to the original ear.
When the Tumor Involves the Ear Canal or Temporal Bone
Surgery with or without post-operative radiotherapy forms the mainstay of treatment for squamous cell carcinoma of the external auditory canal and temporal bone. These tumors behave differently from surface lesions on the rim or lobe, and the surgical plan reflects the anatomy around them.
For growths located closer to the opening of the affected ear, a sleeve resection, which removes the skin of the ear canal, is usually recommended. The goal is to clear the tumor while leaving as much function and structure intact as the location allows.
When Advanced Disease Changes the Plan
More advanced-stage tumors often require a combination of surgery, chemotherapy, and radiation therapy. Immunotherapy is now used as a first-line treatment in some advanced cases, and pembrolizumab has been studied specifically for recurrent or metastatic squamous cell carcinoma. These decisions are typically made by a team rather than a single specialist, and the sequence of treatments can change as the disease responds.
When to Act on a Suspicious Spot on the Ear
If you notice a change in the skin of your ear, an evaluation is the sensible next step rather than a wait-and-see approach. Most cases of ear skin cancer are easily treated, and cancers of the ear canal are generally curable if caught early enough. The same cancer can spread to other parts of the body if untreated, which is the practical argument against monitoring it at home for months.
There is no single answer to how long someone can safely wait before treatment. That timeline depends on the type, size, and depth of the tumor, whether nearby lymph nodes are involved, and other individual factors, so it is a question for your dermatologist rather than a general rule you can apply to yourself. The general principle that the research supports is simpler: earlier diagnosis widens the options and usually makes the treatment smaller.
Questions Worth Asking at Your Appointment
- Is this squamous cell carcinoma, and how was that determined?
- Is Mohs surgery appropriate for my tumor, or would another approach work better?
- Does the tumor involve the ear canal or the temporal bone?
- Would radiation, immunotherapy, or another treatment play a role in my case?
- What signs would mean the tumor is changing and needs faster attention?
Frequently Asked Questions
Is squamous cell carcinoma on the ear considered high risk?
Yes. The ears are treated as a high-risk area for skin cancer, alongside sites such as the lips, and that classification shapes treatment planning. For high-risk areas like these, Mohs surgery is often the preferred method because it removes cancer cells layer by layer while preserving as much normal skin and cartilage as possible. Your dermatologist can confirm whether your tumor fits that profile.
Can squamous cell carcinoma on the ear be treated without surgery?
Surgery is the mainstay for most tumors of the outer ear, where the two main treatments are surgery and radiotherapy. Beyond surgery, options include chemotherapy, cryotherapy, immunotherapy, and photodynamic therapy. Which approach fits a specific tumor depends on its size, depth, location, and whether it has spread, so the plan is made case by case rather than by a single standard.
How is a tumor inside the ear canal treated?
Cancers of the ear canal are rare and can be hard to diagnose because of their location, but they are generally curable if caught early enough. When a growth sits closer to the opening of the affected ear, a sleeve resection, which removes the skin of the ear canal, is usually recommended. For the external auditory canal and temporal bone, surgery with or without post-operative radiotherapy forms the mainstay of treatment.
What happens if squamous cell carcinoma on the ear is not treated?
Most cases of ear skin cancer are easily treated, but the same cancer can spread to other parts of the body if it is left untreated. That is the core reason a persistent change on the ear deserves examination rather than indefinite monitoring at home. Prompt evaluation keeps the treatment options broader and, in most cases, the procedure smaller.
Does Mohs surgery work for squamous cell carcinoma of the ear?
Mohs surgery is widely used for squamous cell carcinoma of the external ear, and one published case series described 170 cases treated with this technique. It is often preferred on the ear because it removes the cancer while preserving as much normal skin and cartilage as possible, which matters for both reconstruction and appearance. Your dermatologist can say whether your specific tumor is suited to it.
Annual Skin Cancer Screening: Who Needs One and When to Start
Skin cancer screening is unusual among cancer checks because it starts with your own eyes and ends with a short visit to a clinician. The harder question is scheduling. Some people are advised to book a full-body exam every year, some every six months, and some can reasonably stretch the interval to two or three years. Which group you fall into depends less on your calendar and more on your personal risk.
What Happens During a Full-Body Skin Exam
Most full-body skin screenings take as little as 10 to 15 minutes to complete. You will be asked to remove your clothes and change into a medical gown before the exam begins. A clinician then works across your skin in a systematic way, checking the scalp, back, arms, legs, and other areas that are difficult to see in a mirror.
Less visible areas deserve the same attention. The CDC advises checking parts of the skin that rarely see daylight, such as the soles of your feet, and telling your doctor about any unusual moles or changes you have noticed. Those changes are often the reason a particular spot gets a closer look in the first place.
Why Regular Screening Matters
Approximately 1 in 5 Americans will develop some form of skin cancer by age 70, yet only 8 percent of patients who recently saw a primary care provider received a skin examination during that visit. That gap is part of why dedicated skin checks exist. A primary care appointment covers a lot of ground, and a full-body skin exam is easy to skip when time is tight.
An annual skin exam performed by a board-certified dermatologist ensures that suspicious spots are detected and addressed before they progress. Timing is the variable that matters most in skin cancer care, and a scheduled exam puts a firm date on the calendar instead of waiting for a spot to become obvious on its own.
Who Needs an Annual Skin Cancer Screening
Harvard Health’s guidance is direct: most people are at low risk of melanoma and do not need annual skin cancer screenings. People should be screened annually if they have risk factors that raise their likelihood of developing the disease.
Other dermatology practices describe the same split from the opposite direction. In that framing, experts recommend annual skin cancer screening for most adults, and personal risk factors can substantially change the recommended schedule. People in higher-risk categories are often advised to come in every six months rather than once a year.
The short version looks like this. Annual screening is the default for people with meaningful risk factors, a six-month interval is common for higher-risk patients, and a longer gap can be reasonable for people with low risk. Because the sources do not agree on a single universal rule, your individual history is what settles the question.
When to Start Screening
The guidance reviewed here does not set one age at which everyone should begin annual skin cancer screening. It ties the start of screening to risk instead, which means the practical starting point is a conversation rather than a birthday.
If you have never had a professional skin exam, a reasonable next step is to ask a dermatologist what interval fits your history. Bring whatever you already know about your own skin, including spots that have changed, and let that information shape the plan. Anyone with a strong reason for concern should not wait for a specific age to arrive before asking.
Screening Frequency: How the Guidance Compares
Different organizations emphasize different parts of the same picture. The table below summarizes what each source recommends, so you can see where the advice overlaps and where it diverges.
| Source | Screening guidance |
|---|---|
| Skin Cancer Foundation | See a dermatologist once a year, or more often if you are at higher risk, for a full-body professional skin exam. |
| Harvard Health | Most people at low risk of melanoma do not need annual screenings. Annual screening is advised for people with risk factors. |
| Dermatology practice guidance | Annual screening for most adults, every six months for higher-risk categories, and two to three years may be sufficient for about 80 percent of people. |
| U.S. Preventive Services Task Force | Inadequate evidence that clinician visual skin examination reduces morbidity or mortality. |
| Memorial Sloan Kettering | Check your own skin regularly, every month, for spots or moles that are new or changing. |
What the Evidence Says About Screening Programs
Not every medical body agrees that routine visual screening changes outcomes across an entire population. The U.S. Preventive Services Task Force found inadequate evidence that screening for skin cancer through visual skin examination by a clinician reduces morbidity or mortality. That finding concerns evidence at the population level, not whether a single exam can turn up a suspicious spot.
Two things can be true at once. A clinician exam can identify a lesion worth evaluating, and the evidence base for mass screening programs can remain unsettled. If you want the current recommendation in full, including any updates since it was issued, read the task force statement directly rather than relying on a summary.
How to Prepare for Your Appointment
Preparation makes a short exam more productive. The Skin Cancer Foundation’s guidance for annual exams puts self-examination first, so come to the appointment ready to point out specific areas of concern.
- Perform a self-exam before your visit so you know what you want to ask about.
- Bring notes about any new, changing, or unusual spots you want your dermatologist to look at.
- Bring smartphone photos of a spot that has changed, since a photo can show a shift that is hard to describe.
It also helps to mention anything you have noticed but dismissed, including a spot on the soles of your feet or another area you rarely inspect. Those details guide where the clinician spends time.
Monthly Self-Exams Between Visits
Memorial Sloan Kettering recommends checking your own skin regularly, every month. This is called a skin self-exam, and the goal is to notice skin spots or moles that are new or changing.
A self-exam does not replace a professional full-body exam, and it is not a diagnosis. What it does is teach you what is normal for your own body, which makes it easier to report something different at your next appointment. Pair the monthly habit with the CDC reminder to check less visible areas like the soles of your feet.
Where to Get Screened in South Denver
Colorado Dermatology Center is a South Denver dermatology practice led by board-certified dermatologist Dr. James M. Swinehart, whose clinical experience spans more than three decades. The practice focuses on medical, surgical, and cosmetic dermatology, with particular emphasis on skin cancer treatment including MOHS micrographic surgery, a technique used to remove certain skin cancers while preserving as much healthy tissue as possible.
If you are unsure whether you need an annual exam, checks every six months, or a longer interval, that question is worth asking at a consultation. Bring your notes and photos, share any family history or past sun exposure concerns you have, and let the exam findings and your personal history guide the schedule you follow from there.
Frequently Asked Questions
How long does a full-body skin exam take?
Most full-body skin screenings take as little as 10 to 15 minutes to complete. You will be asked to remove your clothes and change into a medical gown before the exam begins. Because the visit is short, arriving with notes about the spots you want checked helps the clinician focus on what matters most to you.
Do most people need an annual skin cancer screening?
It depends on risk. Harvard Health notes that most people are at low risk of melanoma and do not need annual screenings, while people with risk factors should be screened annually. Other dermatology guidance recommends annual exams for most adults, with higher-risk patients often checked every six months. Ask your dermatologist which interval fits your history.
Should I check my own skin between professional exams?
Yes. Memorial Sloan Kettering recommends checking your own skin regularly, every month. A skin self-exam means looking for spots or moles that are new or changing. It does not replace a professional full-body exam, but it helps you learn what is normal for your skin so you can report anything different at your next visit.
What should I bring to a skin cancer screening?
Come with notes about any new, changing, or unusual spots you want your dermatologist to examine. If you have taken smartphone photos of a spot that has changed over time, bring those as well. Preparation guidance recommends this self-exam-first approach so the appointment centers on the areas that concern you most.
How often should higher-risk patients be screened?
Dermatologists often recommend screening every six months for people in higher-risk categories. For lower-risk patients, one source suggests two to three years may be sufficient for about 80 percent of people. Because the right interval depends on your personal risk factors, confirm your schedule with your dermatologist rather than relying on a general rule.
Psoriasis Treatment in Denver: From Topicals to Biologics
Psoriasis is a chronic, inflammatory autoimmune disease. The immune system becomes overactive and speeds up the production of new skin cells, so those cells build up on the surface instead of shedding at a normal rate. The result is the redness, scaling, and raised patches that define the condition for millions of Americans.
Because psoriasis behaves differently from person to person, treatment in Denver is rarely a single prescription. It is usually a layered plan that starts with what you apply to your skin, adds light-based therapy when more surface area is involved, and moves toward systemic or biologic medication when the disease is moderate to severe. Understanding how those layers fit together makes it easier to have a productive conversation with a dermatologist.
What Psoriasis Actually Is
In healthy skin, new cells are formed at approximately the same rate that old cells are shed. In psoriasis, that balance breaks down. New cells develop far more rapidly, accumulate at the surface, and create the lesions people recognize as psoriasis.
Several types of psoriasis exist, and each one shows up differently. Lesions may appear as red, scaly, thickened plaques, or as pustules. Common locations include the elbows, knees, and scalp, but the condition can also affect the fingernails and toenails, the soft tissues of the genitals, and the inside of the mouth.
The precise triggers for psoriasis are not fully understood, which is one reason treatment focuses on controlling symptoms and slowing the underlying cell turnover rather than on eliminating a single known cause. That framing matters: psoriasis is managed, not cured, and the goal of care is fewer flares, less discomfort, and clearer skin over the long term.
The Treatment Ladder, Explained
Denver dermatologists generally work from the least invasive option upward, matching the intensity of treatment to how much skin is involved and how much the condition interferes with daily life. The three broad categories below cover most of what patients encounter.
Topical Therapy: Where Most Plans Begin
Topicals are medications applied directly to the affected skin. They are the standard first step for mild to moderate psoriasis, and corticosteroids are the most frequently prescribed medications in this category. They reduce inflammation and help calm the redness and scaling that come with an active flare.
Vitamin D analogues make up a second common topical group. These are often used to help slow the excessive cell growth that drives plaque formation, and they may be prescribed alongside a corticosteroid or used in rotation depending on how the skin responds.
Topical treatment works best with consistency. Applied as directed, these medications can keep limited psoriasis under good control, but they are not designed to manage widespread disease on their own. If plaques cover large areas or keep returning after each course, that is a signal to discuss stronger options rather than simply using more of the same product.
Phototherapy and UVB Light
UVB light therapy involves exposing the skin to controlled ultraviolet B light in a clinical setting. The purpose is to decelerate the excessive cell growth that produces psoriatic plaques, and it is listed among the psoriasis treatments offered by Denver-area practices.
Phototherapy is typically delivered in a series of sessions rather than as a one-time treatment, which means it asks for a real time commitment. It also requires medical supervision, because the dose of ultraviolet light has to be calibrated and adjusted as the skin responds. Session schedules, insurance coverage, and the number of treatments needed vary by practice and by patient, so those details are worth confirming directly with the clinic before starting.
Systemic and Biologic Therapy for Moderate to Severe Psoriasis
When psoriasis is moderate to severe, or when topicals and phototherapy have not produced adequate control, treatment shifts to medication that works throughout the body rather than only on the surface. Biologic therapies fall into this category. They target specific parts of the immune response that drive psoriatic inflammation.
Some biologic therapies are delivered as infusions in a clinical setting, which is why certain Denver rheumatology practices list advanced biologic infusion therapy specifically for moderate to severe plaque psoriasis. That detail is a useful reminder that psoriasis care is not confined to dermatology offices alone.
Biologic treatment is not a casual step. It usually requires a confirmed diagnosis, a review of your health history, and ongoing monitoring while you are on the medication. The tradeoff is that for people with extensive or stubborn disease, biologics can achieve a level of control that topicals and light therapy cannot reach.
Comparing the Main Treatment Categories
The table below summarizes how the three main approaches differ in what they involve and who they typically serve. It is a general framework, not a substitute for an individual assessment.
| Approach | What it involves | Typically considered for |
|---|---|---|
| Topical therapy | Corticosteroids and vitamin D analogues applied directly to affected skin | Mild to moderate psoriasis |
| Phototherapy (UVB) | Controlled exposure to ultraviolet B light, delivered in repeated clinical sessions | Slowing excessive skin cell growth when a broader area needs treatment |
| Biologic therapy | Immune-targeting medication, in some cases delivered as a clinical infusion | Moderate to severe plaque psoriasis |
Why Your Care Team May Include More Than One Specialist
Psoriasis is an immune-driven condition, and Denver rheumatology clinics treat moderate to severe plaque psoriasis with biologic infusion therapy. That overlap means a patient’s care may involve both a dermatologist and a rheumatology team, particularly when biologic treatment is part of the plan.
If two providers are involved, the most important thing is communication. Each one should know what the other has prescribed, how the skin is responding, and whether any new symptoms have appeared. Coordinated care prevents duplicated efforts and makes it easier to judge whether a treatment is actually working.
Questions Worth Asking at a Denver Psoriasis Consultation
A first appointment moves faster and produces more useful answers when you arrive with specific questions. Consider bringing this list:
- Which type of psoriasis do I have, and how much of my body is affected?
- Is topical therapy a reasonable starting point for my case?
- Would UVB phototherapy help, and how many sessions would that require?
- At what point would systemic or biologic treatment make sense for me?
- What side effects should I watch for, and which ones warrant a call?
- How long should I continue a treatment before deciding whether it is working?
- Do I need to see another specialist as well?
Write down the answers. Psoriasis treatment unfolds over months and years, and having a record of the original plan makes it much easier to tell whether the approach is holding up.
Choosing a Psoriasis Provider in Denver
Denver has no shortage of options. A national physician directory lists 508 doctors in the Denver area who treat psoriasis, which sounds reassuring until you realize how hard it becomes to compare them. Volume alone does not indicate who is the right fit for a chronic skin condition that requires long-term management.
A few filters narrow the field quickly. Look for a board-certified dermatologist, since psoriasis is a medical skin condition and diagnosis drives everything that follows. Ask whether the practice offers phototherapy on site, because a treatment that requires repeated visits is much easier to sustain when it is not spread across multiple locations. Ask how the practice handles biologic therapy and whether coordination with other specialists is part of the process.
Colorado Dermatology Center, led by board-certified dermatologist Dr. James M. Swinehart, combines more than three decades of clinical expertise with medical, surgical, and cosmetic dermatology, along with clinical research. For patients with psoriasis, that combination matters: an accurate diagnosis, a realistic treatment plan, and access to newer options as they become available. Appointments can be scheduled through the practice website at coloderm.com.
What Realistic Management Looks Like
Psoriasis is chronic. That single fact reshapes what success means. The target is not a permanent cure but sustained control, with fewer flares, less itching and scaling, and skin that stays manageable between appointments.
Getting there depends heavily on consistency. Topicals only work when they are actually applied. Phototherapy only works when sessions are kept. Biologics only work when the schedule is followed. It also depends on honest reporting. If a treatment is irritating your skin, or if you have stopped using it because of cost or convenience, say so at your next visit. There is almost always another option, and a plan you can live with beats a perfect plan you abandon.
Frequently Asked Questions
Is psoriasis curable?
No. Psoriasis is a chronic, inflammatory autoimmune disease, and the precise triggers behind it are not fully known. Because there is no single cause to remove, treatment focuses on controlling symptoms and slowing the rapid skin cell production that creates plaques. With the right combination of topicals, phototherapy, or systemic therapy, most people can achieve meaningful and lasting improvement.
What is the most common topical treatment for psoriasis?
Corticosteroids are the most frequently prescribed medications for treating mild to moderate psoriasis. They reduce inflammation and help calm redness, scaling, and itching. Vitamin D analogues are another common topical option and are often used to help slow excessive cell growth. Topical therapy tends to work best for limited disease and requires consistent application to keep results steady.
Why would a rheumatology clinic treat psoriasis?
Psoriasis is driven by an overactive immune system, and Denver rheumatology practices list advanced biologic infusion therapy for moderate to severe plaque psoriasis. Biologics target specific parts of the immune response rather than just the skin surface. Because of that, care for moderate to severe disease can involve both a dermatologist and a rheumatology team working from the same treatment plan.
Can psoriasis affect the nails, scalp, or other areas?
Yes. Psoriasis can appear on the fingernails and toenails, the scalp, and the soft tissues of the genitals and inside the mouth, in addition to the elbows and knees. Lesions may look like red, scaly, thickened plaques or as pustules, depending on the type. Treatment for these areas can differ from what works on the body.
How do I choose a psoriasis doctor in Denver?
Start with board certification in dermatology, since accurate diagnosis drives every treatment decision that follows. Ask whether the practice offers phototherapy on site and how it handles biologic therapy, because repeated visits are easier when care is coordinated. A national directory lists 508 Denver-area doctors who treat psoriasis, so narrowing by credentials and services is more useful than choosing by volume alone.
Deep Wrinkle Treatment vs. Fine Line Care: What Works
Fine lines and deep wrinkles are not the same problem, and they rarely respond to the same fix. A serum that softens the small creases around your eyes can do almost nothing for a fold that stays visible when your face is completely relaxed. The in-office procedures that smooth a deep groove are usually far more than a fine line needs. Knowing which category a line falls into is the first step toward choosing a treatment that actually helps.
What Separates a Fine Line From a Deep Wrinkle
Dermatologists begin by looking at the skin to assess the lines and creases and what may have caused them, according to Mayo Clinic. That evaluation also includes a conversation about your medical history and what matters most to you, because results, side effects, and recovery time all shape the recommendation.
In practical terms, fine lines are shallow creases. They show up most clearly when the skin moves, such as when you smile, squint, or raise your eyebrows, and they tend to respond to approaches that improve surface texture and tone.
Deep wrinkles are deeper creases that remain visible even when the face is at rest. They often sit in areas where the skin has folded the same way for years, and they can be linked to sun exposure, repeated expression patterns, and the natural loss of support beneath the skin. Because the crease goes deeper, treatments aimed only at the surface rarely produce a satisfying change.
Why the Same Wrinkle Treatments Do Not Work Equally
Depth is what determines how much a treatment can accomplish. Products applied to the surface work on texture, tone, and very fine lines. Procedures that create controlled injury below the surface, or that add volume under a crease, can change the shape of a deeper wrinkle in ways a cream cannot.
That difference shows up clearly in expert commentary. Dermatologist Bittar told CNN Underscored that the best and fastest way to get rid of deep wrinkles is through laser or microcoring treatments, pointing specifically to ablative fractional lasers such as CO2. That statement is about deep wrinkles, and it comes with recovery considerations that a superficial treatment does not carry.
A drugstore night cream and a fractionated CO2 laser should not be compared as if they are competing for the same job. They are not. The useful question is whether the line you want to improve is a surface crease or a structural fold.
Treatments That Help Fine Lines
Fine lines are the category where consistent home care and lighter procedures can make a visible difference. Options that dermatologists commonly discuss include:
- Over-the-counter retinol products, which appear throughout dermatologist-recommended skin care lists for softening the look of lines
- Prescription creams and serums, since Mayo Clinic notes a doctor may prescribe an anti-wrinkle product with prescription-strength retinoids
- Chemical peels, which are included in published lists of wrinkle treatments that work and are used at lighter depths to refresh surface texture
- Microdermabrasion, a surface exfoliation option that appears on wrinkle treatment lists
- Red light therapy, also included among wrinkle treatments in dermatology coverage
- Microneedling at lighter depths, since the same treatment can be adjusted for deeper concerns
The thread connecting these options is consistency. Fine lines build slowly, and the treatments that address them generally work gradually rather than overnight.
Deep Wrinkle Treatment Options That Go Below the Surface
When a line stays visible at rest, treatment usually needs to reach deeper or restore support under the skin. Options dermatologists discuss include:
- Injectables. Botox injections are listed by Mayo Clinic among wrinkle treatments and appear in dermatologist treatment roundups. They are typically used for lines created by muscle movement.
- Fillers. Dermal fillers are included in lists of wrinkle treatments that work and are used where a crease or fold needs volume restored beneath it.
- Microneedling. The same treatment that helps fine lines can be performed at greater depth for more established concerns.
- Chemical peels. A medium or deeper peel is a different procedure from a light refresh peel, even though both carry the same name.
- Ablative fractional lasers. CO2 and similar ablative fractional lasers are the option dermatologists cite as the fastest route for deep wrinkles.
- Microcoring. Named alongside lasers as a leading option for deep wrinkles.
- Dermabrasion and laser skin resurfacing. Both appear on published lists of wrinkle treatment options.
Because these treatments change skin at a deeper level, the conversation about recovery time matters as much as the conversation about results. Ask what the days after treatment look like before you commit.
Fine Lines vs. Deep Wrinkles: Treatment Comparison
The table below organizes common options by where they are performed and what they are typically used for. Depth, settings, and your individual skin determine the final plan, so treat this as a starting point rather than a prescription.
| Treatment | Where it is done | Typically used for |
|---|---|---|
| Retinol and prescription retinoids | Home, or by prescription | Fine lines, texture, and early creases |
| Chemical peels | In office, depth varies | Light peels for fine lines, deeper peels for more established wrinkles |
| Microdermabrasion | In office | Surface texture and fine lines |
| Red light therapy | Varies by provider | Fine lines |
| Microneedling | In office | Fine lines at lighter depths, deeper concerns at greater depths |
| Botox injections | In office | Lines created by muscle movement |
| Dermal fillers | In office | Creases and folds that need volume support |
| Ablative fractional laser such as CO2 | In office | Deep wrinkles |
| Microcoring | In office | Deep wrinkles |
| Dermabrasion and laser skin resurfacing | In office | More established lines and wrinkles |
Creams and Serums: What They Can and Cannot Do
Skin care aisles are full of products marketed with phrases like Botox in a bottle. Those products are pain-free and comparatively inexpensive, and dermatologists note they can deliver results when used consistently and as directed. What they cannot do is match a professional treatment. No topical formula creates the same result as an in-office procedure.
That does not make topicals pointless. Retinol and prescription-strength retinoids are legitimate, dermatologist-recognized options for softening the look of lines and supporting skin over time. They simply work on a different level than a laser, a filler, or an injectable. If a topical is part of your plan, expect results to build gradually, and do not expect it to erase a fold that stays put when your face is still.
How a Dermatologist Chooses Between Treatments
The decision is not based on a product category name. Mayo Clinic describes the process as assessing the lines and creases along with what may have caused them, reviewing medical history, and discussing what is important to you. Results, side effects, and recovery time are all part of that conversation.
It also helps to remember that treatment is a choice, not an obligation. As GoodRx notes, some people choose to treat wrinkles while others embrace them as part of aging, and both choices are valid. If you do decide to treat, the goal is a plan that fits your skin, your budget of time, and how much downtime you are willing to accept.
At Colorado Dermatology Center, board-certified dermatologist Dr. James M. Swinehart brings more than three decades of clinical experience to evaluations like these, and the practice emphasizes personalized care and natural-looking results. An in-person assessment is the only reliable way to know whether a given line is best addressed with a topical, an injectable, a filler, or a resurfacing procedure.
Preventing Fine Lines From Becoming Deep Wrinkles
Sun protection is the strongest lever you have. According to GoodRx, daily sun protection is the best way to prevent photoaging and slow new wrinkles from forming, and it is never too late to start using sunscreen. That single habit does more for long-term skin appearance than any individual product purchase.
Beyond sunscreen, the habits that support any treatment plan are consistent use of whatever your dermatologist recommends, realistic expectations about timing, and regular skin checks. Fine lines are easier to influence early than late, but starting today still counts.
Frequently Asked Questions
Do over-the-counter creams really work on deep wrinkles?
They can soften the look of lines and improve texture, especially when they contain retinol or a prescription-strength retinoid. What they cannot do is match a professional procedure. Dermatologists are clear that no topical formula produces the same result as an in-office treatment, so a cream is best viewed as support rather than a fix for a deep fold.
Is Botox or a filler the better choice for deep wrinkles?
They address different problems. Botox injections are used for lines created by muscle movement, while fillers are used where a crease or fold needs volume restored beneath the skin. Many treatment plans combine both, because a deep line often has a movement component and a volume component. A dermatologist can tell you which one fits the line you want to improve.
What is the fastest way to get rid of deep wrinkles?
Dermatologists point to procedures rather than products. One dermatologist told CNN Underscored that the best and fastest route for deep wrinkles is laser or microcoring treatment, specifically ablative fractional lasers such as CO2. These are in-office procedures with real recovery considerations, so the tradeoff for speed is downtime. Discuss timing with your dermatologist before scheduling around work or an event.
How do I know which wrinkle treatment is right for me?
It starts with an evaluation. Mayo Clinic describes the process as assessing the lines and creases and what may have caused them, then reviewing your medical history and what matters to you. Results, side effects, and recovery time all factor into the recommendation. The depth of the line, your skin, and your schedule usually narrow the list quickly.
Can fine lines be prevented from turning into deep wrinkles?
Sun protection is the strongest lever. Daily sunscreen use is the best way to prevent photoaging and slow new wrinkles from forming, according to GoodRx, and it is never too late to begin. Retinoids and consistent skin care help over time as well. None of these habits erase existing deep lines, but they can slow how quickly new ones develop.
Laser Acne Scar Treatment Price: What Denver Patients Pay
Acne scarring has a way of outlasting the breakouts that caused it, and the treatments that smooth it out are rarely inexpensive. Published cost data for laser acne scar removal generally lands between $200 and $3,000 per treatment, and the wider market stretches from $100 to $5,000 or more once scar size, scar count, and the number of laser sessions are factored in. Denver quotes sit inside those national bands rather than outside them, so the useful question is not what the price is in the abstract. It is what a specific number covers, and how many times you will be asked to pay it.
What follows is the published pricing picture, the arithmetic that turns a per-session quote into a real total, and the questions that separate a clear written estimate from a vague one.
Why Laser Acne Scar Prices Cover Such a Wide Range
Four variables do most of the work. The first is surface area. Published figures note that laser scar removal costs vary based on the size and number of scars being treated, which is why a small area treated with a single pass and a full-face resurfacing do not belong in the same price conversation. The second is technology, since the quoted range of $200 to $3,000 or more depends partly on the device being used and the size of the session. The third is the provider, because laser removal of acne scars can cost thousands of dollars, particularly when a large area of skin is treated by specialist physicians. The fourth is repetition, and it is the one patients underestimate most often.
- Area treated, from a single cheek to the full face and neck
- Laser technology and whether it is ablative or non-ablative
- Provider type and clinical setting
- Number of sessions required to reach the goal
- Whether combination treatments such as fillers or peels are added
What Published Laser Acne Scar Prices Actually Look Like
Published figures are not quotes, and none of the numbers below are Denver-specific. They are useful as a reference frame, because they show where a fair quote should fall once you know what is being treated.
| Source context | Treatment | Reported price |
|---|---|---|
| National range (GoodRx) | Laser acne scar removal | $200 to $3,000 |
| National range (CareCredit) | Laser scar removal | $100 to $5,000 or more |
| National average out of pocket, October 2019 (Healthline) | Ablative laser skin resurfacing | Around $2,000 |
| National average out of pocket, October 2019 (Healthline) | Non-ablative laser skin resurfacing | Around $1,100 |
| New York City | Single laser acne scar session | $1,500 to $3,500 |
| Encino | Laser acne scar treatment, per session | $800 to $3,000 |
| Los Angeles | Pixel laser, medium area | $349 |
| Knoxville | Fractional laser skin resurfacing | Starting around $300 to $350 |
| Patient-reported (Reddit) | Aggressive CO2 laser | $1,200 |
| Patient-reported (Reddit) | Bellafill | $1,200 |
The spread is enormous, and the gap between the low end and the high end is explained by area and technology rather than by any single market being uniquely expensive. A $300 fractional resurfacing starting price and a $3,500 single session in a major metro describe very different amounts of treated skin.
Session Count Is the Number That Decides Your Total
Published guidance indicates that treatment generally requires two to five laser sessions. That single sentence changes how you should read every quote you receive. A figure of $900 becomes $1,800 to $4,500 once you multiply it across the likely treatment plan, before any maintenance sessions or add-on treatments enter the picture.
Here is the arithmetic using published ranges, offered as an illustration and not as a Denver quote. If a session is priced at the lower end of a typical published band, three sessions stay modest. If a session is priced near the top of the published band for a large area treated by a specialist physician, the same three sessions reach the thousands of dollars that the national data describes. Ask any practice for the projected number of sessions in writing before you commit, because the per-session number alone tells you very little.
Ablative Versus Non-Ablative: The Price Split
The clearest structural divide in published cost data is between ablative and non-ablative laser skin resurfacing. As of an October 2019 industry figure, the average out-of-pocket cost sat around $2,000 for ablative treatments and around $1,100 for non-ablative treatments. That roughly twofold gap reflects the intensity of the procedure and the recovery it involves.
That published average is dated, so treat it as a historical benchmark rather than a current rate. It is still useful for one purpose: if a quote you receive sits far outside that relationship between ablative and non-ablative pricing, it is worth asking exactly which device is being used and why the number falls where it does. Verify current pricing directly with the practice before you plan a budget around any published average.
Non-Laser Options and What They Add to the Bill
Laser treatment is frequently only part of a plan. Published pricing for related procedures includes radiofrequency microneedling at roughly $600 to $1,200 per session and chemical peels at roughly $150 to $400 per peel. One patient reported spending $1,200 on an aggressive CO2 laser treatment and another $1,200 on Bellafill within the same treatment period, which shows how quickly a combination approach doubles the total.
Some clinics publish narrower, device-specific pricing. One Los Angeles provider lists a free consultation alongside Pixel laser treatment at $349 for a medium area, $399 for a medium area plus the neck, $499 for a large area, and higher for an extra-large area. Another clinic publishes smaller line items, including a deep pore treatment at $290, an acne chemical peel at $150, a pigmentation laser at $250, and a pigmentation chemical peel at $150. These figures show what a fully itemized price list looks like, which is the standard you should hold a Denver quote to.
Insurance Rarely Pays for Acne Scar Laser Treatment
Acne scar removal is treated as a cosmetic procedure, and cosmetic procedures are not covered by medical insurance. That means the published ranges above describe money that comes out of your pocket, not a negotiated rate an insurer absorbs.
If you plan to use a health savings account or flexible spending account, confirm eligibility with your plan administrator before scheduling. The rules are set by the plan and by tax guidance, not by the dermatology practice, so a clinic cannot tell you whether your specific account will reimburse the expense. Get that answer in writing from the account administrator first.
Why Denver Quotes Differ From One Practice to the Next
Market pricing varies. In New York City, patients can expect to pay between $1,500 and $3,500 for a single session of laser acne scar removal, which reflects that market rather than a universal standard. Denver is not New York, and it is not a small rural market either, so quotes tend to fall in the middle of the published national bands.
Within a single metro area, differences come down to which devices a practice owns, whether the treating clinician is a specialist physician, how the practice bundles consultations and follow-up visits, and how much of the face or body the quote actually covers. Two quotes for the same dollar figure can describe completely different amounts of treatment. That is why comparing practices means comparing scope, not just numbers.
Questions to Ask Before You Pay a Deposit
A short, direct list of questions will surface almost every hidden cost in a laser acne scar treatment plan.
- Which specific laser or device will be used, and is it ablative or non-ablative?
- Exactly what area does the quoted price cover, and is the neck or jawline included?
- How many sessions are recommended, and is that number guaranteed in writing?
- Is the consultation fee separate, and is it credited toward treatment?
- What is included in follow-up care, and what is billed separately?
- What is the total estimated cost if the full recommended plan is completed?
- Are there payment plan options, and what are the terms?
How to Build a Realistic Acne Scar Budget
Start with a consultation rather than a price list, because published ranges cannot tell you which category of treatment your scarring falls into. Once you have a recommended plan, multiply the per-session price by the recommended session count, then add any separate consultation, topical, or filler costs. Compare that total against the published bands in this article. If the total lands within the $200 to $3,000 per-session range across two to five sessions, the quote is consistent with the national data. If it falls far outside, ask what is driving the difference before you commit.
It also helps to decide in advance how much improvement you are paying for. Published sources list questions such as whether acne scars can be removed completely, whether laser treatment is worth it, and whether laser gets rid of acne scarring entirely as open questions rather than settled ones. A realistic budget is built around measurable improvement in texture and depth, not a promise of flawless skin, and any practice that frames it that way is being straight with you.
Frequently Asked Questions
Does insurance cover laser acne scar treatment?
No. Acne scar removal is classified as a cosmetic procedure, and cosmetic procedures are not covered by medical insurance. Published pricing therefore reflects out-of-pocket cost. Some national averages put ablative laser skin resurfacing around $2,000 and non-ablative around $1,100 as of an October 2019 commercial figure, so plan for the full amount to come from you.
How many laser sessions will I actually need?
Published guidance indicates that treatment generally requires two to five laser sessions, though the exact number depends on scar depth, scar type, the area being treated, and the device used. Because session count multiplies directly into your total cost, ask any practice to put the recommended number of sessions in writing before you schedule the first one.
Why are quotes from different practices so far apart?
The variance usually comes from scope and technology rather than arbitrary pricing. A single session in New York City can run $1,500 to $3,500, while other published listings start around $300 to $350 for fractional resurfacing. Different devices, different treated areas, and different clinician types all move the number, so compare what each quote actually includes.
Can laser treatment remove acne scars completely?
Whether acne scars can be removed completely remains an open question in published consumer sources rather than a settled outcome. Lasers are used to improve the appearance and texture of scarring, and results vary by scar type and skin. Treat significant improvement as the realistic goal, and ask your dermatologist what degree of change is reasonable for your specific scarring.
What should a written acne scar quote include?
A useful quote names the device, states whether treatment is ablative or non-ablative, defines the treated area, lists the recommended number of sessions, and separates consultation fees from procedure fees. Itemized clinic price lists show how this looks in practice, with individual treatments priced separately. Ask for the total estimated cost of the complete plan, not just one session.
Basal Cell Carcinoma on the Nose: Why MOHS Surgery Works
A basal cell carcinoma on the nose creates two problems at once. The first is the cancer itself. The second is that the nose sits in the middle of the face, covered in thin skin stretched tightly over cartilage, where any removed tissue shows. Treatment has to clear the tumor completely while leaving the nose as close to its original shape and appearance as possible. MOHS surgery is often recommended for basal cell carcinomas on the nose, along with the eyelids, lips, ears, scalp, hands, and other areas where preserving healthy tissue matters.
Why the Nose Is a Challenging Place for Skin Cancer
The nose is a high-traffic area for sun exposure, which is part of why basal cell carcinoma so often appears there. A dermatologist can spot a lesion near the tip of the nose that carries a pearly, slightly raised border and would likely bleed easily. That description matches the classic appearance of nasal basal cell carcinoma.
The anatomy makes treatment harder than the diagnosis. Nasal skin is thin and moves with every facial expression. Beneath it lies cartilage that gives the nose its shape. Remove too much tissue, or remove it in the wrong place, and the result can be a dent, a flattened edge, or a pulled nostril. Because of that, the goal in treating a nasal basal cell carcinoma is tumor-free margins with the smallest possible defect.
What Basal Cell Carcinoma on the Nose Looks Like
Basal cell carcinoma is easy to overlook because it rarely announces itself. Early signs on the face include:
- A pearly or shiny bump
- A sore that bleeds or crusts
- A flat, scaly patch
- A scar-like area
On the nose specifically, the lesion may appear as a small raised bump with a translucent or pearly rim. It may bleed when you wash your face or towel off, then seem to heal, then bleed again. Some basal cell carcinomas look like a dry patch of skin or a pimple that never quite goes away. Others look like a small scar that appeared without any injury to explain it.
This variety is why a visual inspection alone is not enough. A dermatologist may examine the spot with a dermatoscope and, if it looks suspicious, take a biopsy. The biopsy is what confirms basal cell carcinoma and rules out other conditions that can look similar on the nose.
Why Treatment Choice Matters More on the Nose
On the back or the shoulder, a slightly larger excision scar is easy to accept. On the nose, every millimeter counts. The tissue there is unforgiving of guesswork, and a repair that distorts the nasal tip or narrows a nostril is a permanent cosmetic and sometimes functional problem.
That is the core reason treatment selection matters so much for this location. Some treatment methods destroy tissue without mapping exactly where the cancer ends. Others leave the surgeon uncertain whether the margins were truly clear, which can mean a second procedure later. For a tumor sitting on the nose, that uncertainty is worth avoiding.
Why MOHS Is Often Recommended
MOHS micrographic surgery is designed for exactly this situation. Instead of removing the visible tumor with a wide margin of normal-looking skin, the MOHS surgeon removes the tumor and then examines the complete outer edge of that tissue under a microscope before deciding whether more needs to come out.
The practical benefit is precision. If cancer cells are found at one spot on the margin, the surgeon goes back for another thin layer at that spot only, not across the whole wound. If the margin is clear, the surgery stops. Nothing healthy is sacrificed beyond what is necessary to get a clean result.
For a basal cell carcinoma on the nose, that tissue-sparing quality is the main argument in favor of MOHS. It also gives the surgeon a mapped, documented answer about whether the tumor was fully removed, which reduces the chance of a surprise recurrence down the road.
What Happens During MOHS Surgery
- The area around the tumor is numbed with a local anesthetic, so you stay awake during the procedure.
- The surgeon removes the visible tumor along with a thin layer of surrounding tissue.
- The tissue is mapped, marked, and processed so the entire outer margin can be examined under a microscope.
- The surgeon reviews the slides. If cancer is still present at any point on the margin, another thin layer is removed from that exact spot.
- Steps three and four repeat until the margin is clear of cancer cells.
- Once the tumor is fully removed, a defect is left behind, and the surgeon repairs it. On the nose, that repair may be a simple closure, a flap, or a graft, depending on the size and depth of the defect.
Because each round of margin checking takes time, MOHS is a longer appointment than many other skin cancer removals. The trade-off is that the surgeon knows the margins are clear before closing the wound, rather than waiting for a pathology report days later.
Other Treatment Options That May Be Considered
MOHS is not the only option for basal cell carcinoma on the nose, and it is not right for every tumor. Cryosurgery, which destroys tissue with cold, has been used for multiple basal cell carcinomas on the nose, and case reports on that approach exist in the medical literature. Radiotherapy has also been recommended for basal cell carcinoma of the nose in certain settings, though published reviews note wide variation in the techniques used and the doses prescribed.
Other factors shape the decision, including the size and depth of the tumor, how it looks under the microscope, and the condition of the surrounding skin. Ask your dermatologist which options apply to your specific lesion and why one is preferred over another in your case.
Recovery and Scarring After Nasal Surgery
Any treatment that removes skin cancer from the nose leaves a scar. The question is what kind of scar and how noticeable it will be. A small, superficial tumor closed in a straight line looks very different from a larger tumor repaired with a flap or graft that borrows tissue from nearby.
Healing timelines vary from person to person, and the final appearance of a scar can take months to settle. Your surgeon is the best source for a realistic picture of what your repair will look like at three weeks, three months, and beyond. Follow the aftercare instructions you are given, keep the area protected from sun, and attend your follow-up visits so healing can be monitored.
Choosing Care for a Nasal Basal Cell Carcinoma
Before committing to a treatment plan, it helps to ask a few direct questions:
- What type of basal cell carcinoma is this, based on the biopsy?
- Why is this treatment recommended over the alternatives for my nose?
- How will the wound be repaired, and who performs the repair?
- What should I expect during healing, and what signs would mean I should call?
- How often should I be checked afterward for new skin cancers?
Colorado Dermatology Center is a South Denver dermatology practice led by board-certified dermatologist Dr. James M. Swinehart, whose clinical experience spans more than three decades. The practice focuses on medical, surgical, and cosmetic dermatology, with particular emphasis on skin cancer treatment including MOHS surgery. Patients looking for evaluation of a suspicious spot on the nose can schedule a consultation to have it examined and, if needed, biopsied.
Frequently Asked Questions
What does basal cell carcinoma on the nose look like?
It often appears as a pearly or shiny bump, a sore that bleeds or crusts and then seems to heal, a flat scaly patch, or a scar-like area. On the nose, a lesion may have a pearly, slightly raised border and bleed easily. Any spot that persists, changes, or bleeds repeatedly should be examined by a dermatologist.
Why is MOHS often recommended for basal cell carcinoma on the nose?
The nose has thin skin over cartilage, so removing too much tissue can change its shape. MOHS surgery examines the entire outer margin of the removed tissue under a microscope, and additional layers are taken only where cancer remains. That gives the surgeon margin control while sparing as much healthy nasal tissue as possible.
Are there alternatives to MOHS for nasal basal cell carcinoma?
Yes. Cryosurgery has been used for multiple basal cell carcinomas on the nose, and radiotherapy has been recommended for nasal basal cell carcinoma in certain situations, with wide variation in techniques and doses across published reports. Which option fits depends on the tumor and the surrounding skin, so discuss the trade-offs with your dermatologist.
How is the wound repaired after the tumor is removed?
Once the margins are clear, a defect remains where the tumor was. The surgeon repairs it based on size, depth, and location on the nose. Options include closing the skin directly, using a flap of nearby tissue, or placing a graft. Your surgeon can explain which approach is planned for your case.
Free Skin Cancer Screenings Near Denver: How to Find One
If you live in the Denver area and want a skin check without paying out of pocket, free skin cancer screenings do exist. The catch is that they rarely happen at the same place on a predictable schedule. Most free screenings come from national programs that travel from city to city, hospital outreach events, and dermatology practices that open a limited number of no-cost appointments.
Finding one takes some legwork, but the search follows a repeatable pattern. The tools and phone calls below are the ones that reliably lead people to a free skin check, along with what to expect at the appointment and what to do if the exam turns up something that needs a closer look.
Why a Professional Skin Check Is Worth Pursuing
One in five people of all skin colors in the United States will develop skin cancer, according to the American Academy of Dermatology. The AAD recommends an annual total-body skin cancer exam performed by a dermatology professional, because skin cancer caught early is generally easier to treat.
A free screening is not the same thing as that annual exam, and it is not a diagnosis. It is a first look by a trained professional, meant to flag spots that deserve closer attention. For anyone who has put off a check because of cost, an insurance gap, or simply not knowing where to go, a free event removes most of those barriers.
Use the AAD Screening Map to Find Events by State
The American Academy of Dermatology maintains a free skin cancer check locator built around a national map. Clicking on your state shows the scheduled free skin cancer checks currently listed there, which makes it the fastest starting point for anyone typing a search like free skin cancer screening near me.
Because these are scheduled events rather than permanent clinics, listings change throughout the year. Check the map before assuming nothing is happening in Colorado, and check it again if the calendar looks empty the first time. Events are often added closer to their date.
How to work the screening map efficiently
- Open the AAD find-a-screening page and select Colorado.
- Write down the dates, locations, and any eligibility notes attached to each listing.
- Contact the sponsoring organization directly to confirm the event is still on before you travel.
- Recheck the map every few weeks, since new screenings get posted through the year.
Destination Healthy Skin, the Skin Cancer Foundation’s Mobile Program
Destination Healthy Skin is a mobile screening and education program run by The Skin Cancer Foundation. A 38-foot RV travels the country with two private exam rooms inside, staffed by volunteer dermatology providers who perform free full-body skin exams. The program offers free exams performed by licensed dermatology professionals, and no appointment is necessary at the mobile unit.
The program’s numbers show how much a mobile clinic can handle. Since its launch, the team has provided 35,000 free skin cancer screenings, identified more than 14,200 potential skin cancers and precancers, including 699 suspected melanomas, and distributed free educational materials and sun protection products to more than 119,000 people.
The tour schedule shifts by city and season, so the practical step is to visit the Destination Healthy Skin page and see whether a Colorado stop is planned during the current tour.
Ask Denver Hospitals and Health Systems About Outreach Screenings
The Prevent Cancer Foundation points people without insurance toward community resources for free and low-cost screening. Its guidance is straightforward: contact your local hospital or health care facility and ask whether routine cancer screening, testing, and vaccinations are offered through their foundations or outreach programs, including mobile testing.
That phone call is worth making in the Denver area. Hospital foundations, cancer resource centers, and community health events frequently host screenings that never surface in a general web search. When you call, ask specifically about skin cancer screening events, whether registration is required, and whether there is an age or eligibility requirement.
Dermatology Practices That Offer Free Screenings to New Patients
Some dermatology practices set aside free skin cancer screenings for new patients as a way of introducing themselves to the community. These offers usually come with conditions. The screening is often valid for new patients only, at participating locations, and you typically need to book rather than walk in.
If you call a practice near you, ask three questions before scheduling:
- Is the screening free for new patients, and at which locations?
- What does the exam include?
- Is there any cost if something needs a closer look afterward?
Getting those answers up front prevents surprises. A free screening offer is not the same as free follow-up care, and a biopsy or treatment is normally billed separately from the screening itself.
What Happens During a Free Skin Cancer Screening
Free screenings are shorter and more limited than a full dermatology visit, and expectations vary by event. The general pattern looks like this:
- The exam is a full-body skin check focused on moles, spots, and lesions that look unusual.
- At the larger national programs, licensed dermatology professionals perform the exams.
- Some community clinics report screenings that last about 10 minutes.
- Some events are walk-in only, while others ask you to sign up online in advance.
- Some clinics set eligibility rules, such as being 18 or older or not having had a professional skin exam within a certain period.
The table below compares the main routes to a free screening so you can decide where to start.
| Where to look | What it offers | What to verify first |
|---|---|---|
| AAD find-a-screening map | State-by-state list of scheduled free skin cancer checks | Current dates and eligibility notes, since listings change through the year |
| Destination Healthy Skin | Free full-body exams in a 38-foot mobile unit with two private exam rooms; no appointment necessary | Whether the tour is stopping near Denver during the current season |
| Hospital and health system outreach | Screenings offered through foundations or community programs, sometimes through mobile testing | Whether skin cancer screening is included and whether registration is required |
| Dermatology practice offers | Free screenings for new patients at participating locations | Whether the free exam covers only the initial check or includes follow-up |
Questions to Ask When You Call About an Event
A short phone call can save a wasted trip. Ask whether the screening is still scheduled, whether you need an appointment, what age or insurance rules apply, and who performs the exams. If you have specific spots that worry you, say so when you call and ask whether the screening format can address them or whether you should book a full dermatology visit instead. It also helps to bring a list of the spots that concern you, along with your personal and family history of skin cancer, so the examiner has context.
If the Screening Finds Something Suspicious
Screening programs are built to flag problems, not to treat them. The Skin Cancer Foundation’s mobile program, for instance, reports identifying thousands of potential skin cancers and precancers over its history, along with hundreds of suspected melanomas. All of those findings needed follow-up with a dermatologist.
That follow-up is where a diagnosis gets made. If a screening professional recommends further evaluation, the next step is usually a dermatology appointment for a closer exam and, if warranted, a biopsy. In the Denver area, Colorado Dermatology Center in South Denver provides that kind of follow-up care. The practice is led by board-certified dermatologist Dr. James M. Swinehart and specializes in skin cancer treatment, including MOHS micrographic surgery for certain skin cancers. A free screening gives you a first look; a dermatology practice handles everything that comes after it.
Insurance, Cost, and Coverage Questions
If you have health insurance, most private insurance companies as well as Medicare and Medicaid cover the cost of certain routine cancer screenings, according to the Prevent Cancer Foundation. Coverage rules differ from plan to plan, so confirm your specific benefits with your insurer before scheduling a diagnostic visit.
If you do not have insurance, the same organization recommends starting with community resources, your local hospital, or a health care facility’s outreach program. Free screening events are the other route, and they exist precisely for people who would otherwise skip a check.
Frequently Asked Questions
Do I need an appointment for a free skin cancer screening?
It depends on the event. The Skin Cancer Foundation’s Destination Healthy Skin mobile unit states that no appointment is necessary, and walk-in screenings are common at health fairs and community events. Other programs, including some hospital events and new-patient offers at dermatology practices, ask you to register or book a time in advance. Always confirm with the sponsoring organization before you go.
Who is eligible for a free skin cancer screening?
Eligibility rules are set by each sponsoring organization, so they vary. Some free clinics are open to adults 18 years or older, and some ask that participants not have had a professional skin exam within a certain period. Others are open to anyone who shows up. Check the event listing or call ahead to confirm the requirements for the specific screening you plan to attend.
What happens if the screening finds something suspicious?
A screening is a first look, not a diagnosis. If the professional examining you sees a spot that needs closer attention, they will recommend a follow-up visit with a dermatologist. At that appointment, the dermatologist may examine the area in more detail and, if needed, perform a biopsy to determine whether it is skin cancer.
Where should I start looking for free screenings near Denver?
Start with the American Academy of Dermatology’s find-a-screening map, which lists scheduled free skin cancer checks by state. Next, check The Skin Cancer Foundation’s Destination Healthy Skin tour schedule and call local hospital foundations to ask about outreach events. Dermatology practices that offer free new-patient screenings are another option worth calling directly.
Is a free skin screening as thorough as a dermatologist visit?
No. Free screenings are shorter by design and focus on spotting anything that looks concerning, with some community clinics reporting exams of about 10 minutes. A full dermatology visit includes a complete history, a total-body exam, and the ability to biopsy or treat on the spot when needed. The American Academy of Dermatology still recommends an annual total-body exam by a dermatology professional.
Finding a Dermatologist in Denver: Medical, Surgical and Cosmetic Care
Denver has no shortage of dermatology offices. A quick search turns up hospital-based clinics, large multi-state groups, and small physician-owned practices, and the list keeps going. That variety is good news for patients, but it makes one question harder to answer: which type of practice fits the problem sitting on your skin right now?
Most people do not start out knowing whether their concern is medical, surgical, or cosmetic. A changing mole sounds serious. A scar left over from teenage acne sounds cosmetic. A patch of eczema flares and then settles. In practice those categories overlap constantly, and a practice that handles all three under one roof saves patients from being handed off across town every time a new issue appears.
What Care Under One Roof Actually Means
Medical, surgical, and cosmetic dermatology are usually described as separate fields because they developed separately. Medical dermatology deals with disease: acne, eczema, psoriasis, and the evaluation of suspicious spots. Surgical dermatology removes skin cancers and other growths. Cosmetic dermatology addresses appearance, including scarring, aging skin, thinning hair, and unwanted fat.
The divisions blur the moment a real patient walks in. Someone treated for skin cancer on the nose may later want the scar revised. Someone whose acne clears with medication may want the pitting left behind smoothed out. Someone whose hair is thinning may need a medical workup before any restoration is considered. When those services sit in one office, the history stays with one team instead of starting over at each visit.
| Category | Typical concerns | Typical approach |
|---|---|---|
| Medical | Acne, eczema, psoriasis, skin cancer evaluation | Diagnosis, prescription treatment, long-term management |
| Surgical | Basal cell, squamous cell, and melanoma skin cancers | Surgical removal, including Mohs micrographic surgery |
| Cosmetic | Acne scarring, aging skin, thinning hair, unwanted fat | Acne scar revision, facial rejuvenation, hair restoration, tumescent liposuction, body contouring |
Colorado Dermatology Center in Denver was built around that combined model. The practice is led by board-certified dermatologist Dr. James M. Swinehart and brings together medical, surgical, and cosmetic services plus clinical research trials in a single location.
Medical Dermatology: The Reason Most People Call
General dermatology fills most appointment slots at any Denver practice, and for good reason. Skin conditions are common, chronic, and often uncomfortable. Acne, eczema, and psoriasis are three of the most frequent reasons patients book a first visit, and each one tends to need a plan rather than a single prescription.
Acne, Eczema, and Psoriasis
Acne responds to a mix of topical and oral treatments, and results usually depend on consistency over months rather than weeks. Eczema and psoriasis are long-term inflammatory conditions that flare and settle, so treatment often means finding a maintenance routine that keeps skin calm between episodes. A dermatologist adjusts that routine as skin changes with season, stress, and age.
Denver’s dry air and high altitude affect how skin behaves, which is one practical reason to see a local dermatologist rather than rely on generic advice. A clinician who treats Colorado patients every day knows how quickly moisture loss and sun exposure can change a skin condition’s course.
Skin Cancer Screening and Diagnosis
Skin cancer evaluation is a core part of medical dermatology, and it is the area where a routine appointment can matter most. Basal cell carcinoma, squamous cell carcinoma, and melanoma are the three main types, and they can look like nothing more than a new spot, a sore that will not heal, or a mole that has changed shape or color.
An examination gives a dermatologist the chance to look at the whole skin surface, not just the spot a patient noticed. Suspicious lesions can be evaluated and, when needed, scheduled for removal. Because the same practice handles both the diagnosis and the surgery, there is no gap between hearing the word cancer and getting a plan for it.
Surgical Dermatology and Mohs Micrographic Surgery
Surgical dermatology covers the removal of skin cancers and other growths, and the technique chosen depends on the lesion’s type, size, and location. Mohs micrographic surgery is one of the specialized options available for treating skin cancer, and it is offered by a limited number of practices. Patients who need it often find they would otherwise be referred to a separate surgical center.
Having surgery available in the same practice as general dermatology changes the experience for patients. The dermatologist who checks your skin is also the person who knows what was removed before, where the scar sits, and how the area has healed since. That continuity matters most for patients with a history of skin cancer, who are often monitored closely for years.
Why Surgical and Medical Care Work Better Together
- Follow-up after removal happens with the same team that performed the procedure.
- Scar care and cosmetic revision can be planned early rather than arranged separately.
- Patients with a skin cancer history can be tracked over time in one record.
- Referrals across town become the exception rather than the default.
Cosmetic Dermatology Without the Hard Sell
Cosmetic dermatology works best when it stays clinical. That means starting with the skin you actually have, setting realistic expectations, and choosing treatments that address the underlying cause of a concern rather than masking it. It also means saying no to a treatment that will not deliver meaningful results.
Acne Scar Revision and Facial Rejuvenation
Acne scarring is one of the more technical cosmetic problems because scars come in different forms and respond to different techniques. Revision work focuses on softening texture and depth rather than erasing scars entirely. Facial rejuvenation follows a similar principle: the goal is a rested version of your own face, not a different one.
Because the same practice manages active acne, patients can move from clearing breakouts to treating what they left behind without switching providers. That sequence matters, since treating scars while acne is still active rarely produces the result patients are hoping for.
Hair Restoration, Liposuction, and Body Contouring
Hair restoration sits at the intersection of medical and cosmetic care. Thinning hair can have several causes, and a dermatologist can evaluate the scalp before recommending a restoration approach. Tumescent liposuction and body contouring address stubborn fat that does not respond to diet and exercise, and they are procedures many general dermatology offices do not offer at all.
Colorado Dermatology Center’s range is a big part of what makes it unusual in the Denver market. Acne scar revision, hair restoration, facial rejuvenation, body contouring, and tumescent liposuction are all handled in-house, which means patients can assemble a treatment plan instead of piecing one together from several offices.
Clinical Research Trials and What They Mean for Patients
Some dermatology practices participate in clinical research, and that involvement shapes how the whole office thinks. Trial work keeps a team current on emerging treatments and protocols. It also creates an option for patients who have not responded well to standard care and want to know whether a study is a reasonable next step.
Participation in a trial is always voluntary and never a substitute for routine care. If you are curious about whether research is relevant to your condition, ask during your appointment and expect a clear explanation of what the study involves before deciding anything.
How to Choose a Dermatologist in Denver
The Denver metro area offers several kinds of practices, and the right choice depends on what you need. Hospital-based clinics, including dermatology services at Denver Health and UCHealth’s Cherry Creek clinic, tend to be part of larger health systems. Larger groups such as U.S. Dermatology Partners and Epiphany Dermatology, which has a Cherry Creek location, offer general, cosmetic, and skin cancer care, with some providing teledermatology. Independent practices round out the list, including physician-owned and boutique offices.
A few practical questions will narrow the field quickly:
- Does the practice handle the specific concern you have, or will you be referred elsewhere?
- Is Mohs surgery available in-house if a skin cancer needs it?
- Are medical and cosmetic services offered in the same location?
- Which insurance plans are accepted, and what happens if yours is not on the list?
- How soon can you be seen, and how far out are follow-up appointments scheduled?
Hours vary widely from office to office, and some Denver clinics close over the lunch hour, so confirm scheduling details directly with the practice rather than assuming. Cost is another detail to verify up front. Prices for dermatology visits and procedures are not standardized, and coverage depends on your plan and whether a visit is considered medical or cosmetic.
What to Expect at a First Visit
An initial appointment usually starts with a conversation about what brought you in, your history, and any treatments you have already tried. A skin examination may follow, and it can cover more than the spot you flagged. From there you should leave with either a diagnosis, a plan, or a clear next step such as a biopsy or a follow-up in a set number of weeks.
Bring a list of medications and any previous biopsy or pathology reports if you have them. Photographs of a spot that has changed are genuinely useful, especially if the lesion looks less obvious on the day of your visit. Write down your questions beforehand so they do not get lost halfway through the appointment.
Frequently Asked Questions
Do I need a referral to see a dermatologist in Denver?
It depends on your insurance plan. Some plans require a referral from a primary care provider before they will cover a dermatology visit, while others allow you to book directly. Some practices also ask for a referral for certain procedures. Call your insurance company first, then confirm with the dermatology office when you schedule so there are no surprises afterward.
Can I see a dermatologist in Denver without insurance?
Many practices see self-pay patients, though policies differ from office to office. Without insurance, you will typically be responsible for the full visit or procedure cost, so ask for pricing before you book. Keep in mind that medical visits and cosmetic treatments are usually priced differently, and some practices require payment at the time of service.
How long does it take to get a dermatology appointment?
Wait times vary by practice, season, and urgency. Routine cosmetic consultations can often be scheduled sooner than general medical appointments, while a concerning lesion may justify a faster slot if you explain the situation when you call. If you are told the next opening is months away, ask to be placed on a cancellation list.
Is Mohs surgery performed in the office?
Mohs micrographic surgery is a specialized technique used to remove certain skin cancers, and it is available only at practices with the training and equipment to perform it. Ask during your consultation where the procedure would take place, who performs it, and how follow-up and scar care are handled afterward.
Can medical and cosmetic concerns be treated in the same visit?
Often yes, but it is worth planning ahead. Bring both concerns to your appointment and let the staff know when you schedule, since a full skin examination plus a cosmetic consultation may need extra time. Be aware that insurance generally covers medical treatment but not cosmetic procedures, so the two may be billed separately.
Choosing a dermatologist in Denver comes down to fit: the right expertise for your concern, a clear plan you understand, and a practice you can return to as your skin changes. When medical, surgical, and cosmetic care live in one office, that continuity is easier to maintain, whether you are managing a chronic condition, following up on a skin cancer diagnosis, or finally addressing scarring you have lived with for years.
Wrinkle Treatment in Denver: Injectables, Fillers, and What Works
Denver has no shortage of places offering to smooth a line or two. Search for wrinkle treatment in Denver and you will find medspas, plastic surgery offices, and dermatology practices, each with a slightly different philosophy and a different menu. The harder question is not where to go. It is which treatment matches the wrinkles you actually have. A forehead line created by years of muscle movement behaves nothing like a fold caused by lost volume, and a plan built for one will disappoint you if your skin needs the other. What follows is a practical way to sort the options, from injectable wrinkle relaxers and dermal fillers to peels, dermabrasion, and laser resurfacing.
Start With the Type of Wrinkle You Have
Wrinkles are not one condition. Dynamic lines appear when muscles pull the skin into a crease, which is why they show up first in the forehead, between the brows, and at the outer corners of the eyes. Static lines stay visible even when your face is at rest, and they usually reflect volume loss, thinning collagen, and cumulative sun exposure. Many people have both at once, which is why a single product rarely solves everything.
Sun exposure in Colorado shows up as more than lines. Uneven pigmentation, sun damage, and melasma tend to appear alongside fine wrinkling, and several Denver treatment menus group these concerns together for that reason. One local package marketed as a dual-action rejuvenation treatment is specifically described as formulated for people dealing with melasma and sun damage. That grouping is not marketing noise. Pigment and texture often respond to the same resurfacing tools.
Before choosing a treatment, figure out whether your lines are mostly movement-driven, mostly volume-driven, mostly texture and pigment, or a mix. That answer narrows your list to two or three realistic options.
Injectable Wrinkle Relaxers: Botox and Dysport
Injectable neuromodulators are the most familiar wrinkle treatment, and in Denver they are widely available under brand names including Botox and Dysport. Providers who specialize in advanced wrinkle relaxers describe their goal as softening lines, refreshing the skin, and restoring confidence rather than freezing expression. The mechanism is straightforward: the injectable relaxes the specific muscles that fold the skin, which reduces how deeply those creases set over time.
What relaxers handle well
Movement-based lines in the upper face are the classic target: horizontal forehead lines, the vertical lines between the brows, and crow’s feet. Because the treatment works on muscle activity rather than on the skin surface, it can soften lines that no topical product reaches. Results are temporary, which is both the appeal and the ongoing cost.
What relaxers do not fix
Relaxers do nothing for volume loss. A fold that remains visible when your face is completely relaxed, such as a deep nasolabial fold or a line running from the corner of the mouth downward, is usually a filler or resurfacing question rather than a relaxer question. That distinction is the most common source of disappointment for first-time patients.
Dermal Fillers: Restylane and Juvederm
Dermal fillers work from a different direction. Instead of reducing muscle pull, they replace some of the volume that has shifted or diminished, which lifts and softens static folds. Denver clinics offering dermal fillers commonly stock Restylane and Juvederm, and those brand families include multiple formulations designed for different areas and depths.
Fillers suit lines that persist at rest, hollowing under the eyes or along the cheeks, and folds around the mouth. They are also frequently combined with a relaxer in the same visit, because the two address separate mechanisms. If your goal is a natural result, that layered approach usually looks more convincing than pushing a high volume of filler into a single area.
Resurfacing: Peels, Dermabrasion, and Laser
A third category improves the skin surface itself. According to treatment information from Denver-area providers, a medium depth peel, light dermabrasion, or gentle laser treatment can produce mild to moderate improvement in wrinkles and in abnormal pigmentation. That word mild matters. Resurfacing is a gradual strategy, often delivered across a series of sessions, and it suits fine lines, texture, tone, and sun-related damage better than deep creases.
Laser treatments are marketed in Denver as a way to reduce wrinkles and fine lines with personalized plans and natural-looking results. Candidacy depends on skin tone, sensitivity, downtime tolerance, and how recently you have had sun exposure, which is a real consideration in a state with strong year-round sun. A board-certified dermatologist can tell you whether your skin type is a good candidate for a given laser or whether a lighter peel is the safer route.
How Denver Practices Put These Together
Most comprehensive anti-aging programs in Denver are built as layers rather than single treatments. One Denver provider describes its program as addressing the skin and body from the surface down to the deepest tissue layer, which is a reasonable description of how injectables, fillers, and resurfacing fit together. The surface layer covers texture and pigment. The middle layer covers volume. The deepest layer covers muscle movement.
Geography shapes the market too. Clinics in the south metro, including those serving Greenwood Village, the Denver Tech Center, and Cherry Hills Village, tend to attract patients who work nearby and want appointments that fit around a lunch break. That detail influences what a practice offers: shorter injectable visits, longer resurfacing sessions, and package pricing that bundles related treatments. When a Denver provider lists a session length and a price together, treat it as a starting point rather than a final quote, since the number of areas and the amount of product change the total.
Board-Certified Dermatology, Medspas, or Both
Denver’s wrinkle treatment market spans a wide range. Directory listings for wrinkle treatments in the area include medical spas such as Cunningham Clinic, Smoothe Denver, Sesen Skin Body Wellness, Happy Clinic Denver, and Novuskin Denver, along with individual physicians listed for the 80246 area, including Dr. Robert G Fante and Dr. Michael Edward Contreras. Names appearing in search results are not an endorsement, and they are not a substitute for checking credentials, licensing, and experience with the specific treatment you want.
There is a practical reason to keep a dermatology practice in the mix. Colorado Dermatology Center, led by board-certified dermatologist Dr. James M. Swinehart, combines more than three decades of clinical expertise with medical, surgical, and cosmetic dermatology, including facial rejuvenation, acne scar revision, hair restoration, and skin cancer treatment such as MOHS surgery. A practice that treats skin disease and skin aging in the same building can evaluate whether a changing spot, a new line, or a rough patch is cosmetic or medical. For anyone with a history of sun damage or skin cancer, that evaluation belongs before the injectable, not after.
Questions Worth Asking at a Consultation
- Which of my lines are movement-based and which are volume-based?
- What result is realistic in one visit, and what would need a series?
- Who performs the injection or the laser, and what is their training?
- What are the risks for my skin tone and my history of sun damage?
- How much downtime should I plan for, and what aftercare is required?
- What is the full cost, including any follow-up sessions?
Timing, Maintenance, and Expectations
No wrinkle treatment in Denver produces a permanent result, and plans that promise otherwise should raise questions. Relaxers are maintained on an ongoing schedule, fillers are gradually metabolized, and resurfacing results build across sessions. The reason to start early is not vanity. Softening a line while it is still dynamic is generally easier than rebuilding a fold that has become static. That said, starting later is not pointless. Patients in their forties, fifties, and beyond are treated regularly, and a well-designed combination plan often produces visible improvement regardless of the starting line.
Realistic expectations matter more than the product name. Providers across Denver describe their goals in similar terms: personalized plans, natural-looking results, and improvement that fits your face rather than changing it.
Frequently Asked Questions
What is the most effective treatment for wrinkles?
There is no single winner, because effectiveness depends on the type of line. Movement-based lines in the forehead and around the eyes respond best to injectable relaxers such as Botox or Dysport. Static folds and volume loss respond to dermal fillers. Fine lines, texture, and sun-related pigmentation respond to peels, dermabrasion, or gentle laser treatments. Most patients get their best result from a combination chosen for their specific pattern.
Is 40 too late to start Botox?
No. Wrinkle relaxers work on muscle movement at any age, so they can still soften dynamic lines that have already formed. What changes with time is how much of the line has become static, which may call for adding a filler or a resurfacing treatment to the plan. A consultation is the best way to learn which category your lines fall into.
How much does wrinkle treatment in Denver cost?
Pricing varies by treatment type, the number of areas treated, and how much product or how many sessions are needed. Some Denver providers publish package prices and session times, but those figures are starting points rather than final quotes. Ask for a written estimate covering the initial visit and any recommended follow-up, since maintenance visits add up over a year.
How long do results last?
Duration depends on the treatment. Injectable relaxers are temporary and require scheduled maintenance, while fillers are gradually broken down by the body over time. Resurfacing results build across a series of sessions rather than appearing all at once. Your provider should give you a realistic timeline for your specific plan, and individual results vary with skin, lifestyle, and sun exposure.
Should I see a dermatologist or a medspa?
Both can be appropriate, and many patients use each for different needs. A board-certified dermatologist can evaluate your skin for medical concerns alongside cosmetic ones, which matters if you have a history of sun damage or skin cancer. Medspas often focus on injectables and package pricing. Check credentials, licensing, and experience with your specific treatment before booking either option.

Acne and Acne Scar Treatment in Denver: Matching Procedures to Scars
Two people can walk into a dermatology office with a similar history of breakouts and leave with completely different treatment plans. That is not inconsistency. It is the nature of scar revision. Acne scars come in distinct shapes, depths, and textures, and no single treatment is best for everyone. What improves one person’s skin may do very little for another’s. Matching the procedure to the scar is the first real decision in any acne and scar treatment plan.
Why Acne Leaves Scars Behind
Acne scarring can develop as a complication of acne itself. Any type of acne spot can lead to scarring, but it is more common when the most serious types of spots, nodules and cysts, burst and damage nearby skin. The damage happens below the surface, which is why a scar can appear after the visible bump has already faded.
Picking and squeezing matter too. Scarring can also occur if you pick or squeeze your spots, so it is important not to do this. That advice is not about willpower. Manipulating a healing lesion adds trauma to skin that is already repairing itself, and that extra injury can make a scar more noticeable.
The Main Scar Types, and Why the Difference Matters
The NHS groups acne scars into three main types. Two of them are easy to picture:
- Ice pick scars: small, deep holes in the surface of the skin that look like the skin has been punctured with a sharp object.
- Rolling scars: caused by bands of scar tissue that form under the skin, which pull the surface into gentle, wave-like depressions.
Ice pick scars are narrow and deep. Rolling scars are wider and shallower but tethered underneath. A third main type also exists, and the practical point is the same for all of them: depth and tethering change how a treatment needs to work. A surface treatment reaches the top layers of skin. A procedure designed to release or fill tissue underneath addresses a different part of the problem. Choosing without classifying the scar first is how people end up disappointed after a treatment that was never aimed at their actual scar.
Procedure Options That Dermatology Uses for Scarring
Multiple treatments exist, including chemical peels, dermabrasion and microdermabrasion, laser treatment, punch techniques, dermal grafting, needling, and combined approaches. Most scars can be improved by modern interventions, which may include surgical revision and excision, laser therapy, intralesional injections, and topical creams.
Those categories can sound like a menu, and in some ways they are, but they work at different depths and in different ways. Dermabrasion, for instance, involves removing the top layer of skin, either using lasers or a specially made wire brush. Soft tissue fillers work differently: injecting collagen, fat, or other substances under the skin can plump the skin over indented scars. Surgical techniques such as punch techniques and dermal grafting address scars that need a structural change rather than surface refinement.
Home care belongs in the plan as well, although it is not a substitute for procedures. Using sunscreen can help limit the contrast between unscarred skin and a scar. Some medicated creams, such as those containing azelaic acid or hydroxyl acids, might help too.
Matching the Procedure to the Scar
| Approach | What the research describes | Where it fits |
|---|---|---|
| Dermabrasion and microdermabrasion | Removing the top layer of skin, either using lasers or a specially made wire brush | Surface texture and shallow irregularity |
| Laser treatment | Listed among treatments for acne scarring and among modern interventions | Resurfacing and scar revision planning |
| Chemical peels | Named among the numerous treatments for acne scars | Surface-level improvement |
| Needling | Named among treatments and can be combined with retinol creams and filler | Surface and deeper marks within a combined plan |
| Soft tissue fillers | Injecting collagen, fat, or other substances under the skin to plump skin over indented scars | Depressed or indented scars |
| Punch techniques and dermal grafting | Named among surgical treatments for scarring | Scars that need structural change |
| Surgical revision and excision | Listed among modern interventions that can improve most scars | Selected scars after evaluation |
| Intralesional injections | Listed among modern interventions for scarring | Specific scar types as determined by a physician |
| Topical creams | Azelaic acid or hydroxyl acids might help; retinoids can visibly lighten dark spots; salicylic acid helps lighten dark areas and even out skin tone | Home care alongside procedures |
Read that table as a starting point for a conversation, not a prescription. Acne scars are stubborn, and no single treatment is best for everyone. One or a combination of approaches might improve the appearance of your skin depending on your scar type, your skin type, and the severity of the scarring.

Combination Plans Target Surface and Depth Together
Combining two or more treatments, such as retinol creams, microneedling, and filler for acne scars, can target both surface and deep skin marks. That layered logic is why combination planning shows up so often in scar revision. A filler addresses volume under an indented scar while a resurfacing method works on the texture above it, and a topical routine supports the skin between procedures.
Combination also means sequencing. Procedures that remove or remodel surface skin and procedures that add volume underneath place different demands on healing tissue. The order, the spacing, and the number of sessions are clinical decisions, and they depend on how your skin responds.
Marks, Active Acne, and Scars Are Different Problems
Not everything left behind by a breakout is a scar. Post-acne marks are color changes, and topical retinoids are one way to improve their appearance; retinol can help visibly lighten dark spots. Salicylic acid is sometimes used for the treatment of acne as well, and studies show it helps lighten dark areas and even out skin tone. Marks and scars can coexist, which is why a plan may include both a topical routine and a procedure.
Active acne deserves its own attention. Treating scarring while breakouts are still forming means new lesions can keep creating new damage. A dermatologist can address active acne and scar revision as parts of one plan rather than treating them as separate errands.
What to Ask During a Consultation in Denver
Colorado Dermatology Center is a South Denver dermatology practice led by board-certified dermatologist Dr. James M. Swinehart, whose clinical experience spans more than three decades. The practice covers medical, surgical, and cosmetic dermatology, and acne scar revision is one of its areas of emphasis alongside skin cancer treatment, hair restoration, and clinical research trials.
Bring specific questions to that visit:
- Which of the main scar types do I have, and where are they located?
- Is what I am seeing a scar, a post-acne mark, or both?
- Do I still have active acne that needs treatment first or alongside revision?
- Which procedures are being recommended, and what does each one target at the surface versus underneath?
- How many treatments are planned, and in what order?
- What home care, including sunscreen and any topical creams, supports the result?
A useful consultation ends with you understanding why a particular procedure fits your particular scars. If the explanation is vague, or if the plan is a single treatment applied the same way to everyone, ask for the reasoning. Scar revision rewards precision, and precision starts with classification.
Frequently Asked Questions
What is the best treatment for acne scars?
There is no single best treatment. Acne scars are stubborn, and no one approach is right for everyone. One or a combination of options might improve the appearance of your skin depending on your scar type, your skin type, and the severity of the scarring. A dermatologist matches the procedure to what your skin actually shows.
Can acne scars actually be improved?
Most scars can be improved by modern interventions. Depending on the evaluation, that may include surgical revision and excision, laser therapy, intralesional injections, and topical creams, along with chemical peels, dermabrasion or microdermabrasion, punch techniques, dermal grafting, and needling. Improvement is the realistic goal rather than erasing a scar completely.
Do I need to clear active acne before treating scars?
Active breakouts can keep creating new damage, including when nodules and cysts burst and damage nearby skin, so it makes sense to address both. A dermatologist can build a plan that manages active acne while planning scar revision, rather than treating the two as unrelated problems. Ask how your own plan sequences them.
Does sunscreen or skincare really matter for scars?
Yes, as support rather than a cure. Using sunscreen can help limit the contrast between unscarred skin and a scar. Some medicated creams containing azelaic acid or hydroxyl acids might help too, and topical retinoids can visibly lighten dark spots. Salicylic acid is also used for acne treatment and helps lighten dark areas and even out skin tone.
Why do dermatologists combine treatments?
Because scars vary in depth and texture. Combining two or more treatments, such as retinol creams, microneedling, and filler for acne scars, can target both surface and deep skin marks. Soft tissue fillers plump skin over indented scars using collagen, fat, or other substances, while resurfacing approaches work on the surface. The mix depends on your scars.

MOHS Surgery Denver: How Micrographic Removal Works
Mohs micrographic surgery is a highly specialized treatment for the removal of skin cancer, and it works differently from almost any other cancer operation. The same physician serves as surgeon, pathologist, and reconstructive surgeon during a single visit, which is why the procedure has earned a reputation as the most precise way to clear certain tumors. The technique is named in honor of Dr. Frederic Mohs, and it is performed in the office using local anesthesia rather than in a hospital operating room.
For patients in Denver searching for a Mohs surgeon, the appeal is easy to understand. The procedure yields the highest cure rate of all skin cancer treatments, with cure rates approaching 99% for tumors that have not previously been treated. Just as important, it spares healthy tissue in a way that standard excision cannot, which matters a great deal when the cancer sits on the nose, eyelid, ear, lip, or another visible part of the face.
What Makes Mohs Surgery Different From Standard Excision
A traditional excision removes the visible tumor along with a margin of normal skin, and the tissue is sent to a pathology lab for review. Results often come back days later. If the margins are not clear, the patient returns for a second procedure.
Mohs surgery compresses that cycle into one appointment. The surgeon removes the cancer, examines 100% of the tissue edges under a microscope while the patient waits, and knows immediately whether any cancer remains. If it does, another thin layer is taken from only the precise area where tumor cells were found. Nothing is guessed, and nothing is removed simply for safety margin.
- The physician acts as surgeon, pathologist, and reconstructive surgeon in one sitting.
- The procedure is performed in the office using local anesthesia.
- The removal of healthy skin is minimized compared with other skin cancer treatments.
- Cure rates approach 99% for tumors that have not previously been treated.
How Micrographic Skin Cancer Removal Works, Step by Step
The procedure relies on the precision and accuracy of examining tissue under a microscope to trace and ensure removal of the skin cancer, which may have roots that extend beyond what is visible to the naked eye. Here is how that plays out during a typical Mohs visit.
- Consultation and biopsy review. Your surgeon confirms the diagnosis and reviews the pathology report, the tumor’s location, and its size before scheduling the procedure itself.
- Mapping the tumor. On the day of surgery, the visible cancer and a small surrounding area are marked and mapped so the tissue can be oriented accurately once it leaves the body.
- First stage removal. The area is numbed with local anesthesia, and the visible tumor plus a thin layer of surrounding tissue is removed.
- Tissue processing. The specimen is flattened, frozen, sectioned, and stained so the entire outer edge can be viewed at once rather than sampled in random slices.
- Microscopic review. The surgeon reads the slides personally and marks on the map exactly where cancer cells remain, if any do.
- Additional stages if needed. When cancer is still present, another thin layer is removed only from the mapped area, and the review repeats until the margins are clear.
- Reconstruction. Once the cancer is fully removed, the surgeon closes the wound, which may involve a simple closure, a flap, or a graft depending on the size and location.
Why the Microscope Step Carries So Much Weight
Skin cancers can send out microscopic extensions that are invisible to the naked eye. Those extensions are the reason some tumors recur after an apparently complete removal. By examining the entire perimeter of each removed layer, Mohs surgery finds those roots while the patient is still in the chair, which is what allows the surgeon to be confident the cancer is gone before the wound is closed.
Reconstruction Is Part of the Procedure, Not an Afterthought
Because the surgeon who removed the cancer also understands exactly how deep and wide the defect is, reconstruction can be planned around both function and appearance. Denver Mohs practices commonly perform reconstructive surgery on the chin, forehead, and nose, areas where a poorly planned closure would be noticeable and where tissue movement and skin tension need careful handling.
Cure Rates and Why Mohs Is Not Used for Every Tumor
Mohs surgery exists in a category of its own when it comes to cure rates. For tumors that have not previously been treated, cure rates approach 99%. That figure is the reason the technique is often reserved for cancers in high-risk locations, cancers that have returned after earlier treatment, tumors with aggressive growth patterns, and cancers where the amount of healthy tissue removed matters a great deal.
Not every skin cancer requires Mohs surgery, though. A small, superficial cancer on the back or shoulder may be managed perfectly well with another approach. The right choice depends on the tumor type, its size and depth, its location, whether it has been treated before, and your own health history. A board-certified dermatologist is the right person to make that call, and a referral to a Mohs surgeon does not automatically mean you need the most complex option.
Who Performs Mohs Surgery in Denver
Mohs micrographic surgery requires training beyond a dermatology residency. Mohs surgeons complete a dedicated fellowship program, which typically runs about a year, focused on the technique itself plus the pathology reading and reconstructive skills that go with it. When you look for a provider in the Denver area, that fellowship training and board certification are the credentials worth checking first.
Denver has a substantial pool of Mohs providers across the metro, from Cherry Creek and central Denver to Aurora, where hospital-based dermatology departments also offer the procedure. Colorado Dermatology Center has served the region for more than three decades under board-certified dermatologist Dr. James M. Swinehart, with Mohs surgery offered as part of its skin cancer services. The Denver and Longmont office can be reached at (303) 761-0906.

What Recovery Looks Like After Mohs Surgery
Most patients leave the office the same day with the wound closed and written instructions in hand. Because the procedure uses local anesthesia only, there is no general anesthetic to recover from. The first days are usually about keeping the site clean, protecting the repair, and managing soreness, and your surgeon’s team will tell you exactly how to care for your specific closure.
Scarring is a normal part of any procedure that removes skin, and Mohs surgery does not change that. What it does change is how much tissue is taken and how carefully the closure can be designed. Patients are typically advised to avoid strenuous activity and sun exposure on the healing site for a period determined by the surgeon, and follow-up visits are used to confirm healing and check for new skin cancers elsewhere.

Questions to Ask Before Booking a Mohs Appointment in Denver
A short list of questions will tell you a great deal about how a practice operates and whether it fits your situation.
- Is the surgeon board certified, and did they complete a Mohs fellowship?
- Who reads the pathology slides, and is the tissue processed on site?
- Who performs reconstruction if my wound needs a flap or graft?
- How long should I expect to be at the office on the day of surgery?
- What does my insurance cover, and what will I be responsible for?
Coverage details vary by plan, so confirm them directly with the practice and your insurer rather than relying on a directory listing or an online summary. For patients comparing providers, it also helps to ask how many stages a typical case requires at that office and whether the surgeon handles the reconstruction personally.
Frequently Asked Questions
Is Mohs surgery painful?
The area is numbed with local anesthesia before any tissue is removed, so most patients feel pressure or movement rather than sharp pain during the stages. Once the numbing wears off, soreness at the site is normal and manageable with standard post-procedure care. Your surgeon will give you specific instructions for pain control, dressing changes, and activity limits based on the size and location of your repair.
How do I choose a Mohs surgeon in Denver?
Start with credentials. Look for a board-certified dermatologist who completed a dedicated Mohs fellowship, since that training covers both the surgery and the microscope work. Then ask practical questions about on-site tissue processing, who performs reconstruction, and how your insurance applies. Denver has providers across Cherry Creek, central Denver, and Aurora, so you have options and can compare before you book.
Will I have a scar after Mohs surgery?
Any procedure that removes skin leaves a scar, and Mohs surgery is no exception. The advantage is that the removal of healthy skin is minimized and the surgeon who clears the cancer also plans the closure, which supports the best possible cosmetic result. Reconstruction on visible areas such as the nose, forehead, and chin is planned around how the scar will mature over the following months.
Can Mohs surgery treat any type of skin cancer?
Mohs surgery is a highly specialized treatment for the removal of skin cancer, and it delivers the highest cure rate of all skin cancer treatments, approaching 99% for tumors that have not previously been treated. Even so, not every skin cancer needs it. Small, low-risk tumors may be handled with another method after your dermatologist weighs the tumor type, location, size, and history.
If you have been told you need Mohs surgery in Denver, the most useful next step is a direct conversation about your specific tumor. Ask who will read your slides, ask who will close the wound, and ask what your recovery will realistically involve. Those three answers will tell you more about your care than any ranking or directory list, and they put you in a much better position to move forward with confidence.
Skin Cancer Screening Cost in Denver: Pricing and Coverage
A skin cancer screening is one of the few medical visits where the price can swing widely depending on where you go, what kind of clinician you see, and whether your insurance treats the visit as preventive care. Published cost figures for a full-body skin check generally land between $100 and $300 without insurance, with dermatologist-performed exams clustering in the $120 to $300 range.
Denver patients face the same broad pricing band as the rest of the country, but the exact number depends on the practice, the type of visit, and your specific plan. This guide breaks down what the published data shows, how coverage usually works, and what to confirm before you book so there are no surprises on the bill.
What You Are Paying For During a Skin Check
A skin cancer screening is a visual examination. A clinician looks over your skin, often from head to toe, checking for spots, moles, or lesions that look new, changing, or otherwise unusual. The visit also includes the clinical judgment behind it: deciding whether something needs to be watched, photographed, or biopsied.
The fee you pay reflects the time and expertise involved, plus the administrative side of the visit. Because there is no single national price list, two offices in the same city can charge different amounts for what sounds like the same appointment. That is why asking for the self-pay rate upfront is worth the phone call.
Typical Skin Cancer Screening Costs Without Insurance
The published ranges below come from cost surveys and consumer health resources. They represent typical national figures rather than a guaranteed rate at any one office, and your actual cost may be higher or lower depending on the complexity of the exam and whether a board-certified dermatologist performs it.
| Type of visit | Typical cost without insurance |
|---|---|
| Full-body check by a dermatologist | $120 to $300 |
| General skin cancer screening | $100 to $200 |
| Dermatologist visit paid out of pocket | $150 to $300 |
| Teledermatology case | $40 to $80 |
| Insurance copay for a dermatologist visit | $30 to $75 |
The lower end of the range usually reflects a straightforward visual exam. The higher end can reflect a more detailed evaluation or a specialist practice. For comparison, published figures for a metro area like Phoenix run $100 to $250, which sits inside the same national band. There is no separately published Denver rate in the sources reviewed here, so treat the national ranges as your starting point and confirm the real number with the office or your insurer.
How Insurance Coverage Usually Works
Most private insurance companies, along with Medicare and Medicaid, cover the cost of certain routine cancer screenings. That sounds straightforward, but skin checks sit in a gray area because a screening visit and a problem-focused visit can be billed differently.
A skin screen performed as part of an annual physical through a primary care physician is usually covered, since it folds into the preventive visit. When you see a dermatologist specifically for a skin check, some plans cover it as preventive care and others treat it as a specialist visit. In the second case, the charge may apply to your deductible or require a copay, which published figures place at roughly $30 to $75.
The practical step is to call the number on the back of your insurance card and ask two questions: how a skin cancer screening is classified under your plan, and what your responsibility would be for a preventive visit versus a diagnostic one. Getting the answer in writing or noting the reference number of the call can help if the claim is processed unexpectedly.
Denver Pricing: What to Confirm Before You Book
Colorado Dermatology Center is a South Denver practice led by board-certified dermatologist Dr. James M. Swinehart, whose clinical experience spans more than three decades. The practice handles medical, surgical, and cosmetic dermatology, with a strong focus on skin cancer treatment, including MOHS micrographic surgery.
Because self-pay rates change and vary by the type of visit, the most reliable approach is to contact the office directly and ask for the current fee for a skin cancer screening, along with what the visit includes. It also helps to confirm whether the practice will bill your insurance and, if so, which billing codes the visit would use. Those codes determine whether your plan processes the visit as preventive or diagnostic care, which in turn determines what you owe.
If you have a specific spot that worries you, say so when you schedule. A focused evaluation of a concern is a different appointment than a full-body screening, and the cost structure can differ.
If a Suspicious Spot Is Found: Biopsy and Follow-Up Costs
A screening itself does not remove or test anything. If the clinician sees something that needs a closer look, the next step may be a biopsy, where a sample of tissue is taken and sent to a lab for examination. That step typically carries its own charges, and how much you pay depends on your plan, whether you have met your deductible, and how the claim is categorized.
The sources reviewed here do not include specific biopsy or pathology pricing, so anyone who needs one should ask their insurer directly about coverage for a skin biopsy and laboratory analysis before the procedure. Requesting a cost estimate from both the practice and the insurance company is a reasonable step, especially early in a plan year when a deductible may not yet be met.
Free and Low-Cost Screening Options
Cost should not be the reason a suspicious spot goes unchecked, and there are established programs built around that idea.
- The American Academy of Dermatology runs its free skin cancer check program, the organization’s longest-standing public health effort. Dermatologists have conducted more than 2.9 million free checks through it.
- Destination Healthy Skin travels to roughly 40 cities around the United States each spring and autumn, offering free skin cancer screenings and educational materials.
- The Prevent Cancer Foundation points people without insurance toward free and low-cost medical care in their community, and suggests contacting a local hospital or health care facility to ask whether it offers routine cancer screening or testing through foundation or outreach programs, including mobile testing.
These options fill up quickly and availability varies by season, so checking program websites for current schedules is the best way to plan.
Ways to Lower Your Out-of-Pocket Cost
Several practical moves can shift the number you pay.
- Ask whether the visit can be handled during an annual physical with your primary care physician, which is usually covered as preventive care.
- Confirm with your insurer how a dermatology skin check is classified before you book, so you know if it falls under preventive benefits or a deductible.
- Consider teledermatology for a specific concern. Published pricing runs about $40 to $80 per case, and these visits are often insured.
- Request the self-pay rate if you are paying cash, since offices sometimes have a different price for uninsured patients.
- Watch for free screening events in your area, particularly in spring and autumn.
Questions to Ask When You Schedule
A short list of questions before the appointment can prevent billing confusion later.
- What is the current cost of a full-body skin cancer screening if I pay out of pocket?
- Do you bill my insurance, and how is a screening visit coded?
- Is this visit treated as preventive care or as a specialist visit under my plan?
- What would a biopsy cost if one is needed, and is pathology included?
- Are there any fees for follow-up visits related to the same concern?
Screening recommendations matter as much as price. The AAD recommends annual exams for adults with risk factors, so the right cadence for you is a conversation worth having with your dermatologist rather than something to decide based on cost alone.
Frequently Asked Questions
How much does a skin cancer screening cost without insurance?
Published figures put a full-body skin check by a dermatologist at roughly $120 to $300, while general screening ranges run about $100 to $200. Dermatologist visits paid entirely out of pocket are often quoted at $150 to $300. The final number depends on the practice, the complexity of the exam, and whether a board-certified dermatologist performs it, so confirm the rate when you schedule.
Does insurance cover skin cancer screenings?
Most private insurance companies, Medicare, and Medicaid cover the cost of certain routine cancer screenings. A skin screen done as part of a primary care annual physical is usually covered. When a dermatologist performs the screening, some plans cover it as preventive care while others treat it as a specialist visit, which may mean a copay of about $30 to $75 or a charge toward your deductible.
Can I get a free skin cancer screening?
Yes, free options exist. The American Academy of Dermatology’s free skin cancer check program has provided more than 2.9 million free checks. Destination Healthy Skin visits roughly 40 cities each spring and autumn with free screenings and educational materials. The Prevent Cancer Foundation also directs people without insurance to free and low-cost care in their community, including hospital outreach and mobile testing programs.
Is teledermatology a cheaper way to get a skin check?
Teledermatology is generally the lowest-cost option in the published data, running about $40 to $80 per case, and these visits are often covered by insurance. It works best for evaluating a specific spot or concern rather than a comprehensive head-to-toe screening. If you have multiple spots or a history of skin cancer, an in-person exam with a dermatologist is usually the better fit.
What happens if the dermatologist finds something suspicious?
A screening does not involve removing or testing tissue. If something needs closer evaluation, the clinician may recommend a biopsy, in which a sample is taken and sent to a lab. Biopsies typically carry separate charges, and the sources reviewed here do not include specific pricing. Ask your insurer about coverage for a skin biopsy and pathology before the procedure.

Skin Cancer Screening at a Dermatologist in Denver: What to Expect in 2026
A skin cancer screening is an appointment where a doctor checks your skin for moles or spots that could be cancer. Most of these exams are performed by a dermatologist, and the goal is straightforward: a thorough look at your skin for signs or pre-signs of skin cancer while they are still small and easy to treat. If you have been putting off a check, or if you have never had one, the visit itself is usually shorter and simpler than people expect.
Colorado Dermatology Center is a South Denver dermatology practice led by board-certified dermatologist Dr. James M. Swinehart, with more than three decades of clinical experience and a strong focus on skin cancer treatment, including MOHS surgery. Here is what a screening involves, how to prepare, and how to know when you should book one sooner rather than later.
What a Skin Cancer Screening Actually Is
A screening is a visual examination, not a laboratory test. A dermatologist scans the body looking for abnormal moles, changes in moles, or suspicious lesions. That means the appointment is built around observation and a conversation about your skin history rather than bloodwork or imaging.
Screenings sit inside a broader prevention strategy. The Skin Cancer Foundation recommends that adults see a dermatologist at least once a year for a professional skin examination, and it positions that annual visit alongside everyday sun protection. The Foundation also advises making an appointment any time you notice something new, changing, or unusual on your skin, without waiting for your next scheduled check.
How Often You Should Be Screened
A once-a-year exam is the general recommendation for adults. Your own schedule may look different depending on what your dermatologist finds and on factors you discuss during the visit, such as your history of sun exposure, prior skin cancers, or a large number of moles. Some patients are asked to return more often than annually, and others are fine on the standard yearly rhythm.
The practical takeaway is to treat the annual exam as a baseline rather than a ceiling. If your dermatologist wants to see you again in six months, that is a clinical judgment about your skin, not a sign that something is wrong.
What Happens During the Visit
Before the exam
You will typically be asked about your history: sun exposure, tanning bed use, family history of skin cancer, and any spots you have noticed on your own. This is the moment to point out anything that has been bothering you, even if it seems minor. A spot you have been watching for months is useful information for the person examining you.
The visual scan
The core of the appointment is the scan itself. The dermatologist looks over your skin for abnormal moles, changes in moles, and suspicious lesions. You will be asked to undress to your comfort level so that areas beyond your face and arms can be checked, including the scalp, back, and areas that rarely see the sun. Skin cancer does not only appear on parts of the body that get direct sunlight.
After the scan
If everything looks stable, the visit ends with a plan for when to come back and what to watch for in between. If something catches the dermatologist’s attention, you will talk through what was seen and what the next step is. Ask questions here. Understanding what your dermatologist is watching and why makes it much easier to follow through on the plan.

How Long a Screening Takes
Most skin check visits take about 10 to 15 minutes. Your appointment may run a little longer if it is your first visit or if you have a lot of moles, since both take more time to review and document. Plan for a bit of buffer around the appointment rather than scheduling something immediately afterward.
When to Book Sooner Than Your Annual Exam
An annual exam is a schedule, not a rule about when you are allowed to call. You should see a dermatologist right away for a skin cancer check if you notice a growth on your skin that lasts for two weeks or longer and is growing or changing. New, changing, or unusual spots also warrant an appointment before your next routine visit.
That guidance is intentionally simple, because the changes that matter most are often the ones you can describe in plain language: this mole got darker, this spot is bigger than it was, this bump was not here last summer. Trust that observation. You do not need to diagnose anything yourself to justify booking a check.
Self-Exams Between Appointments
Monthly self-exams help you learn what is normal for your own skin, which makes it easier to notice when something changes. The American Academy of Dermatology offers a body mole map you can use to perform a self-exam, learn what to look for, and record your spots so you can refer back during your next visit with your dermatologist. Bringing those notes to your appointment gives your dermatologist a clearer timeline than memory alone.
A self-exam does not replace a professional screening. It is a way to stay familiar with your skin so that you arrive at your annual visit with useful information instead of a vague sense that something might have changed.
Choosing Where to Have Your Screening in Denver
Look for a board-certified dermatologist with experience in both diagnosis and treatment, since the same practice can often handle whatever comes next if a spot needs attention. Colorado Dermatology Center handles medical, surgical, and cosmetic dermatology in South Denver, and its skin cancer work includes MOHS micrographic surgery, a technique used for certain skin cancers. Practices that also run clinical research may have additional options available for qualifying patients.
It also helps to ask how the practice handles follow-up. If a screening leads to a biopsy or a treatment recommendation, you want to know who performs it, where it happens, and how results are communicated.
Preparing for Your Appointment
- Remove nail polish from your fingers and toes before the visit so the skin underneath can be examined.
- Skip self-tanner and heavy makeup on the day of the exam.
- Bring a list of spots you want checked, with notes on when you first noticed them and what has changed.
- Write down your history of sunburns, tanning bed use, and any prior skin cancer diagnoses or treatments.
- Bring the name of any family member who has had skin cancer.
- Ask about your insurance coverage and any out-of-pocket cost before the appointment rather than after.
Cost, Coverage, and What to Confirm in Advance
Screening costs vary by practice and by how the visit is coded for insurance, and the research behind this article does not establish a standard price. Call the practice and your insurer directly to confirm what your plan covers for a routine skin exam compared with a visit for a specific concern. Those two situations are often handled differently, and knowing which one applies to you prevents billing surprises.
If cost is a barrier, ask whether the practice offers any lower-cost screening events or whether a visit focused on a specific spot would be covered differently than a full-body exam. A short phone call answers most of these questions.
Frequently Asked Questions
How long does a skin cancer screening take?
Most skin check visits take about 10 to 15 minutes. Your appointment may run longer if it is your first visit or if you have a lot of moles, since both take additional time to review and document. It is reasonable to allow extra time around the appointment, especially for a first screening.
How often should I see a dermatologist for a skin exam?
The Skin Cancer Foundation recommends that adults see a dermatologist at least once a year for a professional skin examination. Your dermatologist may recommend a different interval based on what is found during the exam and on your personal history, so treat the annual visit as a starting point rather than a fixed rule.
What is a dermatologist looking for during a screening?
A dermatologist visually scans the body, looking for abnormal moles, changes in moles, or suspicious lesions. The exam is a thorough check rather than a quick glance at one spot, which is why areas like the scalp and back are included. Anything you have noticed on your own is worth pointing out during the visit.
When should I book a check instead of waiting for my annual exam?
See a dermatologist right away if you notice a growth on your skin that lasts for two weeks or longer and is growing or changing. The Skin Cancer Foundation also advises booking an appointment any time you see something new, changing, or unusual on your skin rather than waiting for your next scheduled visit.
Can I check my own skin between appointments?
Yes. The American Academy of Dermatology offers a body mole map that you can use to perform a self-exam, learn what to look for, and record your spots so you can refer back during your next visit with your dermatologist. Self-exams support professional screenings, but they do not replace them.
Botox and Fillers in Denver: Facial Beautification Without Surgery
Facial beautification no longer requires a trip to the operating room. In Denver, Botox and dermal fillers are among the most accessible cosmetic procedures available, offered everywhere from boutique clinics to neighborhood medical spas. For patients who want to soften expression lines, add lip definition, or refresh facial contours, injectables provide visible changes without the longer recovery period associated with surgery. The appeal is easy to understand: a quick appointment, product options matched to the individual, and results that can last for months.
Why Patients Choose Nonsurgical Facial Rejuvenation
Denver patients are drawn to injectables because the treatments fit into a busy lifestyle. Rejuvenate MedSpa Denver notes that Botox takes just minutes to perform, yet the skin can maintain a more youthful appearance for months afterward. That balance of speed and longevity makes injectables an attractive option for people who want a refreshed look without committing to a surgical procedure or an extended recovery.
The local injectables market is also remarkably diverse. Patients can book appointments at a medical spa such as The Luxe Room, a natural-results practice like Cheeky Denver, a boutique injectable clinic such as Simply Injectables, an aesthetic wellness center like GATTONI Medical Aesthetics & Wellness, or even a dental office. Sloan’s Lake Dental in Denver, for example, offers Botox and dermal fillers to give patients a fresher, more youthful smile. With this range of practice styles, almost anyone can find a setting that feels right.
What Denver Clinics Offer for Facial Beautification
Clinics across Denver organize their injectable menus around a few core categories. Most practices carry a neuromodulator option, one or more dermal filler families, and some form of lip or facial volumizing treatment. The specific array of brands depends on the practice, but common names appear consistently across Service menus.
Botox and Other Neuromodulator Options
Botox is the best-known injectable for smoothing facial lines, but Denver’s clinics often carry additional neuromodulator brands. GATTONI Medical Aesthetics & Wellness lists Botox, Dysport, Xeomin, Letybo, and Daxxify among its services. Happy Clinic Denver focuses on Dysport and Botox and has advertised a Botox and Dysport offer as low as $9 per unit. Having several product choices gives patients flexibility to discuss preferences with a provider rather than accepting a one-size-fits-all recommendation.
Dermal Fillers, Lip Fillers, and Facial Balancing
Dermal fillers address volume loss and enhance facial structure, and Denver practices typically stock more than one product family. Restylane and Juvederm appear frequently, and GATTONI Medical Aesthetics & Wellness includes both alongside Sculptra and lip fillers. Cheeky Denver specifically includes lip filler in its treatment menu, while The Luxe Room offers lip filler as part of a broader injectables program. The goal, as Cheeky Denver describes it, is to enhance facial features with intention and artistry rather than simply adding volume for its own sake.
From Kybella to Sculptra: A Broader Injectable Menu
Some Denver clinics go beyond the standard Botox and filler mix. Simply Injectables, a boutique injectable clinic in the city, provides Botox, dermal fillers, Kybella, and Sculptra under one roof. A practice that carries several product categories, rather than just one or two brands, can tailor a treatment plan more precisely to an individual face. Patients with specific aesthetic concerns benefit from asking which injectables the clinic believes will best match their anatomy and expectations.
Skin Treatments That Complement Injectables
Injectable care often works well alongside other nonsurgical services. The Luxe Room offers microneedling, hydraFacials, and laser treatments in addition to Botox and fillers, giving patients a single destination for skin texture and tone concerns. Cheeky Denver pairs Botox and filler with medical-grade skincare. Combining injectables with supportive skin treatments can help patients achieve a more polished overall result.
Denver’s Practice Styles: From Med Spas to Boutique Clinics
Not all Denver injectable practices look the same. Some present a natural-results philosophy, while others emphasize the technical range of their product menus. Simply Injectables describes itself as Denver’s most personal injectable experience, promising natural results at a price that makes sense. The Luxe Room markets bespoke cosmetic injectables and proprietary treatment techniques. Knowing what each practice emphasizes can help patients choose a clinic whose approach aligns with their own preferences.
| Practice | Practice Style | Highlights |
|---|---|---|
| Cheeky Denver | Medical spa | Natural results focus; Botox, filler, and medical-grade skincare; located in the Sloan’s Lake neighborhood |
| The Luxe Room | Medical spa | Serves Denver, Fort Collins, and Boulder; injectables plus microneedling, hydraFacials, and laser treatments |
| Simply Injectables | Boutique injectable clinic | Botox, dermal fillers, Kybella, and Sculptra; personal service approach |
| Happy Clinic Denver | Aesthetic clinic | Affordable nonsurgical treatments; Dysport and Botox promotions advertised from $9 per unit |
| GATTONI Medical Aesthetics & Wellness | Aesthetic wellness center | Broad product menu including Daxxify, Letybo, Restylane, Juvederm, and Sculptra |
| Rejuvenate MedSpa Denver | Medical spa | Quick Botox appointments with results lasting months |
| Sloan’s Lake Dental | Dental practice | Botox and dermal fillers offered to create a fresher, youthful smile |
Convenience also plays a role in the decision. Cheeky Denver is located in the Sloan’s Lake neighborhood and serves patients from LoHi, the Highlands, Downtown, Wheatridge, Arvada, and Boulder. The Luxe Room extends its services to Fort Collins and Boulder, giving patients in those cities an alternative to a Denver commute. A practice that is close to home or work makes ongoing maintenance easier to sustain.
What to Look for in a Denver Injectables Provider
Injectable results depend heavily on the skill and judgment of the person holding the syringe. A brand name alone does not guarantee a natural outcome, so patients should evaluate a practice before booking. The following points are a good starting place during a search for a Botox or filler provider in Denver.
- Look for a clinic with a clear aesthetic philosophy, such as the facial balancing and natural results approach that Cheeky Denver emphasizes.
- Ask how many product brands the practice offers. A longer menu often means the injector can adapt to different faces and goals.
- Review before-and-after photos and patient feedback. Consumer directories for the Denver area show practices like Simply Injectables and Adore Aesthetix with substantial review histories.
- Consider the practice setting. Medical spas, boutique clinics, and aesthetic wellness centers each create a different experience, and all exist in Denver.
- Confirm who will perform the injection and what credentials that person holds before scheduling treatment.
Because injectable treatment is personalized, some patients choose to book consultations at two or three clinics before deciding. Comparing recommendations, product options, and conversation style can make the difference between a generic result and one that looks intentional. The extra research is worth the effort for a treatment that appears on the face.
Quick Appointments and Results That Last
One reason Botox and fillers have become routine for many Denver patients is the minimal time commitment. Rejuvenate MedSpa Denver reports that Botox takes only minutes to perform, while results can persist for months. Many other Denver practices describe injectables as low-interruption procedures that can be completed during a short visit. Patients should still allow time for a consultation and for the injector to assess facial movement and volume before treatment begins.
Denver’s injectables community has grown large enough to include professional training programs as well. A facial aesthetics training organization offers certification courses in Botox, dermal fillers, and PDO threads at a Denver location. For patients, that training presence reflects a competitive market with many providers, which reinforces the importance of checking each injector’s experience and credentials rather than assuming every clinic delivers the same standard of care.
Making Injectables Part of a Broader Skin Care Plan
Botox and fillers are powerful tools, but they work best within a complete approach to skin health. Patients who already see a dermatologist for medical or surgical skin care can discuss facial rejuvenation during the same visit. Colorado Dermatology Center, a South Denver practice led by board-certified dermatologist Dr. James M. Swinehart, combines medical, surgical, and cosmetic dermatology, with more than three decades of clinical experience. The practice is known for offering procedures many other offices do not, including acne scar revision and facial rejuvenation, and it emphasizes personalized care and natural-looking results.
A board-certified dermatologist brings deep knowledge of facial anatomy and skin health to the injectable conversation. That perspective can be especially valuable for patients who want to coordinate cosmetic injectables with treatment for other skin concerns. No matter which practice a patient selects, the most successful outcomes come from clear communication about goals, honest discussion of product options, and a provider who prioritizes natural-looking change.
Frequently Asked Questions
What kinds of practices offer Botox and fillers in Denver?
Denver patients can choose from several practice styles. Medical spas such as The Luxe Room and Rejuvenate MedSpa Denver offer injectables alongside broader aesthetic services. Cheeky Denver is a medical spa focused on Botox, filler, and medical-grade skincare in the Sloan’s Lake neighborhood. Simply Injectables is a boutique injectable clinic, GATTONI Medical Aesthetics & Wellness is an aesthetic wellness center, and Sloan’s Lake Dental offers Botox and dermal fillers in a dental setting.
Which injectable brands are available in Denver?
In addition to Botox, Denver clinics offer Dysport, Xeomin, Letybo, and Daxxify. Filler menus commonly include Restylane, Juvederm, and Sculptra, with lip fillers offered by many practices. Some clinics also provide Kybella. Product availability changes by practice, so patients should confirm which brands a clinic carries and why the injector recommends a particular product for their needs.
How long does a Botox appointment take?
Rejuvenate MedSpa Denver describes Botox as a treatment that takes just minutes to perform, with results that can last for months. Many Denver medical spas present injectables as low-interruption procedures that fit into a normal day. A full consultation is usually part of the visit, so patients should plan for a little more time than the injection itself requires. The treatment plan determines how many units are used.
Is Denver a good market for patients seeking injectable treatments?
Yes. The city is home to medical spas, boutique injectable clinics, aesthetic wellness centers, and dental offices offering Botox and dermal fillers. Some clinics advertise promotional pricing, and the area even hosts professional injectables training programs, reflecting a large aesthetic medicine community. With so many choices, patients can take time to compare practice styles, product offerings, and injector credentials before making a decision.

Hyperhidrosis Treatment Denver: Options for Excessive Sweating
Sweating is how the body cools down, but for some people, sweat production goes far beyond what the body actually needs. A person might step out of the shower and begin perspiring before reaching for a towel. Palms may feel damp during a routine conversation. Sweat can soak through shirts within an hour of getting dressed. If this sounds familiar, the cause may be hyperhidrosis, a treatable medical condition.
Hyperhidrosis is defined as sweating that goes beyond the body’s normal thermoregulation needs. The underarms, palms and soles of the feet are the most common areas, though sweating can also appear on the head, face and other body sites. Dermatology practices in the Denver area offer multiple treatment options, and patients who seek help often find relief that makes a real difference in their day-to-day comfort.
Colorado Dermatology Center, led by board-certified dermatologist Dr. James M. Swinehart, provides medical, surgical and cosmetic dermatology care to patients across the South Denver area. Hyperhidrosis is a medical skin condition that deserves the same careful evaluation as any other dermatologic concern.
What Is Hyperhidrosis?
In normal circumstances, the body perspires during physical exertion, warm weather, stressful moments or illness. Sweat reaches the surface of the skin and cools the body through evaporation. In a person with hyperhidrosis, sweat glands remain overactive in the absence of these triggers. A patient may perspire heavily while resting, sitting in an air-conditioned office or standing still. The level of sweating simply does not match the body’s need to maintain a stable temperature.
Hyperhidrosis can be limited to a single part of the body or it can affect several areas at once. The condition most often targets the underarms, palms of the hands and soles of the feet, and it may also show up on the head or face, or in skin folds such as beneath the breasts. Because sweating is involuntary, patients have little control over when it begins. Many people learn to plan their clothing, seating and daily activities around the unpredictable nature of the symptom.
The Impact of Excessive Sweating on Daily Life
Excessive sweating can create social stress that goes beyond physical discomfort. A patient might avoid shaking hands, feel self-conscious during presentations or skip fabrics that make sweat more visible. Some activities, such as dancing, exercising with a group or trying on shoes in a store, carry the risk of visible moisture. Over time, this can shape the way a person moves through work, school and relationships, and it can chip away at confidence.
Patients sometimes believe that the problem is caused by strong deodorant not working or by warm weather alone. The reality is that hyperhidrosis affects the sweat glands at a deeper level, and standard grooming products rarely address it. A dermatologist can confirm the diagnosis and shift the conversation from managing symptoms to treating the condition itself.
Hyperhidrosis Treatment Options in Denver
The Denver area offers a broad selection of hyperhidrosis treatments. Some approaches are straightforward, such as applying a prescription antiperspirant or taking an oral medication. Others involve in-office steps like iontophoresis, neurotoxin injections or the miraDry procedure. The ideal treatment depends on the location of the sweating, how much it interferes with daily life and how a patient responds to earlier attempts.
Prescription-Strength Antiperspirants
For excessive sweating on the hands, feet or underarms, prescription-strength antiperspirants are often a reasonable starting point. These products are formulated to handle sweat output that regular antiperspirants cannot control. A dermatologist can select an appropriate product and guide the patient on how frequently it should be applied. Consistent use matters, and skin sensitivity is something the physician will monitor during follow-up visits.
Oral Medications
Patients who sweat excessively in multiple areas may benefit from oral medications designed to decrease sweating. Because these medicines act throughout the body, they can address symptoms that are not contained to one region. Oral options are not appropriate for everyone, so the prescribing doctor will review health history, allergies and current medications before writing a prescription. If oral therapy is chosen, the patient and physician will watch for effectiveness and any unwanted effects.
Iontophoresis for Sweaty Hands and Feet
Iontophoresis uses electrical currents to treat excessive sweating of the hands and feet. During treatment, the affected area is placed in contact with water while a low-level electrical current is delivered. The current works to temporarily disable the sweat glands, which reduces the moisture that reaches the skin. Iontophoresis is noninvasive and does not depend on needles, making it an option for patients who would rather avoid injections.
Botox and Neurotoxin Injections for Hyperhidrosis
Botox is a familiar name in cosmetic dermatology, but it also has a strong role in treating hyperhidrosis. The injections work by blocking the nerve signals that tell sweat glands to produce sweat. For the underarms, palms and soles, Botox provides effective relief, with results lasting six months or longer. It can also be used on the head and face, as well as in the area beneath the breasts. Many patients describe a dramatic improvement in sweating after treatment.
miraDry for Underarm Sweating
miraDry is a device-based treatment approved by the FDA for excessive sweating, and it is offered at dermatology practices in and around the Denver area. It is especially relevant for patients whose main concern is heavy underarm sweating. A consultation is the right time to ask how miraDry works, how long a session takes and what kind of results a patient can reasonably expect.
Finding the Right Hyperhidrosis Treatment in Denver
An individualized approach is central to good hyperhidrosis care. No two patients present the same pattern of sweating. One person may need only a prescription antiperspirant, while another may be a better fit for iontophoresis on the hands or Botox in the underarms. During an appointment, the dermatologist will explore when the sweating started, what makes it worse and what treatments have been tried before.
Patients searching for hyperhidrosis treatment in Denver can feel encouraged by the range of available therapies. The condition no longer has to be managed with extra layers, darker clothing or social avoidance. Board-certified dermatologist Dr. James M. Swinehart brings more than three decades of clinical experience to Colorado Dermatology Center, where concerns like excessive sweating are addressed in a medical dermatology setting. A consultation provides the clearest path toward a treatment that fits each patient’s needs.
Frequently Asked Questions
What kind of doctor treats hyperhidrosis?
A dermatologist is the physician most often responsible for diagnosing and treating hyperhidrosis. Dermatology training covers the skin and its sweat glands, and dermatology practices commonly offer treatments such as prescription antiperspirants, oral medications, iontophoresis, Botox injections and miraDry. During a clinic visit, the doctor will review the sweating pattern and recommend a treatment plan. If other medical issues could be contributing, the dermatologist may coordinate with the patient’s primary care doctor.
What is the most effective hyperhidrosis treatment?
The most effective treatment depends on the body areas involved. Botox injections provide effective relief for hyperhidrosis of the armpits, palms and soles, and results often last six months or longer. Iontophoresis is a common treatment for sweaty hands and feet, while prescription antiperspirants and oral medications work well for certain patients. A dermatologist will tailor the choice to the severity of the sweating and the patient’s lifestyle.
How long does Botox last for hyperhidrosis?
Botox results for hyperhidrosis of the underarms, palms and soles typically last six months or longer. The effect gradually fades when the body renews the nerve signals that stimulate sweat glands. Patients usually schedule repeat treatments as the sweating begins to return, which helps keep the condition under control over the long term.
How much does hyperhidrosis treatment cost in Denver?
The cost of hyperhidrosis treatment varies by therapy, by the size of the treated area and by the practice providing the care. Prescription antiperspirants, oral medications, iontophoresis, Botox injections and miraDry are priced differently, and many factors influence the final bill. Specific pricing is not available without a consultation, so patients should ask the dermatology office for an estimate during the appointment.
Does insurance cover hyperhidrosis treatment?
Insurance coverage depends on the patient’s health plan and on the specific treatment recommended by the dermatologist. Each insurer follows its own guidelines, so benefits cannot be assumed from one plan to the next. Patients should contact their insurance company before the visit or procedure and confirm what is covered. The dermatology office can also explain its billing process and what information a patient may need to provide.

Sclerotherapy for Leg Veins in Denver: What to Expect
Spider veins and varicose veins are among the most common reasons people schedule vein care in Denver. These visible leg veins can show up as fine red, purple, or blue webs, or as twisted, enlarged vessels that feel sore by the end of the day. Sclerotherapy treats both problem types with targeted injections, helping veins fade and letting the legs return to a smoother, clearer appearance. Because the procedure is minimally invasive and takes place in a doctor’s office, it offers a practical option for men and women who want results without surgery.
Spider Veins and Varicose Veins: What They Are
Spider veins are the delicate, web-like vessels that form close to the surface of the skin. They appear as red, purple, or blue lines and are often the first sign of vein trouble in the legs. The condition develops when leaks occur between the deep and superficial veins of the legs. Those leaks can develop from old injuries or from bad valves that allow the high pressure from the deep veins to reach the skin. This pattern is most common on the lateral and inner thighs, and it occurs in both men and women.
Varicose veins are a related but more pronounced concern. They are twisted, enlarged veins located close to the surface of the skin, and they most commonly develop in the legs and around the ankles, where blood circulation may be compromised. While spider veins are often a cosmetic issue, varicose veins can also cause leg pain, swelling, and feelings of heaviness. For that reason, vein specialists in Denver evaluate both the appearance of the veins and the symptoms they cause before recommending a treatment plan.
Treating varicose veins can do more than improve how they look. Vein care programs in the Denver area, including hospital-based centers such as the Denver Health Laser and Vein Care Center, focus on treating varicose veins in order to improve their appearance, lessen pain, and help reduce the risk of complications tied to poorly functioning leg veins. A thorough evaluation helps determine whether sclerotherapy or another approach is the best fit.
How Sclerotherapy Works for Leg Veins
Sclerotherapy is a dedicated vein treatment that eliminates the appearance of unsightly spider veins and smaller varicose veins. During the procedure, a fine needle is used to inject a sclerosant solution directly into the blood vessel. Denver-area practices commonly use solutions such as Sotradecol or Asclera for this purpose. The entire process is designed to be efficient and highly effective for the smaller varicose and spider veins that appear close to the skin.
The injected solution causes the lining of the vein to swell and stick together, and it causes the blood inside the vessel to clot. Once the walls of the vein seal shut, the treated blood vessel fades away over time. Because the body reabsorbs the closed vessel, the visible vein gradually becomes less noticeable, and the surrounding leg develops a cleaner look.
For larger, painful varicose veins, Denver vein specialists often turn to a modified form of treatment called foam sclerotherapy. In this approach, the sclerosant is prepared as a foam that can fill a broader portion of the vessel. Foam sclerotherapy is considered the treatment of choice for these bigger vessels, and in many cases a single treatment can cause the bothersome vein to close. The physician will decide whether standard liquid sclerotherapy or foam sclerotherapy is more appropriate based on the size and condition of the vein.
What Happens During a Sclerotherapy Appointment
Sclerotherapy is performed in the doctor’s office by one of the practice’s physicians. No hospital stay is required, and the treatment is considered minimally invasive. The doctor targets the visible spider veins or small varicose veins and passes a very fine needle into each vessel. The solution is injected directly into the vein, and the patient remains in a comfortable, relaxed position throughout the session.
Denver vein specialists who offer these services describe sclerotherapy as a fast and pain-free treatment that gets patients back on their feet quickly. That makes it an attractive option for people who have postponed vein care because of time constraints or concerns about recovery. The fine needle used during the procedure helps keep discomfort low, and the office setting makes the experience more convenient than a traditional surgical procedure.
Several Denver vein centers advertise insurance-covered treatment options for patients dealing with leg pain, swelling, or visible veins. Because sclerotherapy is often performed for cosmetic purposes, the way a treatment is classified can affect coverage. A practice that provides both dermatologic and vein care can review your symptoms, explain the options, and clarify whether the recommended treatment is considered cosmetic or medically necessary before you schedule.
Why People Choose Sclerotherapy in Denver
Some people feel embarrassed by the appearance of their legs because of web-like red, purple, and blue spider veins. The emotional relief that comes from clearing those visible vessels is one of the most common reasons patients pursue sclerotherapy. The procedure is frequently done for cosmetic purposes to improve the appearance of varicose and spider veins, and it is well suited to the smaller vessels that laser treatments may not address as directly.
There are also medical reasons to consider vein treatment. Leg pain, swelling, and visible veins can interfere with daily comfort, and Denver vein specialists offer treatments aimed at getting patients back to their normal routine without prolonged downtime. Treating varicose veins can reduce pain, improve how the legs look, and help lower the risk of complications related to circulation problems. Because the condition appears in both men and women, sclerotherapy appeals to a wide range of patients who want healthier-looking legs.
How to Choose a Leg Vein Provider in Denver
Denver has a broad range of vein care options, from dermatology practices to dedicated vein clinics and vascular surgery groups. Some practices, such as the Vein Care Institute, focus on non-surgical diagnosis and treatment of varicose veins and spider veins. Hospital-based programs like the Denver Health Laser and Vein Care Center provide vein care alongside other medical services, and vascular surgery groups in the greater Denver area bring board-certified specialists to more complex cases. This variety means patients can usually find a provider that matches their comfort level and treatment goals.
Credentials matter when choosing a provider for leg vein sclerotherapy in Denver. The procedure should be performed by a physician with experience in vein care, whether that physician is a dermatologist or a vascular specialist. Colorado Dermatology Center, for example, is led by board-certified dermatologist Dr. James M. Swinehart, who combines more than three decades of clinical expertise with medical, surgical, and cosmetic dermatology care for patients in the South Denver area. The practice emphasizes personalized care, proven techniques, and natural-looking results.
Before committing to a vein treatment plan, schedule a consultation and ask specific questions. Find out whether the practice offers sclerotherapy, whether foam sclerotherapy is available for larger veins, and which sclerosant solutions the physician prefers. Ask how the practitioner determines which leg veins are contributing to your symptoms and whether the treatment is considered cosmetic or medically necessary. A clear conversation about your goals and your vein history helps ensure that the approach is tailored to your legs rather than a one-size-fits-all plan.
Frequently Asked Questions
Is sclerotherapy for leg veins performed in a hospital?
No. Sclerotherapy is performed in the doctor’s office by one of the practice’s physicians. A solution is injected through a very fine needle directly into the vein, which makes the treatment minimally invasive and eliminates the need for an operating room. Patients can have the procedure done during a regular office visit and avoid the added time and preparation that come with a hospital-based surgery.
Can sclerotherapy treat both spider veins and varicose veins?
Yes. Sclerotherapy is an efficient and highly effective treatment for smaller varicose veins and spider veins. For larger, painful varicose veins, Denver vein specialists often recommend foam sclerotherapy, which is considered the treatment of choice for those bigger vessels. In many cases, a single foam treatment can cause bothersome veins to close, although the exact number of sessions depends on the size and response of the veins being treated.
Are sclerotherapy treatments in Denver covered by insurance?
Many Denver vein centers offer insurance-covered treatments for patients dealing with leg pain, swelling, or visible veins that are tied to vein problems. Sclerotherapy is also frequently performed for cosmetic purposes, so coverage often depends on how the procedure is classified. Before scheduling, ask the practice whether your planned treatment is considered medically necessary or cosmetic and confirm what your insurance plan will cover.
Do men develop spider veins and varicose veins?
Yes. Spider veins occur in both men and women, and they are most common on the lateral and inner thighs. The visible vessels form when leaks develop between the deep and superficial veins of the legs, often because of old injuries or bad valves that allow high pressure to reach the skin. Varicose veins also develop in men, particularly in the legs and around the ankles, so vein evaluation is relevant for anyone with visible veins or leg discomfort.
Female Hair Loss Treatment: Options That Work
Hair loss in women is far more common than many people assume, and the treatment options available today have expanded considerably. Women can choose from over-the-counter products such as minoxidil, prescription medications such as spironolactone and finasteride, and in some cases, surgical procedures. The right plan depends on the underlying cause of the hair loss, the duration of the thinning, and how the scalp responds to treatment.
Because female hair loss has many possible triggers, a thorough evaluation by a dermatologist is an important first step. A dermatologist can determine whether the hair loss represents female pattern hair loss, a side effect of a medication, a response to a medical treatment, or damage caused by styling habits. With an accurate diagnosis, a treatment plan can be built around the cause rather than guesswork.
Women often feel that hair loss is something they have to accept, but that is no longer the case. With the range of effective treatments available, most women can find a strategy that stabilizes thinning and, in many cases, restores density. The key is matching the treatment to the type of hair loss and staying consistent with it over time.
Understanding Female Pattern Hair Loss
Female pattern hair loss is one of the most common reasons women seek help for thinning hair. Unlike male pattern baldness, it usually produces diffuse thinning over the top of the scalp while the front hairline remains relatively intact, although the exact pattern can vary from woman to woman. The condition is influenced by hormones and genetics, and it can begin at any age after puberty.
Not all female hair loss follows this pattern, however. Some women lose hair in patches, while others experience sudden shedding after an illness or a stressful event. Recognizing which type of hair loss is present matters because the treatment approach differs. Female pattern hair loss typically responds to medication, whereas temporary shedding often resolves on its own.
Early evaluation is valuable. When hair thinning is identified and treatment begins promptly, there is more hair to preserve, and the scalp is better positioned to respond to therapy. Delaying treatment can make the process harder, because the medications used for female hair loss work best on follicles that are still active.
Common Causes of Hair Loss in Women
Hair loss in women can stem from several sources, and sometimes more than one factor is involved. The most frequently cited causes include:
- Cancer treatments such as chemotherapy and radiation therapy, which can cause temporary but significant hair shedding.
- Hairstyling practices that place repeated stress on the hair follicles, including very tight styles and harsh chemical treatments.
- Medications that list hair loss as a possible side effect.
- Hormonal influences connected to female pattern hair loss.
Understanding the cause helps guide treatment. Hair loss that follows chemotherapy or radiation often reverses after the treatment ends, while female pattern hair loss generally requires ongoing therapy. Similarly, hair loss related to styling habits may improve once those habits change.
A single cause is not always obvious, and in some women several factors combine. That is why a professional evaluation matters. A dermatologist can sort through the possibilities, confirm the diagnosis, and recommend treatment based on the specific type of hair loss rather than a general approach.
Medication Options for Female Hair Loss
The two main pharmacological approaches for female pattern hair loss are minoxidil and anti-androgen medications. These treatments have been studied extensively, and both need to be continued indefinitely to maintain a response. Stopping treatment usually means losing the benefit that was gained.
Minoxidil (Rogaine)
Topical minoxidil is the most widely used first-line therapy for female hair loss. It is available over the counter and is applied directly to the scalp. The FDA originally approved a 2% minoxidil solution for use in women, and a 5% solution has also become available. Dr. Antonella Tosti, a recognized expert in hair disorders, routinely prescribes topical minoxidil as an initial treatment, usually choosing the 2% concentration.
For women, minoxidil is typically applied once daily. Consistent use can reduce shedding and promote regrowth over time, but results take months to become visible. Because minoxidil works only while it is being used, women who stop applying it may lose the hair they maintained or regrew.
Spironolactone
Spironolactone is a prescription medication that belongs to a group of drugs known as anti-androgens. Androgens are hormones that can contribute to hair thinning in women who are genetically susceptible. Spironolactone works by reducing the influence of these hormones on the hair follicle, helping to slow the progression of female pattern hair loss. Doctors may suggest spironolactone tablets when topical treatment alone is insufficient or when a woman prefers an oral option.
Finasteride
Finasteride is another prescription medication that appears among the treatment options for female hair loss. Like spironolactone, it is considered an anti-androgen therapy and works by affecting hormonal activity related to hair thinning. Women taking finasteride need to be monitored by a physician, and the decision to prescribe it should be made on an individual basis after a full evaluation.
How Long Do Treatments Need to Be Used?
One of the most important facts about female hair loss treatment is that the main pharmacological options must be continued indefinitely to maintain a response. Hair grows slowly, and it can take several months of daily, consistent use before improvement is noticeable. Women who expect a quick fix are often disappointed, while women who commit to a long-term routine are more likely to see results.
Every medication has a different profile, and what works for one woman may not work for another. A dermatologist can guide the choice, adjust the dose, and monitor for side effects. Combining treatments on your own, without medical supervision, is not recommended.
Surgical Treatment for Hair Loss
Medication is not the only path. Surgery is also listed among the standard treatment options for hair loss, and it may be appropriate for certain women. Hair transplant procedures can restore density in areas where thinning has stabilized, provided there is sufficient donor hair. A consultation with a dermatologist is essential to determine candidacy, because surgical treatment is not right for every woman, and the decision depends on the pattern and progression of the hair loss.
Hair Care Habits That Support Treatment
In addition to medical therapy, changing your hairstyling routine can help avoid damaging your hair follicles. Gentle handling, looser styles, and reduced use of heat and chemical treatments can prevent further breakage and give medications a better chance to work. These adjustments are supportive measures rather than substitutes for medical treatment, but they are a meaningful part of an overall plan.
Product selection also matters. In a review of hair loss treatments for women, a medicated shampoo formulated to support hair health was rated as the top pick, which highlights that a complete routine can include products designed to strengthen the hair and scalp. Women should choose products based on their specific needs and discuss them with their dermatologist.
Choosing the Right Female Hair Loss Treatment
With over-the-counter and prescription options available, the choice can feel overwhelming. A dermatologist can narrow the focus by considering:
- The likely cause of the hair loss and whether it is continuing to progress.
- The severity of the thinning and its location on the scalp.
- Other medical conditions and current medications.
- Patient preference for a topical, oral, or surgical approach.
For many women, topical minoxidil is a sensible starting point because it is accessible, well-studied, and recommended as a first-line treatment. If the response is not adequate after several months, adding an anti-androgen such as spironolactone is a common next step. Regular follow-up with a dermatologist allows the plan to be adjusted based on visible progress.
Patience is essential. Visible improvement from minoxidil or anti-androgen therapy can take several months, and the goal is steady maintenance rather than overnight transformation. Tracking progress over time helps determine whether a treatment is working, and adjusting the plan when needed keeps women on the path to healthier hair.
Frequently Asked Questions
Here are answers to common questions about female hair loss treatment.
Can female hair loss grow back?
Hair loss can improve with treatment, but the outcome depends on the cause. For female pattern hair loss, minoxidil and anti-androgen medications can slow thinning and, in many cases, encourage regrowth. However, research shows that these treatments must be continued indefinitely to maintain a response. Hair loss caused by chemotherapy or radiation often grows back after treatment ends, and styling-related loss may resolve when damaging habits stop.
How can women regrow hair?
The most common treatment is topical minoxidil, applied to the scalp once daily. The FDA originally approved a 2% formulation for women, and a 5% solution has since become available. When minoxidil alone is not effective, doctors may prescribe anti-androgen tablets such as spironolactone, or in some cases finasteride. Surgery is another option for suitable candidates. All medication approaches require consistent, long-term use to preserve results.
Are there home remedies for hair loss?
Evidence for home remedies is weaker than the research behind prescription and over-the-counter treatments. One recommendation that does appear consistently is changing your hairstyling routine to avoid damaging your hair follicles, since tight styles and harsh chemical treatments can worsen hair loss. Women considering home remedies should understand that female pattern hair loss generally requires medical treatment, and a dermatologist can confirm which approach is best.

Alopecia Areata Treatment: Proven Options Beyond Clinical Trials
Alopecia areata is an autoimmune disease that attacks the body’s hair follicles, causing patchy hair loss. For many people, the first sign is a small, round bald spot on the scalp, though the condition can affect other areas as well. Once a dermatologist confirms the diagnosis, the next question is usually what can be done about it.
While research studies continue to explore new therapies, many effective treatment options are already available in everyday dermatology practice. These established treatments work by blocking the immune system attack on the hair follicles so hair can regrow. Understanding what is available beyond clinical trials can help patients have more informed conversations with their dermatologist.
What Is Alopecia Areata?
Alopecia areata is an autoimmune condition, which means the immune system mistakenly attacks the body’s own hair follicles. This attack interrupts normal hair growth and leads to patchy hair loss. The condition can affect both adults and children, and the pattern and extent of hair loss vary widely from person to person.
There is currently no cure for alopecia areata, but there are treatments that may regrow hair in both adults and children. The goal of treatment is to control the immune response and create conditions that allow hair to grow again. Because the condition can be unpredictable, ongoing follow-up with a dermatologist is often part of the process.
How Dermatologists Choose a Treatment
Because alopecia areata affects people differently, there is no single approach that fits everyone. The kind of treatment a doctor recommends depends on several factors:
- The type or form of hair loss
- The severity of hair loss, meaning how much hair has been lost
- The patient’s age
- What treatments have already been tried
- Whether the patient also has an atopic or allergic condition, such as atopic dermatitis (eczema)
These factors help the dermatologist determine whether a topical, injectable, or oral approach is most appropriate. Effective treatments for alopecia areata block the immune system attack on the hair follicles so hair can regrow, and matching the right treatment to the right patient is an important part of the process.
Corticosteroid Injections: The Most Common Treatment for Patchy Hair Loss
For adults with patchy alopecia areata, the most common treatment is intralesional injection of corticosteroids. This means the medication is injected directly within the bald patch. Local steroid injections can be used on the scalp and eyebrows and are considered the most effective approach for small patches of hair loss.
The main advantage of this approach is that treatment is targeted precisely to the areas where hair loss is occurring. Because the corticosteroid is delivered directly to the affected site, it can work quickly to suppress the immune attack in that specific area. For patients with limited patchy disease, this is often the first treatment considered.
Topical Corticosteroids and Minoxidil
Topical treatments also play an important role in managing alopecia areata. A common treatment plan involves applying a corticosteroid to the affected areas to regrow hair and later using minoxidil, known by the brand name Rogaine, to keep the hair that has regrown. Corticosteroid creams are among the therapies commonly prescribed for this condition.
This staged approach reflects how dermatologists often combine treatments. One therapy is used to stimulate regrowth, and a second is used to maintain the result. Topical treatments can be especially useful for patients who prefer to avoid injections or who have multiple areas of hair loss that would be difficult to treat individually.
Topical Immunotherapy and Anthralin
When first-line treatments are not effective, or when hair loss is more extensive, dermatologists may recommend other options. Topical immunotherapy is a recognized part of alopecia areata management. It is designed to alter the immune response in the skin so that the attack on hair follicles stops and hair can regrow.
Anthralin is another therapy commonly prescribed for alopecia areata. These options broaden the treatment toolkit for patients who do not respond to corticosteroids or minoxidil. As with all alopecia areata treatments, the choice of therapy depends on the individual patient’s situation and how the condition has behaved over time.

JAK Inhibitors: A Growing Oral Option
One of the most significant developments in alopecia areata treatment has been the arrival of Janus kinase inhibitors, commonly called JAK inhibitors. There are currently six JAK inhibitors that have been reported to be successful in treating alopecia areata, including tofacitinib, ruxolitinib, and baricitinib.
Oral JAK inhibitors used in the management of alopecia areata include baricitinib, ritlecitinib, and deuruxolitinib. These medications work by interfering with specific immune signals that contribute to the attack on hair follicles. For patients with extensive hair loss or those who have not responded to other treatments, oral JAK inhibitors represent a meaningful option beyond topical and injectable therapies.
Treatment Options at a Glance
The table below summarizes the main treatment categories available for alopecia areata outside of clinical trials.
| Treatment | Examples | Role in Alopecia Areata |
|---|---|---|
| Corticosteroid injections | Intralesional corticosteroids | Most common treatment for adults with patchy alopecia areata; most effective for small patches on the scalp and eyebrows |
| Topical corticosteroids | Corticosteroid creams | Applied to regrow hair; often followed by minoxidil to keep the regrown hair |
| Minoxidil | Rogaine | Used after a corticosteroid to help maintain hair that has regrown |
| Topical immunotherapy | Prescription topical therapy | Used in the management of alopecia areata to alter the immune response in the skin |
| Anthralin | Anthralin | Commonly prescribed therapy for alopecia areata |
| JAK inhibitors | Baricitinib, ritlecitinib, deuruxolitinib; also tofacitinib and ruxolitinib | Oral medications that target immune pathways; six JAK inhibitors have been reported successful in treating alopecia areata |
What to Expect From Treatment
It is important to have realistic expectations when treating alopecia areata. Medications and therapies can help hair regrow, though severe cases may not respond to treatment. Regrowth takes time, and maintaining regrown hair often requires ongoing treatment rather than a one-time fix.
A dermatologist can help patients understand what to expect based on the type of hair loss, its severity, and the treatment selected. Because some patients respond better than others, follow-up visits are essential for monitoring progress and adjusting the plan when needed.

The Value of a Personalized Treatment Plan
No two cases of alopecia areata are identical, which is why personalized care matters. The kind of treatment a doctor recommends depends on the type or form of hair loss, the severity of the hair loss, the patient’s age, what treatments have already been tried, and whether the patient also has an atopic condition such as eczema.
Patients who work closely with a board-certified dermatologist benefit from an approach tailored to their specific circumstances. From targeted corticosteroid injections for small patches to oral JAK inhibitors for more extensive disease, the proven options beyond clinical trials provide meaningful paths forward for many people. If you are experiencing patchy hair loss, a dermatology consultation is the first step toward identifying which of these treatments may be right for you.
Frequently Asked Questions
Does hair grow back from alopecia areata?
In many cases, yes. Medications and therapies can help hair regrow, though severe cases may not respond to treatment. Regrowth is possible for both adults and children, and the outcome depends on the severity of hair loss and how well the individual responds to the chosen therapy. A dermatologist can provide a realistic assessment of what to expect based on the specific situation.
What is the most common treatment for adults with patchy alopecia areata?
The most common treatment for adults with patchy alopecia areata is intralesional injection of corticosteroids, meaning the medication is injected directly within the bald patch. Local steroid injections can be used on the scalp and eyebrows and are considered the most effective approach for small patches of hair loss.
What are JAK inhibitors for alopecia areata?
JAK inhibitors, or Janus kinase inhibitors, are medications that block immune signals involved in the attack on hair follicles. Six JAK inhibitors have been reported to be successful in treating alopecia areata, including tofacitinib, ruxolitinib, and baricitinib. Oral options used in management include baricitinib, ritlecitinib, and deuruxolitinib.
Is there a cure for alopecia areata?
There is currently no cure for alopecia areata. However, treatments are available that may regrow hair in both adults and children. Effective treatments work by blocking the immune system attack on the hair follicles so that hair can regrow, and ongoing management is often needed to maintain results over time.
Why do treatment recommendations vary from patient to patient?
Treatment depends on the type or form of hair loss, the severity of hair loss, the patient’s age, what treatments have already been tried, and whether the patient also has an atopic condition such as atopic dermatitis. These individual factors guide the dermatologist in selecting the most appropriate therapy for each person.
Hair Transplant Cost in Denver: What to Expect
Anyone researching hair restoration in Colorado quickly learns that hair transplant cost in Denver is not one fixed number. Published averages, clinic pricing pages, and patient quotes all tell different stories because each procedure is built around an individual scalp. This article explains the numbers, the factors behind them, and what you should look for when you compare Denver hair restoration options.
How Much Does a Hair Transplant Cost in Denver?
According to a 2026 national cost analysis, the average hair transplant cost in Denver, CO, is $11,874. That figure is useful as a starting point, but it is not a guarantee. The same analysis includes averages for other cities, and Denver’s number sits at the higher end of the list.
Other sources add more context. One health care financing guide places the average cost of a hair transplant in the United States between $3,919 and $10,640. A Denver-based clinic notes that a hair transplant session can range from $5,000 to $15,000. Some hair restoration practices advertise pricing starting at $5,000 and say that a full head of hair can pay off for a lifetime. The gaps between these numbers show why a personal quote matters more than any single average.
Published Average Costs in Selected Cities
| City | Average Hair Transplant Cost |
|---|---|
| Atlanta, GA | $7,000 |
| Boston, MA | $7,000 |
| Chicago, IL | $10,000 |
| Dallas-Fort Worth, TX | $9,750 |
| Denver, CO | $11,874 |
Denver’s average of $11,874 is higher than the other cities in this list. That does not mean every Denver clinic charges more than every clinic in another city. It does suggest that patients planning hair restoration in the Denver area should look closely at the details of each quote.
What Factors Affect Hair Transplant Cost?
The cost of a hair transplant procedure depends on multiple factors, including the type of procedure chosen, the number of grafts needed, and your hair restoration goals. These variables are central to any consultation. A small touch-up is not priced the same as a full session, and different approaches can lead to very different estimates.
Type of Procedure
Some Denver practices describe today’s options as advanced stem cell and FUE transplant procedures. A clinic in Englewood, Colorado, also offers FUE consultations and reviews whether a patient is a good candidate for the technique. The method you choose affects the final quote, so ask each practice to explain what is included.
Number of Grafts Needed
Grafts are the basic unit of a hair transplant quote. More grafts generally mean more work and a higher price. In one online hair loss forum, a patient reported being quoted $8,250 for 1,500 grafts. Another commenter called a 3,500-graft price below $5,000 unrealistic. These personal examples illustrate that graft counts and prices are not standardized.
Hair Restoration Goals
A patient who wants full, even coverage across the entire scalp will need a different plan than someone restoring a smaller area. Your expected density and style affect how many grafts the doctor recommends. During a consultation, a provider can explain what a realistic goal looks like for your hair type and pattern.
How to Compare Hair Transplant Quotes in Denver
When comparing quotes, look past the starting price. Ask whether the number covers a full session or only part of the procedure. Ask how many grafts the provider recommends, which method will be used, and whether follow-up care is included. A quote from one clinic will not match a quote from another clinic if they are describing different work.
Payment plans and financing also play a role in the total cost. Some Denver practices offer adaptable financing. One clinic says patients can make payments of about $250 per month. Another practice advertises payment plans alongside pricing that starts at $5,000. Before you book, ask for a written estimate and a clear explanation of the payment terms.
What Does a Full Hair Restoration Session Include?
Published pricing pages often use the word session because a hair transplant visit has multiple parts. A single session can range from $5,000 to $15,000, depending on the clinic and the patient. Some patients need only one session, while others may need additional work to reach their desired fullness. The consultation is the time to learn whether one session will be enough.
The exact details of a session vary by provider. Some clinics include only the transplant itself in their advertised price. Others may include consultation, planning, and follow-up. Because those details are not uniform across Denver, the safest approach is to ask every practice exactly what is covered.
Choosing a Hair Transplant Provider in Denver
Denver has several established options for hair loss treatment. A Yelp search updated in 2026 lists Advanced Hair Restoration and Scalp Artist International among the top-rated hair transplant providers in the area. Bosley also has a Denver hair restoration location and has announced that Bosley and HairClub are uniting. These resources give patients plenty of choices when comparing experience, reviews, and pricing.
For patients who prefer a medical setting, Colorado Dermatology Center in South Denver is another option. The practice offers medical, surgical, and cosmetic dermatology and is led by board-certified dermatologist Dr. James M. Swinehart, who has more than three decades of clinical expertise and an emphasis on hair restoration. Because hair transplant cost in Denver can vary so widely, a consultation with an experienced provider is a useful way to get a reliable estimate.
What to Expect at a Hair Transplant Consultation
Most Denver clinics will not give you a firm price without first seeing your scalp. A consultation in the Denver area may take place at a dedicated hair restoration clinic or at a medical practice. An Englewood, Colorado facility, for example, offers consultations to learn more about FUE, hair restoration cost, and candidacy for treatment.
- Bring your hair loss history and note any treatments you have already tried.
- Prepare a list of questions about procedure type, graft count, and recovery.
- Ask about the total session cost and what the quote includes.
- Ask about financing and payment plans before you commit.
A good consultation covers more than price. It should also show you what the doctor sees as a realistic outcome. The estimate you receive after that visit will be a much better guide than a general average.
Why Denver Averages Are Just a Starting Point
National and city averages are useful for budgeting, but they cannot predict your quote. The U.S. average range of $3,919 to $10,640 is broad, and Denver’s average of $11,874 is even higher. The actual figure you are quoted will depend on the clinic, the procedure, and the number of grafts your case requires.
For that reason, it helps to view all published pricing as an introduction rather than a final answer. A price that works for one person may not work for another, even in the same city. Clinics update their pricing over time, so confirm current rates with the practice you choose. The next step is to find a provider who can examine your scalp and explain the treatment plan.
Frequently Asked Questions
These are some of the most common follow-up questions patients ask after researching Denver hair transplant pricing.
How much does a hair transplant cost in Denver?
Denver’s average hair transplant cost is $11,874, according to one 2026 cost analysis. Other Denver sources place a single session between $5,000 and $15,000, and some practices advertise prices starting at $5,000. The final amount depends on the procedure, the number of grafts, and your hair restoration goals. A consultation is the most reliable way to get a personal quote.
Why do hair transplant prices vary so much?
Hair transplant prices vary because every patient has a different pattern of hair loss, hair density, and desired outcome. The type of procedure, the number of grafts, and the area being restored all influence the final cost. Clinics also include different services in their advertised prices. Comparing quotes is only useful when you understand what each practice is actually offering.
Can I finance a hair transplant in Denver?
Yes, many Denver hair restoration practices offer financing or payment plans. One clinic notes that some patients make payments of about $250 per month. Another Denver provider advertises adaptable financing and stresses that world-class hair restoration does not have to cost a fortune. Ask each clinic about its specific payment terms before making a decision.
How many grafts will I need?
The number of grafts you need depends on your scalp, hair density, and the coverage you hope to achieve. In one online forum, a patient shared a quote of $8,250 for 1,500 grafts, while another commenter said a 3,500-graft price below $5,000 was unrealistic. These examples show why an in-person evaluation is necessary. A provider can estimate your graft count during a consultation.
Hair Loss Treatment in Denver: Medical Therapy to Hair Transplants
Hair loss treatment in Denver spans a wide range of approaches, from medical therapies that address early thinning to hair transplant surgery designed for more advanced balding. The city is home to dermatology practices, specialized hair clinics, and national hair restoration centers, giving patients meaningful choices at every stage of hair loss.
The right treatment depends on the extent of the hair loss, the patient’s goals, and whether they prefer non-surgical care or a procedure with lasting results. Because the options differ so much, a consultation with a qualified provider is the best way to determine which path fits.
Medical Therapy for Hair Thinning
Dermatology practices in the Denver area offer hair thinning solutions that rely on medication, injections, and topical treatments. These medical therapies are often a practical starting point for patients with early shedding or gradual thinning, since they are non-surgical and can be tailored to the individual.
Medical therapy works differently from surgery. Topical treatments are applied directly to the scalp, medications support the hair over time, and injections deliver treatment to the areas that need it most. The Colorado Dermatology Institute, for example, offers hair thinning solutions that include medication, injections, and topical treatments. A dermatologist can examine the pattern of hair loss and recommend the medical approach most likely to help.
PRP Injections for Shedding, Thinning, and Balding
Platelet-rich plasma, or PRP, has become one of the most widely discussed non-surgical hair loss treatments in Denver. PRP is a well-studied and effective treatment for hair loss. The process begins with a blood draw, after which the growth factors are isolated from the blood and prepared for injection.
Those growth factors are then injected into the scalp in the areas where thinning is occurring. PRP injections represent a best-in-class solution for shedding, thinning, and balding, with the goal of restoring quality of life and a sense of youthfulness. Because PRP uses the patient’s own blood, it appeals to people who want a natural, injection-based alternative to surgery.
PRP can be used on its own or combined with other treatments. Patients who are considering PRP should ask their provider how many sessions they might need and how the treatment fits into a broader hair restoration plan.
Hair Transplant Surgery in Denver
For patients with more advanced hair loss, hair transplant surgery offers a route to permanent restoration. Denver has several providers that perform surgical hair restoration, including both national practices and local clinics.
Bosley, which describes itself as the world’s most trusted hair restoration practice, has an office in Denver that offers both surgical and non-surgical hair restoration and hair transplant procedures. The practice is a well-known name in the field and regularly appears on referral lists for hair transplant services in the city.
Local search results show the range of choices available nearby. Yelp’s list of the top 10 hair transplant services in Denver includes Advanced Hair Restoration, listed at about 13.5 miles away, Scalp Artist International, about 1.8 miles away, and Bosley Hair Restoration and Transplant. These options show that patients in the Denver metro area have access to hair transplant specialists without traveling far.
Hair transplant surgery is designed to produce natural-looking, permanent results, but the outcome depends heavily on the surgeon’s experience and the practice’s approach. Patients should evaluate the provider’s credentials, review before-and-after images, and ask detailed questions during the consultation.
Stem Cell Restoration and Specialty Transplant Procedures
Some Denver clinics go beyond traditional hair transplant surgery with advanced procedures. Denver Hair Clinic, for example, offers hair transplant surgery, stem cell hair restoration, platelet-rich plasma therapy, beard transplants, and eyebrow transplants.
The clinic combines expert medical care from board-certified professionals with advanced stem cell technology, with the goal of ensuring a permanent, natural-looking future for the patient’s hair. Stem cell restoration is an evolving area of hair loss treatment that appeals to patients who want a more advanced option.
Beard and eyebrow transplants use the same principles as scalp transplantation but require a high level of precision. These procedures are popular with patients who want to restore density, shape, or definition in facial areas. Providers who offer these services can explain whether a patient is a suitable candidate.
| Approach | Examples Available in Denver | What to Expect |
|---|---|---|
| Medical therapy | Medication, injections, topical treatments | Non-surgical options for thinning hair |
| PRP injections | Growth factor injections from the patient’s own blood | Blood draw, growth factor isolation, scalp injections |
| Surgical restoration | Hair transplant surgery, stem cell hair restoration | Permanent, natural-looking results |
| Specialty transplants | Beard transplant, eyebrow transplant | Precision transplant for facial hair |
Non-Surgical Hair Replacement Options
Not every patient wants surgery, and Denver’s hair restoration market reflects that. Some providers offer non-surgical hair replacement, which is a separate category from PRP and medical therapy. Bosley, for instance, provides both surgical and non-surgical hair restoration at its Denver location.
Non-surgical hair replacement can be a good fit for patients who are not candidates for transplant surgery or who want immediate results without a procedure. A free consultation with a provider can help clarify whether this option suits the patient’s goals.
Choosing a Hair Loss Provider in Denver
Finding the right provider is one of the most important decisions in hair loss treatment. Denver is home to board-certified professionals and clinics that focus specifically on hair restoration, so patients have a strong field to choose from.
Patient ratings can help narrow the options. According to Healthgrades, top doctors who treat hair loss in Denver include Dr. Alexandra Theriault, MD, rated 4.9 out of 5, Dr. Theresa Scholz, MD, rated 3.8 out of 5, and Dr. Peggy Liao, MD. Ratings provide a snapshot of patient satisfaction, but they should be weighed alongside the provider’s experience and approach.
A quality provider also understands the emotional side of hair loss. As Denver Hair Clinic puts it, they do not just “treat” hair loss, they restore the person behind it. That patient-centered mindset matters because hair loss affects confidence and quality of life, not just appearance.
What to Expect From a Hair Loss Consultation
A consultation is the first step in any hair loss treatment plan. At Denver Hair Clinic, patients receive a detailed hair loss assessment and a customized treatment plan designed around their specific needs. National providers like Bosley also offer personalized solutions for patients seeking hair restoration.
During the consultation, the provider examines the scalp, reviews the pattern of thinning or balding, and discusses which treatments are most appropriate. The provider may recommend a single option or a combination of medical therapy, PRP, and surgical restoration. Some Denver providers offer free consultations, making it easier to compare options before making a decision.
Patients who are ready to take the next step can schedule a consultation by phone or through an online booking form. Early intervention often produces better outcomes, so patients who notice persistent shedding should not delay an evaluation. A thorough assessment is the foundation of an effective treatment plan, and the right provider will take the time to explain every option.
Frequently Asked Questions
What non-surgical hair loss treatments are available in Denver?
Non-surgical options in Denver include medication, injections such as PRP, topical treatments, and non-surgical hair replacement. PRP is a well-studied treatment that involves a blood draw, isolation of growth factors, and scalp injections. These options can be used alone or in combination, depending on the patient’s needs and the provider’s recommendations.
Do Denver clinics offer procedures beyond scalp transplants?
Yes. Some Denver clinics offer specialty procedures in addition to standard hair transplant surgery. Denver Hair Clinic, for example, provides stem cell hair restoration, beard transplants, and eyebrow transplants alongside platelet-rich plasma therapy. These options expand hair restoration beyond the scalp for patients with specific aesthetic goals.
How do I choose a hair loss doctor in Denver?
Many Denver hair loss providers are board-certified professionals with experience in surgical and non-surgical restoration. Patient ratings can help, with some top-rated doctors in the city scoring 4.9 out of 5 on Healthgrades. Look for a provider who offers a detailed assessment and a customized treatment plan, and who focuses on restoring confidence, not just treating the condition.
What should I expect at a hair loss consultation?
At a consultation, the provider evaluates the hair loss, reviews the patient’s history, and recommends a treatment plan. Denver Hair Clinic offers a detailed hair loss assessment and a customized plan for each patient. Some providers in Denver offer free consultations, so patients can gather information from more than one practice before deciding on a treatment path.
Mohs Surgery Recovery: What to Expect and How Scars Heal
Mohs surgery is a precise, outpatient procedure used to remove high-risk skin cancer while preserving healthy tissue. The surgeon removes the cancer in thin layers and examines each layer under a microscope, which allows for complete tumor removal and high cure rates. For most patients with basal cell carcinoma or squamous cell carcinoma, Mohs surgery offers a highly effective treatment option. Once the procedure is finished, attention shifts to recovery. Knowing what to expect during healing, how to care for the wound, and how the scar will change over time can make the days and weeks after surgery much easier to manage. The recovery process has clear phases, and each phase has its own set of care instructions.
Understanding Mohs Surgery and the Healing Process
Mohs surgery is considered a precise method for treating certain skin cancers because it allows the surgeon to see exactly where the cancer ends. The layer-by-layer excision means healthy tissue is preserved whenever possible, and the microscopic examination of each layer helps confirm that the tumor has been completely removed. This approach is most effective for treating basal cell carcinoma and squamous cell carcinoma, two of the most common forms of skin cancer.
Recovery from Mohs surgery is not a single event but a process with distinct phases. The first 48 hours focus on protecting the fresh wound. The first two weeks involve dressing changes and basic wound care. After that, the body continues to repair the deeper layers of skin, and the scar gradually matures over many months. Understanding these phases can help you set realistic expectations and follow the right care steps at the right time.
The First 48 Hours: Protecting the Surgical Site
The first 24 to 48 hours after Mohs surgery are the most delicate part of the recovery process. Your surgeon will place a dressing over the surgical site, and that dressing should be left undisturbed during this initial window. Touching, changing, or removing the dressing too early can disrupt the healing wound and increase the risk of complications.
Minor bleeding or oozing may occur within the first 48 hours, and this is normal. If it happens, apply firm, constant pressure with a clean, dry piece of gauze directly on the dressing. Hold the pressure until the bleeding stops. This simple step usually resolves the issue, but contact your surgeon if bleeding continues or seems heavy.
During these first two days, minimize physical activity as much as possible. Avoid anything that may raise your blood pressure or put tension on your incision. Heavy lifting should be avoided entirely during this early period. Keeping your body calm and your heart rate steady gives the wound the best chance to begin healing properly.
Wound Care During the First Two Weeks
Bandages are typically worn for 10 to 14 days after Mohs surgery. During this time, the wound needs consistent but gentle care. Cleanse the area once or twice daily with mild soap and lukewarm water. Keep the wound clean and moisturized, and follow your surgeon’s instructions for changing the dressing and applying any prescribed ointments.
Avoid picking or scratching the surgical site, even when it begins to itch or feel uncomfortable. Picking at the wound can disrupt healing, increase the risk of infection, and lead to a more noticeable scar. If the area feels irritated, resist the urge to touch it and let your surgeon know at your follow-up appointment.
Simple daily habits make a big difference during this period. Pat the area dry rather than rubbing it, and wash your hands before and after any dressing change. If you have questions about how the wound looks or how often to change the dressing, reach out to your surgeon’s office for guidance. It is always better to ask than to guess about a healing wound.
Activity Restrictions and Returning to Normal Life
Most patients will need to avoid strenuous physical activities for a minimum of one to two weeks after Mohs surgery. This restriction is essential to avoid putting tension on the incision while it is still healing. Intense exercise raises your heart rate and blood pressure, which can increase blood flow to the surgical site and lead to bleeding or swelling.
During the first 48 hours, minimize all physical activity. In the weeks that follow, most patients recover within several weeks, though the exact timeline varies based on the size and location of the surgical site and the type of wound closure used. Light activities may be comfortable sooner, but anything that pulls, stretches, or strains the area should wait.
Listen to your body during recovery. If an activity causes discomfort or a pulling sensation around the wound, stop and rest. Your surgeon will let you know when it is safe to resume exercise, heavy lifting, and other demanding activities.

How Mohs Surgery Scars Heal Over Time
Scarring is one of the most common concerns for patients preparing for Mohs surgery, especially when the procedure is performed on the face, neck, or another visible area. The reassuring news is that Mohs scars improve significantly over time, but the process requires patience.
Scars from Mohs surgery continue to heal for 12 to 18 months after the procedure. In some cases, it can take up to a year for the surgical site to fully heal. During this period, the scar will flatten significantly and fade in color. The bright, raised scar you see in the early weeks is not the final result.
Most Mohs surgery scars take 3 to 12 months to fully heal. The way the wound is closed has a direct impact on the healing process. Some wounds are stitched closed, which typically produces a thin, linear scar. Other wounds heal by second intention, meaning the area is left open to heal gradually from the inside out. Each approach has a different healing timeline and produces a different scar pattern. Your surgeon can explain which method was used and what you can expect.
After the dressing comes off, the scar will likely look red and may feel raised or firm. This is a normal part of the healing process. Over the following months, the body gradually remodels the scar tissue, which is why the scar flattens and fades in color. The final appearance of the scar depends on many factors, including its location, your skin type, and how well you followed the post-operative care instructions.
Mohs Surgery Recovery Timeline at a Glance
The table below summarizes the key recovery milestones after Mohs surgery.
| Timeframe | What to Expect |
|---|---|
| First 24 to 48 hours | Keep the dressing undisturbed; minimize physical activity; avoid heavy lifting; minor bleeding or oozing may occur |
| First 10 to 14 days | Bandages are worn; cleanse gently once or twice daily with mild soap and lukewarm water; avoid picking or scratching |
| 1 to 2 weeks | Strenuous physical activities should be avoided |
| Several weeks | Most patients recover within several weeks |
| 3 to 12 months | The scar continues to mature and typically takes this long to fully heal |
| 12 to 18 months | Scars continue to heal, flattening significantly and fading in color |
Tips for Supporting Your Scar’s Healing
Good wound care is the most reliable way to support scar healing after Mohs surgery. Keep the area clean and moisturized, and cleanse it gently once or twice daily with mild soap and lukewarm water. Follow your surgeon’s instructions for dressings and any ointments or creams they recommend.
Avoid picking or scratching the site, and be patient with the appearance of the scar. Early in the healing process, scars often look red, raised, or uneven. Over the following months, they flatten and fade. Ask your surgeon about protecting the scar from sun exposure and whether any scar care products are appropriate for your specific wound.
Consistency matters more than perfection. A simple daily routine of gentle cleansing and dressing changes, followed faithfully, gives your scar the best chance to heal well. If you have concerns about how the scar is developing, bring them up at your follow-up visits.
Frequently Asked Questions
How long does Mohs surgery recovery take?
Most patients recover within several weeks, though the full healing process takes longer. The surgical site may take up to a year to fully heal, and the scar continues to mature for 12 to 18 months. Bandages are typically worn for the first 10 to 14 days, and strenuous activities should be avoided for at least one to two weeks.
Will my Mohs surgery scar go away?
A scar will not disappear completely, but it will improve significantly over time. Scars from Mohs surgery continue to heal for 12 to 18 months, flattening and fading in color as they mature. Most scars take 3 to 12 months to fully heal, and the final result is typically much less noticeable than the fresh wound.
When can I exercise after Mohs surgery?
Most patients need to avoid strenuous physical activities for a minimum of one to two weeks after Mohs surgery. During the first 48 hours, minimize all physical activity and avoid heavy lifting. This is essential to avoid tension on the incision and to prevent bleeding. Ask your surgeon when it is safe to resume your normal exercise routine.
What should I do if bleeding occurs after surgery?
Minor bleeding or oozing may occur within the first 48 hours after Mohs surgery. If this happens, apply firm, constant pressure with a clean, dry piece of gauze directly on the dressing. Hold the pressure until the bleeding stops. If bleeding is heavy or does not stop, contact your surgeon’s office for guidance.

Squamous Cell Carcinoma Treatment: Early Signs and Options
Squamous cell carcinoma (SCC) is one of the most common forms of skin cancer. When caught early, it is highly treatable. Recognizing changes in the skin and seeking timely squamous cell carcinoma treatment can help prevent complications and support the best possible outcome.
Treatment for SCC has advanced in important ways. Most squamous cell carcinomas of the skin can be removed with minor surgery, and some are removed with a medicine applied to the skin. The right approach depends on the size, location, and depth of the tumor, as well as the patient’s overall health.
What Is Squamous Cell Carcinoma?
Squamous cell carcinoma begins in the squamous cells, the flat cells that make up the outer layer of the skin. It is one of the most common forms of skin cancer. Because it develops on the surface of the body, it can often be seen and treated before it becomes more serious.
The first step in effective treatment is awareness. New growths, sores that do not heal, or areas of skin that change in appearance should not be ignored. A dermatologist can evaluate the area and determine whether a biopsy is needed.
Early Signs and the Importance of Prompt Evaluation
Because squamous cell carcinoma is highly treatable when caught early, prompt evaluation matters. The research is clear that recognizing the signs and seeking timely treatment can help prevent complications and ensure the best possible outcome.
Common warning signs can vary from person to person. A new growth, a sore that does not heal, or a patch of skin that changes in color or texture deserves attention. Rather than relying on a general checklist, patients should have any new, changing, or unusual area of skin examined by a qualified professional.
Regular skin exams are a practical way to track changes over time. A dermatologist will look at the skin carefully and may ask about your health history. Early evaluation keeps treatment options open and often leads to simpler, less extensive procedures.

How Squamous Cell Carcinoma Is Diagnosed
Diagnosis begins with a physical exam. A member of the health care team asks about your health history and looks at your skin for signs of squamous cell carcinoma. This focused examination helps identify areas that may need further testing.
If a suspicious area is found, the next step is a biopsy. A biopsy is a procedure to remove a sample of tissue for testing in a lab. The health care team may use a tool to cut away, shave off, or punch out some of the tissue. The sample is then examined under a microscope to confirm the diagnosis.
The biopsy results guide the entire treatment plan. They show whether the cancer is confined to the top layer of the skin or whether it extends deeper. That information helps determine which squamous cell carcinoma treatment options are most appropriate for the individual patient.
Squamous Cell Carcinoma Treatment Options
Squamous cell carcinoma skin cancer treatment may include any combination of therapies. Options include in-office procedures, surgery, topical medications, and radiation therapy. The best plan depends on the tumor’s size, location, and depth, as well as the patient’s health and preferences.
Excisional Surgery
Excisional surgery is the most common and effective treatment for squamous cell carcinoma. During this procedure, the surgeon carefully removes the tumor along with a margin of healthy tissue surrounding it. Removing this margin helps reduce the chance that cancer cells remain behind.
Surgical excision is often a first-line treatment for squamous cell carcinoma. The removed tissue is usually sent to a lab for examination, and the procedure can be performed in an outpatient setting. For many localized tumors, this approach offers an excellent cure rate.
Mohs Surgery
Mohs surgery is a specialized technique used for certain squamous cell carcinomas and is considered the gold standard for treating this disease. Mohs surgery is the most effective technique for removing SCCs, sparing the greatest amount of healthy tissue while achieving the highest possible cure rate.
During Mohs surgery, the tumor is removed in thin layers that are examined under a microscope during the procedure. This allows the surgeon to trace the cancer to its roots and remove it completely. The technique is especially valuable when sparing healthy tissue is a priority.
Curettage and Other In-Office Procedures
Some squamous cell carcinomas can be treated with curettage, an in-office technique used by skin cancer experts. Curettage may be used alone or combined with other methods to address the affected area. A dermatologist can determine whether this approach fits the specific tumor.
In-office procedures are a common part of the treatment picture. They allow many patients to have their cancer managed quickly, often without the need for a hospital stay. The selection of a procedure depends on the tumor and the judgment of the treating physician.
Topical Medications and Chemotherapy
Not every squamous cell carcinoma requires surgery. Some are removed with a medicine applied to the skin, and topical chemotherapy may be used in certain cases. These approaches can be effective for lesions that have not spread deeply into the skin.
Topical treatments target the abnormal cells directly and can be a convenient alternative to cutting procedures. They are not appropriate for every tumor, so a dermatologist will review the biopsy results and the location of the cancer before recommending this route.
Radiation Therapy
Radiation therapy is another option for squamous cell skin cancer. It may be used alone or as part of a broader plan, depending on the situation. Radiation can be considered when surgery is not the best choice or when a tumor is located in a difficult area.
The care team may also recommend radiation after surgery if there is concern about remaining cancer cells. Treatment plans are individualized, and the expected benefits and side effects are reviewed with the patient before the course begins.
Choosing the Right Treatment Approach
With so many effective options, the best squamous cell carcinoma treatment plan is the one that matches the individual diagnosis. The size, depth, and location of the tumor, the results of the biopsy, and the patient’s health history all influence the decision.
The research notes that treatment may include any combination of therapies. A team approach is common when a tumor is complex or advanced. Patients should feel comfortable asking questions about each option and understanding why one treatment is recommended over another.
Early detection remains the most powerful tool. When squamous cell carcinoma is identified early, treatment is often simpler and highly effective. Regular skin checks and prompt attention to any concerning area of skin are the foundation of a good outcome.
Frequently Asked Questions
How curable is squamous cell carcinoma?
Squamous cell carcinoma is highly treatable when caught early. Most cases can be removed with minor surgery, and the cure rate is high when the tumor is treated before it spreads. The outlook depends on the size, location, and depth of the tumor, so early evaluation by a dermatologist gives the best chance of a successful outcome.
How urgent is surgery for squamous cell carcinoma?
Timely treatment is important because recognizing the signs and seeking care early can help prevent complications and support the best possible outcome. The urgency depends on the tumor’s features, and a dermatologist will recommend an appropriate timeline. Patients should not delay evaluation if they notice a new, changing, or non-healing area of skin.
Should I worry if I have squamous cell carcinoma?
While any cancer diagnosis can be concerning, squamous cell carcinoma is one of the most common forms of skin cancer and is highly treatable when caught early. The research emphasizes that prompt treatment helps prevent complications and ensures the best possible outcome. Working closely with a qualified dermatologist is the most effective way to address the diagnosis.
How long can you have squamous cell carcinoma before it spreads?
The research does not provide a specific timeline because each case can progress at a different rate. Some tumors remain localized for a long time, while others can behave more aggressively. Any suspicious lesion should be evaluated promptly, and patients should consult their dermatologist for guidance based on their individual situation.

Ice Pick Acne Scars: Best Treatment Options for Deeper Scars
What Are Ice Pick Acne Scars?
Ice pick scars are one of the three main types of acne scars, along with rolling scars and boxcar scars. They appear as small, deep holes in the surface of the skin that look like the skin has been punctured with a sharp object. Instead of a wide depression, these scars form narrow, puncture-like openings that extend vertically into the dermis. Their depth is what makes them so recognizable, and it is also the reason they are among the most challenging types of acne scarring to treat.
Rolling scars are caused by bands of scar tissue that form under the skin. Boxcar scars are the other common type of depressed acne scar, and they are typically treated with a different approach. Ice pick scars are the narrowest and deepest of the three types. Because each type responds to a different set of treatments, a dermatologist will usually identify the type of each scar before recommending a procedure.
Why Do Ice Pick Scars Form?
Acne scarring can sometimes develop as a complication of acne. Any type of acne spot can lead to scarring, but it is more common when the most serious types of spots, including nodules and cysts, burst and damage nearby skin. Picking or squeezing spots can also increase the chance of scarring, which is why dermatologists advise letting acne lesions heal without manipulation. When the skin experiences that kind of damage, the healing response can leave behind a narrow, deep channel instead of smooth, even tissue. That channel is what becomes an ice pick scar.
Why Ice Pick Scars Need Specialized Care
Because ice pick scars penetrate deeply into the dermis, they rarely respond to surface treatments alone. Products that smooth the outer layer of the skin often cannot reach the deepest portion of the scar. The narrow opening and vertical depth mean the skin needs to be encouraged to produce new collagen inside the scar itself. This is why dermatologists typically recommend in-office procedures designed specifically for ice pick scars, and why patients often see better results with a combination approach.
Surface exfoliation and gentle peels may brighten the skin, but they do not rebuild the collagen missing at the base of an ice pick scar. The scar must be reached at the dermal level with a chemical agent, a surgical tool, a needle, or a laser. This is why the most reliable treatments for ice pick scars are performed by a dermatologist in a clinical setting.
Professional Ice Pick Acne Scar Treatment Options
Several effective treatments can help improve the appearance of ice pick scars. Research and dermatology guidelines identify TCA CROSS, punch excision, subcision, and spot laser irradiation as treatments that work for this scar type. Punch elevation and microneedling also have a role depending on the individual scar. The right plan depends on the depth and number of scars, so an evaluation by a dermatologist is the safest first step.
Treatment | How It Works | Research Notes |
|---|---|---|
TCA CROSS | Acid applied to the base of each scar | Studies show significant improvement in ice pick scars |
Punch excision | Scar surgically removed; wound sealed | Preferred for mild ice pick scars |
Punch elevation | Scar base lifted to skin level | Used for boxcar scars |
Subcision | Breaks bands of scar tissue under the skin | Listed as effective for ice pick scars |
Microneedling | Tiny needling injuries stimulate collagen | Known as collagen induction therapy |
Spot laser treatment | Targeted laser energy delivered to the scar | Works for ice pick scars |
TCA CROSS
TCA CROSS is a targeted chemical treatment used specifically for deep, narrow scars. Clinical studies demonstrate that TCA CROSS produces significant improvement in ice pick scars by inducing dermal collagen formation. A small amount of trichloroacetic acid is applied directly to the base of each scar, which triggers the skin to produce new collagen and gradually raise the depressed area. TCA CROSS is especially useful because it treats the depth of the scar rather than just the surface.
Punch Excision
Punch excision is a surgical technique used to treat mild ice pick scars. The scar is removed with a small circular punch tool down to the subcutaneous level, and then the remaining wound is sealed. Punch or elliptical excision to the subcutaneous level is preferred for ice pick scars because it removes the entire vertical track of the scar. The skin heals with a smaller, smoother mark that is much less noticeable than the original scar.
Punch Elevation
Punch elevation is a related surgical technique that lifts the base of the scar to match the surrounding skin level. It is commonly used for boxcar scars, which are wider than ice pick scars, but dermatologists may consider it when a scar has features of both types. Punch elevation combines the concept of removing a scar with the goal of restoring a more even skin surface. Accurate classification of the scar type helps the dermatologist choose the technique that will give the cleanest result.
Subcision
Subcision works by breaking up the bands of scar tissue that form under the skin. This technique is frequently used for rolling scars, but research also lists subcision as a treatment that works for ice pick scars. By releasing the fibrous tissue that tugs the skin downward, the surface becomes smoother and the shadowing that makes scars visible is reduced. Subcision is often combined with other treatments for a more complete result.
Microneedling
Microneedling, also known as collagen induction therapy, uses a special tool to create several tiny injuries within a scar. These microscopic wounds activate the skin’s natural healing response and stimulate collagen production. Over a series of sessions, the skin texture improves and the depth of the scar becomes less prominent. Microneedling can be used on its own for milder scars or combined with other procedures for deeper ice pick scars.
Spot Laser Treatment
Spot laser irradiation of the scar is another treatment that research identifies as effective for ice pick scars. The laser delivers targeted energy to the scar site, encouraging remodeling of the skin and a smoother surface. Laser treatment can be useful for refining the edges of a scar after surgical treatments, and it can also address discoloration that sometimes accompanies acne scarring.

At-Home Skincare and Prevention
Deep ice pick scars usually need professional treatment, but at-home skincare still matters. Products containing benzoyl peroxide and salicylic acid are effective treatments for acne, which helps prevent new breakouts from forming. Topical retinoids are another option, and they are available in over-the-counter forms. Retinoids support healthy skin cell turnover and can improve the overall texture of the skin, making scars appear less noticeable over time.
Prevention is just as important as treatment. Because picking or squeezing spots can lead to scarring, it is best to avoid touching active acne. Managing acne early reduces the chance of nodules and cysts, which are more likely to burst and cause the deep damage that creates ice pick scars. A consistent routine that keeps breakouts under control is the foundation of any scar treatment plan.
Building a Treatment Plan With a Dermatologist
Ice pick scars vary in depth, size, and number, so no single treatment is right for everyone. A board-certified dermatologist can evaluate the scars and recommend a personalized plan, which may combine TCA CROSS, punch excision, subcision, microneedling, or laser therapy.
During a consultation, the dermatologist will examine the shape, depth, and location of the scars and identify which of the three main scar types are present. Because ice pick scars often appear alongside boxcar and rolling scars, the plan may include several techniques. The dermatologist will also review the patient’s history of acne, since active breakouts may need to be controlled before scar treatment begins.
At Colorado Dermatology Center in South Denver, acne scar revision is a special focus. Dr. James M. Swinehart brings more than three decades of clinical expertise to help patients improve the look and feel of their skin with proven techniques and natural-looking results.
Frequently Asked Questions
Here are answers to common questions about ice pick acne scar treatment.
What causes ice pick scars?
Ice pick scars can develop as a complication of acne. Any type of acne spot can lead to scarring, but it is more common when nodules and cysts burst and damage nearby skin. Picking or squeezing spots also increases the risk of scarring. When the skin is injured this way, the healing process can leave a narrow, deep hole in the surface, which is the defining feature of an ice pick scar.
Are ice pick scars hard to treat?
Yes. Ice pick scars are among the most challenging types of acne scarring to treat because of their deep, narrow penetration into the skin. Their depth makes them resistant to surface treatments alone, and the narrow opening means treatment must be very targeted. This is why dermatologists use specialized techniques such as TCA CROSS, punch excision, subcision, and laser therapy rather than relying on creams or general peels.
Can ice pick acne scars go away?
Ice pick scars rarely go away on their own. Because they extend deeply into the dermis, they do not respond to surface treatments alone. However, specialized procedures such as TCA CROSS, punch excision, subcision, microneedling, and laser therapy can produce significant improvement in the appearance of the scars. With a consistent treatment plan, the scars can become much less visible, although complete disappearance is not guaranteed.
What is the best treatment for ice pick acne scars?
There is no single best treatment for every patient. Research shows that TCA CROSS, punch excision, subcision, and spot laser irradiation are all effective options for ice pick scars. TCA CROSS is particularly well studied, with clinical evidence demonstrating that it induces dermal collagen formation and produces significant improvement. A dermatologist can determine the best treatment or combination of treatments based on the depth and location of each scar.
Can I treat ice pick scars at home?
Some at-home products can help support the skin. Products containing benzoyl peroxide and salicylic acid are effective for treating acne, and topical retinoids are available without a prescription. These products can reduce breakouts and improve skin texture. However, deep ice pick scars rarely respond to surface treatments alone, so professional in-office procedures remain the most reliable way to meaningfully improve their appearance.
Cystic Acne Scar Treatment: How to Smooth Out Deep Scars
Cystic acne is one of the most severe forms of acne, and the scars it leaves behind can be just as challenging as the breakouts themselves. When deep nodules and cysts burst, they can damage the surrounding skin in ways that are difficult for the body to fully repair. The result is often a mix of depressed pits, uneven texture, and stubborn marks that remain visible long after the active acne has cleared. The good news is that cystic acne scar treatment has come a long way. Dermatologists now have a range of medically proven procedures that can smooth out deep scars and give the skin a more uniform appearance.
Why Cystic Acne Leaves Deep Scars
Any type of acne spot can lead to scarring, but scarring is more common when the most serious types of spots, namely nodules and cysts, burst and damage the skin around them. These deep lesions reach far beneath the surface, so when they rupture, the damage extends into the layers of skin responsible for maintaining a smooth, even texture. Severe acne scars form as a result of inflammation and uneven collagen healing, which can leave behind depressed marks, raised tissue, and lingering dark spots. Daily habits matter too. Scarring can also occur if you pick or squeeze your spots, so it is important not to add extra trauma while a cystic lesion is healing.
Types of Deep Acne Scars
Understanding the type of scar you have is the first step in choosing an effective cystic acne scar treatment. Most deep scars fall into a few recognizable categories.
- Ice pick scars: Ice pick scars are small, deep holes in the surface of the skin that look as if the skin has been punctured with a sharp object. These narrow channels extend below the surface, which is why they rarely respond to topical products alone.
- Rolling scars: Rolling scars are caused by bands of scar tissue that form under the skin. Instead of distinct holes, rolling scars give the skin a wavy, uneven appearance that can be especially noticeable in certain lighting.
- Boxcar scars: Boxcar scars are another category commonly described alongside ice pick and rolling scars in dermatology resources. A dermatologist can identify which scar types you have and recommend the treatment approach most likely to smooth them.
Professional Cystic Acne Scar Treatment Options
Many options are available for the treatment of acne scarring, including chemical peeling, dermabrasion, laser treatment, punch techniques, and fat transplantation. Some of the most popular in-office procedures include lasers, microdermabrasion, chemical peels, fillers, and surgery. Because cystic acne scars are often deep, a dermatologist may combine several methods to achieve the smoothest result.
Laser Resurfacing and Fractional CO2
Laser resurfacing is a popular non-surgical treatment for improving the appearance of acne scars. It works by stimulating collagen production and encouraging the skin to renew itself. For cystic acne scarring specifically, fractional CO2 laser treatment and microneedling are two of the most effective, medically proven treatment solutions available. Fractional CO2 creates controlled micro-damage in the skin, which triggers the body’s natural repair process and helps smooth out deep depressions over time.
Microneedling
Microneedling is another medically proven treatment for cystic acne scarring. The procedure uses fine needles to create tiny wounds in the skin, prompting the body to produce fresh collagen as it repairs the area. Over a series of sessions, this collagen remodeling can soften the appearance of deep scars and improve overall skin texture.
Dermabrasion
Dermabrasion involves removing the top layer of skin, either using lasers or a specially made wire brush. By carefully wearing away the damaged surface, this technique allows fresh skin to grow in its place. Dermabrasion can smooth the texture of the skin and reduce the visibility of acne scars, and it is often combined with other procedures for more extensive scarring.
Chemical Peels
Chemical peeling is one of the many effective treatment options for atrophic acne scars. During an in-office chemical peel, a chemical solution is applied to the skin to remove damaged outer layers and encourage new cell growth. Peels can be a good choice for patients who want to improve skin tone and texture without more invasive procedures.
Punch Excision
Punch excision is a minor procedure used for individual acne scars. During the treatment, your doctor cuts out the scar and repairs the wound with stitches or a skin graft. This method removes the damaged tissue entirely, allowing the skin to heal with a smoother, more even surface. Punch techniques are recognized as an effective option for acne scarring.
Steroid Injections
Steroid injections are used for scars that sit above the normal surface of the skin. Steroids are injected directly into a scar to soften the scar tissue, which can reduce its height. Usually you need several steroid injections to see the full benefit, so this treatment is planned over time rather than completed in a single visit.
Fillers and Fat Transplantation
Fillers and fat transplantation both add volume beneath a depressed scar, lifting it up to match the surrounding skin. Injectables and in-office procedures can produce a smoother contour, while fat transplantation is listed among the recognized treatment options for acne scarring. These approaches are often used as part of a broader treatment plan.
Surgery
Surgery is also listed among the popular in-office procedures used to treat acne scars. In selected cases, surgically revising the scar can improve the contour of the skin, particularly when other treatments have not produced the desired result.
At-Home Scar Care and Over-the-Counter Products
Not all scar care happens in the clinic. Over-the-counter products can play a supporting role, especially for scars that are still healing or for milder textural changes. Mederma Advanced Scar Gel, for example, is designed to treat old and new scars and to reduce the appearance of scars from acne, surgery, burns, injury, and stretch marks. Silicone scar gels are another widely available option. Topical products work on the surface of the skin, however. Deep cystic acne scars extend below that surface, which is why the most effective medically proven treatments, such as fractional CO2 and microneedling, are performed by a dermatologist.
Choosing a Dermatologist for Cystic Acne Scar Treatment
Deep acne scars require a provider who understands the structure of the skin and has experience with a range of corrective procedures. A board-certified dermatologist can assess your scar type, discuss realistic outcomes, and build a treatment plan that fits your skin. For patients in the South Denver area, Colorado Dermatology Center offers acne scar revision as one of its core services. The practice is led by board-certified dermatologist Dr. James M. Swinehart, who combines more than three decades of clinical expertise with advanced medical, surgical, and cosmetic dermatology. Personalized care and proven techniques are central to the practice’s approach, with the goal of improving both skin texture and confidence.
Frequently Asked Questions
Can cystic acne scars be treated effectively?
Yes. Dermatologists can treat cystic acne scarring with several medically proven options, including fractional CO2 laser treatment, microneedling, dermabrasion, chemical peels, punch excision, fillers, fat transplantation, and surgery. The right approach depends on the type of scars you have and how your skin responds. A board-certified dermatologist can recommend a plan tailored to your skin.
Do steroid injections help acne scars?
Steroid injections can help certain types of scars. Steroids are injected directly into a scar to soften the scar tissue, which can reduce its height, and most patients need several treatments. This makes steroid injections best suited for scars that sit above the surface of the skin rather than deep depressed pits.
Can picking or squeezing cystic acne cause scarring?
Yes. Scarring can occur if you pick or squeeze your spots, so it is important not to do this. Scarring is more common when nodules and cysts burst and damage nearby skin, which is exactly the kind of trauma that picking can cause. Allowing cystic lesions to heal without manipulation is one of the best ways to minimize long-term marks.
Are over-the-counter scar products enough for deep scars?
Over-the-counter products such as Mederma Advanced Scar Gel can reduce the appearance of scars from acne, surgery, burns, injury, and stretch marks, and they treat both old and new scars. Silicone scar gels are another common option. However, deep cystic acne scars typically form below the surface of the skin, and the most effective medically proven treatments for these scars are in-office procedures.
Cystic acne scarring can feel stubborn, but the skin is capable of meaningful improvement with the right treatment. Modern dermatology offers more ways than ever to smooth out deep scars, from fractional CO2 laser therapy and microneedling to punch excision and injectable fillers. The first step is a thorough evaluation by a dermatologist who can match the treatment to the scar. With a personalized plan and realistic expectations, smoother, more even skin is an achievable goal.

Acne Scar Treatment in Denver: Options That Actually Work
Acne scars can linger long after breakouts clear. For people in the Denver area, several treatment options are available that target different types of scarring. The right choice depends on the shape, depth, and age of the scars, as well as your skin type and treatment goals.
Acne scars are a common problem treated at dermatology practices across Denver. Treatments range from fractional laser resurfacing and microneedling to fillers, subcision, and chemical peels. Some procedures smooth the surface of the skin, while others work beneath it to release scar tissue. Many patients combine approaches to get the best results, and a board-certified dermatologist can help design a plan that fits your specific skin.
Why Acne Scars Form and What Treatment Needs to Do
Acne scars form when inflammation damages the skin’s collagen and elastin. When the skin heals, it can produce too little collagen, leaving a depressed or indented scar, or too much collagen, creating a raised scar. Most acne scars that patients seek treatment for are the depressed type, including rolling scars and boxcar scars.
Treatment needs to do one of two things: resurface the top layers of the skin to improve texture, or stimulate new collagen production to lift the depressed areas. Many advanced treatments do both. That is why dermatologists often recommend a plan rather than a single procedure. The best acne scar treatment in Denver depends on your scar type, so an accurate assessment is the first step.
Choosing the Right Treatment for Your Scar Type
There is no one-size-fits-all answer when selecting acne scar treatment in Denver. A dermatologist or licensed provider will examine your scars to determine whether they are rolling, boxcar, ice pick, or a mix of types. This matters because each type responds differently to treatment, and using the wrong approach can lead to disappointing results.
Rolling Scars and Boxcar Scars
Rolling scars have a wavy appearance and are caused by fibrous bands that tether the skin down. Boxcar scars are broader depressions with sharp edges. Both respond well to subcision, a technique that breaks up scar tissue underneath the skin. Subcision can help release soft, broad acne scars and help them float closer to the surface of your skin, lessening the shadowed effect that makes them visible.
Comparing Common Treatment Options
The table below summarizes how the most common acne scar treatments in Denver compare. Your dermatologist may recommend one of these alone or a combination, depending on the severity of your scarring.
| Treatment | How It Works | Best For |
|---|---|---|
| Fractional laser resurfacing | Creates thousands of tiny wounds in the skin while leaving surrounding tissue intact | Texture issues and general scar smoothing |
| Subcision | Uses a small needle to break fibrous bands under the skin | Rolling and boxcar scars |
| Microneedling and RF microneedling | Stimulates collagen production through controlled micro-injuries | Mild to moderate scarring |
| Fillers | Add volume beneath the scar to lift it level with surrounding skin | Deep, depressed scars |
| Chemical peels | Exfoliate the skin’s surface to improve texture | Superficial scarring and overall tone |
Fractional Laser Resurfacing
Fractional laser resurfacing is one of the most effective tools for acne scar treatment in Denver. This technology creates thousands of tiny wounds in the skin while leaving the surrounding skin intact. Those micro-wounds trigger the body’s natural healing response, which produces new collagen and smooths out the scarred area.
Colorado Dermatology Center specializes in fractional laser resurfacing to treat acne scars. The goal is to reduce the appearance of acne scars by smoothing the skin’s texture and stimulating collagen production. Because only a fraction of the skin is treated at a time, recovery is typically shorter than with older, more aggressive laser systems. Patients often notice gradual improvement as collagen remodeling continues over the following months.
Subcision for Depressed Scars
Subcision is designed for more extensive acne scarring. It is a specialized dermatological procedure that treats depressed acne scars by using a small needle to break down fibrous bands of scar tissue that pull the skin down. These bands are what cause the pitting and indentation seen on the surface.
By releasing these bands, the skin can lift and level out, significantly improving the texture and appearance of the affected areas. Subcision is most commonly applied to the face and is particularly effective for rolling scars, boxcar scars, and other types of atrophic acne scarring that cause depressions.
After the fibrous bands are released, the skin is free to remodel and produce fresh collagen, which helps the scar sit closer to the surface. Some providers combine subcision with laser treatments or fillers to maximize the final result. Because subcision is more invasive than a surface treatment, it should be performed by an experienced provider.
Microneedling and RF Microneedling
Microneedling uses fine needles to create controlled micro-injuries in the skin. Those injuries stimulate collagen production, which gradually fills in shallow scars and improves overall texture. Radiofrequency microneedling, such as Intracel RF microneedling, adds heat energy to the deeper layers of the skin for a stronger collagen response.
RF microneedling is a popular choice for patients who want noticeable improvement without the downtime associated with some laser treatments. It can be used on most skin types and is often combined with other treatments like subcision or fillers for more advanced scarring. A series of sessions is usually recommended, since collagen production builds gradually over time.
Fillers for Immediate Smoothing
Fillers offer a different approach to acne scar treatment. Instead of stimulating the skin to repair itself, a filler is injected beneath the scar to lift it up to the level of the surrounding skin. This can deliver an immediate improvement in the appearance of deep, depressed scars.
Fillers are not a permanent fix, since the body gradually absorbs the product over time. However, they can be an excellent option for patients who want fast results or for scars that are too deep to be fully corrected by collagen stimulation alone. Many Denver practices offer filler injections as part of a comprehensive acne scar treatment plan.
Chemical Peels for Surface Texture
Chemical peels work on the surface level of the skin. They exfoliate the outer layers, which helps reduce the appearance of superficial scarring and improves overall skin tone. Chemical peels are rarely enough on their own for deep acne scars, but they can complement laser and microneedling treatments by keeping the skin smooth and clear.
Patients with active acne may also benefit from peels as part of their ongoing skincare routine. A provider can recommend the right peel strength based on your skin type, tolerance, and the degree of textural damage. Multiple peels are typically needed to see meaningful change.
Scar Revision After Injury or Surgery
Acne is not the only cause of facial scarring. Injuries, surgical procedures, and burns can leave scars that patients want to improve. Scar revision in Denver helps patients improve the appearance of scars due to accidents, surgical procedures, or burns. Techniques may include laser treatments, surgical revision, or a combination of approaches, depending on the scar’s location and characteristics.
While scar revision cannot erase a scar completely, it can make it less noticeable by improving color, texture, and contour. The same collagen-stimulating principles used for acne scars often apply to other types of scarring.
What to Expect From Acne Scar Treatment in Denver
The first step in any acne scar treatment plan is a consultation. During that visit, a board-certified dermatologist will evaluate your scars, review your medical history, and discuss your goals. At Colorado Dermatology Center, care is led by Dr. James M. Swinehart, a board-certified dermatologist with more than three decades of clinical expertise. The practice is known for offering procedures that many practices do not, with an emphasis on personalized care, proven techniques, and natural-looking results.
Several Denver and South Denver practices offer acne scar treatments, including fractional laser resurfacing, Intracel RF microneedling, fillers, subcision, and chemical peels. Some practices also offer minor procedures that can be tailored to individual scar patterns. Because treatment recommendations vary widely, it is worth scheduling a consultation before committing to a specific procedure.
Patients often combine several treatments over the course of a year to achieve their best outcome. The exact number of sessions depends on the depth of the scars, the treatment used, and how your skin responds. Some procedures produce noticeable improvement after one session, while others require a series of treatments spaced several weeks apart. Collagen remodeling continues for months after treatment, so final results are usually assessed after the skin has fully healed.
Frequently Asked Questions
Here are answers to common questions about acne scar treatment in Denver.
Will acne scar treatment completely remove my scars?
Most treatments significantly reduce the appearance of acne scars, but complete removal is not always possible. The goal is usually to improve texture, soften edges, and lift depressed areas so scars blend with the surrounding skin. A dermatologist can give you a realistic expectation during a consultation based on your scar type and the treatment plan recommended for you.
How many sessions will I need?
The number of sessions varies by treatment and scar severity. Some patients see good results after one laser or subcision session, while others need multiple treatments spaced over several months. Collagen production takes time, so results continue to improve after the skin has healed. Your provider will tailor the plan to your specific needs and reassess progress at follow-up visits.
Do acne scar treatments hurt?
Most acne scar treatments are well tolerated. Providers use numbing creams, local anesthesia, or other comfort measures to minimize discomfort during the procedure. After treatment, you may experience redness, swelling, or a sunburn-like sensation, which resolves as the skin heals. Your provider will give you specific aftercare instructions to support recovery and protect your results.
Which treatment is best for my scar type?
There is no single best treatment for everyone. Rolling and boxcar scars often respond well to subcision, while superficial texture issues may improve with microneedling or chemical peels. Fractional laser resurfacing is a versatile option for many scar types. A board-certified dermatologist can examine your scars and recommend the right treatment or combination of treatments for your skin.

Does Medicare Cover Skin Cancer Screening? Coverage Facts
Skin cancer screening is one of the most common reasons people schedule an appointment with a dermatologist. For Medicare beneficiaries, however, the question of whether the visit will be covered is not always straightforward. The answer depends on why you are getting the screening, whether you have symptoms, and how the visit is classified by the dermatology office.
The short answer is that Medicare does not cover routine preventive skin cancer screening for people without symptoms. But Medicare can cover a dermatology visit when a patient has a specific skin concern. That distinction matters more than the type of exam being performed.
This article explains how Medicare treats skin cancer screenings, when a skin check may be covered, and what questions to ask before your appointment so you can plan your care with confidence.
Medicare Does Not Cover Routine Skin Cancer Screenings
Medicare does not cover screening for skin cancer in asymptomatic people. If you have no moles, spots, or symptoms that concern you, a full-body skin check scheduled solely to look for early signs of cancer is not covered as a preventive service.
Medicare also does not cover regular preventive melanoma screenings. The same rule applies to routine preventive dermatology screenings generally. Medicare doesn’t cover skin cancer screening as a free preventive benefit, and it won’t cover the screening if you don’t show signs of skin cancer.
This means that an annual skin check, scheduled for no other reason than to be checked, is treated differently from many other cancer screenings. Medicare pays for certain preventive screening tests used to help find cancer before you have signs or symptoms, but a routine skin cancer screening is not on that list.
Preventive Screening vs. Diagnostic Skin Exam
The key to understanding Medicare coverage for skin checks lies in the difference between a preventive screening and a diagnostic exam. A preventive screening is performed when you have no symptoms. A diagnostic exam is performed because you have a specific concern or symptom that needs evaluation.
| Preventive Screening | Diagnostic Exam | |
|---|---|---|
| Reason for visit | No symptoms or concerns | Specific mole, spot, or symptom |
| Typical Medicare coverage | Not covered | May be covered |
| Example | Routine full-body skin check | Evaluating a changing mole |
This distinction shapes whether Medicare will pay for your appointment. If a dermatologist examines a specific area of concern, performs a biopsy, or orders tests to evaluate a possible problem, that care is diagnostic. Medicare may cover services and tests related to diagnosing and treating skin cancer in those situations.
The same dermatologist, the same office, and even the same skin exam can be treated differently depending on the reason for the visit. If you walk in with no concerns, the visit may be considered a screening. If you point to a mole that has changed in size or color, the visit may be considered diagnostic.
When Medicare May Cover a Skin Cancer Screening
Medicare does cover a physician visit initiated by a concerned patient who has a specific skin concern. If you notice a new growth, a mole that has changed, a sore that will not heal, or any other symptom that worries you, that visit can be considered medically necessary.
Medicare does not typically cover regular skin cancer screenings as part of its preventive services unless the screening is deemed medically necessary by a physician. Once a concern is documented, the visit shifts from a screening to a diagnostic evaluation, and Medicare may pay for the appointment and related tests.
In practical terms, Medicare doesn’t cover “just-because” skin screenings, but it does cover follow-ups when you have a medical reason to be checked. Even if your dermatologist examines your entire skin during that appointment, the visit is rooted in a specific concern, which changes how it is billed and whether Medicare will contribute to the cost.
Ask your dermatology office about the scope of the exam as well. Many dermatologists perform a full skin examination even when the visit starts with a single concerning mole. That thorough approach is good medical care, but it does not automatically change whether the visit is classified as preventive or diagnostic. The documented reason for the appointment remains the deciding factor.
What Counts as a Medical Reason for a Skin Check
A medical reason for a skin check can be straightforward. A mole that looks different from your other moles, a new spot that is growing, a patch of skin that bleeds or itches, or a personal history of skin cancer can all justify a diagnostic visit.
When you schedule an appointment because of a specific concern, be clear about that concern when you book. The reason for the visit should be documented so that the appointment is coded as a diagnostic exam rather than a routine screening. This documentation can affect whether Medicare covers the visit.
If you are not sure whether your concern qualifies as a medical reason, it is reasonable to describe your symptoms to the scheduling team. The dermatology office can help determine how the visit should be classified and what that means for your coverage.
Why This Matters for People Who Need Regular Skin Checks
Some patients need skin checks more often than others. People with a personal history of skin cancer, a large number of moles, or significant sun damage may be advised to see a dermatologist regularly. Those recommendations make sense from a medical standpoint, but Medicare’s coverage rules are separate from your dermatologist’s advice.
Medicare may cover services and tests related to diagnosing and treating skin cancer, but coverage for a monitoring visit can vary depending on the circumstances. A visit to discuss a specific lesion may be covered, while a visit scheduled purely for routine monitoring may not be.
The most reliable way to know what your plan will pay is to ask the dermatology office how the visit will be billed and to check with Medicare directly. Knowing this before the appointment can help you make an informed decision about your care and avoid surprise bills.
Questions to Ask Before Your Appointment
Before you schedule a skin cancer screening, take a moment to ask a few practical questions. These questions can help you understand your financial responsibility and make sure the visit is set up correctly.
- Will this visit be billed as preventive screening or as a diagnostic exam?
- Is my specific skin concern documented in the appointment request?
- Will Medicare cover the visit, or will out-of-pocket costs apply?
- What should I expect if the dermatologist recommends a biopsy during the visit?
- Does my Medicare plan have different rules from original Medicare?
Because Medicare does not cover skin cancer screening as a free preventive benefit, a routine visit may come with out-of-pocket costs. If the visit is diagnostic, Medicare Part B may cover it, but your deductible and coinsurance could still apply. The dermatology office can help you understand how the visit will be coded before you arrive.
Frequently Asked Questions
Does Medicare cover a full-body skin check?
Medicare generally does not cover routine, full-body skin cancer screenings if you don’t have a specific skin concern. If the visit is purely preventive and you have no symptoms, Medicare will not typically pay for it. However, if a specific mole, lesion, or symptom prompted the full-body examination, Medicare may cover the visit as a diagnostic service.
Does Medicare cover a dermatologist visit for a suspicious mole?
Medicare does cover a physician visit initiated by a concerned patient who has a specific skin concern, and a suspicious mole qualifies. Because the visit is diagnostic rather than preventive, Medicare may cover the appointment and any related tests needed to evaluate the mole, including a biopsy if the dermatologist determines it is necessary.
Does Medicare cover melanoma screenings?
Medicare does not cover regular preventive melanoma screenings. However, Medicare may cover services and tests related to diagnosing and treating skin cancer, including melanoma. If a symptom or concern leads to a melanoma evaluation, the diagnostic visit and related care may be covered, even though routine melanoma screening is not included as a preventive benefit.
How much does a skin cancer screening cost with Medicare?
The cost depends on how the visit is billed and the specifics of your Medicare coverage. Since Medicare does not cover skin cancer screening as a free preventive benefit, a routine screening may involve out-of-pocket costs. A diagnostic visit triggered by a concern may be covered under Medicare Part B, but your deductible and coinsurance may still apply. Contact Medicare or your plan to confirm the expected costs before your appointment.
If you have a skin concern that needs evaluation, the team at Colorado Dermatology Center can help you understand your options for skin cancer screening and treatment. Board-certified dermatologist Dr. James M. Swinehart and the practice specialize in diagnosing and treating skin cancer, including basal cell carcinoma, squamous cell carcinoma, and melanoma. Scheduling a visit with a specific concern in mind is the best way to make sure your skin check is both medically useful and aligned with Medicare’s coverage rules. Contact the office to discuss your skin health and to confirm how your visit will be handled.

How Often Should You Get a Skin Cancer Screening?
Skin cancer is one of the most commonly diagnosed forms of cancer in the United States. Estimates suggest that about 1 in 5 Americans will develop some form of skin cancer by the age of 70, which makes regular skin checks an important part of staying healthy. But the question many people ask is simple: how often should you get a skin cancer screening?
The answer depends on several factors, including your age, personal history of skin cancer, and other risk factors. Some people only need a screening every few years, while others should be seen at least once a year. Understanding the general guidelines can help you know what to expect and when to schedule your next appointment.
What Is a Full-Body Skin Cancer Screening?
A professional skin cancer screening is a visual examination of your skin. A dermatologist, a doctor who specializes in skin health, looks for suspicious spots, moles, or growths. This type of check is sometimes called a total body skin examination because it involves looking at your entire body, not just the areas that are exposed to the sun.
The three most common types of skin cancer are basal cell carcinoma, squamous cell carcinoma, and malignant melanoma. Each type can look different on the skin, which is why a trained dermatologist performs the examination. Professional screenings are designed to find suspicious changes early, before they have a chance to grow or spread.
General Screening Guidelines for Most Adults
For most adults, a professional full-body skin exam once a year is the most common recommendation. Many dermatologists suggest an annual visit so that any new or changing spots can be assessed promptly. A yearly screening also gives you a chance to ask questions about your skin and learn about any areas that need monitoring.
However, not everyone needs to see a dermatologist every year. A dermatologist at Harvard-affiliated Beth Israel has explained that skin checks every two to three years are sufficient for roughly 80% of people. For this majority, a screening every few years may be enough to stay on top of skin health without unnecessary appointments.
The general advice for most people is that a routine check every few years may be enough, but annual visits are recommended for those with a history of skin cancer or other risk factors. Your dermatologist can help you figure out which category you fall into.
| Screening schedule | Who it applies to |
|---|---|
| Every two to three years | Most adults with no significant risk factors |
| At least once a year | Adults aged 35 to 75 who have risk factors |
| At least once a year | People with a history of skin cancer |
| Determined by your dermatologist | People who need more frequent monitoring |
Screening Recommendations for High-Risk Individuals
Certain adults should be screened more regularly. According to data-driven screening recommendations, adults aged 35 to 75 with one or more risk factors should have a total body skin examination at least annually. This age range covers a period when skin damage may begin to show up as concerning changes that merit closer attention.
People who have already been treated for skin cancer also need ongoing surveillance. Most dermatologists recommend at least an annual visit to monitor for recurrence or new cancers. In some cases, a dermatologist may recommend a more frequent schedule for people who have had concerning spots removed, and some patients report being seen about every six months. The right interval should always be confirmed with a dermatologist who understands your medical history.
If your risk is high, waiting several years between appointments is not advised. An annual screening gives your dermatologist the opportunity to catch new or recurring skin cancers early, when treatment options are more likely to be effective.
Monthly Skin Self-Exams: What to Look For
Professional screenings are not the only tool for catching skin cancer early. Checking your skin on a regular basis helps you become familiar with your own moles and spots, so you can notice changes quickly. Many organizations, including the CDC and Memorial Sloan Kettering Cancer Center, recommend performing a skin self-exam about once a month.
During a self-exam, you should look for new spots or moles, as well as existing moles that have changed in size, shape, or color. It is also important to check less visible areas of your skin, such as your back, scalp, behind your ears, and between your toes. These hidden spots are easy to overlook, but they can still develop skin cancer.
Monthly self-exams do not replace a professional screening. They work alongside it. If you find something suspicious between professional appointments, you can contact your dermatologist and schedule a visit sooner. Talk to your doctor about how often you should perform a self-exam, because your personal risk level may change the recommendation.
How to Choose the Right Screening Schedule for You
Choosing the right schedule starts with an honest look at your risk factors. Age, a history of skin cancer, and other personal factors all influence how often you should be screened. For some people, a screening every two to three years is perfectly safe. For others, an annual total body skin examination is the minimum.
During a skin cancer screening, your dermatologist can also give you personalized guidance on how often you should return. If you have risk factors that call for more frequent exams, your dermatologist will tell you. If your skin is clear and your risk is low, you may be told that a check every few years is enough.
At Colorado Dermatology Center in the South Denver area, the practice is led by board-certified dermatologist Dr. James M. Swinehart and focuses on medical, surgical, and cosmetic dermatology, with special emphasis on skin cancer treatment, including MOHS micrographic surgery. A complete skin examination can provide peace of mind and a clear plan for your next visit.
No matter what schedule you follow, the goal is the same: catch skin cancer early, when it is most treatable. Regular professional screenings combined with monthly self-exams give you the best chance of noticing changes in your skin before they become a bigger concern. If it has been more than a year since your last total body skin examination, consider scheduling an appointment and asking your dermatologist how often you should be screened.
Frequently Asked Questions
How often should I get a skin cancer screening?
For most adults, a full-body skin cancer screening once a year is a common recommendation. However, some experts note that people with low risk may only need a screening every two to three years. Adults aged 35 to 75 with risk factors should be screened at least annually. Your dermatologist can recommend the right schedule based on your personal history and skin type.
Why do some people need skin cancer screenings more often?
People with a history of skin cancer are usually advised to have at least an annual visit to monitor for recurrence or new cancers. Adults aged 35 to 75 who have one or more risk factors should also be screened at least once a year. In some cases, a dermatologist may recommend a more frequent schedule, such as every six months, depending on your history.
How often should I check my skin at home?
A monthly skin self-exam is a common recommendation from organizations like the CDC and Memorial Sloan Kettering Cancer Center. You should look for new spots or moles, as well as changes in existing moles. Checking less visible areas, such as your scalp, back, and between your toes, is also important. Talk to your doctor about how often you should check your skin.
What happens during a full-body skin cancer screening?
A full-body skin cancer screening, sometimes called a total body skin examination, is a visual exam performed by a dermatologist. The doctor examines your entire skin surface for suspicious spots, moles, or growths. The exam includes hard-to-see areas that are easy to miss during a self-check, which is one reason professional screenings are valuable for early detection.

Free Skin Cancer Screening Denver: Where to Find Free Skin Checks
Colorado’s sunshine and year-round outdoor activities draw people outside in every season. That same sun exposure increases the risk for skin cancer, which makes regular screening an important part of staying healthy. The good news is that free skin cancer screening in Denver is available through several programs, including mobile clinics, annual community events, and dermatology practices that offer no-cost exams to new patients.
Skin cancer is more common than many people realize. One in five people of all skin colors in the United States will get skin cancer at some point. When found early, skin cancer is highly treatable, and free screening programs are designed to help more people catch it in its earliest stages.
Why Free Skin Cancer Screenings Matter
Dermatologists recommend annual total-body skin cancer exams to check for suspicious moles, growths, and other changes. The American Academy of Dermatology’s free skin cancer check program is the organization’s longest-standing public health program, and dermatologists have conducted more than 2.9 million free checks through it. These exams give people who may not have regular access to a dermatologist a chance to have their skin evaluated at no cost.
Colorado’s environment adds to the importance of these screenings. The state is known for its sunshine and year-round outdoor activities, and that combination creates an increased risk for skin cancer. Free screening events help address that risk by making skin checks accessible to more residents across the state.
Free Skin Cancer Screening Options in Denver
Several organizations and practices offer free or low-cost skin cancer screenings in the Denver area. Options range from statewide programs with updated screening lists to mobile clinics that travel to different neighborhoods.
Colorado SPOT Me Program and Trailhead Institute
The Colorado Cancer Coalition supports the SPOT Me program, which connects people with free skin cancer checks available across the state. Trailhead Institute, located at 1999 Broadway, Suite 600 in Denver, is one of the contact points for this program. The coalition directs people to a current listing of free screenings in Colorado through the American Academy of Dermatology’s online find-a-screening tool, which is updated regularly to reflect new events.
SPOT Skin Cancer Screening at Intermountain Health
Intermountain Cancer Center at Lutheran hosts an annual SPOT Skin Cancer Screening event through the American Academy of Dermatology. Dermatologists volunteer their time and expertise to provide skin cancer screenings as a free service to the community. The event takes place at the Red Rocks Medical Center location. Like other annual community screening events, this program gives people a chance to see a volunteer dermatologist without an insurance bill.
The Sun Bus Mobile Dermatology Clinic
The Sun Bus is a free mobile dermatology clinic that provides free skin screening along with sun safety education. Visitors can also receive EltaMD sunscreen and Heliocare products during the bus’s stops. The program operates in Colorado, and people can call (303) 876-7664 for details on where the bus will be and when.
Destination Healthy Skin Mobile Unit
The Skin Cancer Foundation’s Destination Healthy Skin program brings a mobile screening facility to communities for free full-body skin exams. The exams are performed by licensed dermatology professionals, and no appointment is necessary. The mobile unit is designed to make the screening process convenient, so people can stop by without arranging ahead of time.
Colorado Dermatology Center
Colorado Dermatology Center provides customized skin cancer screening and treatment at 1601 E 19th Ave, Suite 4450 in Denver. The practice can be reached at 303-744-1202. Its office hours are Monday through Friday from 7 am to 5 pm, with a closed period from 12 pm to 1 pm. While this center focuses on screening and treatment, it is a helpful resource for anyone who needs a skin exam in Denver.
Denver Health Cancer Screening Mobile Health Center
Denver Health operates the Cancer Screening Mobile Health Center as part of its network of federally qualified community health centers. The mobile center is designed to bring cancer screening services into surrounding communities. Because this is one of several cancer screening resources in the Denver area, anyone interested should contact Denver Health directly for current information about services, schedules, and eligibility.
How to Find Updated Free Screening Schedules
Free skin cancer screening events change throughout the year, so checking current listings is the best way to find an opening. The American Academy of Dermatology publishes a state-by-state list of free screenings, including a dedicated page for Colorado. The Colorado Cancer Coalition also points residents to that same tool for an up-to-date listing of free skin cancer checks across the state.
The Prevent Cancer Foundation maintains resources that can help locate free and low-cost cancer screenings in your area. That includes links to free skin cancer screening programs such as those offered by the Skin Cancer Foundation. Combining these online tools with local program listings gives you a complete picture of what is available near Denver.

What to Expect at a Free Skin Cancer Screening
Free skin cancer screenings are typically quick appointments focused on checking your skin for signs of cancer. During the exam, a dermatology professional looks at your skin for suspicious moles, growths, or other changes.
- Most screenings at mobile clinics involve a full-body skin exam performed by a licensed dermatology professional.
- Some programs, such as Destination Healthy Skin, do not require an appointment, while others ask you to book a slot in advance.
- Bring a list of any moles or spots you are concerned about so you can point them out during the exam.
- The screening is educational as well as medical. Many programs also share sun safety information and skin cancer prevention tips.
After the Screening: Next Steps
If the screening finds something suspicious, the next step is a follow-up visit with a dermatologist for a closer look and possible biopsy. If the area is determined to be noncancerous, the screening professional will usually tell you when to come back for your next check. For those who need ongoing care, board-certified dermatologists in Denver, such as Dr. James M. Swinehart at Colorado Dermatology Center, specialize in skin cancer treatment including MOHS micrographic surgery. Early detection remains the goal, and free screenings are a practical way to stay on schedule with your skin health.
Frequently Asked Questions
Here are answers to common questions about free skin cancer screening in Denver.
Are free skin cancer screenings really free?
Yes. The programs listed above provide skin cancer screenings at no cost to the participant. The American Academy of Dermatology’s free skin cancer check program relies on volunteer dermatologists, and organizations like the Skin Cancer Foundation operate mobile units that offer free full-body exams. Some practices, such as Advanced Dermatology, offer free screenings specifically for new patients, so be sure to confirm any eligibility requirements when you book.
Do I need an appointment for a free skin cancer screening?
It depends on the program. The Destination Healthy Skin mobile unit does not require an appointment, so you can simply stop by when it is in your area. Other events, including annual SPOT screenings and practice-based exams, may ask you to register ahead of time. The Sun Bus can be reached at (303) 876-7664 for scheduling details, and Advanced Dermatology accepts bookings by phone or online.
Who performs free skin cancer screenings?
Most free screenings are performed by dermatology professionals. At Destination Healthy Skin, exams are completed by licensed dermatology professionals. At SPOT Skin Cancer Screening events, dermatologists volunteer their time and expertise to provide the exams at no cost. The American Academy of Dermatology’s free screening program has conducted more than 2.9 million checks since it began.
How often should I get a skin cancer screening?
The American Academy of Dermatology recommends annual total-body skin cancer exams by a dermatology professional. People with a history of skin cancer, heavy sun exposure, or many moles may need more frequent checks. Free screening events in Denver are a good way to keep up with that yearly schedule, and mobile clinics make it easier to fit a skin check into your routine.
What happens if a screening finds something suspicious?
If the screening professional sees a mole or growth that looks concerning, they will recommend a follow-up appointment with a dermatologist. A dermatologist can examine the area more closely and decide whether a biopsy is needed. Early detection makes skin cancer highly treatable, which is why these free programs exist in the first place.
Skin Cancer Screening Cost Without Insurance: Prices, Free Options, and More
Skin cancer screenings are a routine part of dermatology care, but the cost without insurance can feel uncertain. If you are paying out of pocket, the price of a screening depends on the type of visit, the provider you see, and whether any additional procedures are needed. Knowing what those visits typically cost can help you plan ahead and find affordable options in your community.
The figures below come from published health sources and reflect general estimates. Actual charges vary by practice and region, so the numbers here are a starting point for your own research rather than a guarantee of what any single dermatology office will bill.
What Does a Skin Cancer Screening Cost Without Insurance?
For a straightforward visual skin check without a biopsy, many uninsured patients see charges that commonly range from about one hundred to three hundred dollars. Most estimates put a standard full-body exam at $100 to $250, with some sources reporting up to $300 for a complete body check by a dermatologist.
The office visit is the largest part of the cost. A screening typically includes about $100 for the appointment so a dermatologist can examine your skin. In total, a skin cancer screening without insurance generally costs $100 to $200, though reports from national price comparison tools and dermatology practices indicate that a standard screening or mole removal can range from $150 to over $400 depending on the region and the complexity of the visit.
Because prices vary so widely, it is a good idea to request a price estimate before booking an appointment. Many dermatology offices will share a breakdown of the exam fee over the phone, and some offer discounts for patients who pay at the time of the visit. Asking about the charge for a new patient visit and a full-body exam before scheduling can prevent surprises on the bill.
Why the Price of a Skin Screening Varies
No single price applies to every skin cancer screening. The final cost depends on several factors that can change the total from one patient to the next.
Full-Body Exam vs. Targeted Check
A full-body skin exam is more involved than a focused check of one mole or spot. The cost of a full-body exam typically ranges from $100 to $250 without insurance. A targeted check of a single lesion may be billed as a shorter visit, which can lower the price. Clarify with the office ahead of time whether you are booking a complete exam or a limited consultation.
Biopsies and Additional Procedures
If the dermatologist sees a suspicious spot during the screening, a biopsy may be recommended on the spot. Biopsies can range from $150 to $400 before insurance. The final cost depends on the size and location of the biopsy, the technique used, and whether the tissue sample is sent to a laboratory for analysis. That lab fee is usually separate from the biopsy procedure itself, so ask for a full estimate that includes both the procedure and the pathology reading.
Location and Provider Type
Dermatology practices in higher-cost regions tend to charge more than providers in other areas. The same exam can cost more in a large city than in a smaller community. Board-certified dermatologists may also have higher exam fees than other providers who perform skin checks. Comparing prices at a few local practices can help you find a rate that fits your budget.
Do Health Plans Cover Skin Cancer Screenings?
Many health insurance plans help cover an annual skin cancer screening. Most private insurance companies, as well as Medicare and Medicaid, cover the costs of certain routine cancer screenings. However, skin cancer screening is not always included in the list of preventive services that are covered with no cost sharing.
If you have coverage, contact your health plan directly to ask whether a skin cancer screening is considered a preventive benefit. If it is, the exam may be covered at no cost to you. If the plan does not cover it, the screening will be billed as an office visit, and you may be responsible for a copay, coinsurance, or deductible depending on the design of your plan.
Free and Low-Cost Skin Cancer Screening Options
People without insurance still have options for getting their skin checked. The American Academy of Dermatology runs a free skin cancer check program that is its longest-standing public health initiative. Through this program, dermatologists have conducted more than 2.9 million free checks. The organization provides a search tool on its website to help you find participating screenings in your area.
Individual dermatology practices sometimes offer free skin cancer screenings for new patients as a way to encourage early detection. These offers vary by practice and may be limited to certain dates or times of year, so it is worth contacting local offices directly to ask whether they have any free screening days or new patient promotions.
If you do not have health insurance, a variety of resources can help you locate free and low-cost medical care in your community. You can also contact your local hospital or health care facility to ask whether they offer routine cancer screening through their foundations or outreach programs. Some facilities offer mobile testing that brings screening services directly to neighborhoods.
What If You Think You Have Skin Cancer and Don’t Have Insurance?
If you have a concerning mole or spot and do not have coverage, the first step is to find a screening program or clinic that charges on a sliding scale. Community health centers, hospital outreach programs, and free screening events are all reasonable places to start. A screening can tell you whether the spot needs a biopsy, which is the only way to confirm a skin cancer diagnosis.
Waiting to have a suspicious spot checked can allow a potential problem to grow. One in five people of all skin colors will get skin cancer in their lifetime, and the condition is highly treatable when found early. Contacting a local dermatology office to ask about payment plans or cash discounts may also make the visit more affordable. The earlier a suspicious spot is examined, the sooner you can learn whether a biopsy is needed.
Frequently Asked Questions
How much does a skin cancer screening cost out of pocket?
Without insurance, a full-body skin exam typically costs $100 to $250, with some sources reporting a range of $100 to $300. The office visit accounts for roughly $100 of that total. If a biopsy is needed during the visit, the biopsy can add $150 to $400 to the bill before insurance.
Can I get a free skin cancer screening?
Yes. The American Academy of Dermatology sponsors a free skin cancer check program that has provided more than 2.9 million free checks. Some dermatology practices also offer free screenings for new patients or host screening events at certain times of the year. Local hospitals and health care facilities may offer free or low-cost screenings through their foundations or outreach programs.
What if I think I have skin cancer but I don’t have insurance?
Contact local hospitals, community health centers, or dermatology practices to ask about sliding-scale fees, payment plans, or free screening events. A screening can tell you whether the spot needs a biopsy, which is the only way to confirm a diagnosis. Most dermatology offices can give you an estimate of the cost before your appointment.
Does health insurance cover skin cancer screening?
Many health plans help cover an annual skin cancer screening, and most private insurers, Medicare, and Medicaid cover certain routine cancer screenings. However, skin cancer screening is not always included in the preventive services that are free to the patient. Contact your plan to confirm whether the exam is covered and what your out-of-pocket cost would be.
Skin Cancer Screening in Denver: What Happens During a Full-Body Exam
Colorado is known for its sunshine and year-round outdoor activities, and that same sunny climate comes with an increased risk for skin cancer. Regular screening makes it possible to find skin cancer early, when it is highly treatable. For anyone in the Denver area, a full-body skin exam is one of the most direct ways to stay ahead of the disease. Knowing what happens during a full-body exam can help you walk into your appointment with confidence.
Why Skin Cancer Screening Matters in Denver
Denver residents spend more time outdoors than people in many other parts of the country. High-altitude sunshine means stronger UV exposure, and year-round recreation keeps skin in the sun during every season. The result is clear: Colorado is known for its sunshine, its year-round outdoor activities, and an increased risk for skin cancer.
That increased risk makes regular screening more than a precaution. When skin cancer is diagnosed and treated early enough, nearly all cases are curable. The more time it takes to identify skin cancer, the harder and more difficult treatment becomes. A routine screening appointment can catch suspicious spots long before they become a larger problem.
Who Should Consider Regular Skin Cancer Screening
Anyone can develop skin cancer, but some people face a higher risk than others. A personal or family history of skin cancer, a large number of moles, a history of sunburns, and years of outdoor activity all raise the odds. The American Academy of Dermatology’s SPOT program is designed to help people find out whether they are at high risk and learn how to monitor changes in their skin. If any of these risk factors apply to you, a full-body exam with a dermatologist is a reasonable next step.

What Happens During a Full-Body Skin Exam
A full-body skin examination is exactly what it sounds like: a head-to-toe check of your skin. If you have never had one, knowing what to expect can make the appointment feel more comfortable.
Scalp to Toes Examination
During a full-body skin check, the dermatologist examines your skin from scalp to toes. This includes areas that are easy to overlook, such as the scalp, behind the ears, between the toes, and the backs of the legs. The exam is thorough by design because skin cancer can appear in places that rarely see the sun.
You will be asked to undress to your underwear and wear a medical gown so the dermatologist can see all of your skin. The appointment is clinical and professional, and the goal is simply to check every spot for signs of skin cancer.
Specialized Magnifying Devices
Dermatologists do not rely on the naked eye alone. During a screening, they use specialized magnifying devices to look closely at suspicious spots. A dermatoscope is a handheld tool that allows the doctor to see structures in the skin that are not visible without magnification. This helps the dermatologist tell the difference between a harmless mole and something that needs a closer look.
Photography and Skin Mapping
Many practices use medical photography, also called skin mapping, during the screening process. Full-body skin examinations and medical photography are among the most powerful tools in skin cancer detection. The dermatologist takes photos of suspicious spots to document their size, shape, and color. At future appointments, those images can be compared to see whether anything has changed.
Skin mapping is especially useful for people with many moles or a history of sun damage. A visual record makes it easier to spot changes over time, and it gives many patients peace of mind between visits.
How to Prepare for Your Appointment
Preparing for a full-body skin exam is simple, but a few steps can make the screening more effective. The goal is to give the dermatologist a clear view of every area of your skin.
- Skip makeup, nail polish, and heavy lotion so your skin is fully visible.
- Wear your hair loose or pulled back so your scalp and neck can be examined.
- Make a mental list of spots that have changed, itched, bled, or looked different.
- Bring details about your personal and family history of skin cancer.
Tell the dermatologist about any spots that concern you at the start of the appointment. The more the doctor knows about your skin history and sun exposure, the more accurate the screening can be.
How to Perform a Self-Exam Between Screenings
Skin exams do not end when you leave the dermatologist’s office. Checking your own skin between screenings helps you catch changes early. Look for new spots, growths that are changing, or sores that do not heal. Pay attention to moles that look different from the rest or that change in shape and color.
Use a full-length mirror and a hand mirror to check your back, scalp, and other hard-to-see areas. If anything looks different, call a dermatology practice to schedule an exam. Early detection gives you the widest range of treatment options.
Where to Get a Skin Cancer Screening in Denver
Several dermatology practices and community programs in the Denver area offer skin cancer screening. Options include private practices, free community events, and mobile clinics.
Private Dermatology Practices
Denver Dermatology Center provides customized skin cancer screening and treatment. It is located at 1601 E 19th Ave #4450 in Denver and can be reached at 303-830-2900. The practice is open Monday through Friday, and patients should call to confirm current hours.
Alta Vista Dermatology offers skin cancer screening for the Denver and Highlands Ranch areas. Call 303-888-6426 to schedule a consultation.
Cara Mia Dermatology, located in Denver, also provides skin cancer screenings. Its free screenings require a phone call to book at 866-400-3376. They are valid for new patients only and are subject to limited availability at participating locations.
Colorado Dermatology Center, led by board-certified dermatologist Dr. James M. Swinehart, serves the South Denver area. The practice focuses on medical, surgical, and cosmetic dermatology, with special emphasis on skin cancer treatment and MOHS micrographic surgery. The center also offers hair restoration, acne scar repair, and clinical research trials.
Free and Community-Based Screenings
Free skin cancer screenings are available across the state of Colorado through the American Academy of Dermatology’s SPOT me program. The Colorado Cancer Coalition provides an up-to-date listing of free skin cancer checks, with offices at Broadway, Suite 600 in Denver, Colorado 80202. Area dermatologists volunteer their time and expertise for these events.
Intermountain Health hosts an annual SPOT Skin Cancer Screening event at its Red Rocks Medical Center. The event is offered at no cost to participants, and dermatologists volunteer through the American Academy of Dermatology. Anyone interested should confirm scheduling details with the organizer before traveling.
The Sun Bus is a free mobile dermatology clinic that provides free skin screening, sun safety education, and sunscreen products such as EltaMD and Heliocare. Call (303) 876-7664 to find out where the bus is headed next.
What Happens If Your Doctor Finds Something Suspicious
If the dermatologist finds a spot that looks concerning, the next step is usually a biopsy. A biopsy removes a small sample of skin tissue and sends it to a laboratory for analysis. Skin cancer detection in Denver often begins with a skin exam and is confirmed with a biopsy, and many practices perform both in the same office.
Most biopsied spots turn out to be benign. If the results do show skin cancer, early diagnosis keeps treatment options open. Skin cancer comes in several forms, including basal cell carcinoma, squamous cell carcinoma, and melanoma. Depending on the type and stage, treatment may include removal of the lesion, MOHS micrographic surgery, or other procedures. Nearly all cases are curable when they are diagnosed and treated early enough.
Frequently Asked Questions
Can I get a free skin cancer screening in Denver?
Yes. Free skin cancer screenings are available across Colorado through the American Academy of Dermatology’s SPOT me program. The Sun Bus also provides free mobile screenings with sun safety education and sunscreen products. Some private practices, including Cara Mia Dermatology, offer free screenings for new patients, subject to availability. Calling ahead is required to confirm scheduling and eligibility.
How much does a skin cancer screening cost?
Costs vary by practice and insurance coverage. Some screening options in Denver are free, including AAD-hosted events, The Sun Bus, and new-patient promotions at participating clinics. Most dermatology practices accept insurance for medical skin exams. To get an accurate cost estimate, contact the specific practice directly and ask about pricing, insurance, and any available free screening programs.
What should I expect during a full-body skin exam?
A full-body skin check covers your skin from scalp to toes. The dermatologist will inspect your scalp, ears, back, legs, and other areas using specialized magnifying devices. Suspicious spots may be photographed for your medical record. The exam is generally quick, and you will be given a gown for the appointment. Tell the doctor about any spots that have changed or concern you.
How often should I get a skin cancer screening?
The right screening schedule depends on your personal risk. People with a history of skin cancer, many moles, or significant sun exposure may need more frequent exams. Others may only need an annual check. Your dermatologist can recommend a schedule based on your skin type, family history, and sun exposure. Regular self-exams between visits are also useful for noticing changes early.
ACTINIC KERATOSIS
“Actinic= sun-related; “keratosis”= rough, thick skin. Up to 15% of these precancerous spots can turn into squamous cell carcinomas, so it is important to treat them. Therapies include liquid nitrogen, chemical peels, 5-Fluorouracil, diclofenac, imiquimod, and ingenol mebutate. Any actinic keratoses that recur after these treatments should be biopsied to evaluate for the presence of skin cancer.
PSORIASIS
Although the exact molecular or genetic causes have yet to be identified, psoriasis is often triggered by infections including bacteria, viruses (including strep), and fungi. In the past, treatments have included UV light, antibiotics, sulfasalazine, and topical agents. However, many types of injectables, including monoclonal antibodies, are now also available.
Contact Dermatitis
Contact dermatitis (an allergic rash on the skin) is generally caused by external allergens. Although scratch tests and blood tests can be used to diagnose hay fever or asthma, patch testing is used to diagnose contact dermatitis. A standardized series of 36 tests is applied to the back on Day 1, removed 2 days later, and read 3 days later. The offending allergens can be avoided to decrease the risk of recurrence.
TREATMENT OF DEEP WRINKLES
Injectables, including those with hyaluronic acid, generally last for only a few months. Botox is mostly effective for wrinkles around and above the eyes. Facelifts are pricey and involve major surgery. However, dermal grafting offers a permanent solution for deep facial wrinkles. With this method, dermal tissue is removed from beneath the skin behind the ear and placed under the deep creases via a tiny incision. Since this involves your own tissue, the risk of rejection is minimal.
Neck Lift
Sagging neck skin can be caused by a combination of excess fat, loose skin, and platysma (superficial) neck muscles. Less invasive than a full face lift, a neck lift at the Colorado Dermatology Center involves removing the excess fat first by liposuction. The cannulas can be extended up onto the lower cheek to effect some tightening of the skin. In addition, another incision can be made under the chin in order to treat the platysma muscles.
CAN COSMETICS CAUSE ACNE?
Yes! Many cosmetics, especially those containing oils, are “comedogenic” (i.e. cause”comedones” or blackheads). Moisturizers with oils can also clog pores and cause acne. In contrast, our “Regine” line is noncomedogenic and hypoallergenic.
DO SUNSCREENS DAMAGE CORAL REEFS?
Although no controlled studies exist, it seems unlikely that a gram of sunscreen diluted by a cubic mile of ocean could be as much as culprit in damaging reefs as the pollution from automobiles, trucks, planes, boats , cruise ships, or waste runoff from homes or industrial sources.
SUNSCREENS-WHAT IS SPF?
A Sun Protection Factor (SPF) of 30 means that it takes 30 times as long to sunburn with a sunscreen as it would to sunburn with no sunscreen at all. For instance, if you normally would start to burn within 30 minutes without sunscreen, it would take 15 hours to burn with the SPF 30 sunscreen on (30 x .5). Since it is rare to be in the sun for 15 hours, a SAPF 30 sunscreen would be more than adequate.
EYELIFT
Sagging upper eyelid skin, in the absence of eye muscle abnormality, can be removed via a blepharoplasty, or upper eyelid lift, under local anesthesia in the office. Unless your vision is completely obstructed, this procedure is considered cosmetic in nature.
LEG VEINS
Larger veins and varicose veins are ofter treated in vein clinics via lasers or ultrasound. However, smaller 1-2 mm veins, also known as “spider veins” or “telangiectasias” , are considered cosmetic in nature and are treated by a dermatologist with sclerotherapy. Hypertonic saline, although slightly stinging when injected, minimizes the risk of allergy, since saline is found in your own body.
DERMABRASION vs. MICRODERMABRASION
Microdermabrasion, generally only effective for very fine lines, involves the use of a stream of fine sand particles. Dermabrasion, on the other hand, uses a motorized wire brush on a diamond wheel (under local anesthesia). To treat deeper facial wrinkles and acne scars, the combination of dermabrasion, dermal grafting and punch elevation can often produce considerable improvement of deep facial scars.
WHICH CHEMICAL PEEL IS BEST?
Jessner’s peels (“lunchtime peel” or “model’s peel”) are only used for the earliest, finest lines. Phenol peels. including the Baker’s peel and the 88% phenol peels, are employed for the deepest facial lines. In between these, trichloroacetic acid (TCA) peels may be combined with 50%–70% glycolic acid peels. Salicylic acid ointment peels. often combined with Jessner’s solution and dermasanding, can treat severe sun damage on the arms and legs.
Treatment of Sunken Acne Scars and Wrinkles
Do your acne scars or facial areas and line look like deep valleys in the mirror? These can be filled in, for a less sunken appearance, with subcision and dermal grafting.
Your own tissue from beneath the skin behind your ear is inserted. Under local anesthesia under each scar, facial line, or deep wrinkle. Since it is taken from you, there is minimal chance of rejection. The implants are permanent, unlike artificial fillers. Call today for a consultation, our number is 303-744-1202!
Acne
Acne is a common skin condition that affects a significant portion of the population, particularly adolescents and young adults, although it can persist into adulthood. Multiple factors – including hormonal fluctuations, genetics, and environmental influences – contribute to the pathogenesis of acne. Effective treatment is essential for both cosmetic and psychological well-being.
The development of acne is driven by four key factors: increased sebum production, follicular hyperkeratinization, bacterial proliferation, and inflammation. These elements contribute to clogged pores, and the subsequent inflammatory responses lead to the characteristic lesions of acne.
Acne is most commonly treated with topical treatments and oral medications. However, one advanced option available at Colorado Dermatology Center is dry ice cryotherapy. This method uses powdered carbon dioxide to deliver a cooling effect to the skin, helping to reduce inflammation, shrink pores, and promote the appearance of acne scars. This treatment is particularly effective for those with persistent acne, that hasn’t responded well to traditional treatments. There are several benefits to dry ice treatment: it’s noninvasive, reduces inflammation, and improves skin texture.
Acne remains a complex condition with diverse triggers and manifestations, requiring individualized management. Dry ice therapy offers a promising adjunct to conventional acne treatments, particularly those with cystic acne. For more information on this advanced treatment and to schedule a consultation, please contact our office at 303-744-1202.
Treatment of Deep Pitted Acne Scars
Deep acne scars that are less than 3mm ( 1/8 “) wide can be treated with punch elevation or punch grafting. Under local, a cylindrical core containing the scar is first removed, or raised up level with the surrounded skin. Next, a small graft is inserted, and a tiny dissolving suture is placed. Call 303-744-1202 for a consultation.
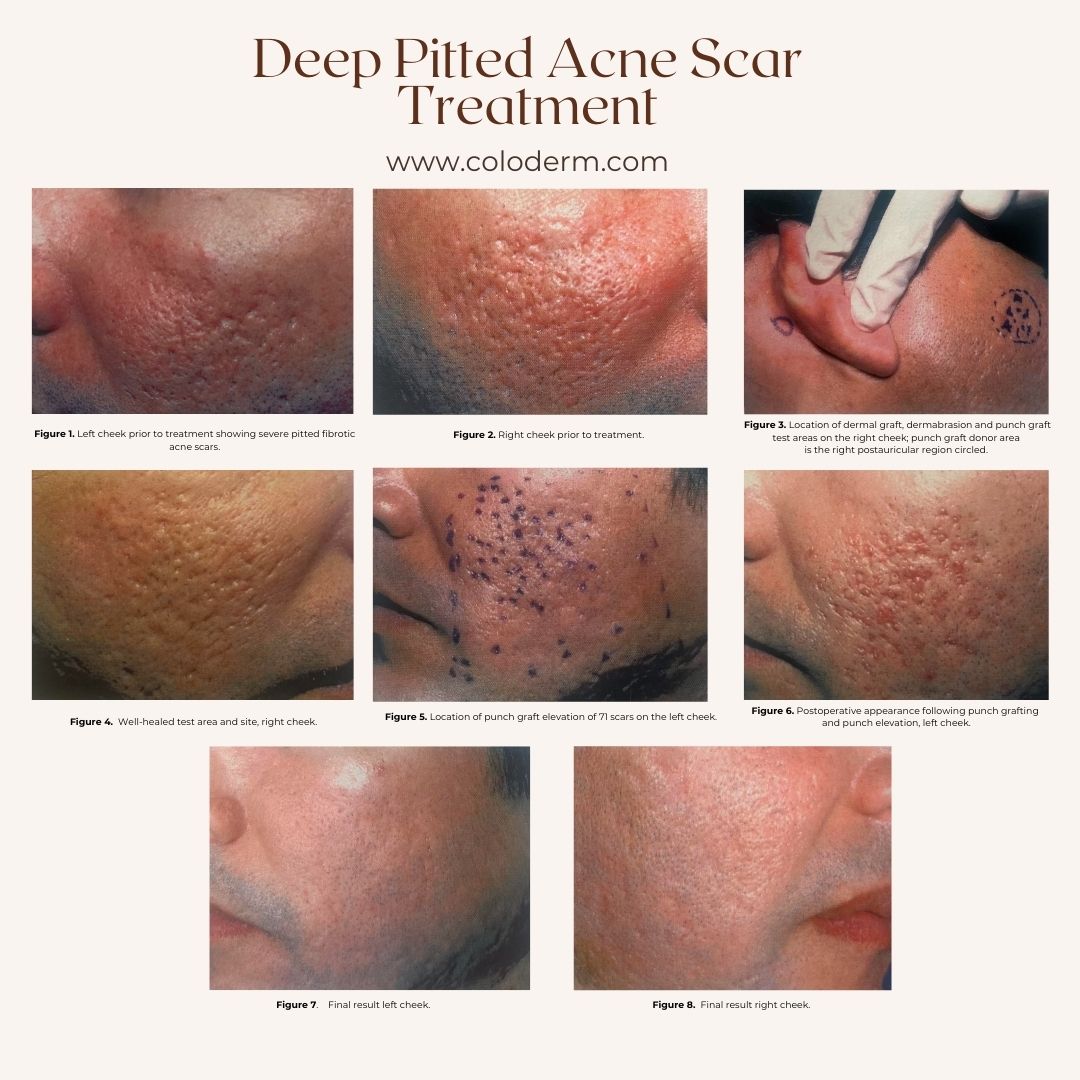
Treatment of Large Pores on the Nose and Central Face
Deep, large pores can be treated with the “cross technique”, whereby a tiny amount of trichloroacetic acid is pierced into each pore with a toothpick. Once the inflammation has subsided, the pores tend to shrink in size. The procedure may be done more than once. Dry ice cryotherapy can also be used for these pores. For more information and to schedule an appointment, call 303-744-1202!
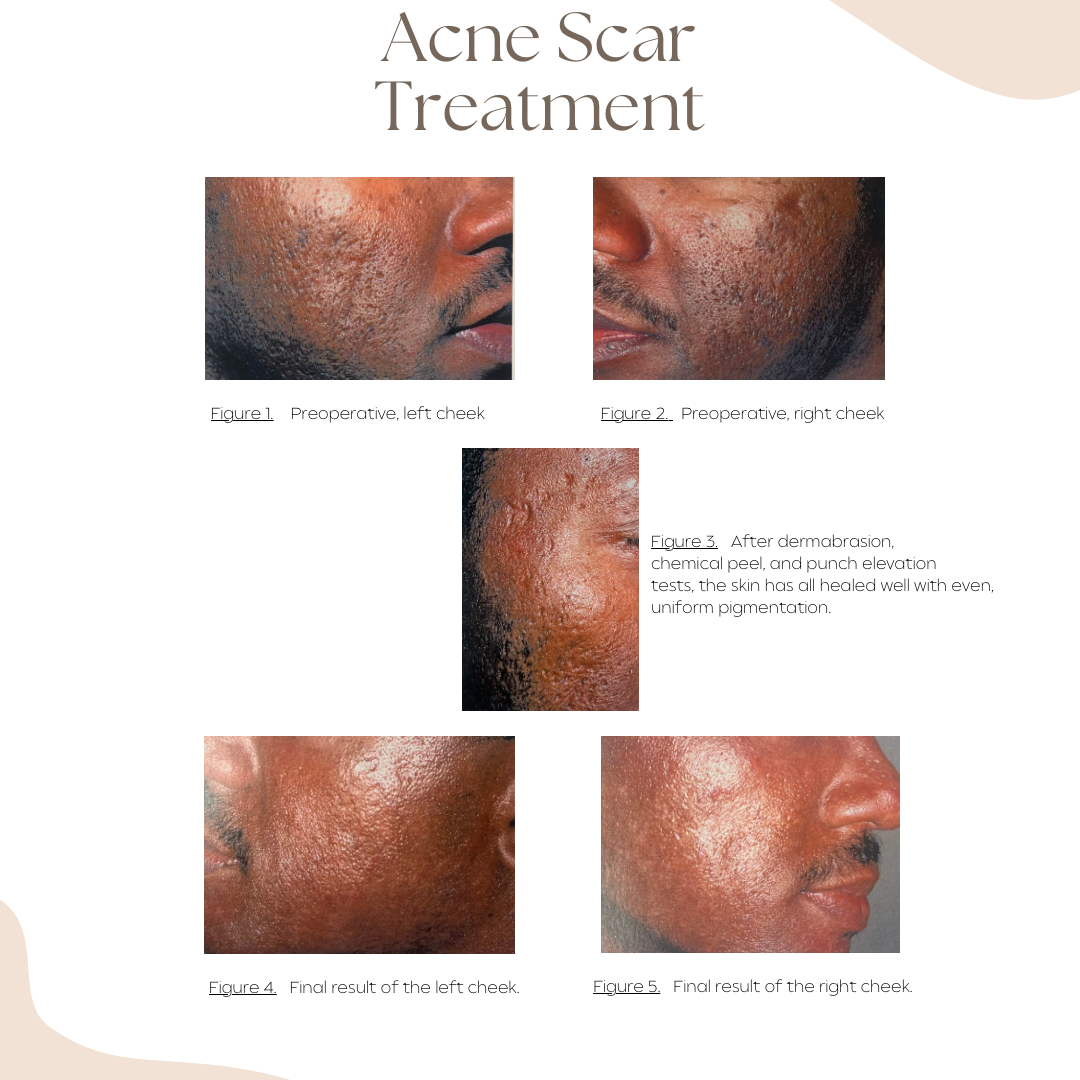
Types of Acne Scars
“Large Pores” – Most commonly seen on the nose, glabella, and cheeks
Fibrotic Scars – Firm, 2-4 mm scars containing scar tissue
Soft, Depressed Scars – 3-6 mm seen on cheeks, forehead, chin. These sometimes coalesce to form undulating scars.
Violaceous Scars – Red – purple due to underlying blood vessels
Hyperpigmented Scars – In individuals with darker complexions
Excoriated Scars – Due to picking (scratching acne lesions)
Hypertrophic Scars – Containing an excess buildup of scar tissue
Why Mohs Treatment of Skin Cancers?
To Whom It May Concern:
I am a 75 year old woman who grew up in Florida, basking in the wonderful sunshine for the first 18 years of my life, swimming on the high-school team, and loving the ocean and the beach. We never heard of “sunscreen”.
Now I live in Colorado, but ten years ago I bought a condo in Florida on the East Coast and once again began basking in the sunshine, and “living” on the beach and in the ocean, again without “sunscreen” (my favorite lotion was the Hawaiian darkening oil). But now I have numerous skin cancers, so what am I doing about them?
I am allowing Dr. Swinehart to remove them by Mohs treatment.
I have had four people that I know personally, die from skin cancer. It is very sad to hear the story of the 31 year old woman who left a wonderful caring husband, and five young children. It is very sad to see a young man that swam on the high school team with me, die and leave his wife and grandchildren at 63 years old. It is very sad to see the young sales lady at my favorite boutique in the little town in Florida, die leaving her husband, never having children yet. It is very sad to hear of the 40 something year old man who merely thought he had back trouble, die leaving his wife and three children. These are each people whose last two years of life or less were filled with horrible pain, secondary illnesses caused by chemotherapy and radiation, and a life that was hopeless and horrible. These four cases that I am personally connected to died because they were either misdiagnosed or because they waited too long to do anything about their skin cancer.
So why ignore it or wait. If you know that you have a skin cancer, and need the Mohs treatment, get it done as soon as possible. I have had five done, and am expecting as I write this letter to have another one done. There really is nothing to it; some local anesthetic, pleasant music, a few stitches, a bandaid, and later a stitch removal. With the first two, the scars have completely disappeared, and the next three are fading as time passes.
Why wait? You have nothing to loose, but your life!
Scheduling
Need a same-week dermatology appointment? Tired of waiting 6 weeks just to see a physician assistant? We will do our best to see you ASAP. Colorado Dermatology Center (303) 744-1202
Acne Scars
Treatment of Acne Scars
First we must treat and clear up the acne itself. Then scars and red marks can be improved by these 10 steps:
-Dry Ice Cryotherapy
-Peels
-Microdermabrasion
-Tretinoin
-Subcision
-Punch Grafting
-Punch Elevation
-Cross Technique
-Dermal Grafting
-Dermabrasion
Call us today at (303) 744-1202
Scabies
Scabies is characterized by intense itching, particularly at night, and the appearance of a rash with small red bumps or blisters. It is caused by tiny burrowing mites and can spread easily through close physical contact, making awareness and prevention essential. Scabies can be easily treated with topical creams or pills if necessary. For treatment of scabies or any other rash schedule an appointment with Dr. Swinehart at Colorado Dermatology Center (303) 744-1202
Atopic Dermatitis – Eczema
Atopic dermatitis, commonly known as eczema is a chronic skin condition affecting millions of people worldwide. People with eczema usually experience intense itching, often worsening at night, red, inflamed patches of skin, dry, scaly skin that may crack or bleed, and thickened skin due to chronic scratching. It often begins in childhood but can persist into adulthood, affecting quality of life. Do you have eczema? Schedule your consultation with Dr. Swinehart to be seen and go over different treatment options today! (303) 744-1202
Skin Checks
Skin cancer is one of the most common types of cancer, with one in five Americans developing it by age 70, according to the American Academy of Dermatology. Routine skin checks are essential for early detection and treatment.
During a skin check, you’ll change into a gown while Dr. Swinehart examines your skin for changes in moles, performs biopsies if needed, or uses liquid nitrogen to treat pre-cancerous lesions. You’ll also receive tailored advice on sun protection and skincare.
Don’t wait—call us at (303) 744-1202 to schedule your skin check today.
Female Hair Loss
What causes it? And what can I do about it? Some men may be ‘ok’ with it, but it’s of course very distressing to a woman, at any age. Various causes include hormones, heredity, and alopecia areata. There are a variety of possible therapies, including Minoxidil, Estrogen, Spironolactone, and hair transplants. Call us at (303) 744-1202 today to schedule a consultation.
Vitiligo
Do you have Vitiligo- (loss of pigmentation) on 10% or less, on your face and body? The Colorado Medical Research Center is conducting a clinical trial, with an experimental gel. For more information call our research coordinator Mickey at (303) 744- 7000.
Do you have Vitiligo?
Do you have Vitiligo- (loss of pigmentation) on 10% or less, on your face and body? The Colorado Medical Research Center is conducting a clinical trial, with an experimental gel. For more information call our research coordinator Mickey at (303) 744- 7000.
Dry Ice Cryotherapy
Dry Ice Cryotherapy is a technique used to treat acne and acne scars by cleansing the skin, reducing acne causing bacteria, soothing inflammation, and reducing comodones. This treatment is effective at unclogging pores and reducing the appearance of acne scars after several treatments. The antibacterial and anti-inflammatory properties along with the mild exfoliating effect offered by the dry ice treatment makes it key to your acne regimen. Schedule a consultation with Dr. Swinehart today to be evaluated to be considered for treatment! (303) 744-1202
Vitiligo Clinical Research Study
Dr. Swinehart will soon be starting a new clinical research study with an investigational topical cream for treatment of vitiligo. For more information concerning the study, or to see if you might qualify, call the Colorado Medical Research Center at (303) 744-7000.
The Wonderful Fragrance ‘Elma’
Do you dream of a special sweet floral fragrance for those special occasions? ‘Elma’ has all of this, and more. We combine essential oils of Hawaiian Plumeria, gardenia, pikake, jasmine, rose, osmanthus (sweet olive) and vanilla for a most heavenly scent. If you are seen as a patient, please ask to try some on your skin! Call us at (303) 744-1202 to schedule your appointment today!

Female Pattern Hair Loss
Are you experiencing thinning hair? This is often seen after pregnancy, menopause, change in hormones, or due to heredity. Treatments include Minoxidil, Spironolactone, Estrogen, and even hair transplantation. Call us at (303) 744-1202 for a consultation!
10 Weeks to Healthy Skin
Would you like healthier, livelier, younger skin in only ten weeks? With a combination of facial beautification techniques, this goal is now attainable. Dr. Swinehart, a Board-certified dermatologist and dermatologic surgeon, member of the American Academy of Dermatology, and past president of the Colorado Dermatologic Society, has spent 20 years perfecting these techniques and 10 years formulating, testing, and perfecting the Regine cosmetic line. With just one visit per week you can chance your life forever!
Week 1.
Initially, a skin consultation will be scheduled with Dr. Swinehart. At this time, we will analyze your skin, and design your customized 10 week plan—just for you! You may begin use of a moisturizing cleanser, sunscreen, and moisturizer by Regine®. A microdermabrasion will be discussed with you and can be commenced if you desire.
Week 2.
At this point, we can perform test spots for chemical peeling, dermasanding, or dermabrasion, and/or laser peels. You may also begin Regine® glycolic cream and may also need separately to start a retinoic acid cream or gel for your sun damaged skin. Another microdermabrasion may be preformed.
Week 3.
A Jessner’s peel or microdermabrasion will be performed, causing gentle exfoliation that lasts 1-2 days. The Jessner’s peel is often called the “model’s peel”. You will also test the Regine® powder, foundation, an/or concealer for your facial lines and blemishes, to find your exact color shade.
Week 4.
At this point you will begin a custom designed retinoic acid-glycolic acid-citric acid combination cream for more extensive sun damaged skin. You will continue use of your sunscreen. Also, vascular laser therapy can be performed at this visit for spider veins of the face.
Week 5.
An alpha-hydroxy acid peel or microdermabrasion will be performed at this time. This will cause mild redness and peeling lasting 1-2 days followed by gentle exfoliation.
Week 6.
Botox® can be injected into the lines on the forehead, glabella, and crow’s feet. The effects of this treatment last for 6-8 months. Collagen can be administered for finer facial lines.
Week 7.
The preoperative visit for your facial resurfacing or laser peel, as well as other procedures, will be performed at this time. Photographs, lab work, and pre and post op instructions will be given and all of your questions will be answered.
Week 8.
At this point, you will stop aspirin, and start your preoperative medications. You will continue using your retinoic-glycolic cream right up to the time of the procedure.
Week 9.
Therapy for your wrinkles, facial lines, and scars will be performed by laser, dermasanding or chemical peeling. At this point also, you may receive a upper lid “eye lift” (blepharoplasty) for excess eye skin, liposuction of the neck, and dermal grafting for deep scars or deep facial lines on the face.
Week 10.
We will see you again in the office. You will restart your sunscreen, and continue utilizing your concealer and foundation therapy. Finally, treat yourself or your significant other to the wonderful tropical floral Elma® and Florene® fragrances by Regine!
Neck Lift
Are your saggy neck and jowls starting to look like your Thanksgiving turkey (when it was still alive)? We have a solution for this! We first perform tumescent liposuction with local anesthesia in the office, followed by a tightening procedure if needed. Call us today at (303) 744-1202 to schedule a consultation!
Deep Facial Wrinkles
What about the really large facial folds and creases too deep to treat with a laser or peel? You need to first fill up the deep valleys before smoothing the skin. Fillers with hyaluronic acid dissipate with time. However, dermal grafts, using your own dermal tissue, are permanent. Dr. Swinehart is an expert in this technique, having performed many over the last 30 years. Call us for a consultation at (303) 744-1202!

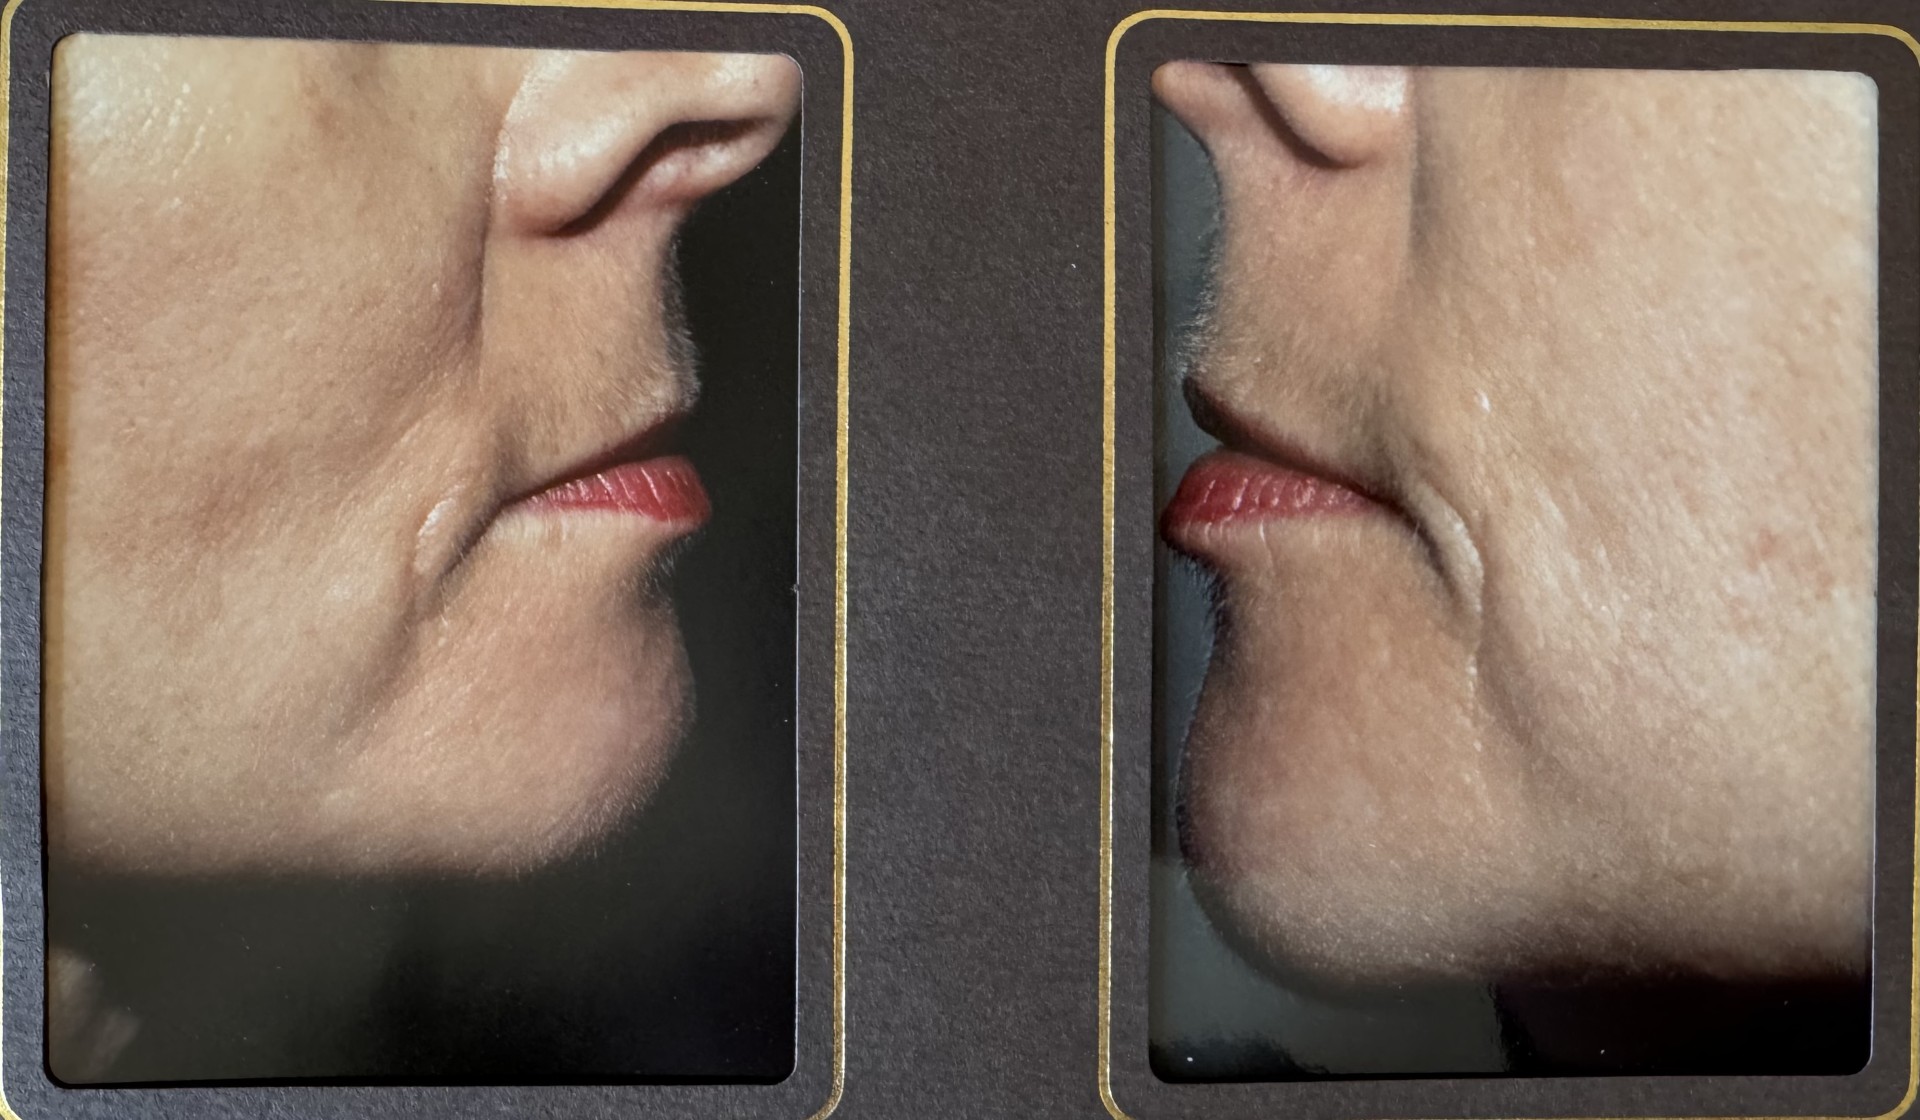
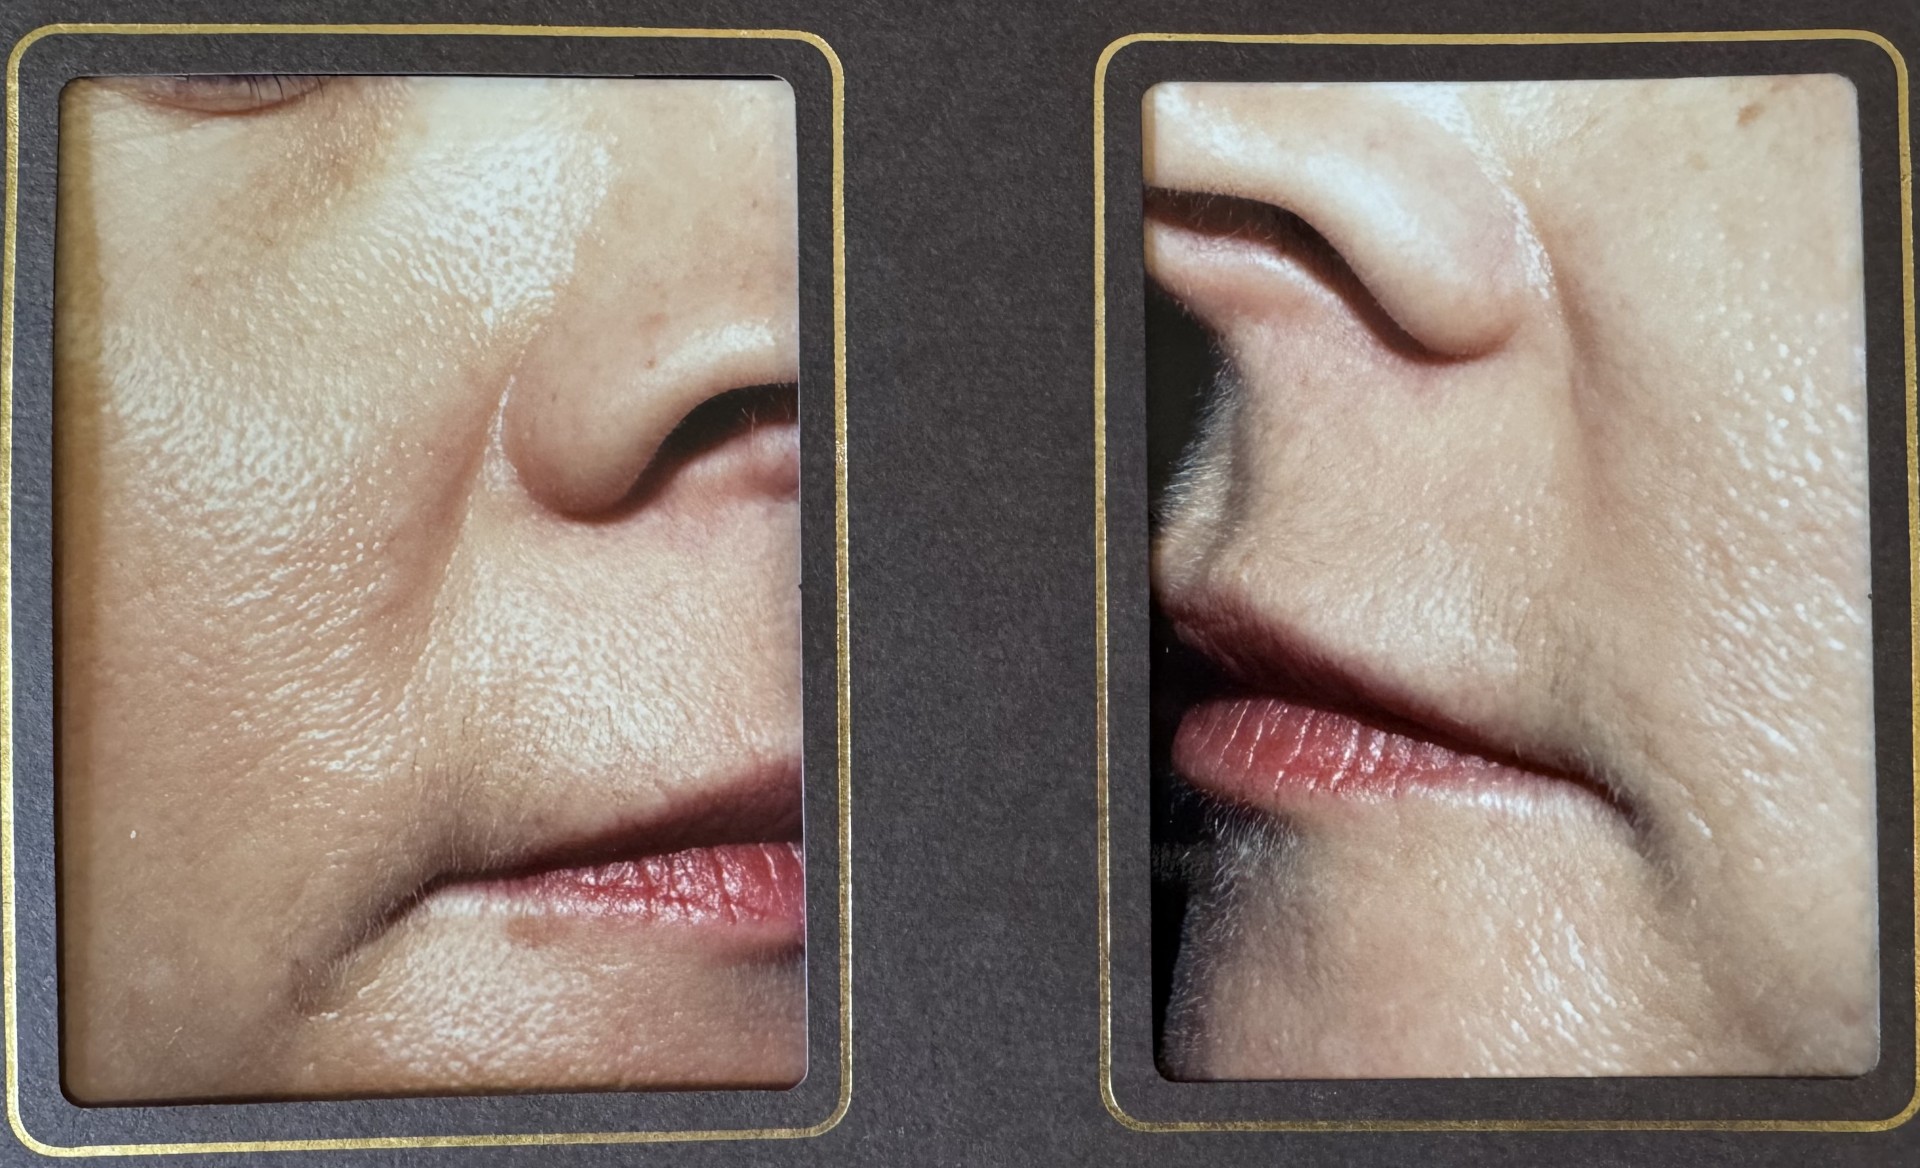
Do you have baggy or saggy upper eyelids?
This excess upper eyelid skin is usually a combination of loose/lax skin and small fat pads. Using a cosmetic procedure called a blepharoplasty, two small parallel incisions are made on both upper lids. The excess skin and fat are excised and small sutures are placed. This procedure is performed in the office under local anesthesia. You can go home that day and resume your normal activities! Call us for a consultation at (303) 744-1202!
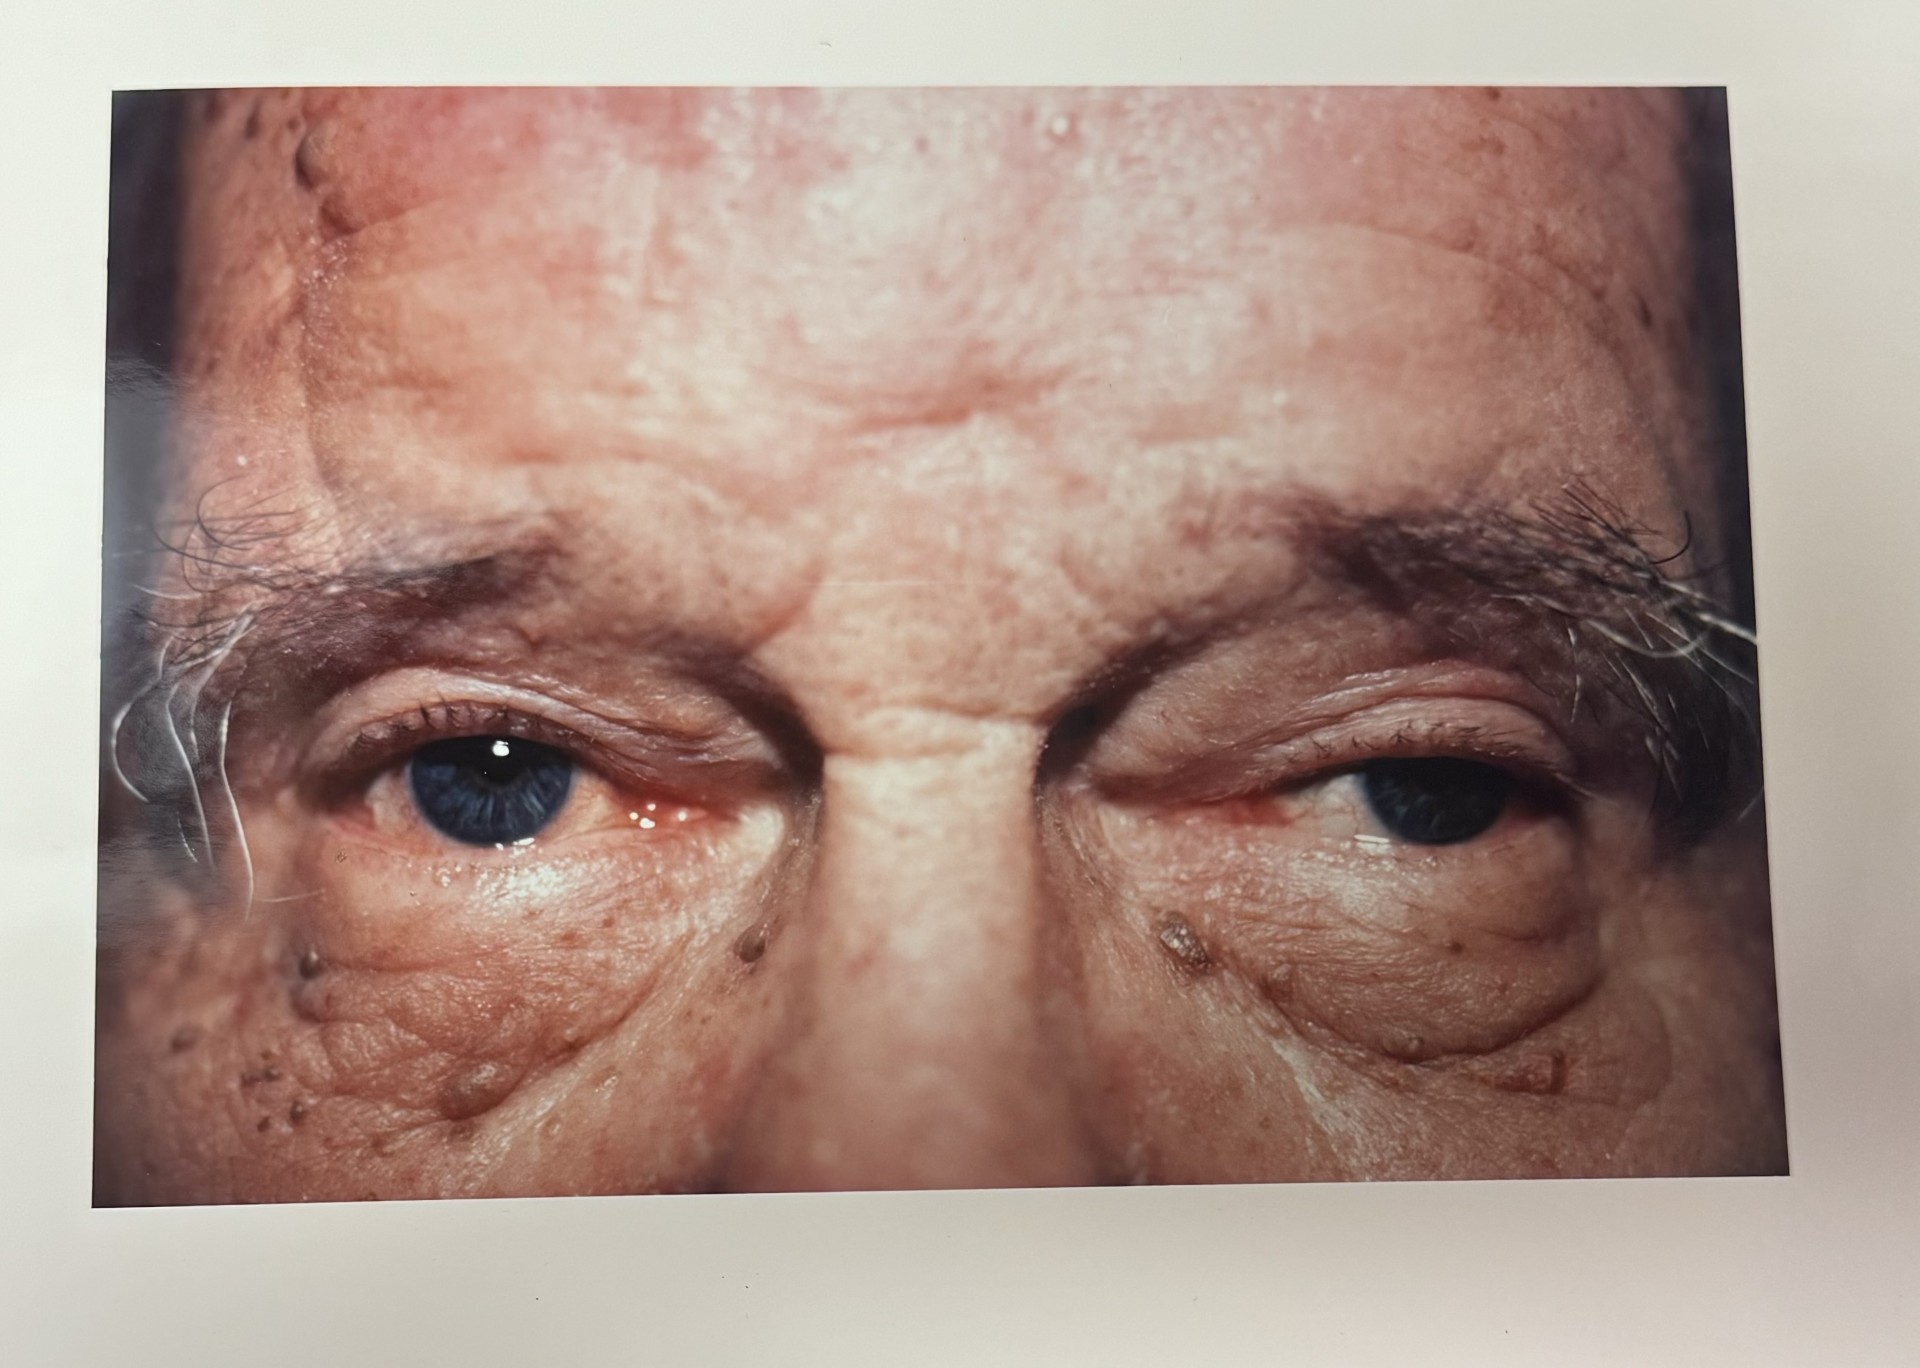
Hair Loss
Do injections of stem cells or platelet rich plasma actually grow hair? We’ll let you be the judge on those. However, the two medications approved by the FDA are minoxidil and finasteride. And hair transplantation using your own donor hair to create a new hair line and thicken the frontal scalp has been performed. Successfully for over 80 years. Call Dr. Swinehart to schedule a consultation today! (303) 744-1202
Wrinkles Away!
- For sun damage, hands & arms: superficial abrasion, Jessner’s & Salicylic Acid
- For Finer Facial Lines: Tretinoin, Jessner’s, TCA & Glycolic Acid
- For Deeper Wrinkles: Succession, Dermal Grafting, and Dermabrasion
- For Baggy Upper Eyelids: Blepharoplasty
Call us today at (303) 744-1202 for a consultation!
Blepharoplasty
Today Dr. Swinehart performed a bilateral upper lid blepharoplasty, in which excess skin and fat are removed from the upper eyelids, decreasing the wrinkles, drooping and bulging of the eyelid skin. This cosmetic procedure is performed under local anesthesia in the office, resulting in minimal downtime. For a consultation, call us at (303) 744- 1202!
Hair Transplant
Dr. Swinehart performed a large hair transplant this week. This was this patient’s 5th session over the course of 40 years, and he would be bald otherwise. Dr. Swinehart used 1, 2, and 3 follicular unit grafts to the hairline and anterior crown of the scalp to create a fuller appearance. Would you like to have more hair up front? Call us today at (303) 744-1202 to schedule your consultation.
Outreach Clinics
Dr. Swinehart regularly participates in outreach clinics in La Junta, Colorado, and Goodland, Kansas. By participating in outreach clinics, Dr. Swinehart is bringing his expertise to different communities and ensuring that individuals in La Junta and Goodland have the opportunity to receive specialized care without having to travel far. Dr. Swinehart is at the La Junta office on the second Thursday and Friday of each month and at the Goodland office on the third Friday of each month. If you or someone you know is in the La Junta or Goodland area and would like to schedule an appointment during one of Dr. Swinehart’s outreach clinics, please contact our office at (303) 744-1202.
Doctor Patient Care
At Colorado Dermatology Center, we are committed to providing you with the best dermatological care, ensuring that your skin is not just healthy but beautiful. Unlike many practices where time with the doctor is limited or you only see a physician’s assistant, at Colorado Dermatology Center, we understand the importance of spending quality time with each patient. You can expect a minimum of a 20-minute appointment with Dr. Swinehart. This allows for a comprehensive assessment, thorough discussion of your concerns, and the development of a customized treatment plan tailored to your unique needs. Please call our office at (303) 744-1202 to be scheduled.
Male Pattern Hair Loss
Minoxidil or Finasteride not effective? That laser cap or laser comb didn’t grow hair? PRP or stem cell injections didn’t work for you? The definitive treatment for this condition is Follicular Unit Hair Transplantation. Dr. Swinehart has performed this technique for 30 years and was certified as a Fellow by the International Society for Hair Restoration Surgery. Call us today for a consultation (303) 744-1202!
Acne Scarring
Acne Scarring
Possible treatments include dry ice cryotherapy, microdermabrasion, and chemical peels. Lasers are not as effective since they only penetrate up to 100 microns deep (1/10th of a millimeter). Hyaluronic acid fillers don’t last more than a few months. Deeper scars can first be filled in with Dermal Grafting using your own tissue from under the skin behind your ear. The surface can then be planed with dermabrasion under local anesthesia. Call us at (303) 744-1202 to schedule your consultation today!
Excessive Sweating
Do you suffer from excessive underarm sweating? Possible solutions include: aluminum chloride 20%, Qbrexa pads, Robinul, Botox, or Microwave Ultrasound. However, if those are not effective, the sweat glands can be suctioned out directly under local anesthesia with the Tumescent Technique. This therapy has proven to be effective over the past 30 years for reducing underarm sweating, known as hyperhidrosis. For a consult call us at (303) 744-1202!